How to Memorize the Cranial Nerves Without Losing Your Mind
I spent three years in med school listening to professors drone on about olfactory receptors and optic chiasms before I finally figured out a system that actually stuck. The standard mnemonic everyone uses — Oh Oh Oh To Touch And Feel Very Good Velvet — covers all twelve nerves but tells you absolutely nothing about which ones do what. That mnemonic gets you through the first exam and then you blank during your clinical rotations when a patient actually presents with a weird deficit. Here is how I actually learned them and how I teach it now to my residents.
Cranial Nerves In Order: The Functional Approach
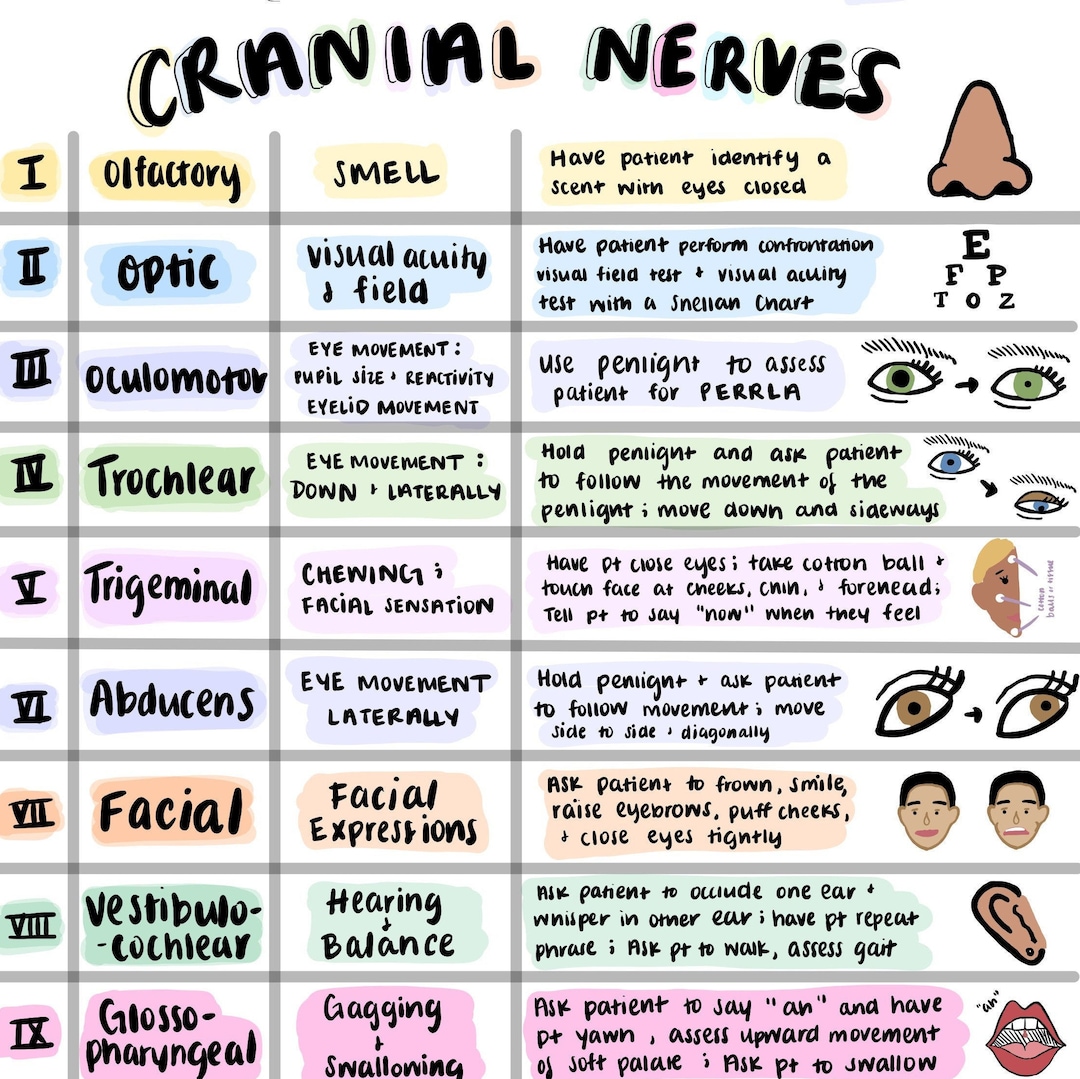
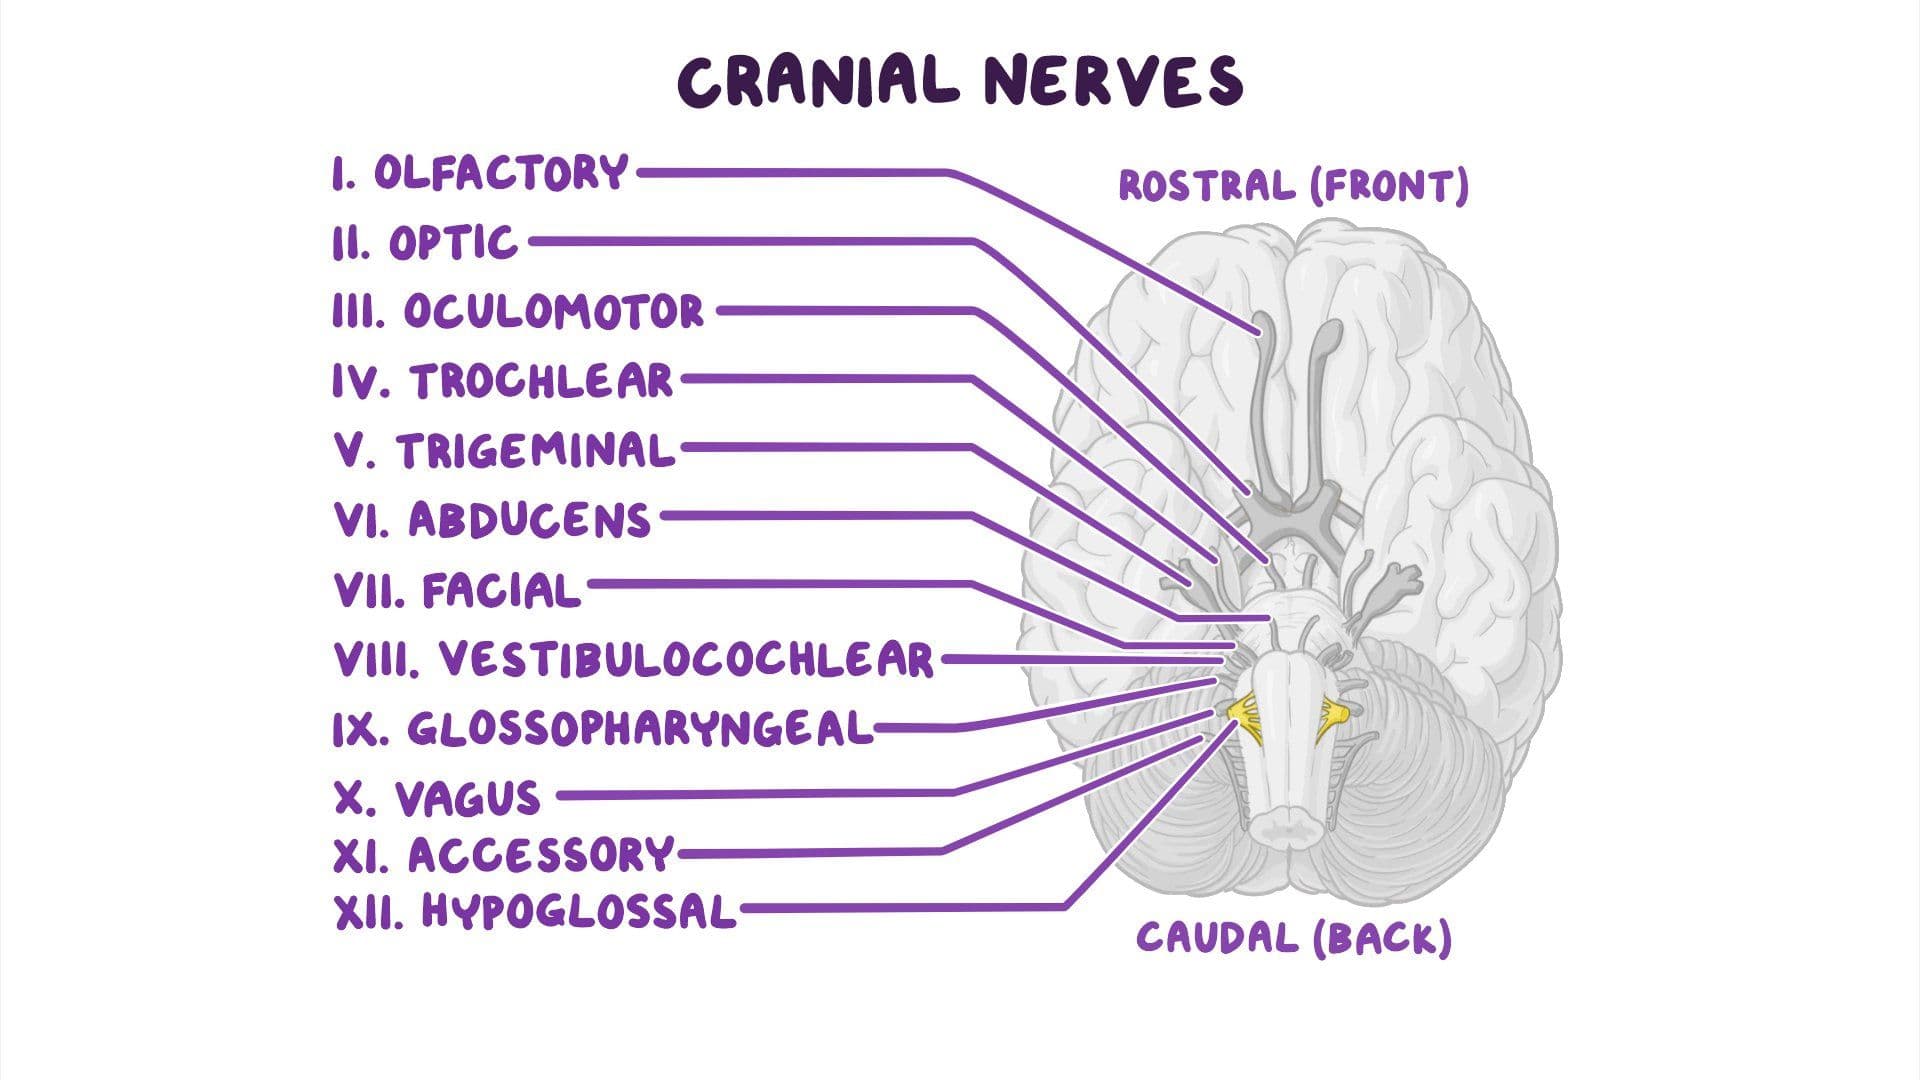
Start with the Roman numerals and the one-word job description. I prefer grouping them by function rather than memorizing a list. The sensory-only nerves are I, II, and VIII. The motor-only nerves are III, IV, VI, XI, and XII. The mixed bag — the ones that do both sensory and motor — are V, VII, IX, and X. If you know the functional categories first, the individual nerves make sense instead of being arbitrary labels. Olfactory is number one. It goes through the cribriform plate and connects directly to the piriform cortex without synapsing in the thalamus like every other sensory pathway. I had a trauma case where a patient fell off a ladder and the lateral rotation of the head tore those tiny filaments. The tell was not loss of smell itself — that is obvious — but anosmia on one side with intact contralateral olfaction, which pointed right to a unilateral fracture through the cribriform plate. CT missed it initially because the bleed was subtle. We confirmed it clinically when they could not detect ammonia on the left nostril alone. Optic nerve is two. This one gets tested with a fundoscopic exam and visual field confrontation. The pitfall here is assuming normal acuity means normal function. A patient can read the 20/20 line and still have a bitemporal hemianopsia from a pituitary macroadenoma compressing the chiasm. I learned this the hard way when a patient complained of headaches and I cleared her vision screening. Two weeks later she came back unable to see people approaching from either side. The MRI showed a 3cm lesion. This is why visual fields are not optional — they take thirty seconds and they catch things the acuity chart never will.
Trigeminal is five and it has three divisions you need to map clinically. V1 is ophthalmic, V2 is maxillary, V3 is mandibular. The motor component of V3 innervates the muscles of mastication. I test jaw strength by having the patient clench while I palpate the temporalis and masseter, then ask them to open against resistance. Weakness here points to V3 specifically, not the whole trigeminal system. Peripheral lesions spare the pupillary light reflex because that is parasympathetic running with V1, not the sensory branches themselves. Facial nerve is seven. The most common facial palsy I see is Bell's palsy, but you must distinguish central from peripheral lesions immediately. In a central stroke, the forehead is spared because the upper face receives bilateral cortical input. In Bell's, you cannot wrinkle the entire ipsilateral forehead. I use the ability to close the eye as the critical differentiator — a patient who cannot close the eye on the affected side has a peripheral lesion and needs eye protection to prevent corneal ulceration. This usually cuts the process down from finding the answer in two minutes instead of waiting for imaging results that will just confirm clinical suspicion. Glossopharyngeal and vagus are nine and ten. These two get tested together with the gag reflex and voice quality. A dangling uvula points to vagus weakness on that side. I had a post-thyroidectomy patient who developed hoarseness and aspiration. The recurrent laryngeal branch of the vagus was nicked during the dissection. Checking for vocal cord paralysis with bedside laryngoscopy caught it before she aspirated pneumonia. This usually saves a two-day workup because you can see the immobile cord directly.
Get the Full Details
Hypoglossal is twelve. Test it by having the patient stick out the tongue and push it against each cheek while you palpate. Deviation toward the side of the lesion indicates lower motor neuron damage. The classic pitfall is confusing a central upper motor neuron lesion with a peripheral one — in a stroke affecting the corticobulbar tract, the tongue deviates away from the lesion side because the intact contralateral generator pushes it that direction. I explain this to students by having them push their own tongues against resistance and feel the difference between voluntary and forced movement.
The Mnemonic Problem and What Works Instead
The traditional mnemonics are fine for passing the first neuroanatomy quiz but they create a false sense of mastery. You can recite all twelve nerves in order and still not recognize a Horner's syndrome when you see one. I stopped using mnemonics after my third year and started drawing the brainstem cross-sections instead. Understanding where each nerve exits the brainstem makes the clinical localization automatic. Dorsal roots carry sensory information. Ventral roots carry motor. The cranial nerves follow the same principle but the brainstem organization adds complexity. Each nerve has a specific nucleus cluster you can trace back to its functional type. Motor nuclei sit more medially. Sensory nuclei form the laminar alar plate laterally. If you know this anatomical principle, you can predict where a lesion will hit based on the symptoms alone. The vestibulocochlear nerve is eight and it splits into vestibular and cochlear components. Vertigo points to vestibular involvement. Hearing loss points to cochlear. I had a patient with acoustic neuroma who presented with unilateral tinnitus and imbalance but preserved hearing. The tumor was growing along the vestibular division and compressing the cochlear nerve slowly enough that hearing adapted. An MRI through the internal auditory canal showed a 1.5cm lesion. This progression pattern is why pure tone audiometry alone misses early tumors — you need the MRI to see the actual compression.
When the Standard Approach Fails
Memorizing nerve names and numbers will not help you when a patient presents with overlapping deficits. A cavernous sinus thrombosis can affect III, IV, V1, V2, and VI simultaneously. The key is recognizing the anatomical territory rather than listing individual nerves. I use a checklist approach: which extraocular muscles are weak, where is the sensory loss, is the pupil involved, can the patient elevate the soft palate. The pattern tells you the location faster than any textbook definition. The limitation of this approach is that some lesions do not follow clean anatomical boundaries. Multiple sclerosis plaques can hit any part of the pathway. Ischemic strokes in the brainstem can create crossed findings where the face is affected on one side and the body on the other. I learned to map the deficit to the vascular territory rather than the nerve name. This usually cuts the diagnostic uncertainty from days to hours when you know the anterior circulation supplies the upper brainstem and the posterior circulation supplies the lower structures. If you want a quick reference, the standard neuroanatomy textbooks cover all the nuclei and pathways in detail. For clinical localization practice, I recommend working through the case studies in Bradley and Jacoby's Neurology textbook. The bedside approach beats the mnemonic approach every time you encounter a real patient who does not fit the textbook pattern.


