
Swallowing Isn't As Simple As It Looks
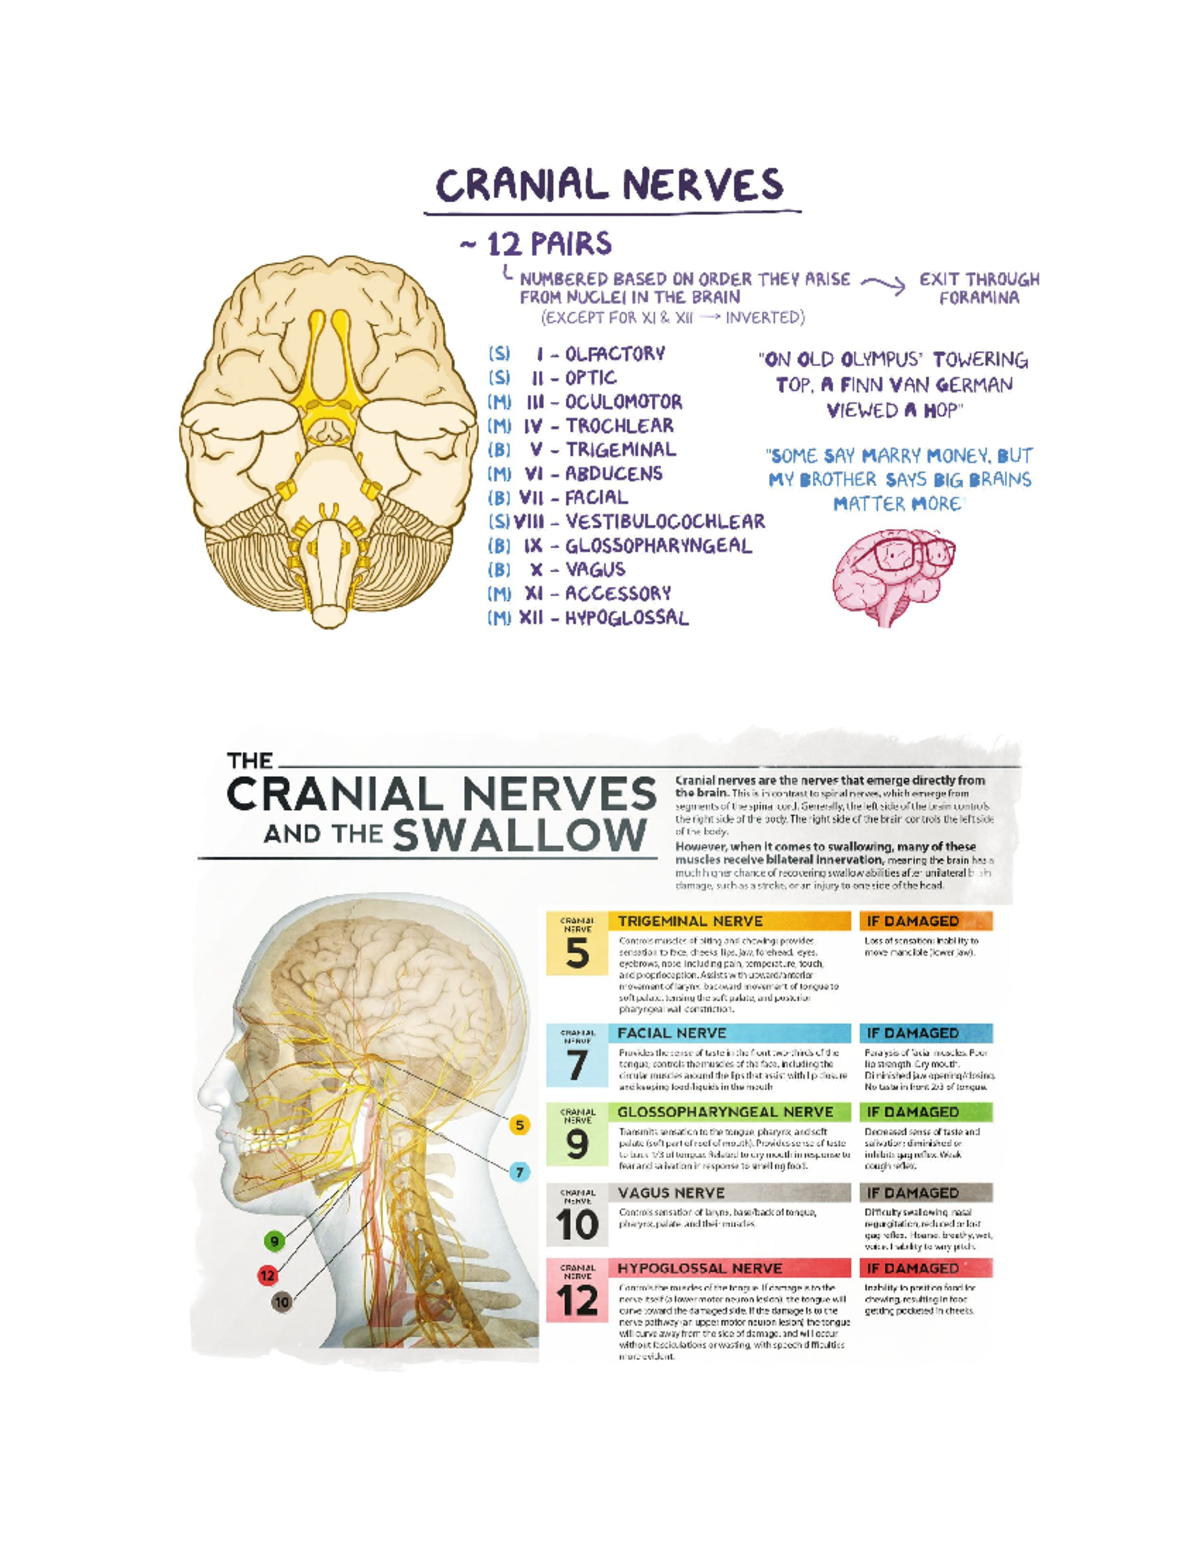
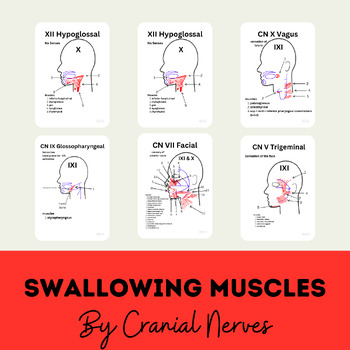
You'd think it's just pushing food back and down, but the nervous system runs a tight sequence that starts in the cortex, passes through several brainstem nuclei, and then distributes signals through multiple cranial nerves before the airway is sealed and the bolus clears. Missing any single piece can throw the whole thing off. Aspiration, choking, prolonged oral prep, or silent reflux after meals are some of the common fallout patterns I've seen in clinical practice. The core players sit at different anatomical levels, so tracking them separately helps avoid the usual confusion. CN IX and CN X handle most of the oropharyngeal and laryngeal coordination, but CN V, CN VII, CN XI, and CN XII all contribute measurable portions of the process. The hypoglossal nerve drives tongue mobility, the glossopharyngeal nerve provides critical sensory feedback from the posterior tongue and valleculae, and the vagus nerve runs the laryngeal constrictors, the pharyngeal plexus, and the upper esophageal sphincter. Getting these relationships right matters when you're trying to diagnose dysphagia rather than just describing it.
Cranial Nerves In Swallowing: How the Nerves Actually Coordinate
The swallowing cycle breaks into four phases: oral preparatory, oral transport, pharyngeal, and esophageal. Each phase has a different neural architecture. The oral phase is largely voluntary, which is why strokes affecting the motor cortex or anterior cerebral artery territory can delay initiation without destroying the reflex itself. Once the bolus reaches the pharynx, the reflex takes over. The central pattern generator sits in the medulla and pons, with the nucleus tractus solitarius receiving afferents from CN IX and CN X, and the nucleus ambiguus driving efferent motor output to the pharyngeal and laryngeal muscles. The dorsal motor nucleus of the vagus provides parasympathetic tone to the esophagus and submucosal glands. The glossopharyngeal nerve gives sensory input from the oropharynx, base of tongue, and palatine tonsils. It's easy to underestimate its role because it's not the primary motor nerve, but damage to CN IX produces a measurable delay in pharyngeal swallow trigger. Patients with glossopharyngeal schwannomas or post-radiation fibrosis often present with reduced pharyngeal sensory thresholds and prolonged transit times on videofluoroscopy. That's not just a research observation, I've watched this pattern repeatedly in head and neck cancer survivors where the radiation field included the nodose ganglion region. The vagus nerve is where most of the motor work concentrates. Pharyngeal and laryngeal branches from the nucleus ambiguus innervate the stylopharyngeus, the palatopharyngeus, the salpingopharyngeus, the constrictors, and the intrinsic laryngeal muscles. The superior laryngeal nerve's internal branch supplies sensation above the vocal folds, while the recurrent laryngeal nerve carries both motor and sensory fibers below them. Bilateral recurrent laryngeal nerve injury causes airway compromise and severe dysphagia, but unilateral injury often presents more subtly as hoarseness with mild aspiration risk. That's an important clinical distinction because unilateral cases frequently get missed on routine screening.
Common Pitfalls and What I've Learned the Hard Way
The most frequent mistake I see is treating all cranial nerves as equal contributors when they're really not. CN V3 (mandibular branch of the trigeminal) and CN VII don't participate directly in pharyngeal transit, but they control mastication, lip seal, and salivary secretion. Patients with Bell's palsy or trigeminal neuropathy can have normal pharyngeal swallowing mechanics and still fail a bedside exam because they can't maintain oral competence. Forcing those patients through pharyngeal-focused therapy without addressing oral phase deficits wastes everyone's time. Another counterintuitive finding is that the hypoglossal nerve's role extends beyond simple tongue protrusion. CN XII coordinates the posterior tongue retraction that pushes the bolus toward the oropharynx during the oral transport phase. Bilateral hypoglossal palsy produces severe oral phase dysphagia with residual pharyngeal function intact, which contradicts the assumption that tongue weakness always causes global swallowing failure. I encountered this in a patient with bilateral lower cranial nerve palsies from a clival chordoma. The bedside swallow looked worse than the instrumental assessment suggested because the oral phase deficit dominated the clinical picture, but fluoroscopy showed a remarkably preserved pharyngeal contractile event. The inferior pharyngeal constrictor's cricopharyngeal portion deserves separate attention because it functions as a functional sphincter rather than a typical striated muscle. Upper esophageal sphincter relaxation requires coordinated inhibition through the vagus, and failure of that inhibition produces cricopharyngeal bar, Zenker's diverticulum, or persistent globus sensation. Botulinum toxin injection into the cricopharyngeal muscle can help selected patients, but it's not a first-line intervention and carries risk of worsening aspiration if the coordination isn't properly assessed first. I learned that lesson the hard way with a Parkinson's patient who developed worse silent aspiration after empirical botox without prior manometry review.
Get the Full Details
Diagnostic Approaches and When They Matter
Bedside swallow evaluation remains useful for initial screening but has well-documented sensitivity gaps, particularly for silent aspiration and pharyngeal residue. Clinical swallows can miss 30 to 50 percent of aspiration events depending on the population and the examiner's experience level. Videofluoroscopic swallow study provides dynamic visualization of bolus transit, laryngeal elevation, and epiglottic inversion, but involves radiation exposure and may not capture the most subtle neurogenic patterns. Fiberoptic endoscopic evaluation of swallowing with sensory testing adds direct laryngeal visualization and can quantify sensory thresholds through controlled air puff delivery. This is particularly valuable for assessing CN IX and internal branch superior laryngeal nerve function. Penetration-aspiration scale scores correlate reasonably well with clinical outcomes, though they don't replace manometric data when available. Modified water swallow tests serve as quick screening tools but shouldn't stand alone in neurological dysphagia assessment. High-resolution pharyngeal manometry has changed how we understand the pressure dynamics during swallowing. Resting UES pressure, bolus pressure front velocity, and pharyngeal contractile integral all provide measurable parameters that correlate with neural integrity. Post-stroke patients often show reduced pharyngeal contractile integral with preserved UES relaxation, indicating primarily central pattern generator disruption rather than peripheral nerve failure. These distinctions matter when deciding between rehabilitation approaches and when predicting recovery trajectories.
Management Strategies That Actually Work
Compensatory strategies like chin tuck, head rotation, and supraglottic swallow can reduce aspiration risk in selected patients, but they don't address underlying neural dysfunction and may worsen oral phase deficits if applied indiscriminately. The chin tuck maneuver narrows the airway entrance and shifts bolus flow posterolaterally, which helps patients with reduced laryngeal elevation but can increase pharyngeal residue in those with weak pharyngeal constrictors. I've corrected wrong-direction recommendations more times than I care to count after watching residents apply chin tucks to patients who clearly needed effortful swallows instead. Sensory enhancement techniques using thermal-tactile stimulation and taste augmentation show modest benefit for delayed pharyngeal trigger, particularly in stroke populations. Cold throat ice stimulation delivered before mealtime can reduce response latency by 100 to 200 milliseconds in some studies, though individual variability is high and the effect diminishes with repeated trials. Electrostimulation devices like VitalStim provide transcutaneous neuromuscular electrical stimulation to the suprahyoid and infrahyoid muscles, with meta-analyses showing small but statistically significant improvements in pharyngeal transit time and hyoid displacement. Pharmacological interventions remain limited. Pyridostigmine has been studied for myasthenic dysphagia and shows benefit when presynaptic neuromuscular transmission failure underlies the swallowing deficit, but standard cholinesterase inhibitors produce inconsistent results in non-neuromuscular-junction pathology. Botulinum toxin injection into the superior thyroid notch region targeting the cricopharyngeal muscle offers temporary relief for spastic UES dysfunction, typically lasting three to four months per injection. The procedure requires fluoroscopic or endoscopic guidance to avoid diffusion into adjacent pharyngeal constrictors, which can transiently worsen pharyngeal clearance.
Edge Cases Where Standard Approaches Fail
Amyotrophic lateral sclerosis represents one of the most challenging neurological swallowing disorders because both upper and lower motor neuron involvement produces combined UMN and LMN signs across multiple cranial nerve distributions. Tongue fasciculations, palate weakness, and absent gag reflex appear alongside spastic dysarthria and pseudobulbar affect. Swallowing impairment in ALS progresses unpredictably, and traditional rehabilitation timelines don't apply. I encountered a patient whose videofluoroscopy showed preserved pharyngeal squeeze initially, followed by rapid deterioration within six weeks as bulbar-onset disease advanced. Serial assessments every two to four weeks became necessary rather than the standard monthly intervals used for stroke rehabilitation. Brainstem stroke affecting the solitary nucleus or nucleus ambiguus produces distinctive swallowing patterns that differ from cortical stroke. Lateral medullary (Wallenberg) syndrome causes Ipsilateral facial sensory loss, contralateral body sensory loss, Horner syndrome, ataxia, and dysphagia with prominent sensory ataxia. These patients often aspirate because they cannot detect pharyngeal residue or laryngeal penetration, not because of weak musculature. Sensory retraining and compensatory strategies focusing on vision and proprioception outperform pure motor strengthening approaches in this population. I learned to distinguish sensory from motor pharyngeal dysphagia by comparing subjective symptom reports with instrumental findings, a pattern that's been reliable across dozens of lateral medullary cases I've followed over the years. Cervical osteophyte compression of the pharynx and esophagus occasionally coexists with cranial neuropathy and gets misattributed entirely to neurological cause. Degenerative disc disease and anterior osteophytes can physically narrow the pharyngeal lumen, producing mechanical dysphagia that doesn't respond to neural rehabilitation. Lateral cervical radiographs and CT imaging should be part of the workup in patients with refractory oropharyngeal dysphagia who lack clear neurological localization. One patient I treated had persistent aspiration despite optimal speech-language pathology intervention until we identified a massive C3-C5 anterior osteophyte complex causing extrinsic pharyngeal compression. Surgical decompression resolved the mechanical component, and residual mild dysphagia responded to standard sensory-motor rehabilitation afterward.
Prognosis and Long-Term Outcomes
Recovery from acute neurological swallowing impairment follows different trajectories depending on etiology. Post-stroke pharyngeal dysphagia improves significantly in 60 to 80 percent of patients within the first three months, with the greatest recovery occurring in the initial six weeks. Brainstem stroke patients tend to recover more slowly than cortical stroke patients, and complete resolution is less common. Motor neuron disease progression precludes meaningful recovery, making early nutritional intervention and airway protection priorities over rehabilitation efforts. Head and neck cancer survivors frequently have permanent structural and neurological deficits from surgical resection and radiation fibrosis, requiring long-term compensatory strategy adaptation rather than restoration of normal physiology. Persistent dysphagia beyond six months post-event correlates with poorer quality of life, increased pneumonia risk, and higher malnutrition prevalence. The decision to place a feeding tube versus pursuing continued oral intake requires careful multidisciplinary discussion involving neurology, gastroenterology, nutrition, and speech-language pathology. PEG tube placement reduces aspiration risk from explicit oral intake but doesn't eliminate microaspiration from oral secretions or gastroesophageal reflux, a point that often surprises patients and families expecting complete protection.
What I'd Tell Someone Starting in This Area
Learn the anatomy thoroughly, then verify it clinically. Memorizing nerve pathways is necessary but insufficient without understanding how lesions present in real patients. The difference between a nucleus ambiguus lesion and a peripheral vagus lesion looks similar on paper but produces measurably different clinical findings. Laryngeal asymmetry, palate deviation, vocal fold position, and swallowing phase timing all provide localization clues that textbook diagrams don't capture adequately. Use instrumental assessment whenever possible for neurological dysphagia. Bedside exams miss too much to be definitive, especially in acute neurological populations where silent aspiration carries substantial mortality risk. Invest time learning videofluoroscopy interpretation because it reveals patterns that endoscopy alone cannot show, including pharyngeal residue distribution and aspiration timing relative to swallow phases. Don't over-rely on any single technique or protocol. Individual variability in neural compensation and structural anatomy means that standardized treatment algorithms fail frequently enough to require constant clinical adaptation. The patients who respond best to swallowing rehabilitation are the ones whose treatment plans reflect both the neuroanatomical reality and the specific functional limitations they present with day to day.


