Understanding the Basics
Craniosacral therapy for infants is a very gentle hands-on approach that works with the membranes and cerebrospinal fluid around the brain and spinal cord. The idea is simple enough: babies can carry tension from birth, and sometimes their cranial bones haven't quite settled into comfortable positions. Practitioners use extremely light touch — usually less than the weight of a nickel, about five grams of pressure — to help release restrictions in the craniosacral system. I've been doing this work for years, and the honest truth is that most parents come to it because their baby won't stop crying, won't latch properly, or seems stuck on one side. Those are the common entry points. But the therapy itself isn't magic, and it doesn't fix everything.
What Is Craniosacral Therapy For Infants
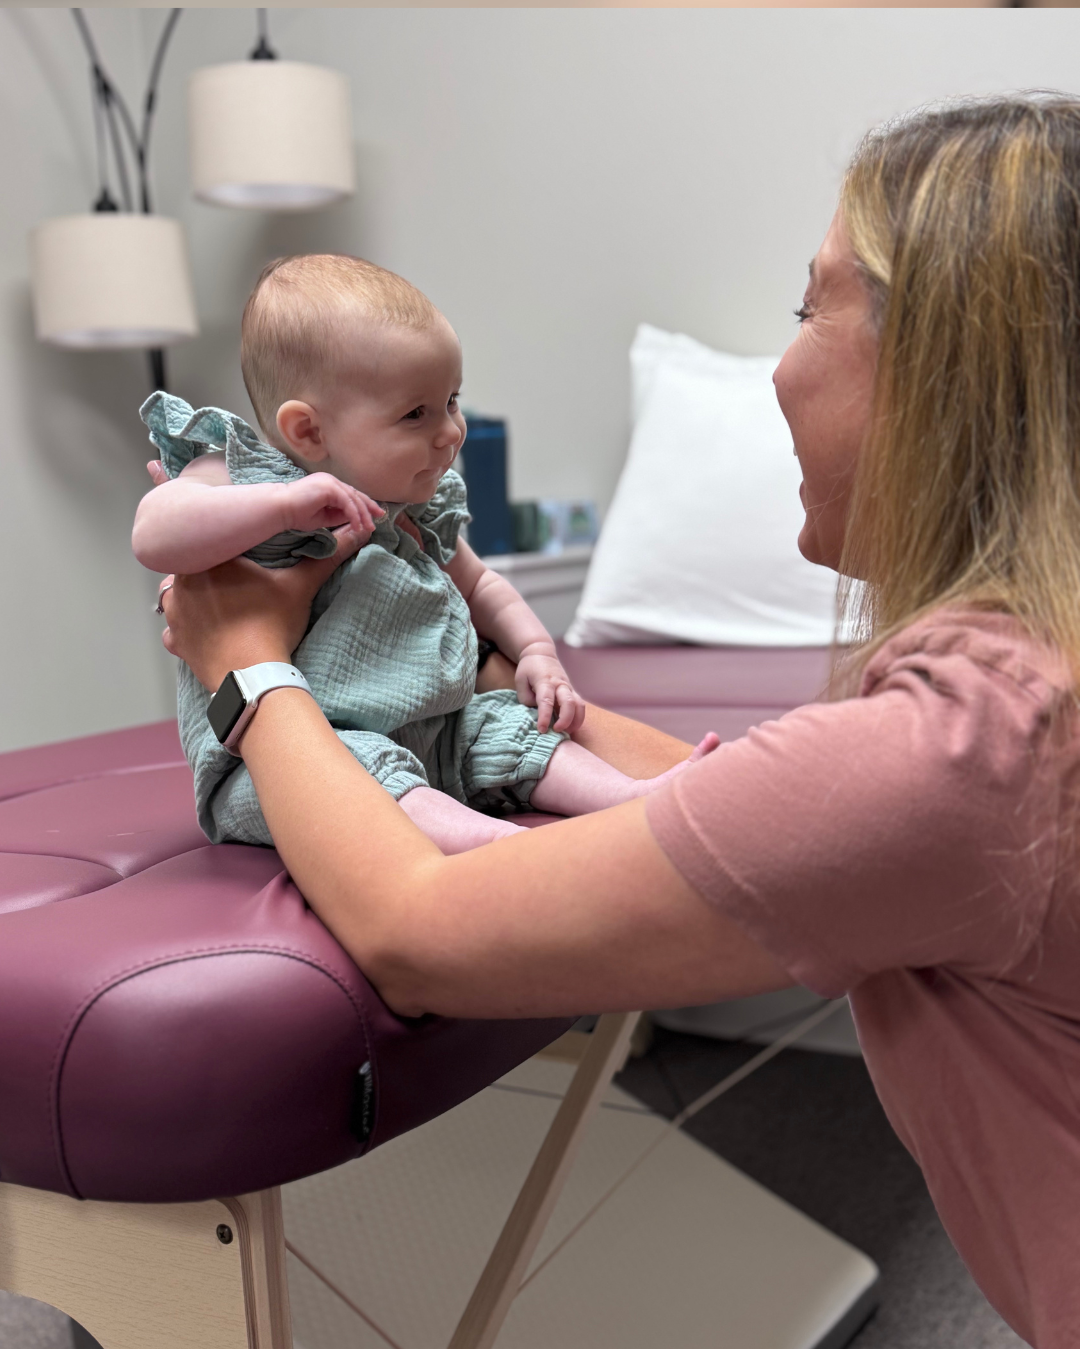
The technical definition involves the cranium, the sacrum, and the rhythmic fluctuation of cerebrospinal fluid. In practice, what it means is that a trained therapist places their hands on specific points around the baby's head, spine, and pelvis to detect and gently guide releases in the fascial connections between these structures. The session typically lasts between ten and twenty minutes. You'll usually see three to five sessions needed for a noticeable change in feeding, sleep, or fussiness patterns. The effects are cumulative, not instant. When I work with an infant, the room needs to be warm, quiet, and dimly lit. Babies are extremely sensitive to environmental stimuli, and if they're overwhelmed before I even begin, nothing I do will land properly. I lay the baby on a treatment table, usually on their back, and I let them settle for a few minutes before I touch them. That pause matters more than people realize. The technique starts at the feet. I hold the baby's ankles and apply minimal pressure, feeling for the rhythm of the craniosacral system. It's a subtle motion, somewhere between eight and twelve cycles per minute, and you develop a sense for it through repetition. From the feet, I move up through the legs, the pelvis, the sacrum, and finally the skull. Each area gets a few minutes of assessment and gentle hold.
The actual release happens through what we call indirect methods. I'm not pushing on anything. I'm supporting tissues in the direction of their ease and waiting for the body to do the work. A release feels like a subtle unwinding, a softening under my hands. The baby might yawn, sigh, or shift their legs. Sometimes nothing visible happens at all, and that's fine. One thing I want to be clear about: the cranial bones in newborns are meant to overlap. That's called molding, and it's normal. What we're looking for isn't perfect symmetry — it's the absence of restriction. A baby who was delivered with a vacuum or forceps will often carry more tension in specific areas of the skull, and those are the areas I'll spend more time on. But even then, I'm not trying to "fix" the bones. I'm facilitating the body's own self-corrective mechanisms.
Get the Full Details

A Real Complication I've Encountered
Here's a specific case that taught me something important. I had a six-week-old infant whose mother brought him in because he refused to breastfeed on the left side. Every attempt resulted in immediate arching and screaming. We did two sessions addressing the left temporal bone and the left side of the occiput, and there was marginal improvement but nothing dramatic. On the third visit, I noticed something I should have caught earlier. The baby had a significant tightness in the sternocleidomastoid muscle on the left side, which is a classic sign of congenital muscular torticollis. That tight neck muscle was pulling on the skull base and creating secondary restrictions that no amount of cranial work was going to resolve on its own. I stopped the craniosacral protocol and referred the mother to a pediatric physical therapist. After three weeks of PT, the breastfeeding issue resolved almost entirely. The craniosacral work had helped a little, but it wasn't the primary problem. The takeaway here is that you need to know when craniosacral therapy isn't the right tool. Torticollis, GERD, tongue-tie, and ear infections all present with symptoms that can look identical to what a parent assumes is a cranial restriction. Misdiagnosing any of those can delay proper treatment by weeks.
What This Therapy Cannot Do
I need to be straightforward about the limitations. Craniosacral therapy will not treat autism, ADHD, colic as a standalone condition, or any structural brain abnormality. There is a significant amount of pseudoscientific claim-making around this modality, and practitioners who tell parents it can cure neurological disorders are either ignorant or dishonest. The evidence base is thin. Most published studies are small, methodologically weak, or sponsored by training organizations. A 2018 systematic review in the journal of Alternative and Complementary Medicine concluded that while some data suggest benefit for colic and breastfeeding difficulties, the overall quality of evidence is low. That's the honest summary. Cost is another practical limitation. Sessions typically run between sixty and one hundred twenty dollars each, and most babies need multiple visits. Insurance rarely covers infant craniosacral therapy, so this becomes an out-of-pocket expense for families who are already spending heavily on pediatric care.
If your baby has a fever, a diagnosed medical condition, or visible trauma to the skull, do not attempt any form of craniosacral work. Send them to a pediatrician first.

Alternative Approaches Worth Considering
For parents who want something similar but more accessible, infant massage is a reasonable alternative. It's free, it strengthens the parent-child bond, and it can address some of the same tension patterns without requiring specialized training. A few minutes of gentle belly massage in a clockwise pattern can help with gas and colic symptoms that sometimes overlap with craniosacral concerns. Chiropractic care specifically for infants is another option some parents pursue. Pediatric chiropractors use even lighter touch than craniosacral therapists, and some studies suggest benefit for colic and ear issues. The evidence quality is similarly limited, but it's a structured alternative that some families find helpful. The most important step regardless of which path you choose is getting a proper medical evaluation first. Rule out infection, reflux, anatomical issues, and other conditions before assuming the problem is a craniosacral restriction. A good pediatrician will do that work quickly and without judgment.