Why Most Nurses Skip the Thinking Part
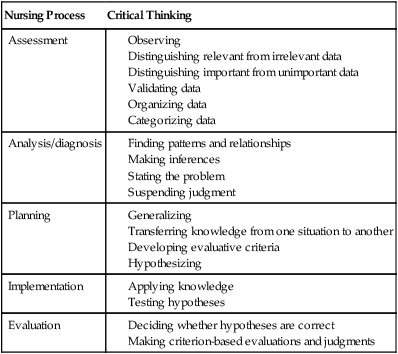
I spent six years on med-surg, then moved to the ICU, and honestly the biggest difference between good nurses and excellent ones wasn't knowledge. It was how fast they could recognize when their initial assessment was wrong and pivot without panic. The Critical Thinking Process In Nursing isn't some academic concept you learn in nursing school and forget. It's the mental checklist you run through every single shift when a patient's vitals shift or a medication order looks slightly off. Let me walk you through how this actually works in practice rather than how it reads in a textbook. You get a patient assignment at 0700. You do your initial assessment. By 0900, the patient is complaining of vague epigastric pain. A new nurse writes this off as indigestion and documents it under gastrointestinal assessment. An experienced nurse runs through the process differently. They ask what changed since admission. They check the labs. They look at the cardiac enzymes. They notice the EKG shows subtle ST depression that wasn't flagged because everyone was focused on a different problem. That process—gathering data, analyzing it against baseline, identifying discrepancies, and making a clinical judgment—is critical thinking in action. The formal steps most programs teach you are: assessment, diagnosis, planning, implementation, and evaluation. That's the nursing process, which happens to be the framework critical thinking sits inside. But here's what they don't tell you in class. The steps aren't linear. You're not filling out a form in order. You're constantly moving backward and forward between them, sometimes within seconds.
I remember one specific case that really cemented this for me. I had a post-op cholecystectomy patient, day two, who kept saying his shoulder hurt. The surgical team documented it as referred pain from the pneumoperitoneum, which is normal after laparoscopic surgery. Everyone agreed. Then I noticed his oxygen saturation had dropped from 97 to 93 on room air, he was mildly tachycardic, and his pain was worsening despite analgesics. I pulled up his chest X-ray from admission to compare with a new one, ran his D-dimer because the timeline fit for a PE, and called the hospitalist before the surgeon arrived for rounds. Turns out it was a small pulmonary embolism, not referred pain. The shoulder pain was both. If I had stopped at the first explanation, that patient would have coded on my unit. That's the difference between pattern recognition and actual critical thinking. Pattern recognition says this looks like that. Critical thinking says this looks like that but also looks like something else, and here's why I'm checking.
The Counter-Intuitive Parts Nobody Talks About
First, being thorough doesn't mean checking more things. It means checking the right things in the right sequence. Novice nurses tend to gather excessive data before making any decision. They run every test available and then get overwhelmed. Expert nurses gather just enough data to rule out the most dangerous possibilities, make a judgment call, and then refine as new information arrives. This is called bounded rationality, and it's the reason experienced clinicians can make accurate decisions in three minutes that would take a new grad twenty. Second, confidence is your enemy during the assessment phase. When you're confident your patient is fine, your brain stops looking for disconfirming evidence. This is called confirmation bias and it kills patients. The workaround is simple but uncomfortable. Before you finalizing your assessment, ask yourself a specific question: what finding would prove me wrong? Then actively look for it. If you can't find it, note that you looked. This takes twelve seconds and has prevented me from missing two silent sepsis presentations this year alone. Third, documentation and critical thinking are not the same thing. You can document perfect critical thinking and still think poorly. Documentation is a legal record. Critical thinking is a cognitive process that may or may not be visible on paper. When the charge nurse asks why you called a code blue on a certain patient, don't tell them what your notes say. Tell them what you observed, what you considered, and why you chose your action over the alternatives. Your documentation will be reviewed in a lawsuit. Your reasoning will be reviewed by your peers. The second matters more for your actual practice.
Get the Full Details
When The Process Breaks Down
The Critical Thinking Process In Nursing fails under three conditions I've seen repeatedly. First, severe time pressure combined with understaffing. When you're managing six unstable patients with no help, you revert to protocol and pattern matching. That's not a character flaw. That's cognitive overload. The workaround is to slow down to a deliberate crawl on your first high-acuity assessment and then move faster afterward. The initial investment of thirty seconds saves you from a missed deterioration that takes forty-five minutes to manage. Second, groupthink on busy units. When the attending physician says one thing and four nurses agree, dissenting with a different clinical interpretation requires social courage that training programs rarely teach. I've watched nurses stay silent when their assessment didn't match the plan because the hierarchy felt impenetrable. The alternative is a structured communication tool like SBAR, which gives you a socially acceptable script to present a conflicting observation without attacking someone's authority. Third, burnout. Emotional exhaustion directly reduces working memory capacity, which is the mental space where critical thinking happens. A burned-out nurse can recite every step of the process but won't have the cognitive resources to execute it under stress. There is no workaround within the system except recognizing when you're in this state and adjusting your expectations accordingly. Double-check your meds. Ask a colleague to co-assess your complex patients. Don't make high-stakes judgments on empty. This isn't weakness. It's risk management.
The process works when you treat it as a habit, not an exam answer. Run through it unconsciously until it breaks, then consciously rebuild it. That's how you keep patients alive.