How to Build a Critically Appraised Topic (CAT) Without Losing Your Mind
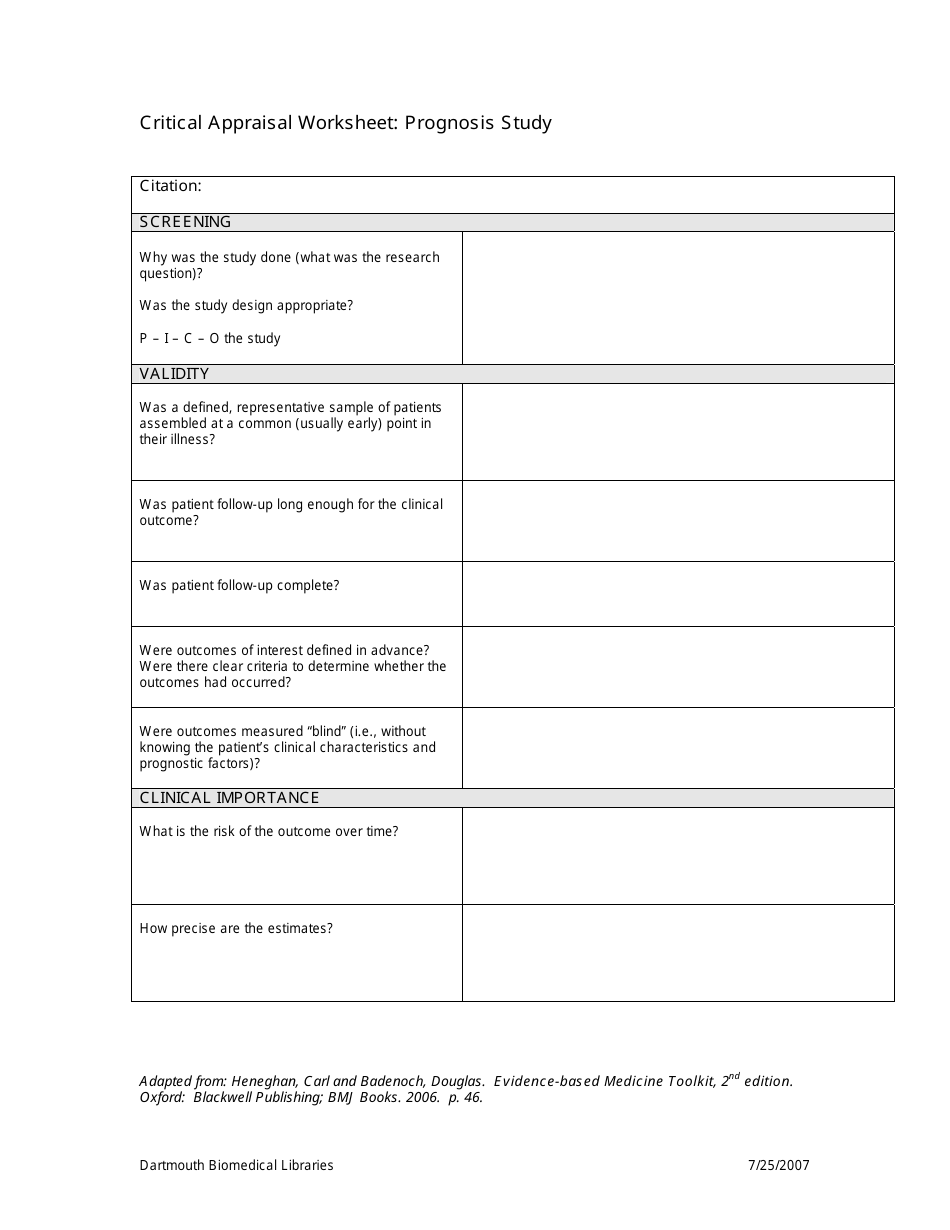
A Critically Appraised Topic Worksheet is a structured document you use when you need a quick, trustworthy answer to a specific clinical question. It sits somewhere between a full systematic review and your gut instinct. You take a focused question, run a targeted literature search, appraise whatever evidence surfaces, and distill it into something you can actually use at the point of care. That is the whole idea, anyway. The worksheet itself is just a scaffold. Different institutions template it differently, but every version asks the same core things. What is the clinical question? What search strategy did you use? What studies did you find, and what do they actually say? How confident are you in the results? And what would you do differently next time? I have filled out dozens of these across different specialties. The ones that actually help are the ones where someone did the honest work of documenting why they excluded certain papers, not just listing inclusion criteria and moving on. A CAT that does not show its reasoning is basically just a literature review with a fancy title.
Step-by-step: building a working CAT
Start with the question. Not the topic. The question. "Does chlorhexidine reduce gingivitis?" is a topic. "In adults with moderate chronic gingivitis, does a chlorhexidine mouthwash used twice daily for four weeks reduce bleeding on probing scores compared to placebo?" is a question. You want the second one. PICO or PICOS format forces you to specify the population, intervention, comparator, outcome, and sometimes study design. This matters because it determines everything that follows. Next, define your search. Write out the exact database names, the search terms, the Boolean operators, and the date range. I used to skip this step when I was rushed. You will never forgive yourself later when someone asks you how you found those six papers and you cannot reproduce it. Keep a copy of your search strings. Put the URLs for your result sets. This is the single most common thing people get wrong on a CAT. Then screen. Title and abstract first. Full text after. Document how many you excluded at each stage and why. This is not optional paperwork. If you cannot explain why you dropped a paper, your evidence base is weaker than you think. I once spent two days on a CAT about probiotics for antibiotic-associated diarrhea and realized halfway through that I had unconsciously excluded three trials because the sample sizes were under 50 patients. That was a selection bias I had baked into my own work. I added them back in and the conclusion changed direction.
Appraise the included studies using a recognized tool. CASP checklists, GRADE, the Cochrane risk of bias instrument — pick one and stick with it. Do not switch mid-stream. Rate each study and record your justification. A study can be perfectly conducted but still answer a different question than yours. That is not a flaw in the study. It is a limitation of applicability, and you note it separately. Finally, synthesize and conclude. This is the part most people rush. If the evidence is heterogeneous, say so. If the confidence is low, say so. Do not pad your conclusion with phrases like "further research is needed" unless you actually mean it. That phrase is often a polite way of saying your CAT was not useful enough to drive a decision.
Get the Full Details

Common mistakes I see repeatedly
Question drift is the biggest one. You start with one sharp question and by the time you have read fifteen papers you have silently expanded your inclusion criteria three times. The CAT looks thorough but it is actually answering a softer, broader question than you originally posed. Lock your PICO before you search and resist changing it unless the evidence forces you to. Another thing: people treat the CAT as a grading exercise. They slot each paper into high or low quality and then average the results. Quality ratings are not numeric inputs. A well-conducted RCT with n=30 and a poorly conducted RCT with n=500 are not comparable in a simple quality-weighted aggregate. Appraise each study for what it is and let the synthesis reflect the actual body of evidence.
When a CAT is the wrong tool
A CAT takes roughly 4 to 8 hours for a first-time author working alone, depending on complexity. If your question changes weekly or requires constant updating, a CAT will become stale before you finish it. In those cases, a living evidence summary or a regularly updated scoping review is more appropriate. Also, if your clinical setting involves a condition where high-quality evidence simply does not exist — rare diseases, novel procedures, emerging infections — a CAT will not generate good answers. It will just give you a very structured way of documenting that there is nothing good to go on. I worked through a CAT on a topical antimicrobial protocol for pediatric otitis media with effusion where the available literature consisted entirely of case series and expert opinion from 1998 to 2004. The worksheet forced me to appraise low-quality evidence transparently, which is useful for honesty, but it could not create evidence where none existed. In that situation, I switched to a formal Delphi consensus exercise instead and documented the CAT as a preliminary scan that informed the consensus process.
Where to get a usable template
Most academic health centers have their own version. If yours does not, the CASP website offers free worksheets in multiple formats. The ADA and various pharmacy education programs also publish their own templates. Pick one that matches your discipline's conventions. A dentistry CAT that uses PEDro-style scoring will look different from a nursing CAT using JBI tools, and that is fine. The important part is not which template you use. It is whether you fill it in carefully enough that someone else can verify your work. That is the only measure of a CAT that matters.