Where Person-Centred Therapy Gets It Wrong
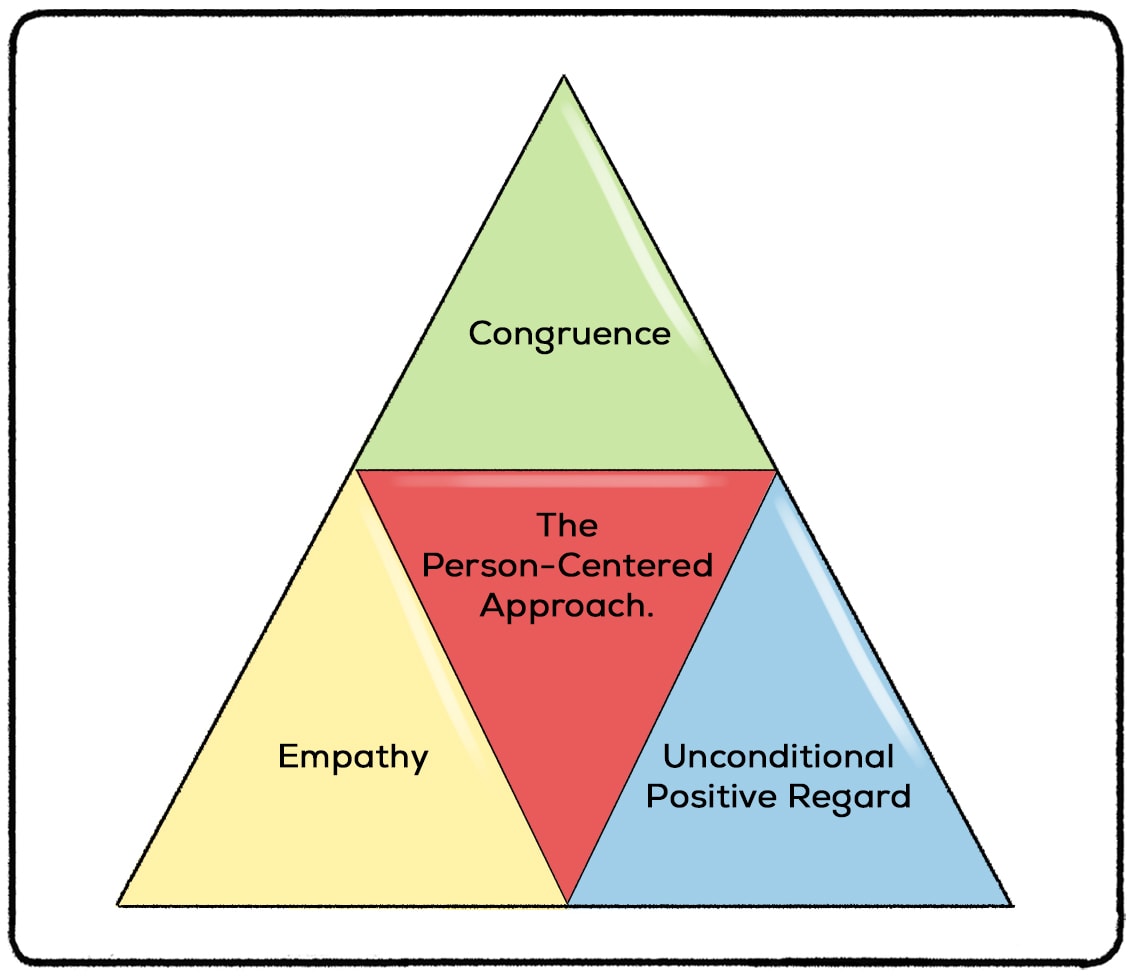
Person-centred counselling has its place, but the criticisms are real and most of them come from actual clinical experience rather than theory. The model assumes clients have enough self-awareness and motivation to benefit from non-directive work. That sounds reasonable until you sit across from someone who cannot articulate what they want from therapy and keeps circling the same three thoughts for twelve sessions. The therapist mirrors them kindly through each repetition. The core triad of Rogers—unconditional positive regard, empathy, and congruence—is genuinely useful. But usefulness is not the same thing as sufficiency. Many people enter therapy during active crisis and need concrete coping strategies, not a warm sounding board. The method was never built for that population. It was built for people who already had some internal resources and needed a space to find their own way through.
Criticisms Of Person Centred Counselling
The most common criticism is the lack of structure. Without sessions moving toward specific goals, therapy can drift indefinitely. Clients may leave after many sessions feeling heard but not fundamentally changed. A meta-analysis by Dings et al. found that person-centred outcomes were modest compared to more structured approaches, particularly for anxiety and depression. This is not a minor flaw. It is the structural flaw. There is also the problem of therapist comfort masquerading as fidelity to the model. Some practitioners default to person-centred techniques because they feel safe. Reflective listening requires less clinical courage than challenging a client or introducing cognitive restructuring. I have seen seasoned therapists hide behind empathy because directing a session feels risky when the outcome is uncertain. The client pays for that risk aversion in stalled progress. Cultural bias is another legitimate concern. Person-centred counselling emerged from Western individualism. In cultures where family hierarchy, spiritual guidance, or direct authority figures are the expected framework for help, the non-directive stance can feel cold or dismissive. A client from a background that values a therapist who takes a firm, instructive position may interpret the Rogerian silence as indifference rather than respect.
The evidence base itself is thinner than competitors. CBT, solution-focused brief therapy, and ACT all have larger and more rigorous trial records. Person-centred therapy has empirical support, but it is smaller and older. The evidence does not prove it fails. It proves it has less proof behind it than alternatives. That gap matters when you are recommending a treatment modality to someone who wants to know what is most likely to work. Time and cost are practical criticisms. Effective person-centred work often requires extended duration because insight develops gradually through the relationship. Sixteen to twenty sessions is not unusual. Insurance panels and public health systems frequently cap sessions at ten or twelve. The model does not fit those constraints well. Clients get discharged before the therapeutic conditions mature enough to produce meaningful change. I ran into a specific edge case last year with a client who presented with chronic indecision and repeated relationship failures. The person-centred approach kept returning to the same theme: explore feelings, reflect the narrative, trust the process. After six sessions we were describing the same pattern with slightly different words. The reflection was technically accurate. It was also not moving the needle. I shifted to a more structured intervention using behavioral activation paired with values clarification from ACT. The next four sessions produced concrete action plans instead of recursive awareness. The client ended therapy with measurable change in decision-making behavior, not just improved rapport with the therapist.
Get the Full Details

The deeper criticism that nobody wants to state outright is that person-centred counselling can enable dependency on the therapeutic relationship. When the therapist is consistently warm and accepting, the client may conflate the feeling of being accepted with the feeling of having been helped. Progress gets confused with comfort. This is hard to detect in real time because both the client and therapist feel good about the sessions. The subjective experience of growth is not the same as objective growth. Another overlooked issue is the therapist's ability to remain non-judgmental under stress. The model demands radical acceptance from the practitioner. Not everyone can sustain that consistently, especially in high-volume caseloads. When empathy erodes, the technique becomes mechanical reflection without the underlying presence that gives it meaning. Clients sense this shift quickly even when they cannot articulate it. For acute trauma cases, pure person-centred work can be insufficient or even counterproductive. Trauma processing typically benefits from phased, structured protocols like EMDR or trauma-focused CBT. Simply providing a supportive environment does not resolve traumatic memory networks. Research on trauma treatment consistently shows that structured interventions outperform purely relational ones for PTSD symptom reduction.
There is also the gatekeeping problem. People who struggle with introspection, alexithymia, or cognitive limitations do not benefit as much from a method that assumes verbal reflection is the primary vehicle for change. Intellectual insight is not the same as behavioral change, and person-centred counselling tends to favor the former. The workaround is not to abandon the model entirely. It is to use it selectively. Person-centred principles work best as an approach to the therapeutic relationship regardless of modality. The skills of empathy and unconditional positive regard improve every therapeutic style. The problem arises when the philosophy becomes the entire method. Combining person-centred rapport-building with structured interventions from CBT, ACT, or Gottman-based frameworks produces stronger outcomes across a wider range of clients. The honest assessment is that person-centred counselling is a foundation, not a complete building. It provides the conditions under which change is possible. It does not reliably produce change on its own for the clients who need it most. Any practitioner who treats it as a complete system for all presenting problems is either unaware of the limitations or unaware of the clients suffering from that unawareness.
If you are studying this approach, read Rogers directly but also read the empirical critiques. Eysenck's early objections were harsh and sometimes unfair, but the modern evidence base has sharpened the arguments considerably. Look at studies by Bohart and Wade, by McLeod, and by the various outcome research groups. The field has moved past simple praise and simple dismissal. Both positions are equally unhelpful.