What you actually need to know about cross sectional imaging of the thigh
Most people coming into this want a clean diagram they can memorize and regurgitate on an exam. That works fine until you're looking at an actual MRI slice with pathology and nothing looks like the textbook. I've spent years reading CT and MRI through the lower abdomen and down into the proximal thighs, and the gap between illustrated anatomy and real clinical images is wider than you'd think. Let me walk through what you're actually dealing with when you look at a cross sectional image of the leg at the thigh level, then I'll point out the things that trip people up most of the time.
Getting to grips with Cross Sectional Anatomy Of Thigh
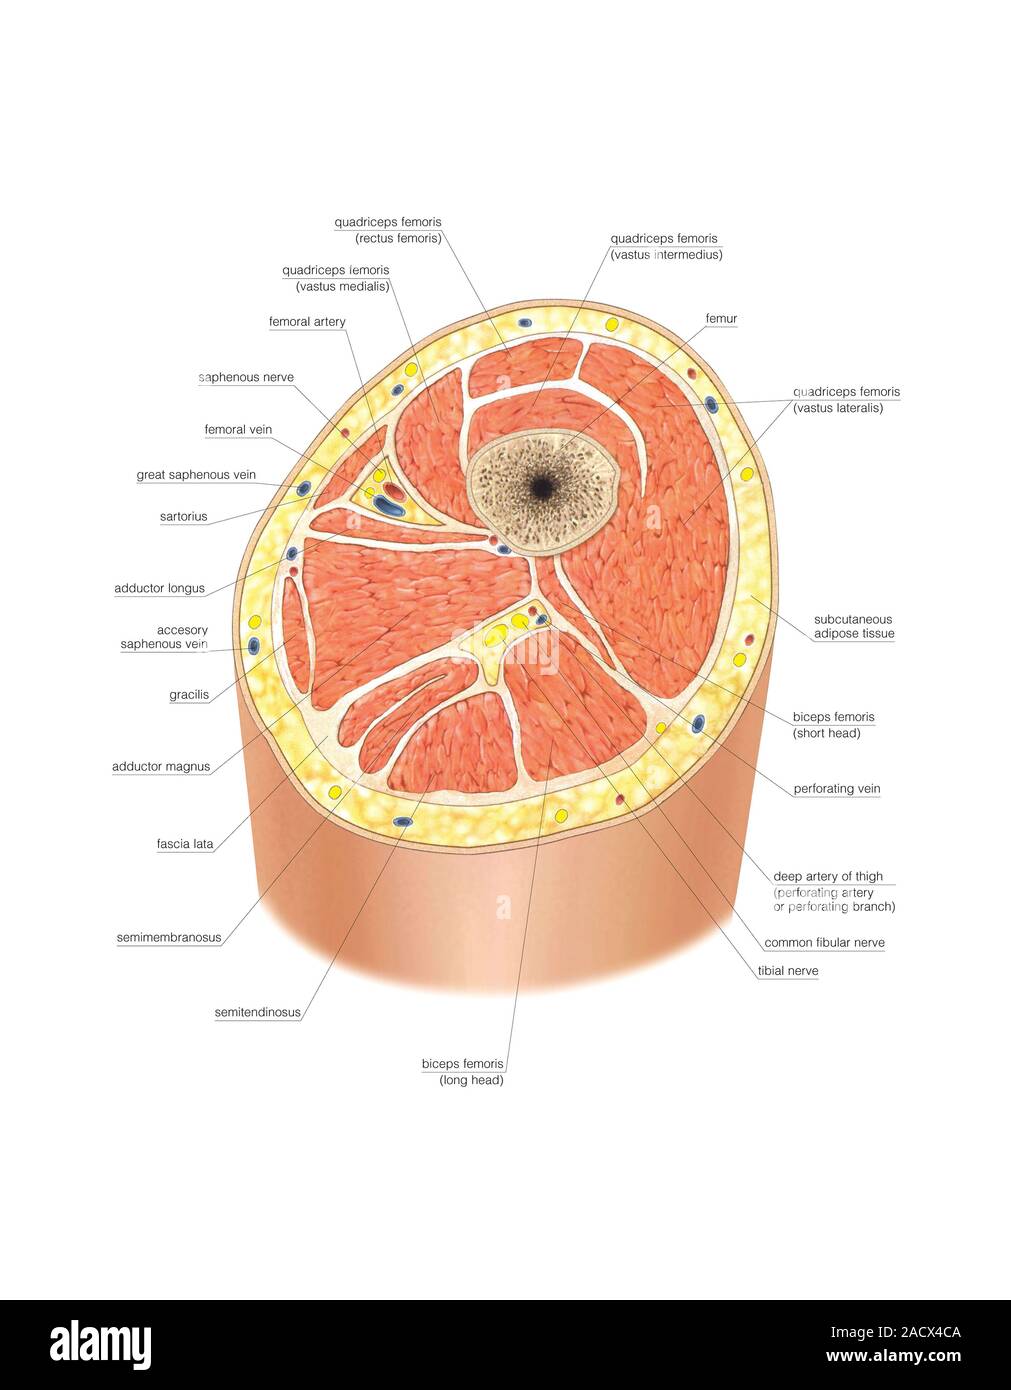
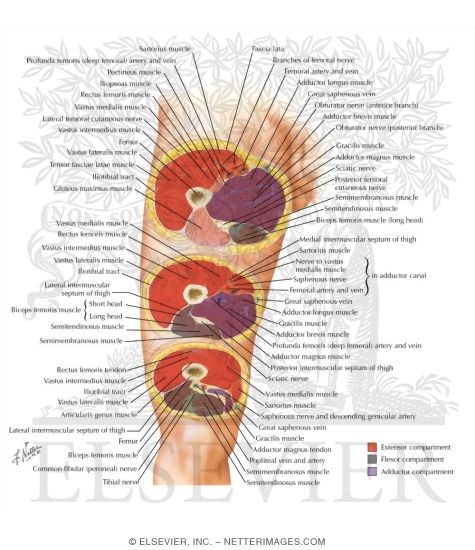
The thigh on axial imaging is divided into three main compartments, and understanding this division matters more than memorizing every muscle name. The anterior compartment sits in front, bounded laterally by the iliotibial tract and medially by the medial intermuscular septum. The posterior compartment occupies the back, wrapped by the posterior intermuscular septum. Then there's the adductor or medial compartment sandwiched between those two. If you can track these septa, you can orient yourself on any slice regardless of the exact level you're at. The femur sits roughly in the center but slightly posterior on axial cuts. Surrounding it you've got the vastus intermedius sitting right on the anterior femoral shaft, then the quadriceps group wrapping around the sides and front. The hamstrings take up the posterior compartment — biceps femoris laterally, semitendinosus and semimembranosus medially. The gracilis, adductor longus, adductor brevis, and adductor magnus fill out the medial compartment with the pectineus tucked up near the anterior margin near the hip. Here's something I learned the hard way: the adductor magnus has both an adductor portion and a hamstring portion, and on imaging they look different. The adductor part is anterior and medial, while the hamstring part runs more posteriorly and inserts on the adductor tubercle. On a CT scan through the mid-thigh, people often miss that the posterior part of adductor magnus is functionally part of the hamstrings, not the adductors. This matters when you're tracking a tear or a strain.
How I actually read a thigh cross section
Start with the bone. The femoral cortex should be uniformly dark on MRI and uniformly bright on CT. Any focal defect, any irregularity in the cortex, any surrounding marrow signal change — that's your anchor point. Once you've confirmed where the femur is, you know exactly where everything else should be. Then check the fascia. The deep fascia of the thigh, the fascia lata, should appear as a thin dark line surrounding the entire compartment system. It's easy to overlook on lower-quality images, but if that line is disrupted, you're looking at a fascial tear, which changes the whole picture for a muscle injury. A contained tear stays within the muscle belly. A fascial rupture means the muscle fibers can bulge out, and that's a different grade entirely. The neurovascular bundle lives in the anterior medial aspect. The femoral artery and vein sit just posterior to the inguinal ligament, and the femoral nerve is lateral to them. As you move distally through the thigh, these structures shift. By the adductor canal, the femoral artery and the saphenous nerve are the main contents, with the nerve to vastus medialis wrapping around. I've seen multiple cases where radiologists reported normal neurovascular anatomy simply because they weren't tracking the structures carefully through each sequential slice.
Get the Full Details

Practical edge case that cost me time
About three years ago I was reviewing a series of MRIs from a patient with anterior thigh pain and vague swelling. The standard read came back as normal quadriceps strain, grade one. But something felt off. I kept looking at the medial aspect of the distal thigh, just above the adductor hiatus, and there was this subtle signal change that everyone was attributing to artifact. Turns out it was an isolated tear of the adductor magnus hamstring portion with a small hematoma tracking along the posterior compartment. The patient was a former soccer player who'd felt a pop during a sprint. Standard imaging protocols for thigh trauma often don't emphasize the posterior adductor magnus enough because everyone's focus is on the more commonly injured semimembranosus or biceps femoris tendons. I ended up using a high-resolution T2 fat-suppressed sequence through the specific level of the adductor hiatus to confirm it. That extra five minutes of scanning made the difference between a correct diagnosis and a missed injury that would have required longer rehab. If you're studying this for clinical purposes, don't skip that region. The adductor magnus hiatus area is a blind spot on routine thigh protocols and it's where interesting pathology hides.
Counter-intuitive things that aren't in the textbooks
The sartorius muscle behaves differently depending on the level you're imaging. Near the hip it's a flat broad muscle on the anterior surface. By the mid-thigh it becomes more cord-like and moves toward the medial side as it heads toward its insertion on the pes anserinus. On axial images at different levels, it can look like completely different structures if you're not tracking it continuously. I've seen junior residents call it the rectus femoris at one level and then the gracilis at the next, missing the fact that it was the same muscle the whole time. Another thing: the size and shape of the femoral vein varies dramatically with respiration and positioning. On supine CT scans, it's often flattened and oval. On MRI, especially with certain sequences, it can appear much more prominent and round. This isn't pathology. It's just physiology. But I've seen multiple reports where a normal-appearing femoral vein on one sequence was flagged as anomalous because the reader was comparing it to a different sequence where it looked completely different.
What this approach does not do well
Cross sectional anatomy of the thigh through CT and MRI has real limitations. Small muscle strains, especially grade one injuries with minimal edema, can be invisible on standard protocols. The sensitivity for detecting early myositis ossificans drops significantly in the first two weeks after injury. And spatial resolution, while good, still can't replace direct palpation and dynamic ultrasound for assessing muscle bulk changes and subtle weakness patterns. If you're relying solely on static cross sectional images, you're missing a lot of the functional picture. Ultrasound should be your first-line tool for most soft tissue complaints, and cross sectional imaging should complement it rather than replace it. MRI is overkill for simple strains and underkill for dynamic assessment. The sartorius crosses from lateral to medial across the anterior thigh, and where it intersects the adductor longus is a reliable landmark. The conjoined tendon formed by sartorius, gracilis, and semitendinosus at the pes anserinus is another key reference point. The vastus lateralis is the largest single muscle in the thigh and occupies most of the lateral anterior compartment. If you see a large muscle mass on the lateral side of the femur, that's your vastus lateralis. The rectus femoris is the only quadriceps head that crosses the hip joint, so it's the only one you'll see continuing superiorly into the pelvis on coronal and sagittal views. The sciatic nerve runs through the posterior compartment, usually lying on top of the adductor magnus and the posterior capsular structures. It's relatively protected but can be compressed in cases of deep gluteal syndrome or piriformis tension, and on cross section you'll see it as a rounded structure with a characteristic honeycomb internal pattern. That pattern disappears when there's nerve pathology, which is useful for identifying neuritis or entrapment.

The great saphenous vein runs subcutaneously along the medial thigh. It's not deep, and it shouldn't be confused with the femoral vein. Mixing those up is a beginner mistake that happens more often than you'd expect, especially on thinner axial slices where the vessels are close together.