Reading a thoracic CT isn't as bad as people make it seem, but you need a system that actually works
Most radiology residents and med students try to memorize the chest CT by going slice by slice from apex to base, which is fine until you're looking at a lung window with diffuse ground glass opacities and you can't tell where the right middle lobe ends and the lingula begins. I spent about three years doing this wrong before someone told me to stop treating each slice like it was isolated and start thinking in terms of vascular landmarks. The lung parenchyma can look basically normal on a given slice while the adjacent vessels are doing something pathological.Why Cross Sectional Ct Thorax Anatomy Confuses People
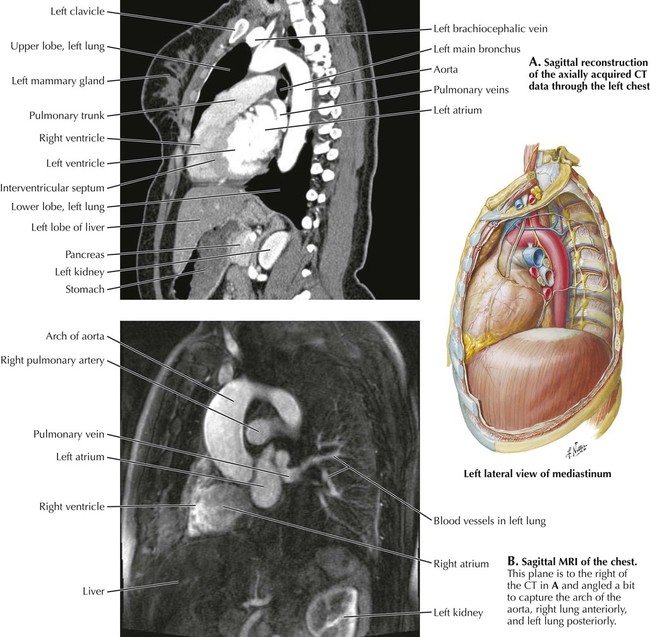
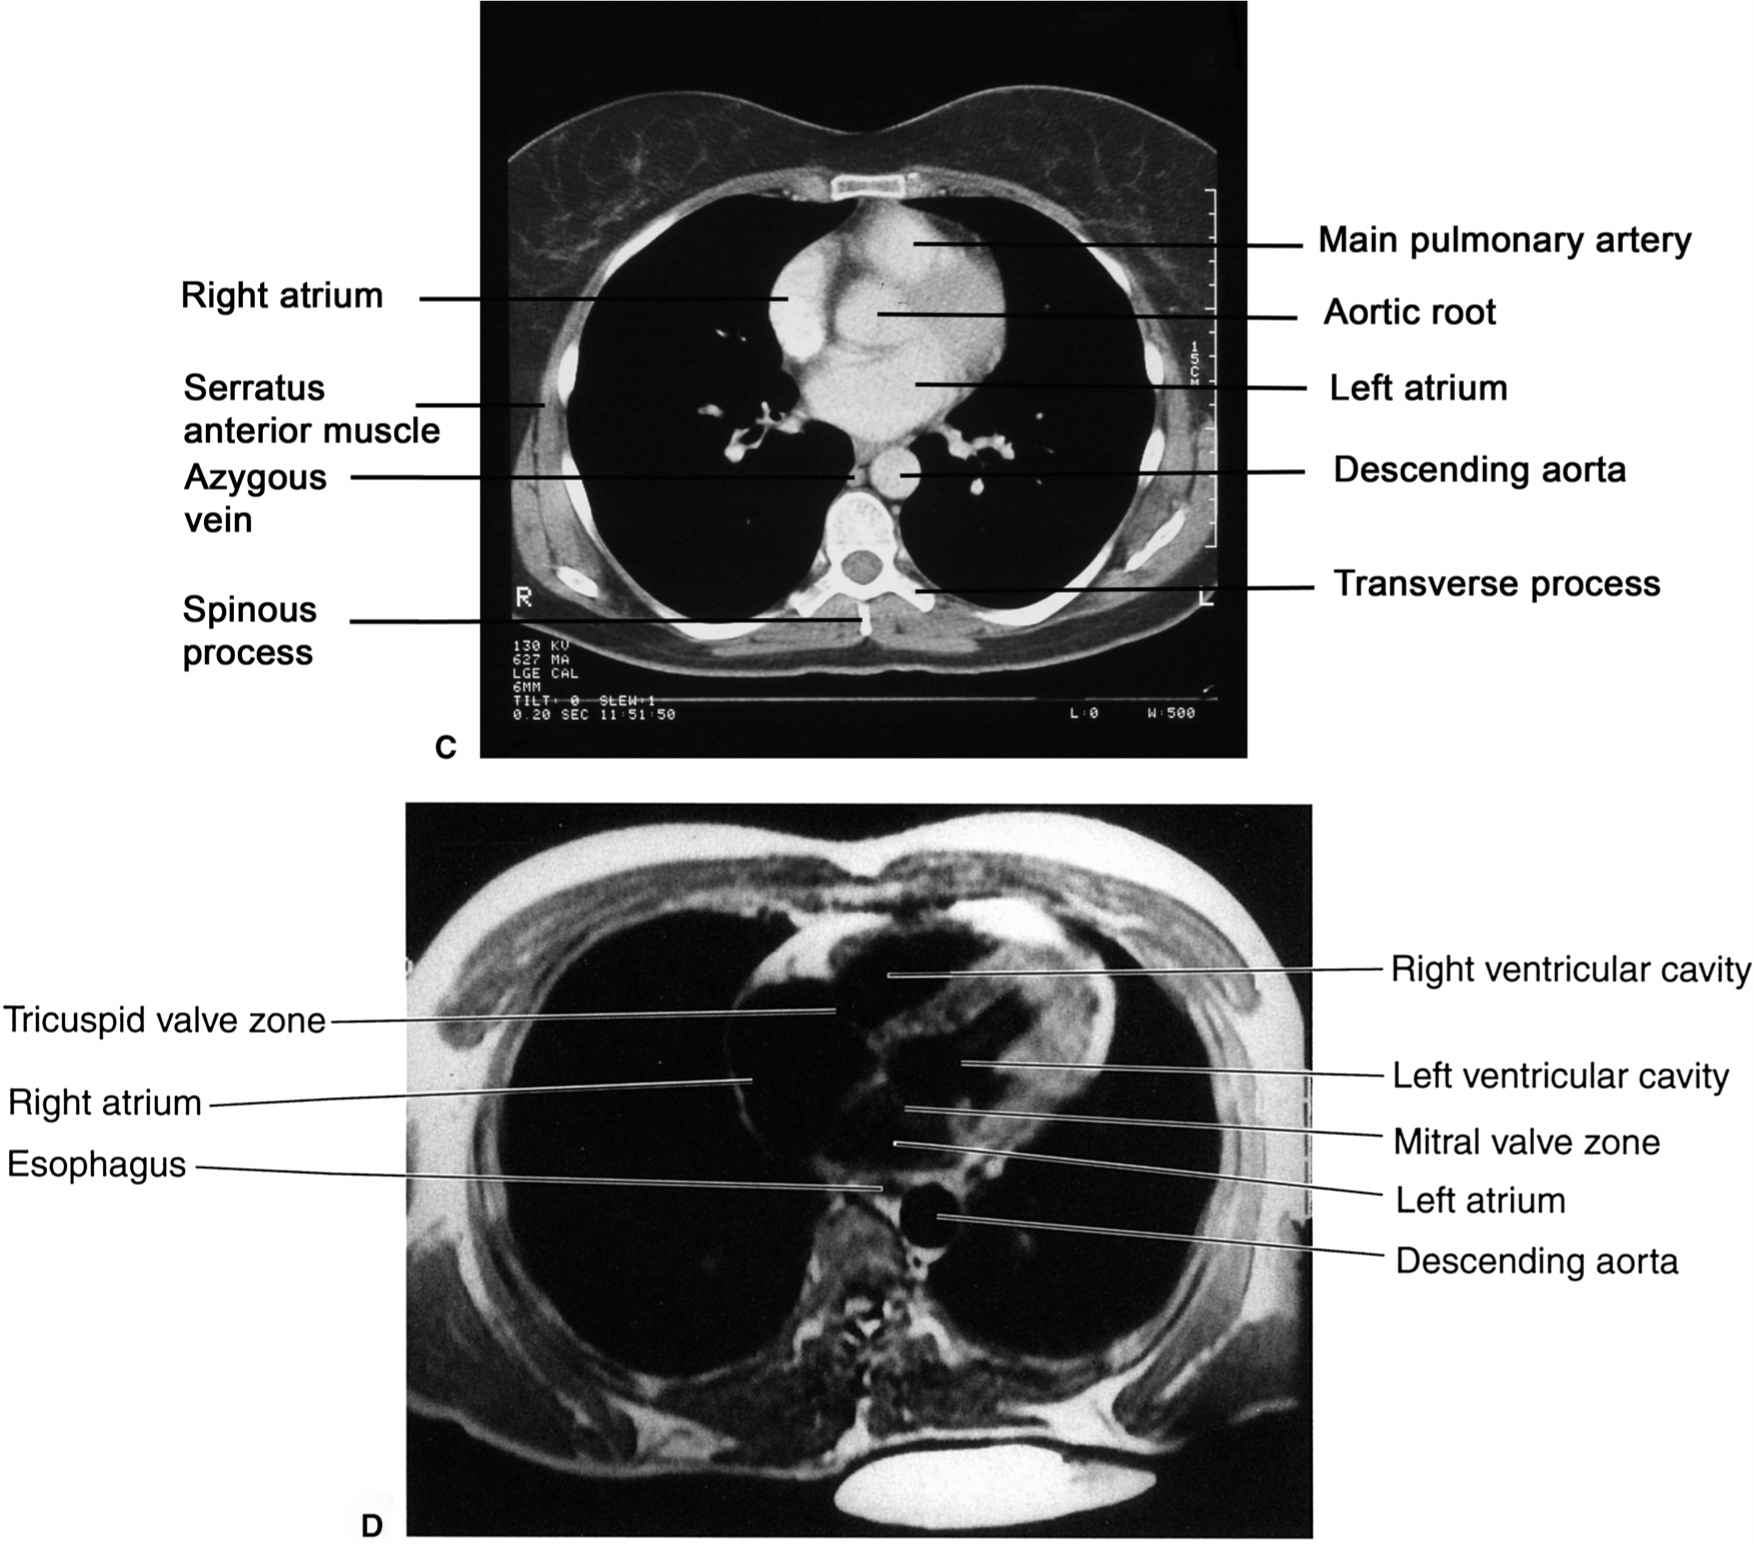
The cross-sectional view inverts everything you learned from frontal and lateral X-rays. Anterior is up, posterior is down, the patient's right is on your left, and structures that sit next to each other in 3D space appear separated by several millimeters on adjacent slices. The descending aorta sits posterior and slightly to the left of the spine. On axial CT it looks like a bright circular structure just off the midline. If you miss that on one slice, you might assume the aorta isn't there at all when really you just skipped over it between two windows. The mediastinal fat is your best friend here. It outlines structures that would otherwise be invisible. Without contrast, the heart chambers all look like the same shade of gray. With contrast, they separate nicely, but you still need to recognize that the right atrium is the most anterior chamber on the right side, sitting just behind the sternum, while the left ventricle wraps around posteriorly and to the left. I once misread a slice as showing a pericardial effusion because I didn't account for partial volume averaging. The fluid was actually just the blood pool in the right atrium, and the adjacent pericardium had a thin layer of fat that blended into the window setting. I caught it when I scrolled back through the original DICOM and adjusted the window width to 350 and level to 40. The effusion disappeared. It hadn't been there at all. That mistake cost me about forty minutes of my evening and reminded me to always verify suspicious findings by adjusting the window and scrolling through contiguous slices rather than trusting a single static image.The hilar regions are where most people get tripped up. The right hilum sits higher than the left in about sixty percent of normal scans. On the left, the pulmonary artery arches over the left main bronchus, forming what radiologists call the pulmonary artery sling. If you don't know that landmark, you might mistake the left pulmonary artery for a lymph node or a mass. The bronchus intermedius is another classic pitfall. It appears as a short tubular air-filled structure emerging from the right main bronchus and heading toward the right middle and lower lobes. Beginners often call it a lymph node because it's round on a single axial slice. It's not a lymph node. It's a bronchus. Let's talk about the azygos vein. It arcs over the right main bronchus and empties into the superior vena cava. On axial CT it looks like a small circular structure anterior and lateral to the right paratracheal region. An enlarged azygos vein is a sign of superior vena cava obstruction or right heart failure, but a normal azygos can measure up to eight millimeters. I've seen residents flag a five millimeter azygos as abnormal because they were using a cutoff of three millimeters they picked up from a review article that wasn't specific to adult imaging.
How to actually read a thoracic CT in practice
Start with the lung windows. Scroll from apex to base in about ten second intervals without pausing on any single slice. Look for nodules, consolidations, or architectural distortion. Then switch to mediastinal windows and scroll the same distance at the same speed. Now you're looking at the heart, vessels, lymph nodes, and mediastinal structures. If something catches your eye on either pass, go back and look at it in both windows. A lesion that's invisible on lung window might be obvious on mediastinal window, and vice versa. The carina is your primary landmark for dividing the upper, middle, and lower zones. Above the carina, you're in the upper zone with the great vessels and trachea. At the carina, you see the right and left main bronchi. Below the carina, you enter the lower zone where the pulmonary arteries and veins become more prominent. The pulmonary artery trunk bifurcates roughly at the level of the carina, but this can vary by two to three vertebral levels depending on the patient's height and body habitus. I work through the slices in a consistent order now: trachea first, then carina, then main pulmonary artery bifurcation, then each pulmonary artery branch, then the pulmonary veins, then the atria, then the ventricles, then the diaphragm. This gives me a mental map of where each structure should appear. When something is where it shouldn't be, I notice it immediately. A lymph node at the subcarinal station (station 7) that measures more than fifteen millimeters is abnormal regardless of how well the surrounding tissue looks. A pulmonary nodule that appears on only one slice is probably a vessel on end, but if it appears on two or more contiguous slices, it's a nodule until proven otherwise. The lower lobes are the most common location for malignancies and infections. The superior segment of the left lower lobe lies posterior to the heart and can be difficult to distinguish from lingular pathology on mid-level slices. The key is to follow the left pulmonary artery. When you see the left upper lobe pulmonary artery coursing horizontally, the lung tissue posterior and inferior to it is the left lower lobe. The lingula is anterior and medial to that same artery. Window settings matter more than people admit. For lung parenchyma, I use a width of fifteen hundred and a level of negative six hundred. For mediastinum, width of three hundred fifty and level of fifty. These aren't religious doctrines. They're starting points. If a patient has emphysema, I might narrow the lung window width to eight hundred to better appreciate the low attenuation areas. If a mediastinal mass is isodense to muscle, I'll drop the width to two fifty to increase the contrast between the mass and surrounding fat. The pulmonary veins are easy to miss because they're thin-walled and don't have the same bright contrast enhancement as the arteries in a standard arterial phase scan. There are four of them: two from each lung, draining into the left atrium. The right superior pulmonary vein runs anterior to the right main bronchus and inferior pulmonary artery. The left superior pulmonary vein passes anterior to the left main bronchus. Knowing these relationships helps you identify them quickly instead of scrolling past them.Slice thickness affects everything. A standard chest CT uses one millimeter slices, but some protocols use five millimeter slices for screening or follow-up. With five millimeter slices, a five millimeter nodule can be completely missed due to partial volume effect. It gets averaged into the surrounding tissue and disappears. I've seen this happen twice in the last year on lung cancer screening scans. The lesions were there, probably two or three millimeters, but they were below the resolution threshold of the thicker slices. This is why thin-slice acquisition matters, especially when you're looking for early stage disease. One thing that drives me crazy is people confusing the descending aorta with the esophagus. They sit next to each other in the posterior mediastinum. The aorta is circular and pulsatile, which creates a mild motion artifact on some scanners. The esophagus is collapsed and variable in shape. Sometimes it contains a small amount of air or contrast. If you're unsure, look at the adjacent slices. The aorta maintains its circular cross-section through multiple levels. The esophagus is more likely to change shape or disappear entirely as you scroll.
There are things this approach doesn't cover well. Cross-sectional CT of the thorax is excellent for anatomy and most pathologies, but it's poor at assessing functional information. You can't tell if a bronchus is narrowed because of external compression versus intrinsic disease without additional imaging or bronchoscopy. You can't evaluate valvular function. You can't assess perfusion deficits without contrast timing that's specifically designed for perfusion studies. The anatomy is clear, but the physiology often isn't, and that gap matters clinically. If you want anatomical references, the Radiopaedia thoracic CT atlas is free and accurate. The textbook by Hatabu and Kazerooni covers the basics well. But no book will replace the time you spend scrolling through actual DICOM cases and building the mental map I described. The numbers and names are secondary. The spatial relationships are what you need to internalize.