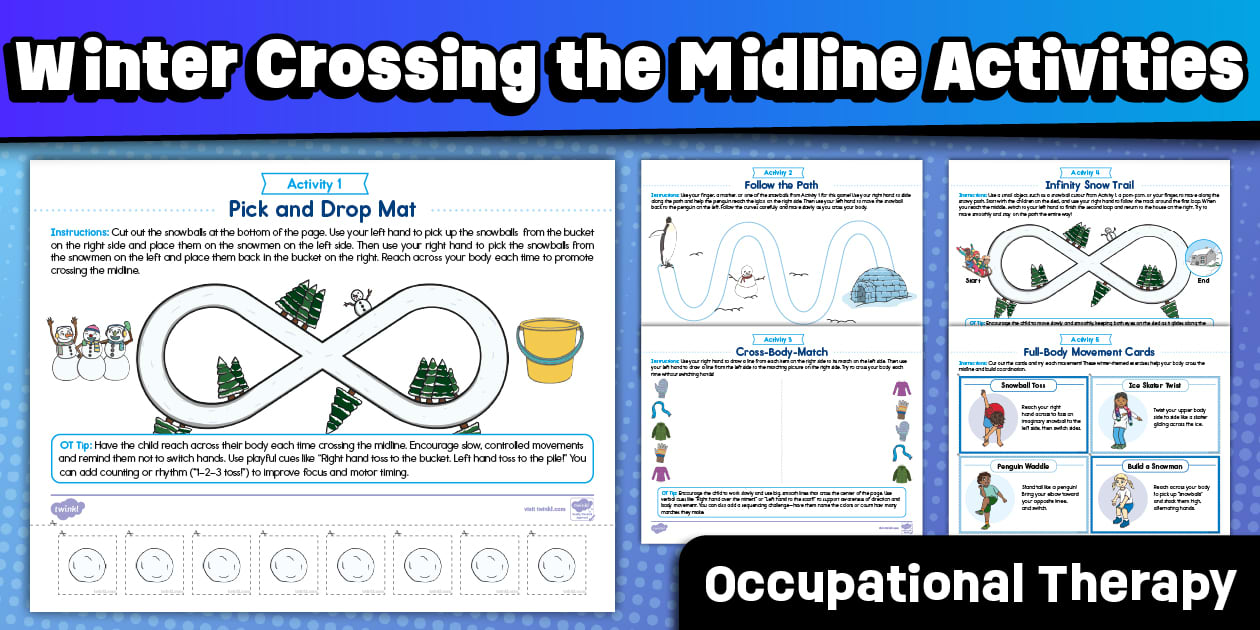
Why Standard Crossing Midline Drills Fail Most Kids
The whole idea behind crossing midline in occupational therapy is simple on paper: get the child to move one hand across the imaginary line that divides their body, which should help both brain hemispheres communicate. What nobody tells you is that for a significant number of kids, this is one of the most frustrating interventions you can attempt. I spent three years running these activities and watching kids either avoid them completely or perform them mechanically without any real neurological carryover. The real problem is that midline crossing isn't a skill you just teach. It's a developmental milestone that emerges from a foundation of good bilateral coordination, adequate core stability, and integrated vestibular input. When kids lack that foundation, throwing crossing activities at them is like asking someone with weak legs to run a marathon. They might manage the motion, but nothing meaningful is happening underneath it.
Crossing Midline Activities Occupational Therapy
Here's what actually works. Start with bilateral activities where both hands meet in the midline without the pressure of crossing. Things like rolling playdough with both palms, squeezing therapy putty between the hands, or holding a ball with both hands while passing it back and forth. These build the basic neural pathways for bilateral integration first. Only after a child can do those smoothly for about two weeks should you introduce actual crossing movements. From there, the progression I use goes like this: horizontal plane tasks first, then vertical, then diagonal. A simple version of horizontal crossing is having the child use one hand to pick up pieces from a tray placed on the opposite side of their body and move them to the other side. Not drawing across the midline—that's too complex for most kids still learning this. Just simple transfer tasks. The vertical plane work comes next. I'll have the child stand at a vertical surface like a whiteboard and make marks with one hand while reaching across their body. But here's where most therapists go wrong. They tell the kid to "cross over." That explicit instruction actually makes it harder. The child starts monitoring the movement consciously instead of letting it happen automatically. Just set up the task so crossing is necessary without mentioning it.
Diagonal movements are the hardest and come last. A cat-dog walk where the child touches their opposite elbow to their knee, or crawling patterns on the floor, are the gold standard here. These require more complex motor planning and core engagement, so kids usually need at least four to six weeks of consistent horizontal and vertical practice before attempting these. I should mention something specific from my own experience. I had a kid, about seven years old, who could do every crossing activity I threw at him but only with his right side. Left side crossing was completely absent. I assumed it was just slower development on that side. Turns out he had subtle unilateral neglect from a past concussive event that nobody had picked up on. The left side crossing drills were pointless until we addressed the neglect with prism adaptation exercises and visual scanning training first. Once that was in place, the left side started working within about three weeks. That case changed how I approach this whole topic.
Get the Full Details

The Details That Actually Matter
Session length matters more than people think. Ten to fifteen minutes, three to four times per week, is the sweet spot. Longer sessions lead to fatigue and the quality of movement degrades quickly. I've seen therapists push 30-minute crossing sessions and wonder why kids regress. The brain doesn't consolidate new motor patterns through volume. It consolidates them through focused repetition followed by rest. Environment setup is another thing nobody talks about enough. The tray of materials for a horizontal crossing task should be placed about three inches past the child's shoulder line on the opposite side. Not far enough to strain, but far enough that the crossing is genuinely necessary. If the tray is too close, the child can reach it without crossing. If it's too far, they'll lean their whole torso instead of just crossing with their arm. Both of those are compensatory strategies that defeat the purpose. Surface angle makes a difference I didn't expect when I started. Flat table surfaces are actually the worst for learning midline crossing. When the paper is flat on the table, kids naturally rotate it or reposition their whole body instead of crossing their arm. Having the paper tilted at about a 45-degree angle against a book or wedge forces the arm into the crossing pattern naturally. The paper position does the cueing for you.
One more thing that surprised me: the dominant hand usually crosses more easily than the non-dominant hand. This is backwards from what you'd expect. The reason is that the non-dominant hemisphere controls the left side of the body, and the left hemisphere, which governs language and sequential processing, tends to dominate the right side. When the non-dominant hand crosses the midline, it requires more interhemispheric transfer, which is a harder neural task. So don't assume the easier side will develop first. The harder side often needs more attention even though progress is slower.
When This Approach Doesn't Work
I need to be honest about the limitations. Crossing midline activities have a high failure rate in certain populations. Kids with significant developmental coordination disorder, or DCd, often cannot develop spontaneous midline crossing regardless of how many drills they do. In my experience, maybe one in five kids with DCd ever achieves true spontaneous crossing without ongoing support. The rest learn compensatory strategies like turning their body or repositioning materials instead, which is functionally fine for daily tasks but doesn't give them the neurological integration the activities are supposed to build. Kids with autism spectrum disorder also present a different picture. Some will avoid midline crossing because it's genuinely unsettling for them—the sensation of the hand moving across the body's center line can trigger proprioceptive confusion. Others will perform the movements perfectly but without any functional carryover to handwriting or self-care tasks. I've seen both scenarios repeatedly. For the avoidant group, gradual desensitization through bilateral activities that never actually cross the midline is a better starting point than pushing through the resistance. Another limitation worth noting: midline crossing has limited predictive value for academic outcomes. Yes, it correlates with handwriting development in typically developing children. But in clinical populations, the correlation breaks down. A child can master crossing activities and still struggle significantly with writing. The skills that matter more for handwriting are bilateral integration, proximal stability, and fine motor precision. Midline crossing is one piece of that puzzle, not the whole thing. Parents and even some therapists overestimate its importance.

If midline crossing activities aren't producing results after six to eight weeks of consistent practice, the issue is likely elsewhere in the sensorimotor system. At that point, I'd recommend evaluating vestibular function, proprioceptive processing, and core stability before continuing with the same approach. Sometimes the problem isn't the crossing activity itself—it's that the child doesn't have the postural control to support it. The bottom line is that crossing midline activities belong in occupational therapy because they address a real developmental gap. But they work best when they're part of a broader program that addresses the underlying foundations first, and when you're honest about what they can and cannot accomplish. A kid who can cross midline but can't dress themselves hasn't gained much. A kid who builds bilateral coordination and core strength first and then crosses midline as a natural byproduct of those stronger foundations is where you want to aim.