What CRRT Actually Looks Like Before You Get Certified
Continuous renal replacement therapy for nurses starts with understanding that you are running an extracorporeal circuit around the clock. The machines look intimidating at first, mostly because there are so many alarms and so many variables to adjust. After a while, you stop noticing the beeping and start noticing trends. That shift takes some time, but it does come. The training itself is usually split between classroom modules and hands-on simulation. Don't expect to be put on a real patient on day one. Most programs require you to pass a simulation evaluation first, and that's reasonable. These machines are unforgiving, and mistakes made during training hurt nobody.
CRRT Training For Nurses: What the Hands-On Component Actually Covers
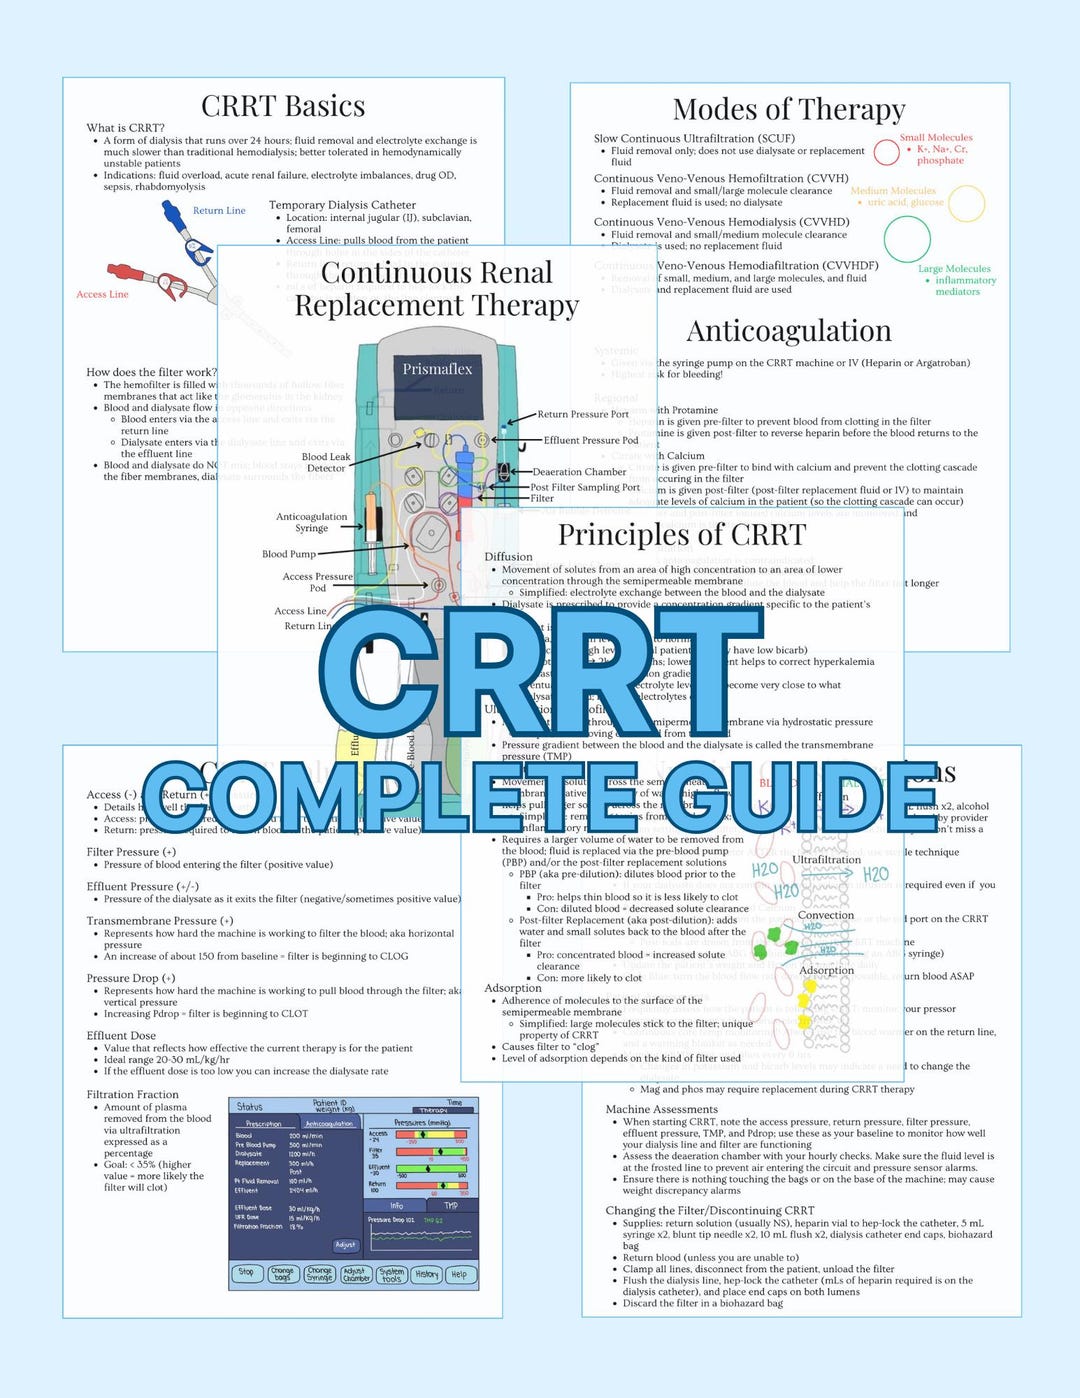
The practical sessions typically start with circuit assembly. Yes, it sounds like assembling LEGO, except every connection matters and a single kink can cost you thousands of dollars in wasted filters. You learn the order of operations: priming the circuit, bleeding out air, connecting to the vascular access, and then letting the machine do its thing. That last step is where most new nurses feel uncomfortable. You have to trust the machine while simultaneously monitoring everything else. After assembly, you move into mode selection. The three main types you will encounter are CVVH, CVVHD, and CVVHDF. Convection, diffusion, and a combination of both. The difference matters because each one clears solutes differently, and your prescriber's order will specify which is appropriate. Most hospitals default to CVVHDF now, but you should understand why. Then there is anticoagulation management, which is where things get complicated. Heparin is the old standard. Citrate is now preferred in most centers because it produces fewer bleeding complications and the circuits last longer. But citrate is not a free pass. It requires monitoring of ionized calcium levels, and if the patient has liver dysfunction, citrate can accumulate. You need to know the signs.
I once had a patient with severe cirrhosis on citrate anticoagulation whose ionized calcium rose to 2.1 mmol/L while the total calcium was also climbing. The prescriber hadn't flagged the liver failure as a contraindication risk. I caught it during a routine check and held the next dose. The resident was frustrated, but the alternative would have been worsening hypercalcemia with potential arrhythmias. That is the kind of thing training doesn't fully prepare you for because it depends on knowing the patient, not just the machine. The other major skill is alarm recognition and response. High venous pressure usually means a clot or a kinked line. Low arterial pressure often points to venous access issues or hypovolemia. Circuit pressure changes can signal problems with the blood pump or filter integrity. You learn these by repeating scenarios until the responses become automatic.
Get the Full Details
Online and Formal Program Options
The National Kidney Foundation offers web-based CRRT modules through their nephrology nursing resources. These are free and cover the fundamentals, though they do not replace hands-on training. The American Association of Critical-Care Nurses has a dedicated CRRT course that runs both online and in person, typically taking about six to eight hours depending on the format you choose. The Association for the Advancement of Medical Instrumentation also publishes educational materials specifically for nurses working with continuous therapies. Most hospitals require their own internal competency validation regardless of outside coursework. This usually involves an observation period where an experienced nurse or charge nurse watches you run a circuit from start to finish and signs off on your skills. Some institutions use standardized checklists, while others rely more on informal assessment. Either way, the requirement exists for a reason. If you are looking for a downloadable curriculum, the American Society of Nephrology occasionally makes educational materials available to member institutions, though these are generally distributed through formal partnerships rather than public download links. The Baxter and Fresenius medical care websites also host operator guides and quick reference cards that some units adopt as supplementary training materials.
What the Textbooks Don't Tell You
One thing that comes up repeatedly in practice but rarely in training manuals is the problem of circuit lifespan. The literature says citrate anticoagulation can extend filter life to 48 to 72 hours in stable patients. In my experience, the average is closer to 36 hours for acutely ill ICU patients, and sometimes much less. The variables are numerous: hematocrit, platelet count, temperature, dialysate flow rate, and the patient's inflammatory state all interact in ways that are difficult to predict. You will lose filters earlier than expected, and that is normal. The trick is recognizing when a clot is inevitable versus when you can still salvage the circuit with a small adjustment. Another counter-intuitive point is that CRRT is not necessarily gentler on blood pressure than intermittent hemodialysis for every patient. While the slower fluid removal is advantageous for most, some patients on CRRT still experience significant hemodynamic instability, particularly during the first few hours while the prescription is being fine-tuned. The machine is continuous, but that does not mean the patient is stable. You still need to monitor vasopressor requirements and fluid balance closely from the start. Electrolyte management deserves more attention than most programs give it. CRRT changes potassium, magnesium, and phosphate levels continuously, which means you cannot rely on a single daily lab draw to guide replacement fluid adjustments. Many units check basic metabolic panels every six to eight hours for the first 24 hours, then space out the draws as the patient stabilizes. I have seen patients develop hypokalemia rapidly on CRRT because the standard replacement fluid did not account for ongoing losses. The fix is adjusting the dialysate and replacement fluid potassium concentration based on trending values, not single readings.
Practical Tips That Come From Doing This Work
Keep a cheat sheet at the nurse station with the common alarm codes for the machines your unit uses. Different manufacturers organize their alarms differently, and in an emergency, you do not want to be searching through a manual. Most programs provide these, but having your own laminated copy saves time. When you are learning vascular access management, spend extra time on line care. CRRT circuits carry large volumes of blood, and any breach in sterility is a serious risk. I have seen infections traced back to a single moment of compromised technique during a filter change. The extra twenty seconds it takes to properly clean a connection point is nothing compared to the consequences of a bloodstream infection. Fluid removal calculations are another area where small errors compound quickly. If your prescription calls for 200 mL per hour of net negative balance, confirm that the machine is actually achieving that. Cross-check the numbers manually at least once per shift until you are confident in the machine's readouts. I learned this the hard way when a pump calibration error resulted in a patient receiving almost no ultrafiltration for six hours. The alarm had sounded briefly and been silenced, and nobody noticed because the display looked normal. Manual verification caught it.

Limitations of Current Training Approaches
Not all CRRT training programs are equal. Some focus heavily on machine operation while underemphasizing the clinical decision-making aspects like anticoagulation management and hemodynamic interpretation. If a program you are considering does not cover citrate anticoagulation in depth, that is a gap you should be aware of. Citrate is now the standard in most adult ICUs, and lacking competency in its use will put you at a disadvantage regardless of how well you know the machine interface. Another limitation is the shortage of simulation time. Many programs allocate only a few hours to hands-on practice, which is insufficient for building true confidence. If possible, seek out programs that offer extended simulation blocks or mentorship on the unit after formal training. The first few circuits you run independently will feel slower and more uncertain than they should, and that is okay. It improves with repetition. There is also the issue of scope of practice variability. Some regions and institutions allow nurses to adjust replacement fluid rates and anticoagulation parameters independently, while others require physician orders for every change. Understand what your facility expects before you start, and do not overstep or underperform based on assumptions. Communication with the prescriber is part of the job, and knowing when to escalate is as important as knowing how to operate the machine.
Where to Start Your CRRT Training For Nurses
Begin by checking with your unit manager or clinical educator about required and recommended programs. Most hospitals have a designated CRRT nurse specialist or champion who can guide you toward the resources your institution recognizes. Supplement that with the AACN or NKF modules for theoretical foundation, then focus your energy on the hands-on portions where you can ask questions without a real patient at risk. The knowledge sticks better when you have physically assembled a circuit and responded to simulated alarms before being responsible for one on the unit. The work is demanding but manageable with proper preparation. CRRT nurses are not replacing nephrologists, but they are the closest clinicians to the therapy throughout the day, and that position carries real responsibility. The training exists to give you the tools to handle that responsibility safely. Use it well.