What You Actually Need to Know About Head and Neck CT
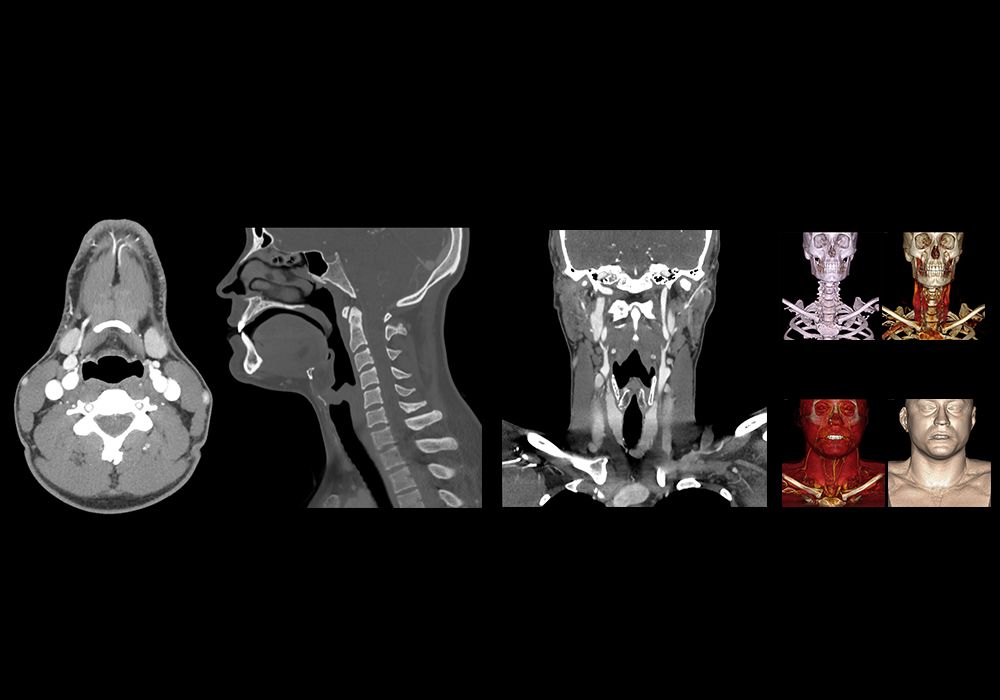
CT anatomy of the head and neck is one of those things where people memorize diagrams and then still get confused when they look at an actual scan. The problem isn't that the anatomy is complex. It's that you're looking at 2D slices and trying to build a 3D mental model while the patient is barely still and the technologist is rushing you to the next case. I'll walk through what matters practically, not what's in the textbook. The textbook gets you through an exam. Real practice is different.
Ct Anatomy Head And Neck: Where to Start
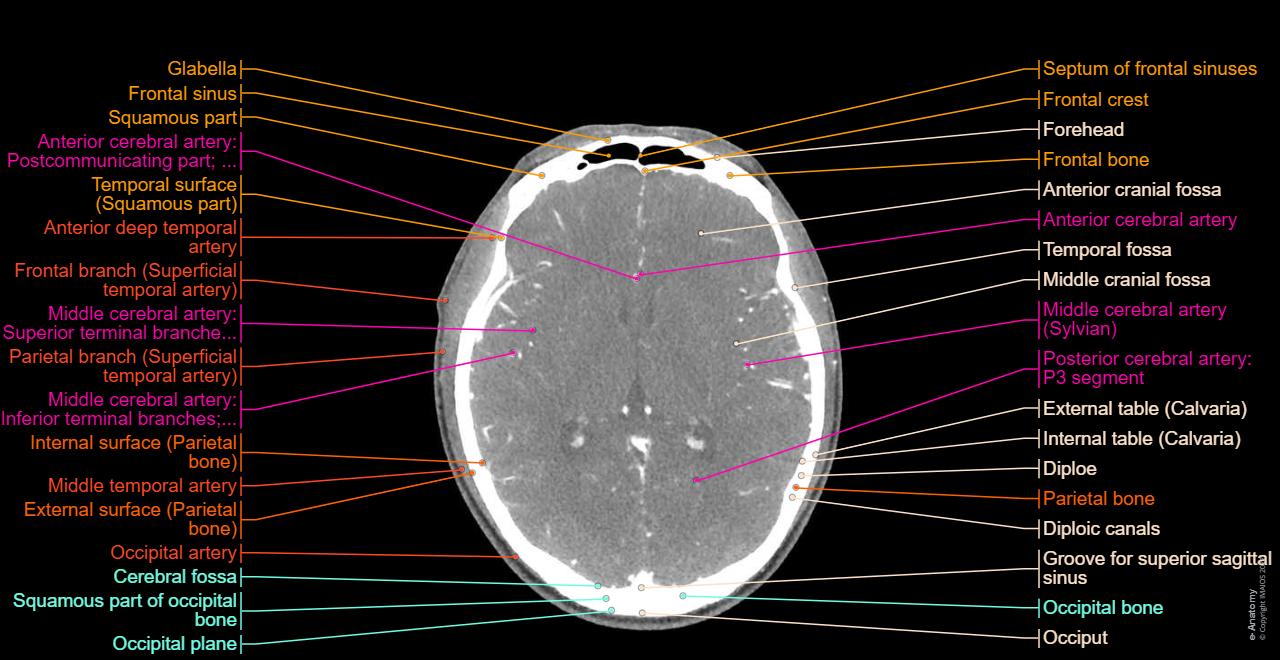
Begin with the basics and work outward. A head and neck CT typically covers from the skull vertex down to the thoracic inlet. That's roughly 30 to 40 centimeters of anatomy. You're looking at bone, soft tissue, air, and vessels all in the same field of view, which means window settings dictate what you actually see. The standard protocol splits into phases. Non-contrast comes first for trauma or acute stroke workups. Then contrast-enhanced scans in arterial and venous phases. Each phase shows something different. A glioma might be invisible without contrast. A carotid dissection needs the arterial phase. Venous sinus thrombosis requires the venous phase. Don't skip phases because the referring doctor didn't specify. You can always add them. I once had a case where a patient presented with a headache and the initial read was normal. The non-contrast looked fine. The soft tissue window showed nothing obvious. I went back and re-walked the images in bone window and noticed a tiny fracture line through the clivus that had been completely lost in the default soft tissue settings. The fracture was 1.5 millimeters. It wouldn't have shown up on MRI as clearly. Bone window saved that diagnosis. That's how easy it is to miss things when you're locked into one reconstruction.
The Anatomical Regions, Practically Speaking
Break the head and neck into zones. Each zone has its own landmarks and its own common pathologies. The skull base is where most people struggle. The foramina here are small and variable. Foramen magnum, jugular foramen, carotid canal, opt ic canal. On CT, you need axial slices no thicker than 1 millimeter for the skull base. Thicker slices and partial volume averaging turns these structures into blobs. Coronal and sagittal reformats help, but the raw data has to be there first. The middle cranial fossa holds the temporal lobes. The posterior fossa holds the brainstem and cerebellum. The petrous ridges separate them. On a good CT, you can trace the internal auditory canals, the semicircular canals, and the ossicles. These matter when you're evaluating hearing loss or facial nerve pathology. They also matter for temporal bone fractures, which I'll get to.
Get the Full Details
A counter-intuitive point: the pituitary gland often looks asymmetrical on CT. One side of the sella can appear fuller than the other. Beginners sometimes call this a microadenoma. It's usually just normal variation. Look for disruption of the pituitary stalk, not just asymmetry. If the stalk is midline and the gland enhances homogeneously, it's probably fine.
Paranasal Sinuses
The sinuses are air-filled, which makes them easy to see. The problem is that mucosal thickening is everywhere. Nearly every adult has some degree of chronic sinusitis on CT. The question is whether it's clinically significant. Opacification of the entire sinus with air-fluid levels is acute. Mucosal thickening under 5 millimeters without symptoms is usually incidental. Don't report every finding as pathology. That just creates noise. The osteomeatal complex is the drainage pathway for the maxillary, frontal, and anterior ethmoid sinuses. It's located in the lateral nasal wall. Blockage here causes recurrent sinus infections. On CT, you're looking for the uncinate process, the bulla ethmoidalis, and the semilunar hiatus. These terms mean nothing if you can't point to them on a scan. Spend time on axial cuts at the level of the maxillary sinus and trace each structure.
Orbits
Orbital CT uses thin cuts, usually 1 to 2 millimeters, because the extraocular muscles and optic nerves are small. The orbit has four walls and four rectus muscles. The optic nerve runs through the optic canal into the cavernous sinus. A crushed optic nerve from trauma looks like a discontinuity or hematoma around the nerve sheath. On non-contrast scans, you're looking for blood, fracture, or nerve swelling. Here's something that trips people up: the inferior ophthalmic vein can be prominent in normal scans, especially in children and young adults. Don't mistake a normal variant vein for an orbital mass. Follow it to its termination. If it drains into the superior ophthalmic vein and then the cavernous sinus, it's just a vein.
Nasal Cavity and Parapharyngeal Space
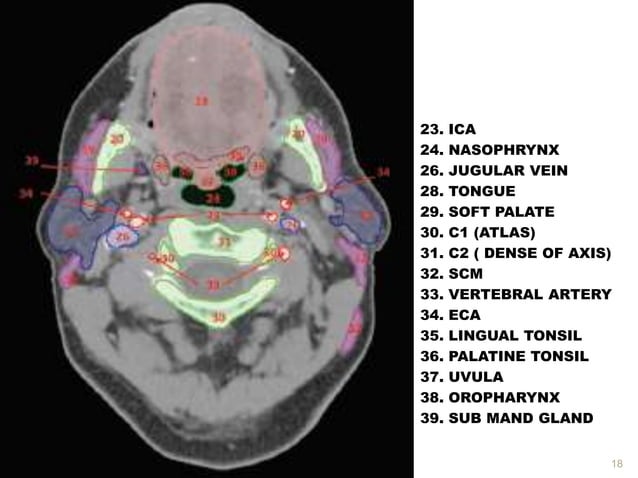
The nasal cavity sits between the septum and the turbinates. The inferior, middle, and superior turbinates are normal structures. Hypertrophic turbinates can cause obstruction, but again, correlate with symptoms. A deviated septum is almost always present to some degree. The parapharyngeal space is a fat-filled compartment lateral to the nasopharynx and oropharynx. It contains the internal carotid artery, internal jugular vein, and the sympathetic chain. Masses in this space displace the vessels. An anterior displacement of the carotid suggests a parotid or periparotid origin. Posterior displacement suggests a deep lobe parotid or retropharyngeal process. This spatial relationship is more useful than any single measurement.
Salivary Glands
The parotid is the largest salivary gland, wrapping around the mandibular ramus. It's divided into superficial and deep lobes by the plane of the facial nerve. On CT, the facial nerve itself is rarely visible unless it's enlarged or there's a mass around it. You infer its course by the split between the two lobes. The retromandibular vein marks the boundary. The submandibular gland sits in the submandibular triangle, below the mylohyoid muscle. It's smaller than the parotid but easier to identify because it's surrounded by fat. The sublingual glands are tiny and often overlooked on CT unless you're specifically looking for sialoliths or inflammation. A practical note: sialolithiasis is more common in the submandibular gland than the parotid, despite the parotid producing more saliva. The submandibular duct is longer, runs uphill, and the saliva is more alkaline and mucinous. Stone formation follows those facts. If you're looking for stones, the submandibular duct at the floor of the mouth is the first place to check.
Pharynx and Larynx
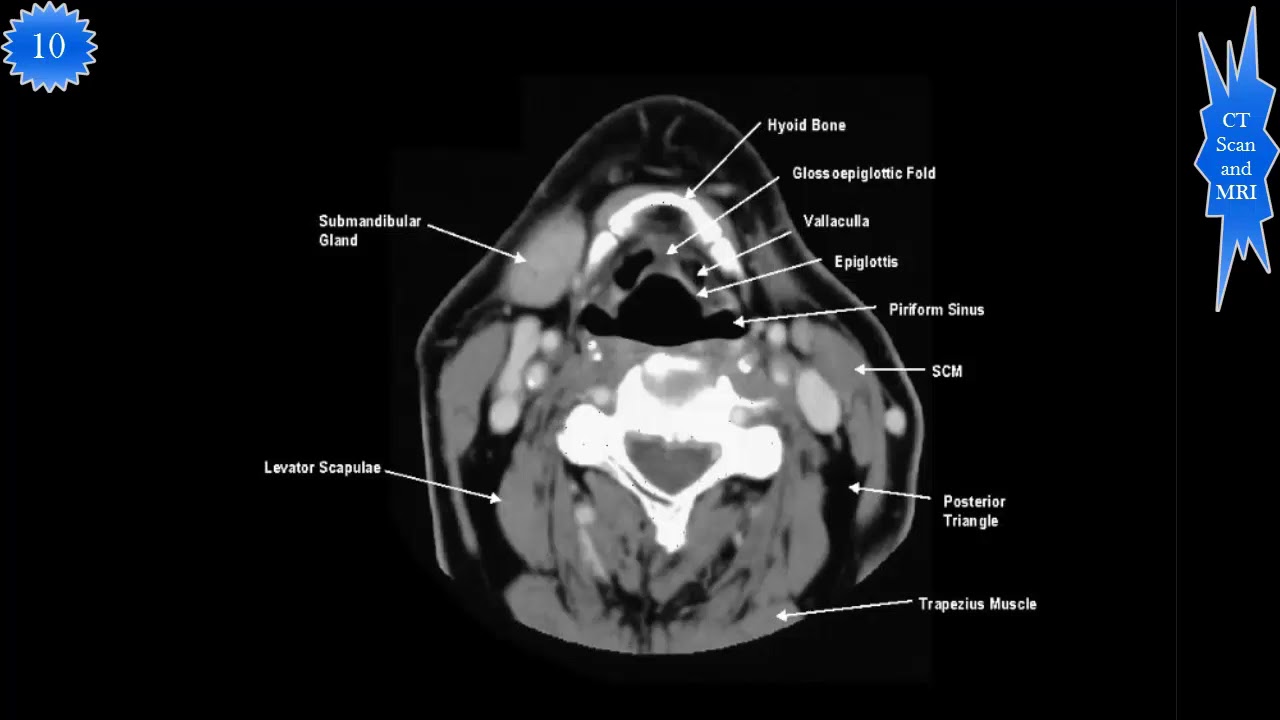
The pharynx connects the nasal and oral cavities to the esophagus and larynx. It's divided into nasopharynx, oropharynx, and hypopharynx. The nasopharynx has the adenoids and the torus tubarius, which is the cartilaginous opening of the Eustachian tube. Enlarged adenoids are normal in children and should not be reported as pathology in a pediatric scan. The oropharynx includes the base of tongue, palatine tonsils, and posterior pharyngeal wall. Tonsillar hypertrophy can be asymmetric, and asymmetry here raises suspicion for malignancy more than it does in the nasopharynx. A tonsil that is noticeably larger than the contralateral side with irregular enhancement deserves a closer look. The larynx has three levels: supraglottis, glottis, and subglottis. The vocal cords are the glottis. They appear as thin soft tissue bands on axial CT. Supraglottic structures include the epiglottis, aryepiglottic folds, and false vocal cords. Laryngeal cancers often start in the glottis and spread along the mucosal surfaces before they become masses. Early glottic cancer can look like subtle asymmetry of the vocal cord contour. If one cord looks thicker or less mobile, consider laryngoscopy even if the CT doesn't show a clear tumor.
Vascular Structures
The carotid arteries bifurcate at the level of C2 to C4, which is approximately at the angle of the mandible. The internal carotid enters the skull through the carotid canal in the petrous temporal bone. The external carotid supplies the face and scalp. On contrast-enhanced CT, you can trace both from the common carotid bifurcation all the way to the cavernous sinus. The jugular veins run alongside the carotids in the carotid sheath. The internal jugular is larger and more lateral. Jugular bulb variants exist. A high-riding jugular bulb can extend into the mastoid air cells and mimic a glomus tumor. If you see a rounded enhancing structure in the promontory region, check whether it connects to the jugular vein on adjacent slices. If it does, it's a variant, not a tumor. Carotid stenosis is graded on CT angiography using the North American Symptomatic Carotid Endarterectomy Trial criteria. Less than 50 percent is mild. Fifty to sixty-nine percent is moderate. Seventy to ninety-nine percent is severe. Complete occlusion is, obviously, complete. The tricky part is distinguishing severe stenosis from near-occlusion. In near-occlusion, the distal vessel appears tiny because of the reduced flow. This can be mistaken for a chronic total occlusion. Look for a tapered narrowing rather than an abrupt cutoff.
Cervical Spine
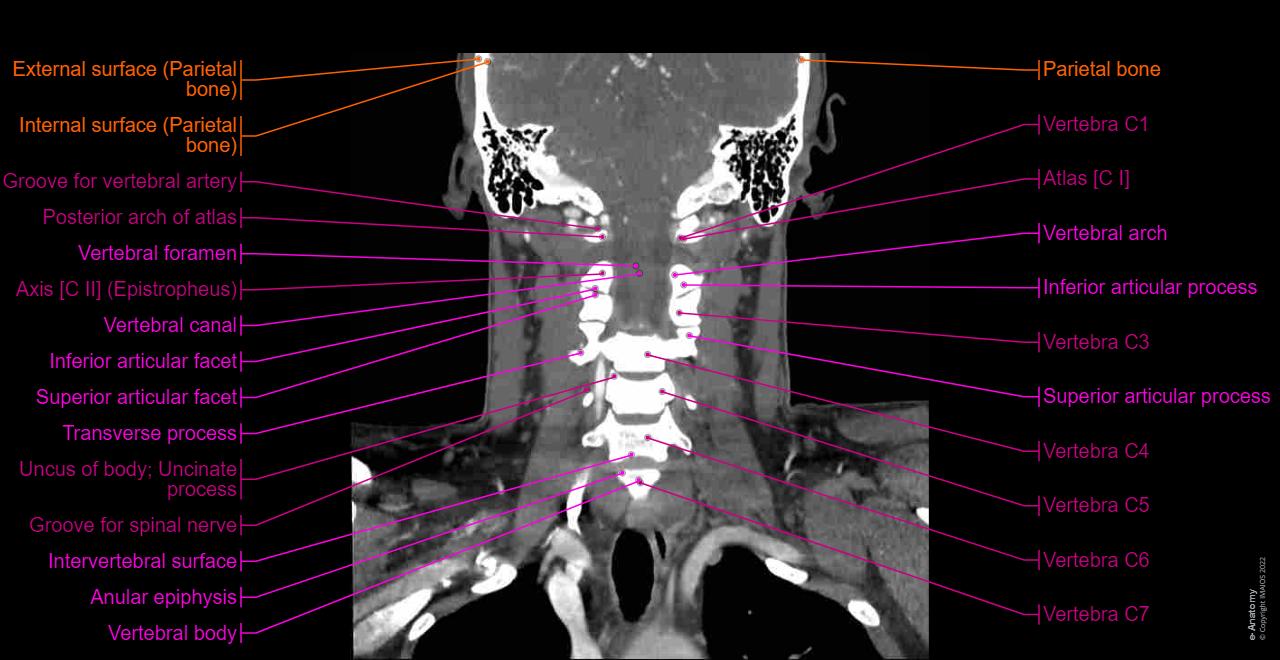
The cervical spine has seven vertebrae. The unique ones are C1 (atlas) and C2 (axis). C1 has no body. C2 has the dens, which articulates with C1. Fractures of the dens are common in falls, especially in older adults. Type II dens fractures, at the junction of the dens and the body of C2, have the highest nonunion rate. On CT, look for a clear fracture line through the narrowest part of the dens. Even a 1-millimeter displacement matters. The spinal canal at C1 and C2 is wider than below. A epidural hematoma that would cause severe compression at C5 might be tolerated at C1. Don't apply the same severity threshold across all levels.
Artifacts and Pitfalls
Dental amalgam creates streak artifacts that can completely obscure the oropharynx and upper cervical spine. This is one of the most common problems in head and neck CT. The workaround is simple: ask the patient to remove dentures if possible, position the head to minimize the artifact path through the region of interest, and use iterative reconstruction if your scanner supports it. Iterative reconstruction reduces streak artifacts significantly compared to filtered back projection, and it doesn't require a dose increase. Motion artifact is harder to deal with. Confused, agitated, or dyspneic patients move. A single bad series can ruin an otherwise good study. If you catch motion during the scan, rescan immediately. The patient is already on the table. It takes thirty seconds. Don't send them back and hope for a better result later. Beam hardening from the petrous temporal bones can create dark bands across the posterior fossa. This makes cerebellar and brainstem evaluation difficult. Shift the reconstructed image slightly anterior or use a higher keV reconstruction. Modern dual-energy CT systems can generate virtual monoenergetic images at 140 keV, which effectively eliminates this artifact.
When CT Isn't the Right Tool
CT is excellent for bone, acute hemorrhage, and calcifications. It's fast, widely available, and relatively inexpensive. It's not great for early ischemic stroke within the first few hours, for marrow pathology, or for delineating tumor margins in the sinonasal tract. MRI is superior in all three cases. If the clinical question is "is there a malignancy invading the skull base," CT gives you bone detail but misses soft tissue extension. MRI shows the soft tissue invasion but is less precise about cortical bone destruction. Often you need both. A specific scenario where CT fails: evaluating the cranial nerves. The trigeminal, facial, and vestibulocochlear nerves are too small and too close to bone to be reliably seen on standard CT. If you need to assess these nerves, order an MRI with dedicated internal auditory canal protocols. Don't waste the patient's time with a CT and then tell them they need an MRI anyway.
Protocol Recommendations
For trauma: non-contrast head CT plus a dedicated facial bone and cervical spine protocol. If there's suspicion of vascular injury, add a CTA of the neck. Use 1 millimeter slices for the face and spine. Use 5 millimeter slices for the brain non-contrast. This cuts scan time and keeps radiation reasonable. For oncology staging: contrast-enhanced CT from skull base to thoracic inlet. Arterial and venous phases. Slice thickness of 2 to 3 millimeters through the primary tumor site. Thinner slices through the neck nodes. This gives you enough detail for nodal staging without blowing the dose. For sinus disease: non-contrast thin-section axial CT through the sinuses. Coronal reformats are essential. Coronal images show the osteomeatal complex better than axial images because they align with the natural drainage pathways. Axial images are better for evaluating the skull base and orbital apex.
Reading Strategy
Don't read left to right, top to bottom. That's efficient for the computer but not for pattern recognition. Pick a landmark and work outward. For a brain scan, start at the tentorium. Move up to the lateral ventricles, then the cortex. Move down to the posterior fossa. For a neck scan, start at the hyoid bone and work up to the skull base, then down to the thoracic inlet. Consistency prevents skipping structures. Always compare to prior studies if available. A subtle asymmetry that looks new might be old. A known lesion that has grown one millimeter over two years is probably stable. Without priors, you're guessing. With priors, you're reading. The single most useful thing you can do is develop a mental checklist that you run through every single study, regardless of the referral reason. Trauma protocol. Stroke protocol. Tumor protocol. They overlap but they're not identical. A checklist prevents the kind of error where you're looking for a fracture and miss a subdural, or you're looking for a bleed and miss a subtle mass. The checklist is boring. Boring keeps you safe.