Working With Labeled CT Chest Anatomy
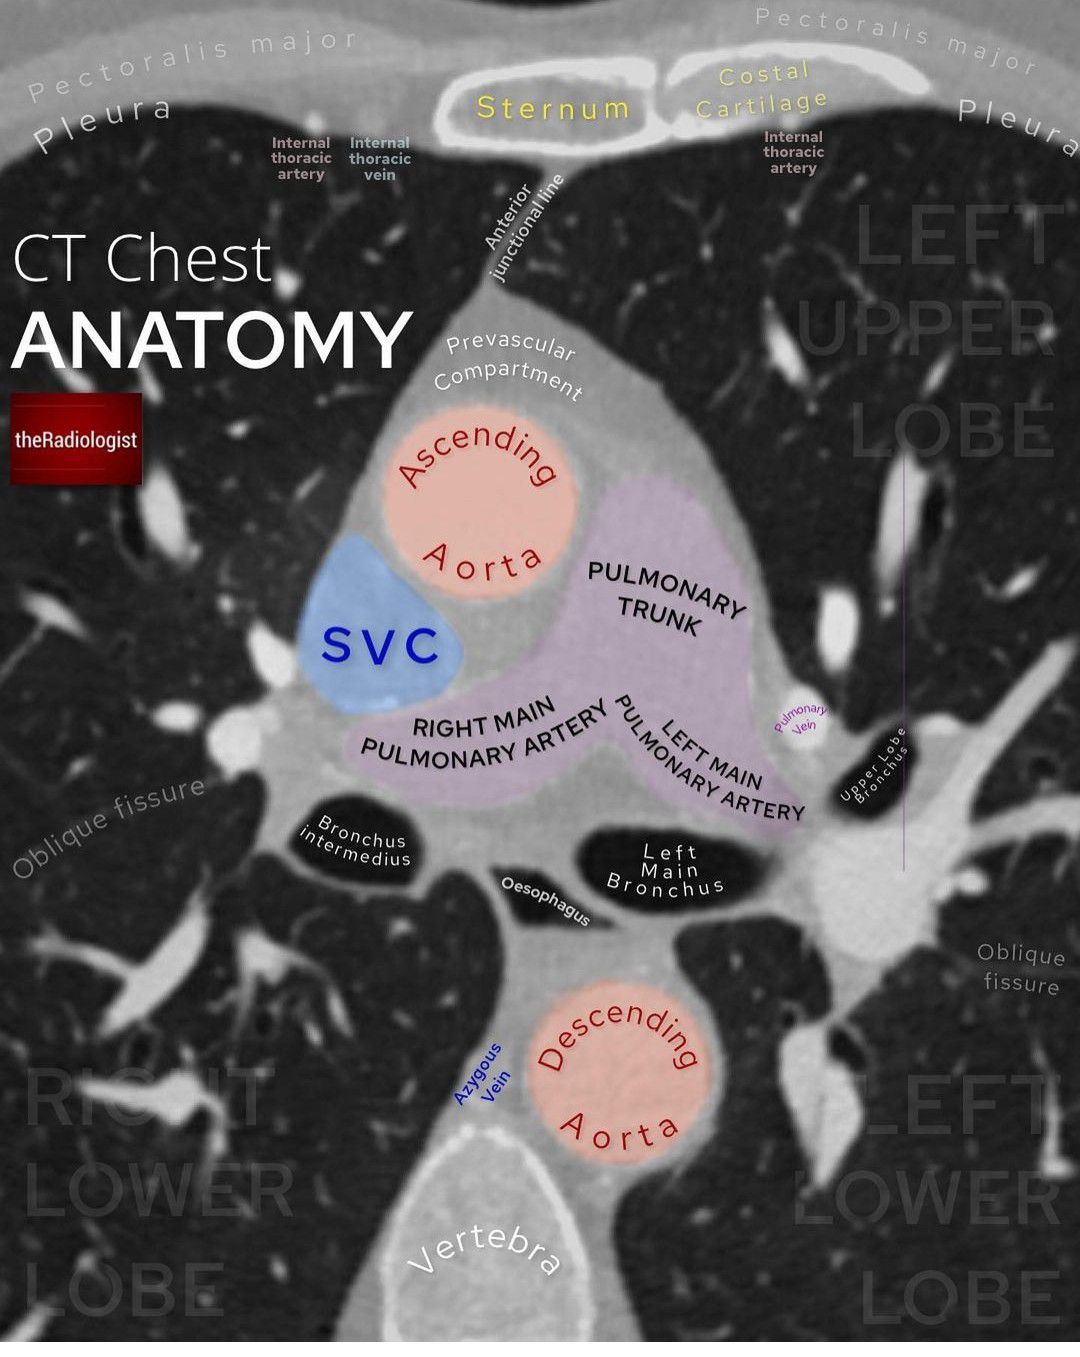
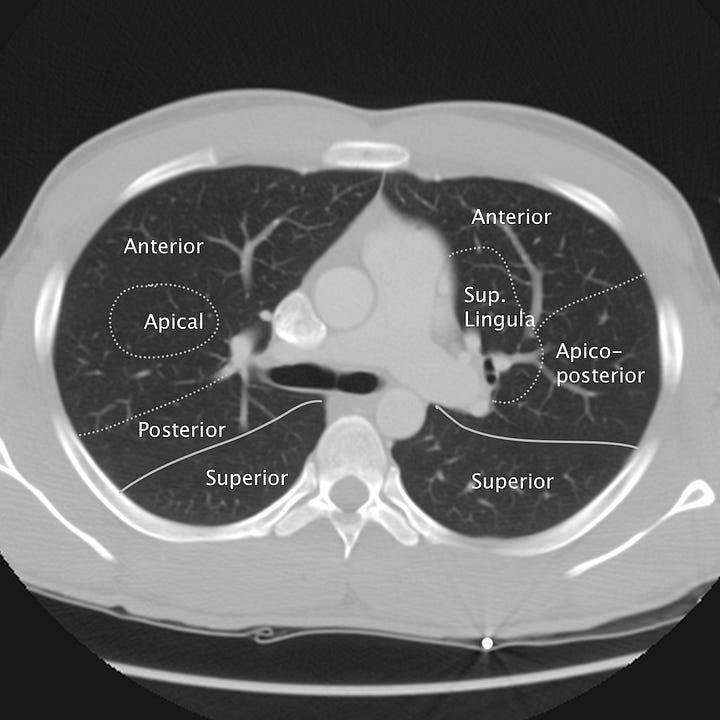
I spent years reviewing thoracic CTs before I ever got involved in the annotation side of things. What made the transition rough wasn't the anatomy itself. It was understanding how labels actually get attached to pixels and what happens when the data doesn't match the textbook. Most people start with standard axial images and work outward from there. That approach has a real blind spot I'll get to. A Ct Chest Anatomy Labelled dataset is fundamentally a collection of DICOM slices where structures have been mapped to specific regions. The standard structures you will encounter include the lungs with their lobes, the heart chambers, the great vessels, the trachea and main bronchi, the esophagus, the ribs, vertebrae, and the diaphragm. Some annotations go further and label pulmonary nodules, lymph node stations, and pleural surfaces. The format you use determines everything about how usable the result ends up being.
Ct Chest Anatomy Labelled - Where People Actually Start
The most common format you will run into is NIfTI with a separate segmentation mask, usually paired with a JSON file that maps each label ID to an anatomical name. You also see STIRADO, MHD, and standalone DICOM-RT Structure Sets. Each has its own quirks. The DICOM-RT format is technically part of the DICOM standard and can be opened in most PACS systems, but the coordinate system it uses is origin-based and flips in ways that confuse anyone who only thinks in standard radiological orientation. I learned that the hard way. Here is the problem I ran into repeatedly. A colleague sent me a Ct Chest Anatomy Labelled set from an external vendor. Everything looked fine when I opened it in 3D Slicer. The lungs, heart, and spine aligned correctly on the axial slices. But when I exported the contours back to DICOM-RT and loaded them into our clinical Radiology workstation, the left lung was mapped to the right side of the image and the spine labels were inverted. The dataset was generated in neurological convention where the patient is supine with the left side on the viewer's left, which is the opposite of how clinical CTs are displayed. I spent two hours writing a Python script to flip the X-axis coordinates before the masks would align correctly in the clinical environment. The fix is straightforward once you know to check the PatientOrientation field in the DICOM header, but nobody warns you about it upfront.
The Actual Labeling Process
If you are creating a labeled dataset yourself, the workflow breaks down into four practical stages. Stage one is DICOM ingestion and quality control. You pull the raw CT series from the archive and verify that the slice thickness is consistent. Gaps larger than two millimeters between slices will ruin any volumetric segmentation. I usually reject any series with slice spacing over three millimeters unless I am explicitly doing a low-resolution screening study. Stage two is organ-level segmentation. You label the gross anatomy first. The lungs are relatively straightforward since the air-tissue interface creates high contrast. The heart is where things get messy. The pericardium is barely visible on most standard chest CTs without contrast, and the boundary between the right atrium and the inferior vena cava can be nearly indistinguishable from a pericardial effusion if you are not looking carefully. I typically trace the epicardial fat plane as my guide rather than trying to see the pericardium directly. It is more reliable. Stage three covers the finer structures. Bronchi, pulmonary arteries, and the esophagus require you to work slice by slice because these structures are small and often collapsed or compressed by adjacent vessels. The mediastinal window settings are mandatory here. Lung window settings will make the mediastinal structures disappear almost entirely. I use a window width of 350 and a level of 50 for mediastinal structures. That is standard but worth stating because people skip it.
Get the Full Details

Stage four is validation. You rotate through axial, coronal, and sagittal planes and check for continuity. A common error I see is a label that jumps between adjacent structures because the annotator lost track of a specific bronchus across five slices. The label will look fine in one plane and completely wrong in another. This is why multiplanar verification is not optional. It usually adds about twenty minutes to a full-case annotation but prevents the kind of error that makes an entire dataset unusable for model training.
Common Pitfalls That Waste Time
Beginners almost always under-segment the lung apices and costophrenic angles. The apex is small on individual slices and easy to skip when you are moving quickly through a stack. The costophrenic angle gets missed because the diaphragm and chest wall merge visually at the periphery. Both areas are clinically significant. Missed apical pathology is a well-documented source of delayed lung cancer detection. I mark those regions separately and do a second pass focused only on them before I finish any case. Another issue is inconsistent labeling of the hilar structures. The right and left hila contain different combinations of arteries, veins, and bronchi. The right hilum has the superior pulmonary vein anteriorly and the ascending bronchus posteriorly. The left hilum sits higher because the left pulmonary artery arches over the left main bronchus. Beginners often swap these or label everything in the hilum as a single mass. For a labeled dataset meant for training purposes, this level of imprecision propagates errors through whatever model consumes it. I make sure each hilar component gets its own separate label rather than a generic hilar region tag. Contrast timing matters more than people admit. A non-contrast chest CT and a contrast-enhanced one will look completely different for vascular structures. If you are building a generalized labeling tool or dataset, mixing contrast and non-contrast studies without marking the phase will create confusion. The ascending aorta on a non-contrast scan has a Hounsfield unit value around 40 to 60. On a contrast-enhanced arterial phase scan, it is typically 300 to 400. These values overlap with calcified plaque and thrombus, which means threshold-based automated segmentation fails frequently in the mediastinum regardless of how good the algorithm claims to be.
What This Approach Does Not Handle Well
Labeled CT datasets struggle with pathological anatomy. Standard anatomical labels assume normal structure. When the heart is enlarged, the pericardium distended, or the lungs consolidated, the labels break down or become misleading. A segmentation trained on labeled normal anatomy performs poorly on pleural effusions, pneumonectomy cavities, or massive lymphadenopathy. I have seen datasets claim highDice scores and then fail completely on any chest that deviates from typical presentation. This is a fundamental limitation of supervised segmentation approaches and it affects anyone planning to use labeled data for clinical deployment rather than just research. Another limitation is inter-annotator variability. Two experienced radiologists will produce noticeably different segmentations of the same heart, particularly around the atria and the great vessels. The differences are small in volume but structurally significant. If you are building a ground-truth dataset, you need at least two independent annotators and a conflict resolution step. Single-annotator datasets introduce bias that is difficult to detect later. I usually aim for a second pass by a different annotator on roughly a third of all cases and reconcile the differences. It doubles the labeling time for those cases but catches systematic errors early.

Where to Find Existing Labeled Data
The largest publicly available resource is the LiTS challenge dataset, which includes abdominal and thoracic structures with segmentation masks. The MICCAI NTIRE and CHAOS challenges also release labeled datasets periodically. For purely thoracic anatomy, the Kaggle chest CT dataset with accompanying segmentations is widely used, though the label quality varies significantly between contributors. The SegTHOR challenge provides a focused benchmark for esophagus, heart, and aorta segmentation specifically. If you need whole-lung lobe segmentation, the LUNA16 dataset includes nodule annotations alongside some lung volume data, but it is not a comprehensive anatomical labeling resource. If you are looking for a ready-made Ct Chest Anatomy Labelled resource to start with, the MSD (Medical Segmentation Decathlon) thorax dataset is probably the most complete free option. It includes lung, liver, and kidney structures with manually annotated masks. The labeling protocol is documented, which helps when you need to understand exactly what each label represents. Download times vary depending on whether you pull the full dataset or just the thoracic subset. The full dataset is roughly thirty gigabytes. The thoracic portion is closer to eight gigabytes.
Practical Tips That Actually Matter
Use a graphics tablet if you are doing manual annotation. Mouse-based tracing on fine structures like bronchi and pulmonary vessels is slow and inaccurate. A basic Wacom tablet reduces annotation time by about forty percent and improves boundary precision noticeably. This is one of those things that sounds minor but makes a real difference over hundreds of cases. Always save intermediate progress. Annotation software crashes. Projects corrupt. I have lost entire labeling sessions when the application updated mid-export and corrupted the output file. I save every fifteen minutes now. It adds maybe thirty seconds per case but has prevented multiple total data losses. Document your labeling conventions in a separate text file before you start any project. Define exactly what each label ID means, what slice thickness you are accepting, and what you do when structures are ambiguous. Without this, you will spend hours later trying to remember why label seven corresponds to the left pulmonary artery instead of the left main bronchus. I learned that the hard way on a project that required six months of retrospective clarification.
If you need automated assistance rather than manual annotation, tools like 3D Slicer with the Segmentation extension, ITK-SNAP, and MONAI Label are the standard options. MONAI Label is particularly useful if you are already working in a PyTorch pipeline because it integrates segmentation models directly into the annotation workflow. The model proposes contours and you refine them. This approach is faster than pure manual tracing but still requires careful review. Automated labels are not automatically correct labels. The hardest part of working with labeled CT data is not the software. It is developing the spatial understanding to recognize when a label is wrong before it gets baked into your dataset. You learn that by looking at thousands of slices across multiple planes until the anatomy becomes automatic rather than something you have to consciously map onto the image. There is no shortcut around that. It just takes time and a willingness to question every label you produce.