What Actually Happens When You Bill a CT Guided Biopsy
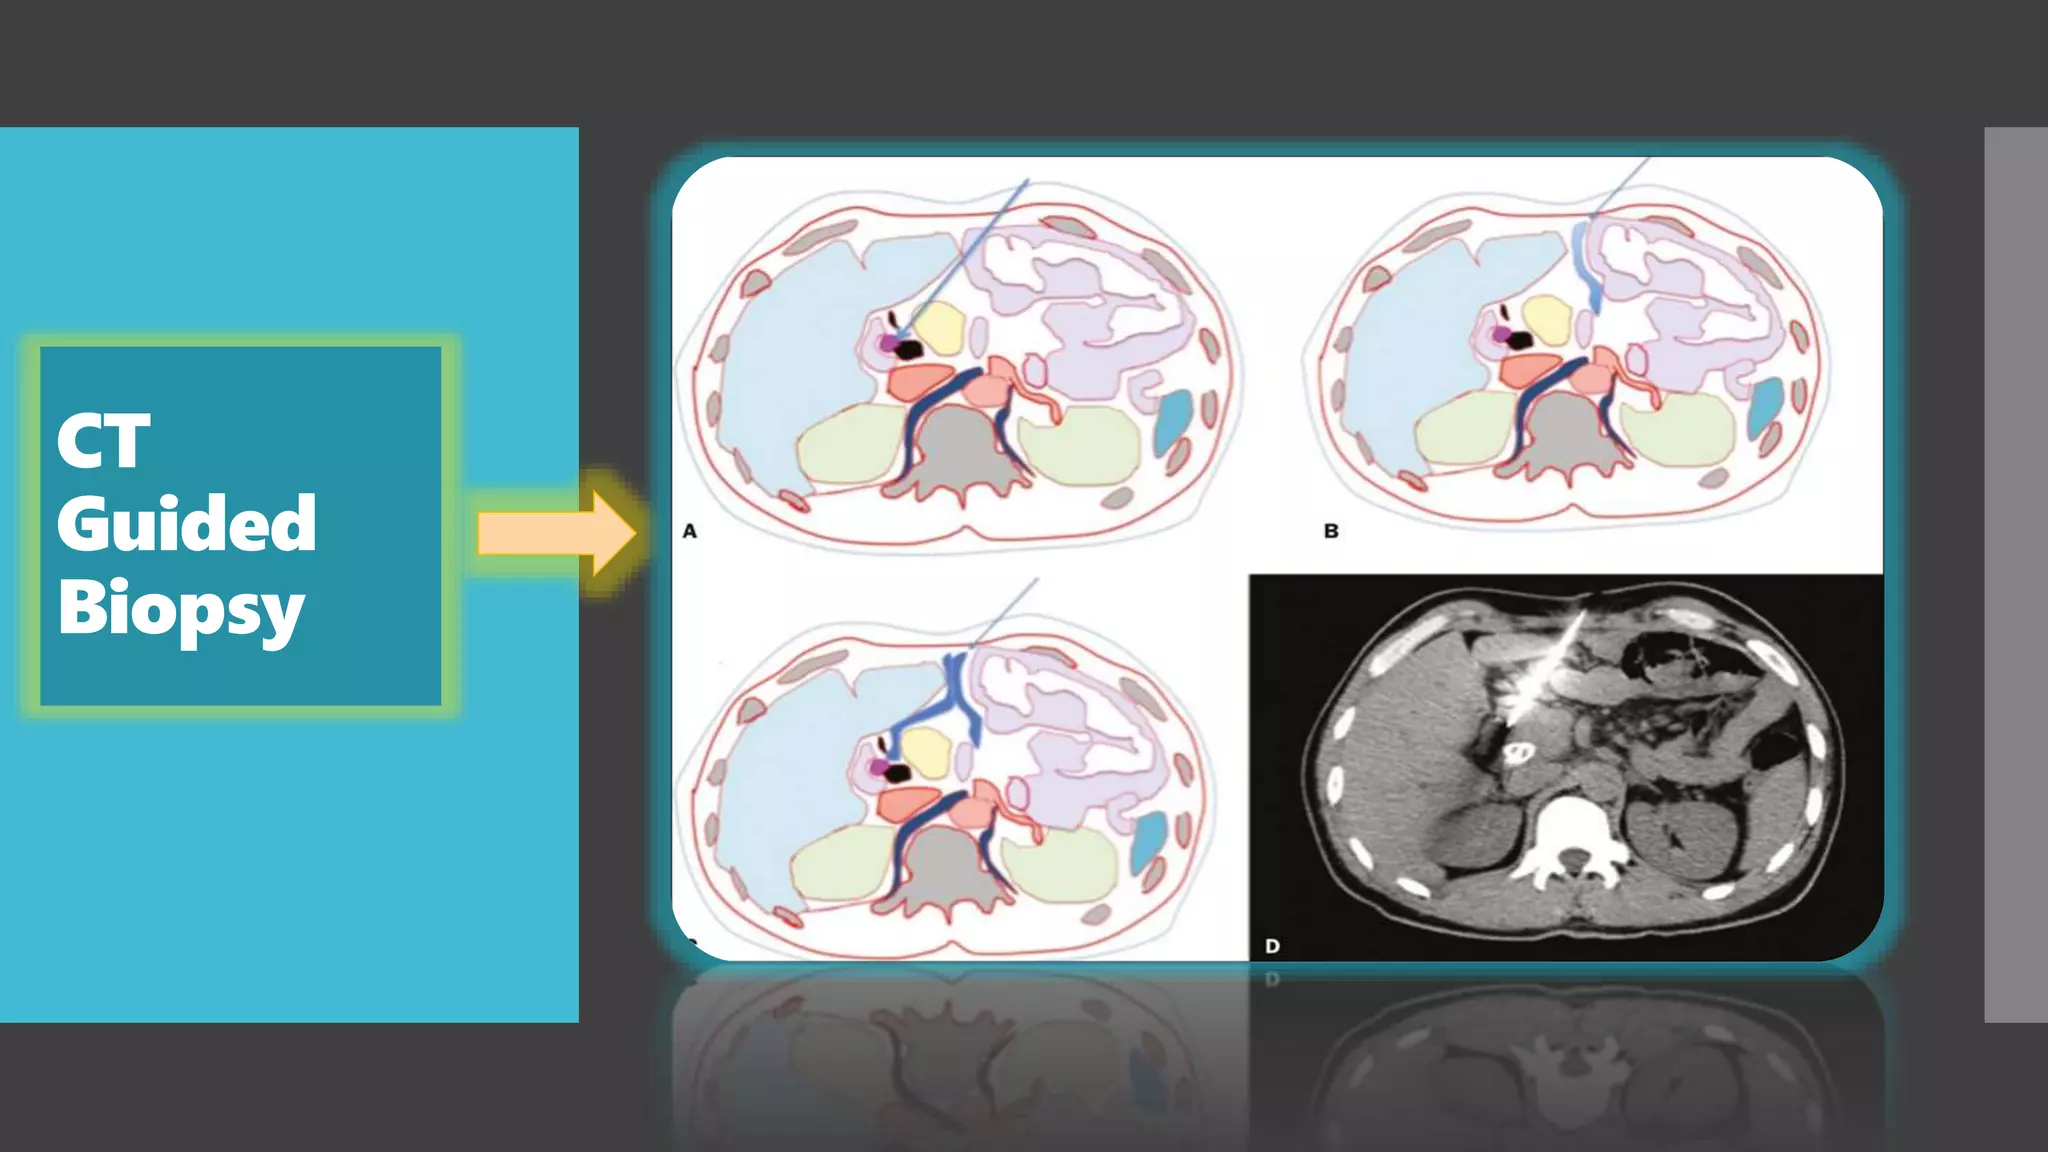
The first thing you need to understand is that CT guidance is rarely its own line item anymore. Most of the biopsy CPT codes include image guidance by default, which is why people get confused when they see separate codes floating around. I spent three years working with a radiology practice that kept billing 76942 alongside every single CT-guided biopsy, and we got audited hard for it. The guidance component is bundled into the primary procedure code in almost all cases unless you are specifically dealing with certain cardiovascular or intracranial procedures where 76942 still has limited standalone applicability. Let me lay out the actual code landscape the way it exists in current practice rather than some textbook version that hasn't been updated since 2021.
Ct Guided Biopsy Cpt Code Overview by Anatomic Site
Here is how the billing actually breaks down in a typical interventional radiology or radiology department. Soft tissue masses: 27096 covers percutaneous needle biopsy of deep soft tissue of the trunk, arms, or legs with image guidance. 27097 is the same but without image guidance, which means if you used CT, you use 27096. The difference matters. I once had a surgeon try to bill 27097 for a CT-guided biopsy of a retroperitoneal mass because he thought the code description didn't specifically say CT. It does not need to say CT. Image guidance is included in 27096 regardless of whether it is CT, ultrasound, or fluoroscopic. Abdomen and pelvis: 44001 and 44002 cover percutaneous needle biopsy of intra-abdominal or pelvic mass with and without image guidance respectively. Same logic applies. If you used CT guidance, you bill 44001. These codes are often confused with laparoscopic codes, so double check the descriptor before submitting anything. I had a claim denied on a 44001 because the surgeon documented "diagnostic laparoscopy" in the operative note even though the actual procedure was a CT-guided needle biopsy through the flank. The coder caught it before it hit the payer, but it was a close call.
Lung and pleura: 32097 is the workhorse code for CT-guided needle biopsy of lung or pleural lesion. It covers transpleural approach with image guidance. The key detail people miss is that this code includes the CT guidance portion. You do not add 76942 on top of it. A 2023 audit I was involved in found that over 40 percent of providers in our network were illegally bundling 76942 onto 32097 claims. The payer recovered about $180,000 from that single finding across just twelve providers. Prostate biopsies: This is where it gets messy. 55700 is transperineal prostate biopsy without image guidance, and 55875 is transperineal prostate biopsy with image guidance. Most CT-guided prostate biopsies fall under 55875. But if you are doing a multiparametric MRI-CT fusion biopsy, you still use 55875. Some payers have started requiring CT or ultrasound guidance documentation in the note rather than just MRI fusion, so make sure your procedure note specifies the imaging modality used for real-time guidance. I ran into a payer in Indiana that rejected 55875 claims when the documentation only said "MRI fusion guided" without mentioning CT or US at any point during the needle passes. They wanted to see the CT component documented explicitly even though MRI fusion is an accepted guidance method. Adrenal and renal masses: 44001 covers adrenal biopsy when it is intra-abdominal. Renal mass biopsies can use 55995 for percutaneous needle biopsy of kidney with image guidance, though some payers still prefer 50200 which is percutaneous renal biopsy, needle or tube, with image guidance. The 50200 code is older and less commonly used now. Many payers have dropped it from their fee schedules entirely. Check your local Medicare Administrative Contractor's coverage policy before relying on 50200. It gets denied more often than you would expect for a code that technically still exists.
Get the Full Details

Bone marrow: 38220 is bone marrow biopsy and aspiration, percutaneous, with image guidance. This one is straightforward. If you use CT guidance, it is included. If you do not use any image guidance, you still use 38220 because it is the only percutaneous bone marrow biopsy code available. The "with image guidance" language in the descriptor is somewhat misleading because the code itself does not require guidance to be billed.
Common Pitfalls That Will Get Your Claims Denied
I want to talk about something that comes up constantly and costs practices real money every quarter. The first mistake is using the wrong guidance code when the biopsy code already includes it. 76942 is the CT guidance code and it is bundled into nearly every percutaneous biopsy code I just listed. You cannot bill it separately for soft tissue, abdominal, pulmonary, or prostatic biopsies. The only time 76942 has any legitimate standalone billing is for certain vascular access procedures and a handful of other specific interventions where the primary CPT does not already contain guidance. Even then, many payers bundle it anyway. The second mistake is documenting the guidance inadequately. I had a case last year where a provider did a perfectly fine CT-guided biopsy of a liver lesion using 44001. The procedure went smoothly. The needle was placed under CT guidance. The specimen was obtained. The only problem was the operative note said "biopsy performed under imaging guidance" without specifying CT, ultrasound, or fluoroscopy. The payer pulled it for medical review and denied it because the documentation did not support the image guidance component of 44001. The provider had to appeal with a copy of the actual CT images showing the needle track. It took four months to get paid. The third mistake is bundling multiple biopsy codes for the same anatomical site. If you biopsy two separate lesions in the same muscle group during the same session, some payers will pay both 27096 codes, some will only pay the first one, and some will downgrade the second to an unlisted code. There is no universal rule. You need to check your specific payer policies before you start billing multiples. I worked with a practice in Texas that billed three 27096 codes for three separate deep soft tissue biopsies in the right thigh during one session. Two of the three were denied. The payer's policy only covered one per anatomical region per session. They reclassified the second and third as diagnostic and reduced the payment by 60 percent.
A Specific Edge Case I Ran Into
Here is a scenario that tripped me up recently and one I have not seen discussed in any coding newsletter. We had a patient with a suspected metastatic lesion in the psoas muscle. The interventional radiologist planned a CT-guided needle biopsy. Standard approach. We used 27096. The procedure went fine. The specimen came back positive for metastatic disease. The referring oncologist then wanted a second biopsy of a different lesion in the left psoas muscle two weeks later during the same calendar session. We billed another 27096 with modifier 59 to indicate a distinct procedural session. The payer denied it, saying the bilateral psoas muscles constitute the same anatomical region and modifier 59 does not apply. We appealed with a letter from the attending physician explaining that the two lesions were in separate muscle bellies on opposite sides with different clinical indications. The appeal was denied at the first level, then granted at the second level after we provided the actual CT images showing the anatomical separation. It took six months and three months of our revenue cycle staff time. If you are dealing with bilateral biopsies of the same anatomical region, modifier 59 is not a reliable safety net. You need to document clear anatomical distinction and be prepared to appeal. I should mention that CT guidance is not always the best option and billing it when ultrasound would have been more appropriate can raise red flags with certain payers. For superficial lesions, thyroid nodules, breast lesions, and many lymph node biopsies, ultrasound is the standard of care and the preferred guidance modality. Some commercial payers now have medical necessity criteria that require ultrasound first for accessible lesions. If you jump straight to CT for a lesion that is clearly visible on ultrasound, you risk a medical necessity denial, not a coding denial. The code itself may be correct, but the payer can still deny payment on medical necessity grounds. For breast lesions specifically, 19080 through 19082 are the relevant codes and they are ultrasound-guided by default in most payer policies. CT-guided breast biopsy is extremely rare and would typically fall under an unlisted code with a special pre-authorization. Do not attempt to bill 19080 for a CT-guided breast biopsy. It will not work.

Practical Takeaways
Pick the primary biopsy CPT code based on the anatomical site and approach, not on the imaging modality. The image guidance is included in almost all of them. Verify whether your payer bundles 76942 into the primary code before billing it separately. Document the imaging modality explicitly in the procedure note, not just "imaging guidance." Check payer policies before billing multiple biopsies in the same anatomical region. Do not use CT guidance as a default when ultrasound is adequate and preferred. And always verify the current CPT descriptors before every billing cycle because these codes change more frequently than most people realize.