What You Need to Know About Fatty Oval Bodies in Urinalysis
Fatty oval bodies are a standard finding in microscopic urinalysis. They show up when lipid material breaks down into rounded structures within the urinary tract. Most people encounter them while reviewing a urine sediment slide and immediately think nephrotic syndrome. That assumption isn't wrong, but it's incomplete. The presence of these bodies tells you there's lipid in the urine, but it doesn't tell you why.Cuerpos Ovales Grasos En Orina
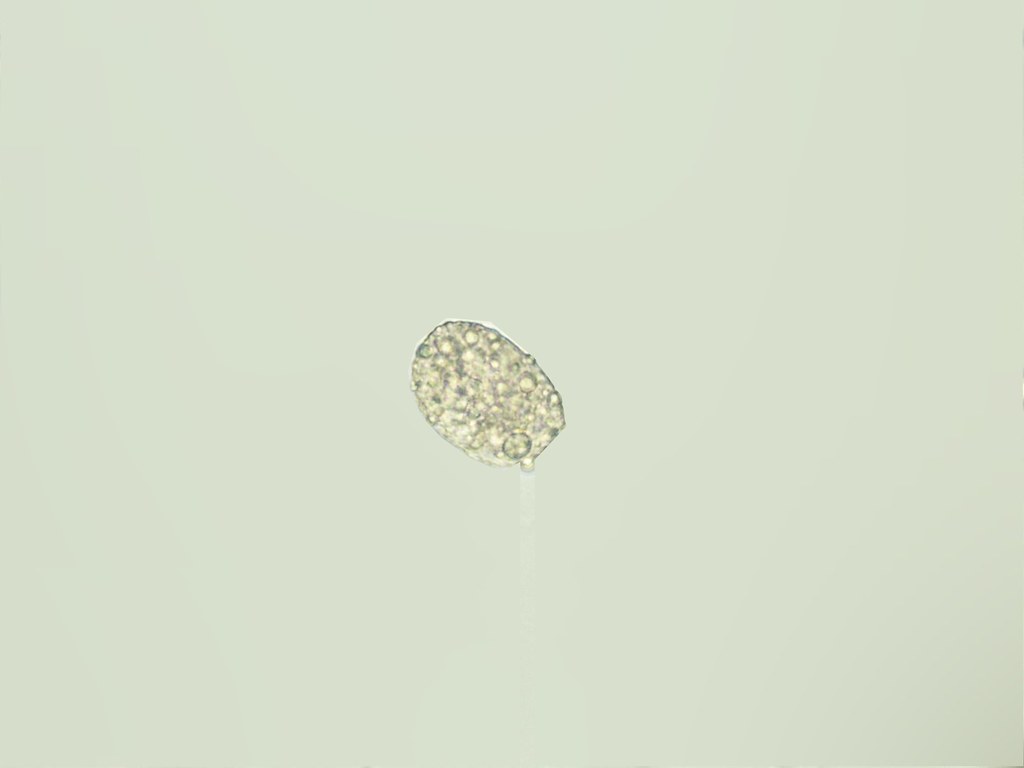
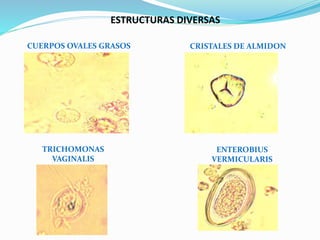
The full Spanish term translates directly to "fatty oval bodies in urine." These structures appear as round or oval shaped elements with a characteristic refractive quality under the microscope. When you adjust the light correctly, you'll notice they have a bright, almost glowing appearance compared to the surrounding sediment. That brightness comes from the lipid content inside them. They form when triglycerides accumulate within renal tubular epithelial cells and then slough off into the urine as the cells break apart. The technical name is oval fat bodies. They're a subtype of renal tubular epithelial cell that has become laden with lipids. Under phase-contrast microscopy, the lipid droplets inside show up as maltese cross patterns. This is the same polarization phenomenon you see with cholesterol esters. Not every lab has phase-contrast equipment. If you're working with brightfield only, the maltese cross won't be visible, and identification becomes more difficult. You'll rely on the refractile quality and the overall oval shape instead, which is less specific. I've seen technicians miss these entirely because they were looking for casts and bacteria and didn't bother adjusting the light properly. The trick is dimming the condenser slightly. When the light is too bright, fatty oval bodies look almost transparent and blend into the background. When you reduce the illumination just enough, they pop out immediately. It's one of those things that seems trivial until you're scanning through a field that barely has any cellular elements at all and you're second-guessing every bright spot.
How to Identify Them Properly
Start with a properly collected and processed urine sample. The specimen should be centrifuged at 400 to 600 x g for about five minutes. After that, resuspend the sediment gently in a drop of the supernatant. Too much resuspension and you'll break up the structures you're trying to identify. Place a cover slip and let it sit for a minute before examining under low power, then switch to high dry and oil immersion. Under 40x magnification, you'll see the oval bodies as refractile, rounded structures ranging from 5 to 15 micrometers in diameter. They're larger than red blood cells and roughly comparable in size to white blood cells, but the key differentiator is the internal appearance. Normal epithelial cells look fairly uniform. Oval fat bodies have a granular or vacuolated interior where the lipid droplets cluster. Under 100x oil immersion, you can see individual lipid droplets more clearly. The Sudan IV stain will confirm lipid content by turning the droplets orange-red. This is useful when the refractile appearance isn't enough to make a call, especially in samples with lots of debris or mucus that can mimic the shape. I recommend having a staining protocol ready before you start examining slides. Waiting until you're on the microscope and uncertain costs time and introduces variability since different technicians will interpret the same slide differently.
What the Finding Actually Means Clinically
The primary association is with nephrotic syndrome. When glomerular damage allows significant protein leakage, the kidneys reabsorb lipoproteins through the proximal tubules. These lipoproteins get broken down inside the tubular cells, and the resulting lipid accumulation causes the cells to swell and eventually shed into the urine as oval fat bodies. This is why their presence alongside proteinuria and hyperlipidemia forms a recognizable clinical pattern. But here's where it gets less straightforward. Oval fat bodies can appear in conditions that aren't nephrotic syndrome. Diabetic nephropathy, lupus nephritis, amyloidosis, and even acute tubular necrosis can produce them. I once spent two days tracking down why a patient with well-controlled type 2 diabetes and no significant proteinuria had prominent oval fat bodies in their urine. The workup revealed early membranous changes on biopsy that weren't showing up on routine testing. The oval fat bodies were the first clue, but they pointed in a direction that required additional investigation beyond the urinalysis alone. Free fat droplets in the urine can also create a similar appearance. These aren't oval fat bodies because they lack the cellular structure. They're just lipid particles floating freely. The distinction matters because free fat droplets suggest a different source of lipid in the urine, sometimes related to dietary intake or chyluria rather than renal tubular damage. Under the microscope, free droplets are more variable in shape and size and don't have the defined cellular boundary that oval fat bodies do.
Get the Full Details

Common Pitfalls and Where the Method Breaks Down
The biggest issue is sample handling. If the urine sits at room temperature for more than two hours before examination, cellular elements degrade. Oval fat bodies are relatively stable compared to red blood cells, but prolonged storage causes the lipid droplets to coalesce and change appearance. You might count fewer bodies than were actually present, or misidentify degraded forms as something else. Refrigeration slows this down but doesn't stop it entirely. Another problem is overcalling. Not every refractile oval structure in the urine sediment is an oval fat body. Yeast cells, especially Candida species, can look similar under certain lighting conditions. Pollen grains from plant contamination are another common mimic. These are larger, have a thicker wall, and don't respond to Sudan IV staining the way lipid-containing structures do. If you're uncertain, a quick stain confirmation takes about thirty seconds and eliminates most of the diagnostic noise. The method also has a detection threshold. You typically need around 10 to 20 oval fat bodies per high-power field before the finding is considered clinically significant. Below that, it's noted as present but not quantified heavily. This means a single field with one or two bodies doesn't carry the same weight as a slide where they're abundant throughout multiple fields. Reporting should reflect this distinction rather than giving a binary positive or negative result.
Practical Workflow for the Lab
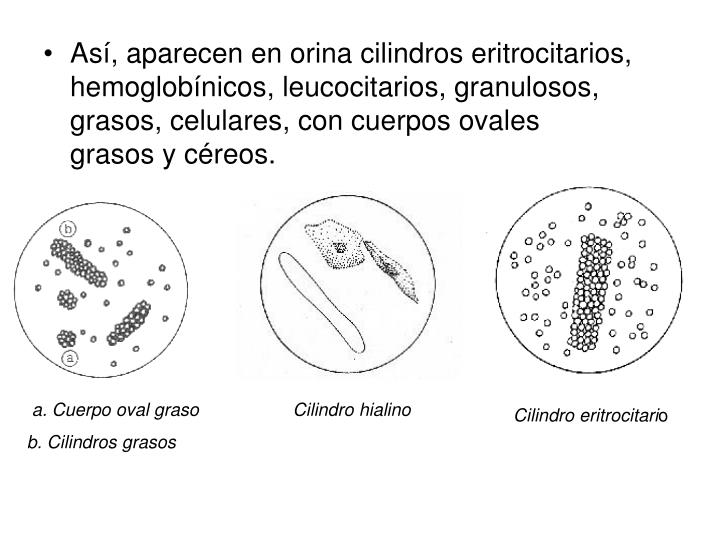
Set up a consistent routine. Centrifuge, decant, resuspend, stain slide, examine systematically. Don't skip the staining step even when the refractile bodies seem obvious. The confirmation step catches the borderline cases that cause disagreements between technicians. Document the count per high-power field and note whether Sudan IV staining was performed. This level of detail matters when the results are used to monitor disease progression or response to treatment over time. If you're working in a setting without phase-contrast microscopy, invest in good quality brightfield optics and proper adjustment of the condenser and iris diaphragm. The difference in identification accuracy between a properly adjusted system and one that's been left on autopilot is significant. I've seen labs miss significant findings simply because the microscope wasn't calibrated to the person using it at that moment. When oval fat bodies are present alongside other findings like fatty casts or free fat droplets, the clinical picture becomes clearer. Fatty casts form when oval fat bodies get trapped in a protein matrix within the renal tubule and pass into the urine as a unit. The presence of both features together strongly supports a diagnosis of active glomerular disease with lipid abnormality. Alone, oval fat bodies are suggestive but not definitive. That's the nuance that separates a competent urinalysis from a thorough one.