What Actually Happens When You Run a Cultural Competence Assessment
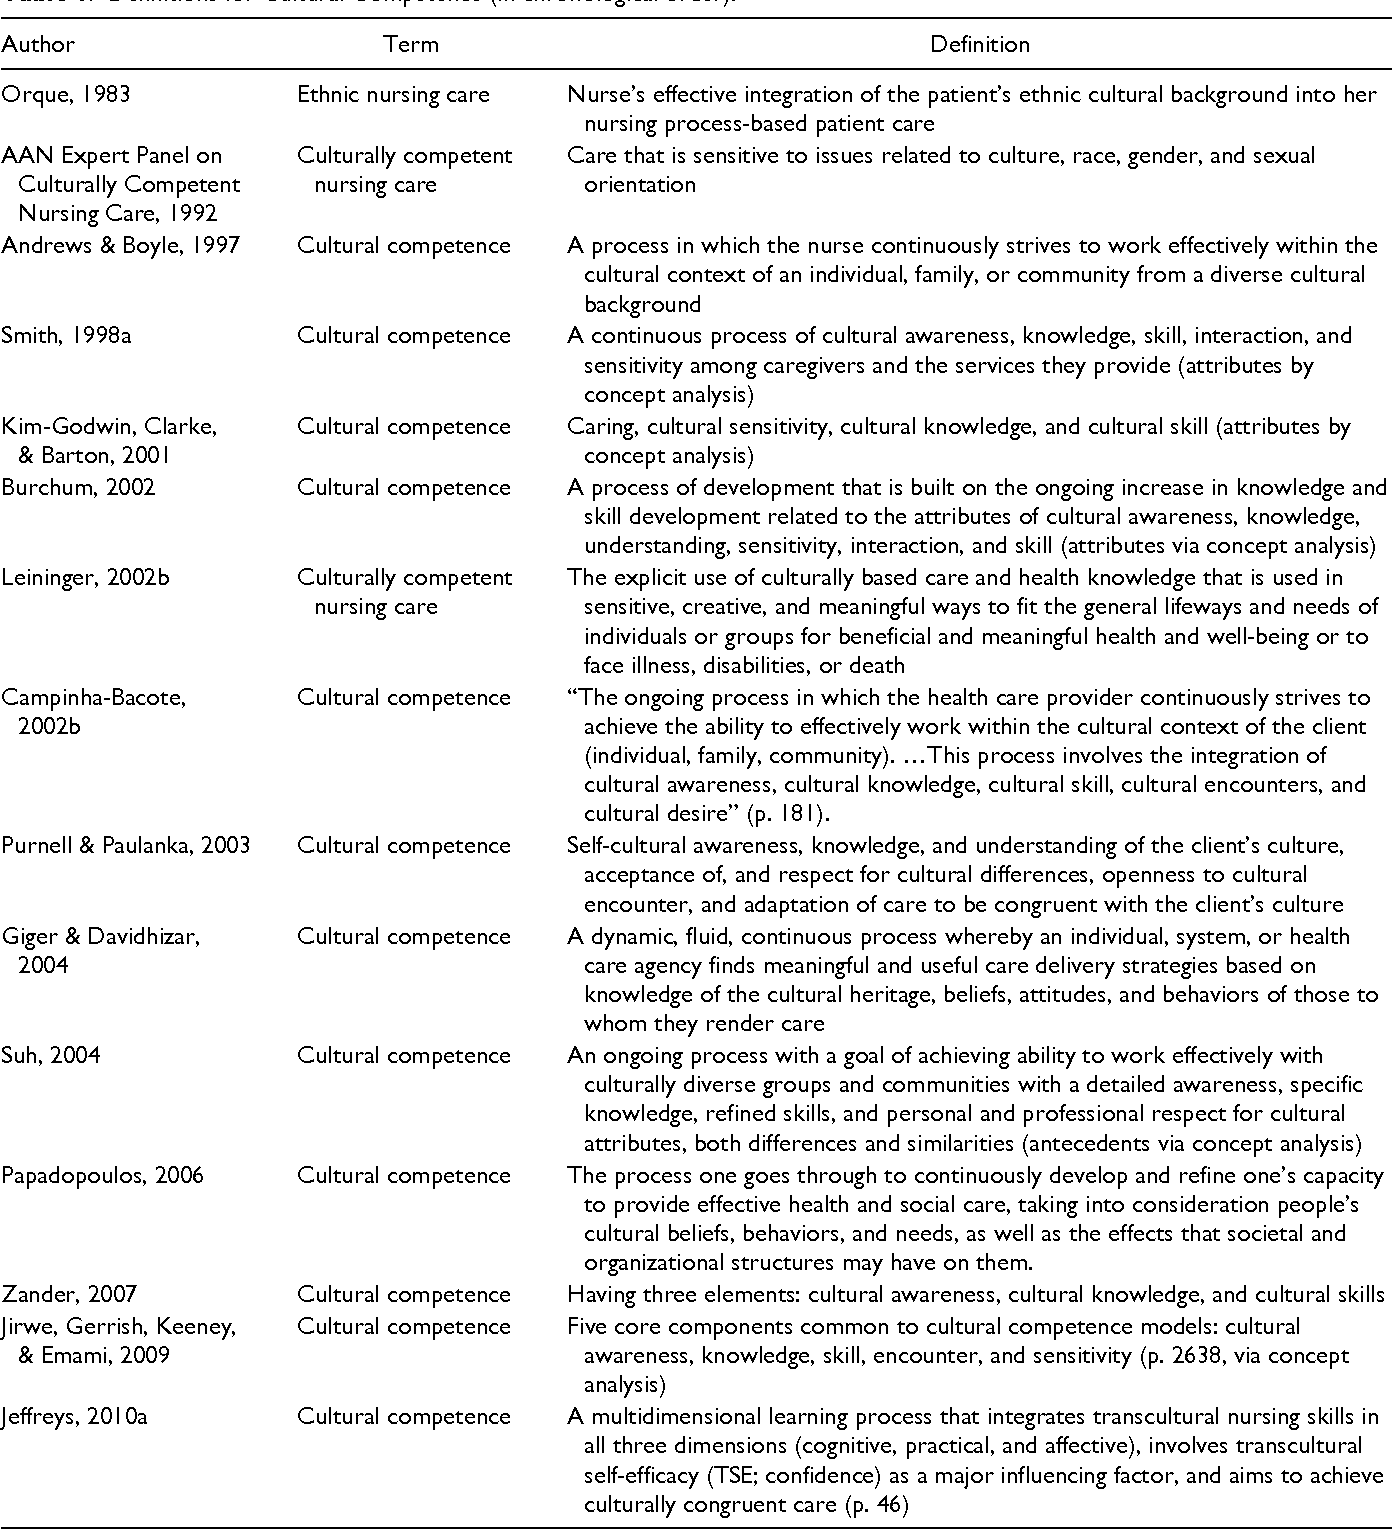
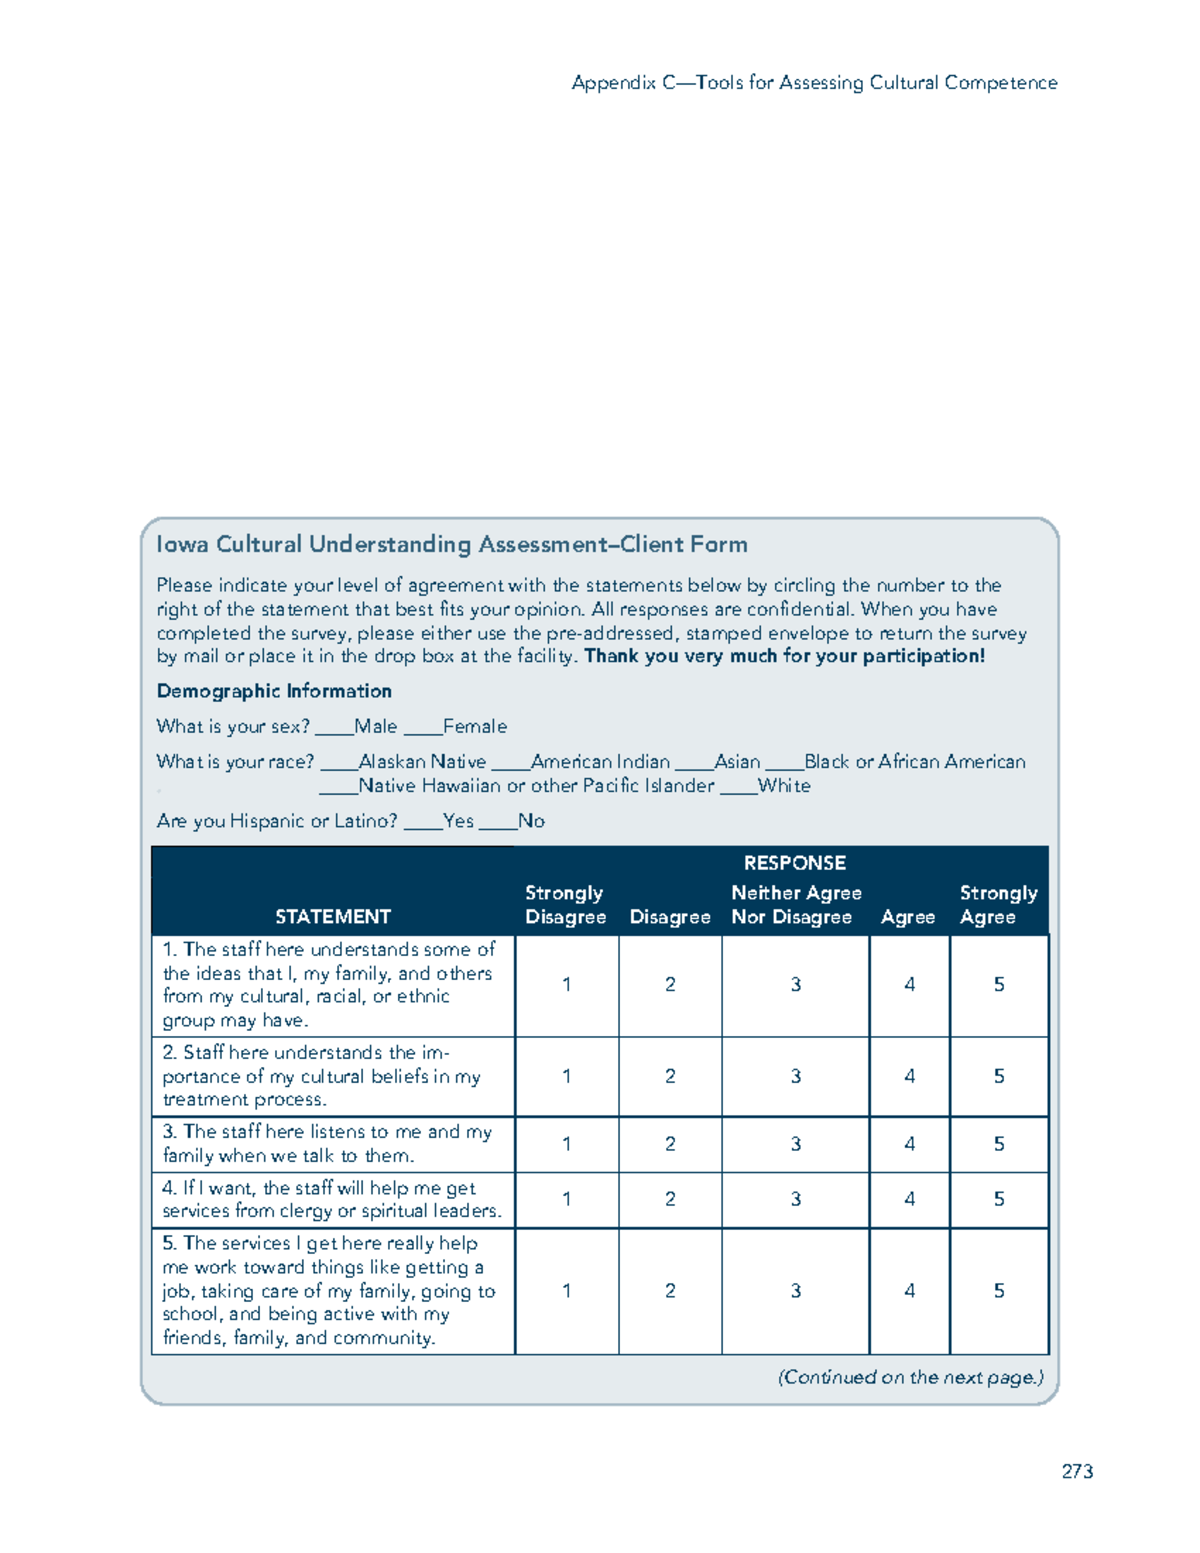
I have watched nurses treat cultural competence checklists like they were vital sign forms. They fill them out, file them, and forget about them. That is not how these tools work. They are diagnostic instruments for understanding patient context, and when used correctly, they reveal blind spots that standard history-taking misses entirely. The most commonly used instruments are the CLAS Standards framework, the Competency Assessment Tool from the Transcultural Nursing Society, and the Playfair Cultural Competence Assessment. Each serves a different purpose depending on your setting. The Playfair tool is probably the most practical for bedside use. It breaks down into seven domains: awareness of your own cultural biases, knowledge of cultural health beliefs, skills in culturally sensitive communication, encounters with diverse patient populations, desirability of cross-cultural practice, professionalism and advocacy, and linguistic competency. A typical self-assessment takes about 20 minutes and produces a radar chart you can reference later. The problem is that most people rate themselves too high across every domain. I have seen registered nurses with twelve years of experience score themselves a four out of five on cultural knowledge. When I asked them to name three specific health belief systems practiced by their largest non-English-speaking patient group, they could not answer. Here is what actually works. Take the tool seriously enough to score yourself honestly, then cross-reference your weaknesses with your patient census data. If your unit admits twelve Hispanic patients a week and you scored yourself low on language competency, that is not a theoretical gap. That is an immediate action item. I used to tell new grad nurses that cultural competence assessments are not about collecting CEUs. They are about identifying where your clinical judgment might be wrong before it becomes a patient safety issue.
The Counter-Intuitive Part Nobody Talks About
Most people assume cultural competence means learning about other cultures. That is only half of it. The more difficult skill is recognizing how your own cultural framework shapes every clinical decision you make. A nurse who grew up in a culture where direct eye contact shows respect will interpret an avoidant gaze as disengagement or deception. That assumption can alter pain management decisions, discharge planning, even the quality of your handoff report. The assessment tools force you to confront this because they include self-awareness items that most respondents rush through or answer dishonestly. I ran into this problem with a Somali patient who had been admitted for poorly controlled diabetes. My initial assessment score on cultural humility was a three out of five. The patient was nonverbal during most of my interactions, which I initially attributed to language barrier. What I did not understand was that in her cultural context, prolonged eye contact from someone in a position of authority is considered confrontational. She was not being uncooperative. She was being polite. When I adjusted my approach and communicated through a certified interpreter while reducing direct eye contact, her engagement improved dramatically and we got a complete social history within twenty minutes.
Where These Tools Fail and What to Do Instead
Cultural competence assessments have real limitations. They measure self-reported behavior, not actual behavior. A nurse can check all the right boxes and still deliver culturally insensitive care. The tools also tend to frame culture as something external to the patient rather than something constructed through interaction. This matters because it shifts the burden onto the nurse to adapt rather than creating a system where cultural responsiveness is built into the workflow itself. The biggest failure mode is organizational. I worked at a hospital that required annual cultural competence training and assessment for all nursing staff. Eighty percent of nurses completed it in under thirty minutes. The remaining twenty percent, the ones who actually needed the time to reflect on their biases, were the ones who took the assessment more seriously. The system created the opposite of its intended effect. The workaround I found was to tie assessment results to preceptorship assignments. Nurses who scored low on specific domains were paired with experienced colleagues who had demonstrated strength in those areas for a four-week observational rotation. This turned the assessment from a paperwork exercise into a development plan.
Get the Full Details

Which Tool Should You Actually Use
If you want something quick and free, the Playfair Cultural Competence Assessment is the most accessible option. It has a five-point Likert scale format and covers the core domains without requiring specialized training to interpret. The Transcultural Nursing Society tool is more rigorous but requires purchasing a license and comes with certification prerequisites that most bedside nurses do not have time to pursue. The CLAS Standards framework is not technically an assessment tool. It is a policy framework developed by the Office of Minority Health that outlines nine standards for healthcare organizations. You can use it as a checklist to evaluate your unit's practices rather than your personal competencies. This is useful when you are trying to advocate for structural changes like translation services or interpreter staffing ratios.
A Practical Walkthrough
Take the Playfair assessment first. Allocate forty-five minutes minimum. Do not complete it during a break between shifts. Rate yourself honestly and write down specific patient encounters that triggered each low score. Bring those notes to your next unit council meeting. Use them to propose concrete changes like adding culturally specific dietary options to the patient menu, requesting interpreter services for languages that appear on your census, or creating patient education materials in the top three languages spoken by your patient population. Then repeat the assessment annually. Track your scores over time. The goal is not perfection. The goal is to become aware of where your assumptions might be leading you astray before they affect patient outcomes.