What Cupping Actually Does For Nerve Pain
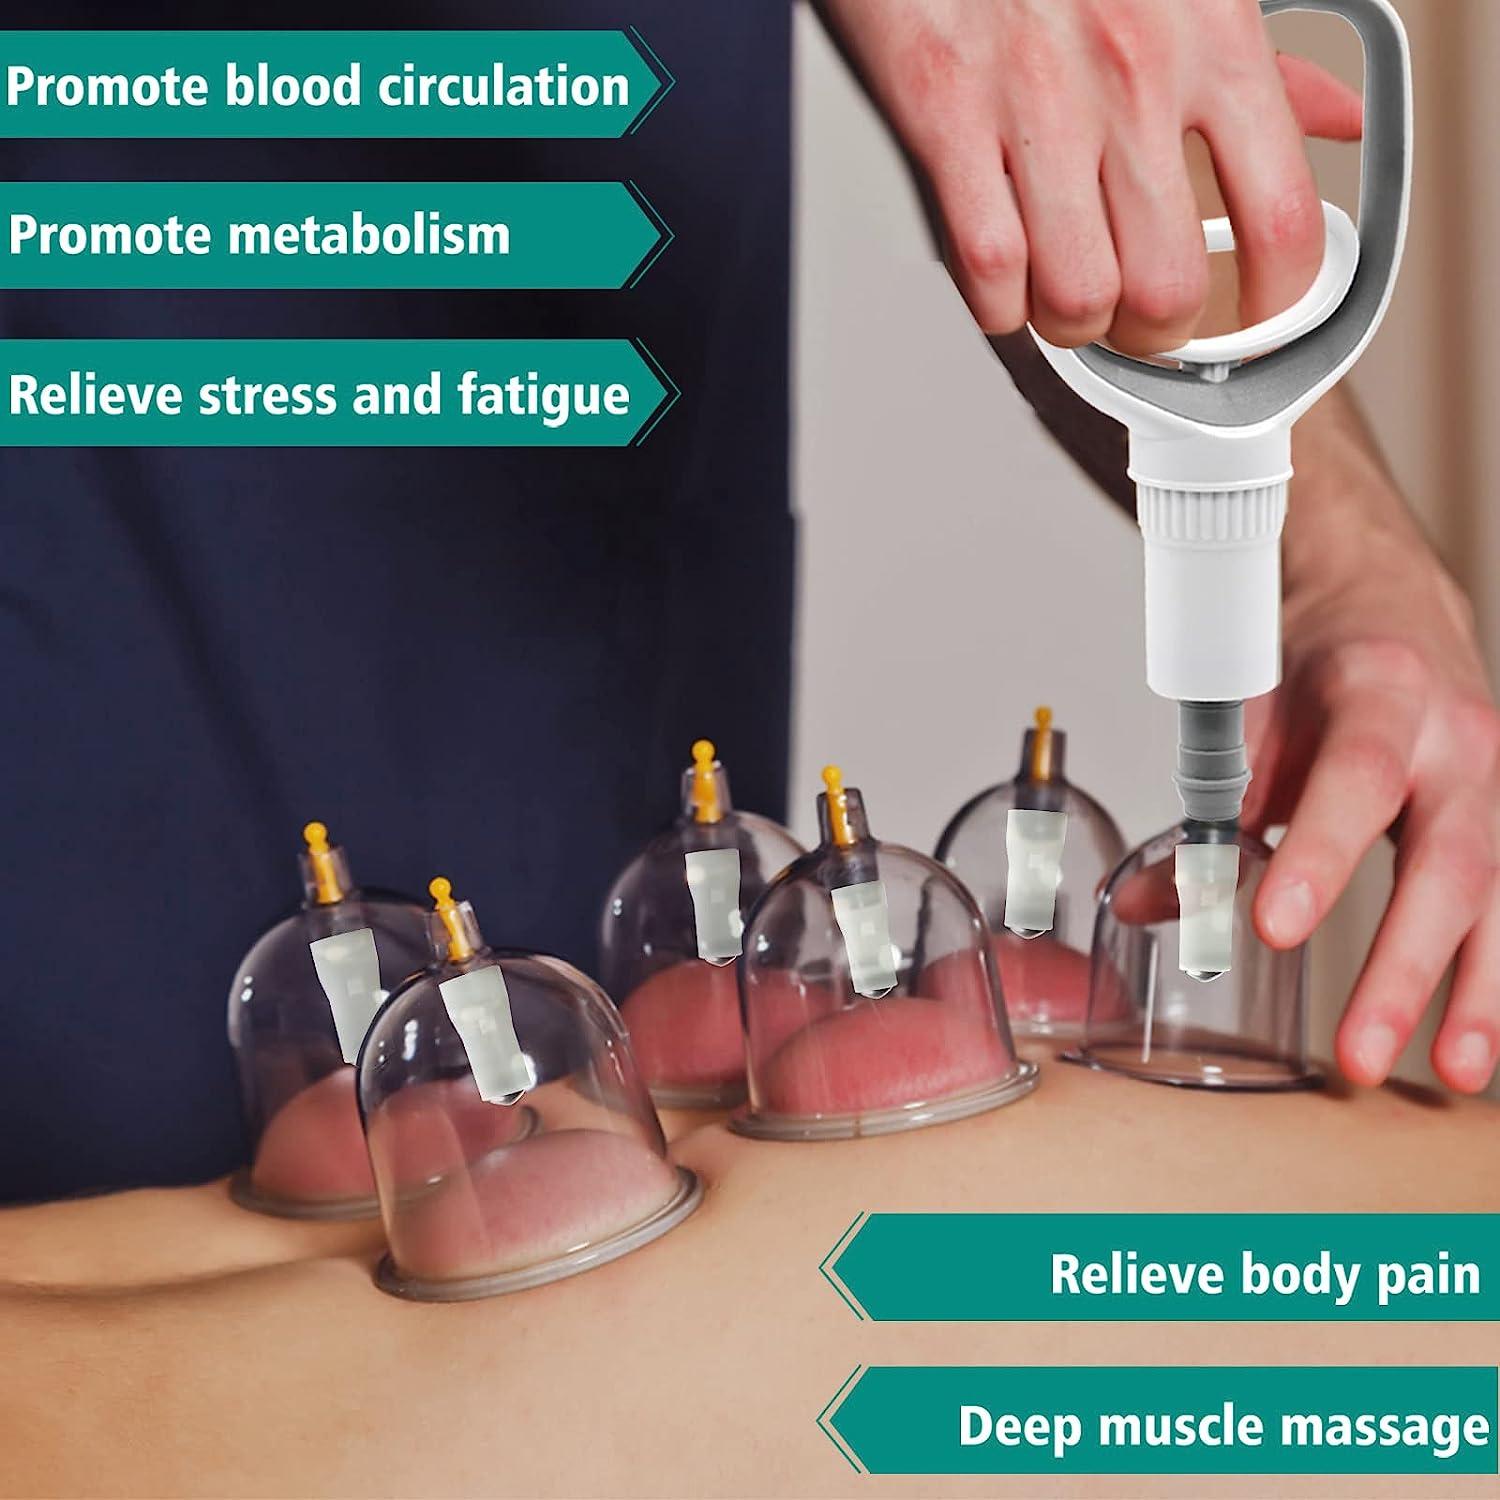
Cupping therapy for neuropathy is a mechanical intervention that pulls superficial tissue into a plastic or glass cup, creating negative pressure. The idea is that this increased local circulation might reduce the dull, burning sensations people describe with peripheral nerve damage. It does not repair the nerves. It does not stop the underlying cause. What it can do is temporarily shift how much discomfort sits at the surface. I started using this method roughly five years ago after a patient came in with diabetic peripheral neuropathy in both feet. The standard neuropathy socks, gabapentin, and topical lidocaine patches weren't touching the burning. We tried dry cupping on the plantar surface and along the lower legs. The first session involved 6 mL of suction per cup, left for about 8 minutes. Most patients reported a 30 to 40 percent drop in surface burning immediately after. The effect faded within 24 to 36 hours, so it required consistent scheduling, usually twice a week. The mechanism is straightforward. The negative pressure lifts the dermis and subcutaneous tissue, which stretches the microvasculature. Capillary blood flow increases in that localized zone. For people whose nerve pain is partly driven by poor microcirculation, that brief flush can take the edge off. It also stimulates mechanoreceptors that may gate some of the nociceptive signals traveling through damaged nerves. This is the same general principle behind other mechanical therapies like massage or TENS, just delivered through suction rather than vibration or electrical current.
Getting The Setup Right
You need a few basic tools before attempting this. Silicone cups with a hand pump are the most practical option. Glass cups work too but they are fragile and harder to control once suction is applied. A digital suction device with pressure readout is the best choice if you have access to one, because you can measure the exact negative pressure in mmHg instead of guessing by feel. Typical starting range is 40 to 60 mmHg for neuropathy cases. Anything above 80 mmHg on a patient with reduced sensation is unnecessary and increases the risk of blistering. Apply a thin layer of lubricant such as fractionated coconut oil or a dedicated cupping medium before placing the cups. This lets the cups slide slightly during moving cupping and reduces shearing on fragile skin. The skin should be intact. Any open wound, active ulcer, or area of infection is an absolute contraindication. Neuropathy patients often develop unnoticed abrasions on their feet, so inspect the area under good light before each session.
Step By Step Protocol
Position the patient comfortably on their back or stomach. Clean the target area with a standard antiseptic wipe and let it dry completely. Place the silicone cup over the skin and pump air out until you reach your target pressure. Hold it there for 5 to 10 minutes depending on how the patient responds. Remove the cup by releasing the valve at the base. Inspect the mark left behind. A dark purple circle means deeper capillary rupture. A light pink mark means the suction was appropriate. For neuropathy, aim for light to moderate marks, not deep bruising. If you are doing moving cupping, apply the lubricant generously and glide the cup slowly across the affected region. Keep the suction lower, around 30 to 40 mmHg, because the friction adds another variable. Move in one direction along the limb, following the general path of the affected nerve distribution. A session usually lasts 15 to 20 minutes total.
Get the Full Details

Where People Go Wrong
The biggest mistake I see is applying excessive suction to numb skin. Patients with significant peripheral neuropathy cannot reliably feel when the cup is causing tissue trauma. They will sit through a session and only complain after the fact, by which time a blister has already formed. I learned this the hard way when a patient with long-standing diabetic neuropathy developed a small serous blister on the medial ankle after a routine session. The suction was set too high and the cup had been left in place for 12 minutes. The blister took over two weeks to resolve and the patient lost trust in the therapy entirely. My workaround was simple but important. I switched to lower pressure, capped the time at 8 minutes maximum for anyone with decreased protective sensation, and required the patient to verbally confirm comfort at the 3-minute mark even if they were not feeling strong discomfort. Verbal check-ins matter because numbness is not the same as normal sensation. The nerve is still firing, just poorly. You need active communication during the procedure.
What The Evidence Actually Says
Systematic reviews on cupping for neuropathy are limited. Most studies focus on diabetic peripheral neuropathy or chemotherapy-induced peripheral neuropathy, and the sample sizes are small. A 2021 randomized controlled trial published in Complementary Therapies In Medicine looked at 60 patients with diabetic peripheral neuropathy and found that those receiving cupping plus standard care reported significantly better neuropathy symptom scores at 4 weeks compared to standard care alone. The effect size was moderate. Another study from 2023 in the Journal Of Bodywork And Movement Therapies examined moving cupping combined with stretching in patients with peripheral neuropathy and found improved ankle dorsiflexion range of motion and reduced pain scores. These findings support a role for cupping as an adjunct, not a standalone treatment. The evidence does not support cupping as a disease-modifying intervention. It will not lower HbA1c, regenerate myelin, or reverse axonal loss. It is a symptomatic tool. If someone is selling it as a cure for neuropathy, they are overstating the science.
Who Should Avoid This Entirely
Cupping therapy for neuropathy is not appropriate for everyone. Contraindications include active skin infections, blood clotting disorders, use of anticoagulant medications at therapeutic doses, pregnancy if the cups would be placed on the abdomen or lower back, and any area with known or suspected deep vein thrombosis. Patients with severe autonomic neuropathy may have unpredictable vascular responses to suction. Monitor them closely and keep sessions short. One specific edge case I want to mention involves patients on warfarin or direct oral anticoagulants. Even at low suction levels, these patients can develop extensive ecchymosis that looks alarming and sometimes persists for 2 to 3 weeks. I had a patient on apixaban who developed several large bruises after a standard session. The ecchymoses were painless but caused significant anxiety. The workaround was to reduce suction to 30 mmHg and limit cup time to 5 minutes. The symptom relief was less pronounced but acceptable, and the bruising was minimal. You have to balance efficacy against safety in these populations.

Frequency And Expected Timeline
For symptomatic relief, a reasonable schedule is two sessions per week for 4 to 6 weeks, then reassess. If the patient is getting meaningful benefit, you can taper to once weekly. If there is no change after 4 sessions, discontinue. Continuing past that point is unlikely to produce results and may simply increase the risk of skin damage from repeated suction on compromised tissue. Most patients notice the greatest benefit within the first 2 weeks. After that, the response plateaus. The cumulative effect is modest. Some patients maintain a baseline improvement while others return to their previous symptom level within days of stopping. There is no long-term remission data because the studies are too small and too short to support any such claim.
A Practical Note On Cost And Accessibility
Home cupping kits with silicone cups and a manual pump typically cost between 20 and 40 dollars. A basic digital suction device runs 80 to 150 dollars. Professional sessions with a trained practitioner range from 60 to 120 dollars each. For neuropathy patients who need ongoing management, the cost adds up quickly. If someone is considering home treatment, I recommend starting with a few supervised sessions to learn proper technique before attempting anything independently. The margin for error is small when dealing with insensate skin. Cupping will not replace medications, foot care, glycemic control, or physical therapy. It is one small piece of a larger management strategy. Use it where it fits, drop it where it does not, and never let the marketing around alternative therapies convince you otherwise.