Setting Up and Reading CVP Monitoring at the Bedside
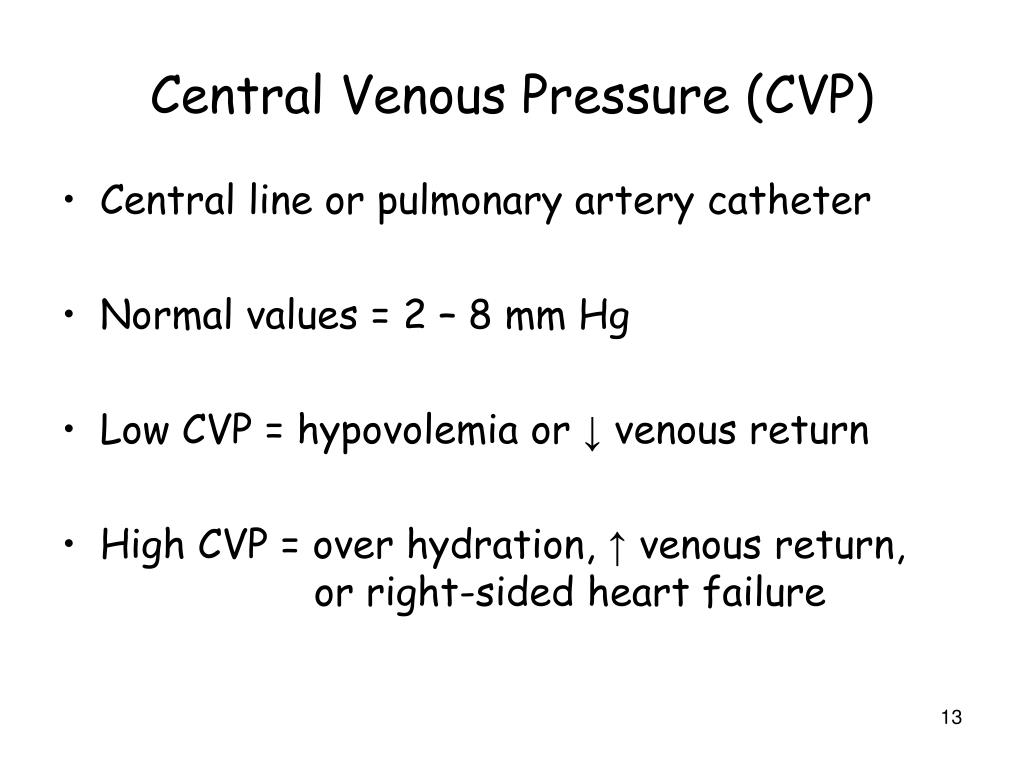
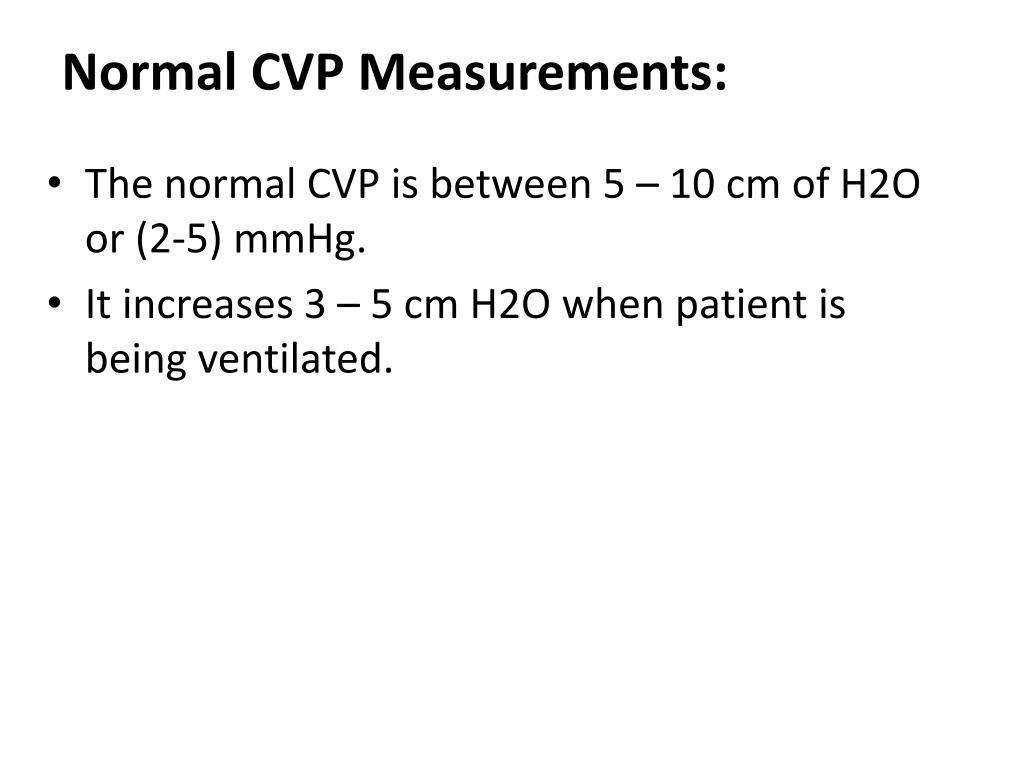
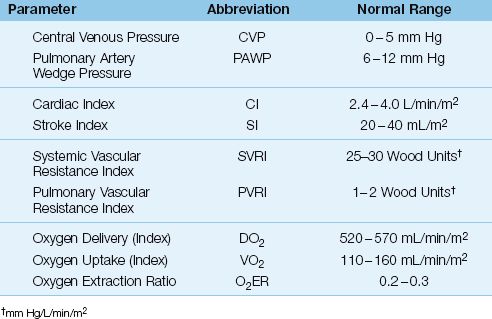
Central venous pressure monitoring is one of those things that sounds simple on paper but falls apart if you don't respect the mechanics. The Cvp Pressure Normal Range is typically 2 to 8 mmHg in a spontaneously breathing patient, or 6 to 12 mmHg if they are mechanically ventilated with positive pressure. That baseline number is easy to find in any textbook. Getting a reliable reading from a patient in real time is a different problem entirely. I need to explain the setup first because most people skip straight to the number and then wonder why their tracing looks wrong. You transduce the line at the phlebostatic axis, which is the fourth intercostal space at the right atrium level. The zero reference point matters more than anything else. If your transducer is even two centimeters off, your reading shifts by about 1.5 mmHg. That is enough to change a clinical decision when you are sitting on the edge of the normal range anyway. The catheter needs to be patent and free of kinks. Flush the line before connecting the transducer tubing. Air bubbles in the system will dampen the waveform and give you a falsely low systolic and artificially high diastolic reading. I had a case last year where a patient's CVP looked like 3 mmHg consistently, and I was about to hold fluids for possible hypovolemia. I recalibrated the transducer, eliminated the bubble, and the actual pressure was 9 mmHg. The difference was an air bubble trapped near the catheter tip that I hadn't noticed. It saved that patient from unnecessary fluid restriction.
Zero the transducer to atmospheric pressure every time you reposition it or change the setup. Level it to the phlebostatic axis each time. Those two steps take about thirty seconds and they are non-negotiable for accuracy.
Interpreting the Waveform and the Number
The numeric value alone is almost useless without the waveform. Look at the tracing. The a wave represents atrial contraction. The c wave is tricuspid valve bulging into the atrium during ventricular systole. The v wave is venous filling against a closed tricuspid valve. The x descent follows atrial relaxation. The y descent is passive opening of the tricuspid valve and rapid ventricular filling. If you see giant cv waves, think tricuspid regurgitation. If the y descent is prominent and rapid, that points toward constrictive pericarditis or restrictive cardiomyopathy. A blunted y descent suggests cardiac tamponade. These patterns matter more than the absolute number in many scenarios. I once managed a septic patient whose CVP was 7 mmHg, right at the upper edge of normal. The number looked fine, but the waveform showed a deep, rapid y descent and massive v waves. The patient had significant tricuspid regurgitation from a pulmonary hypertension spike. The static number was lying. The waveform told the real story. This is the kind of thing that catches people who only focus on the digit on the monitor.
Get the Full Details
Common Pitfalls That Ruin Readings
Pneumothorax on the side of the catheter can artificially elevate the reading by changing intrathoracic pressure transmission. Positive end-expiratory pressure (PEEP) raises intrathoracic pressure and shifts the CVP upward regardless of actual volume status. A PEEP of 10 cmH2O can add roughly 8 mmHg to your reading. Some clinicians subtract the PEEP value from the measured CVP, but that is an approximation and not universally reliable. Abdominal pressure matters too. Intra-abdominal hypertension compresses the inferior vena cava and raises central venous pressure. I have seen critically ill patients with tense ascites or severe ileus show CVP readings in the 14 to 16 mmHg range with no sign of volume overload. Decompressing the abdomen brought the number down to 7 mmHg immediately. Right heart failure produces elevated CVP. So does pulmonary embolism. So does hypovolemia in a patient on high PEEP. The same number can mean opposite things depending on context. That is why CVP is a terrible standalone predictor of fluid responsiveness. Multiple studies have shown this. A single CVP value or even a trend does not reliably tell you whether a patient will respond to a fluid bolus.
What to Use Instead or Alongside
If you need to guide fluid therapy, look at dynamic parameters instead of static CVP values. Stroke volume variation, pulse pressure variation, and passive leg raise tests with echocardiography or arterial waveform analysis give you actual information about fluid responsiveness. CVP can still be useful for tracking trends over time, assessing right heart function, and guiding certain vasoactive therapies, but it should never be the only number you trust when making fluid decisions. Echocardiography has largely replaced CVP monitoring for volume assessment in many centers. The IVC diameter with respiratory variation is quick and gives you a better sense of volume status than a catheter transducer in most cases. That said, CVP lines remain standard in many ICUs and operating rooms, so you need to know how to use them properly even if you would rather not rely on them.
Quick Reference for Setup
Use a 7 French multi-lumen catheter placed in the internal jugular or subclavian vein. Connect to a sterile transducer set. Flush all lines to remove air. Zero at the phlebostatic axis. Confirm a good waveform with a square wave test. Document the level each time you move the patient or readjust the transducer. Record the number along with the PEEP setting, ventilator mode, and abdominal pressure status if relevant. Without those contextual details, the number is nearly meaningless. The normal range exists as a reference point. Clinical judgment exists for interpreting it. The two work together only when you pay attention to the waveform, the setup, and the patient's actual condition rather than staring at a single number on a screen.