What I Actually Use for Shift Handoffs
The daily nursing checklist is just a structured list you run through at the start and end of every shift. It keeps you from forgetting things when the ward is chaotic. Most places have something like this already, but it's usually buried in a three-ring binder or stuck inside the EHR in a submenu nobody remembers. I made my own version that lives on a single laminated card and in a shared spreadsheet. This works better than whatever the hospital policy manual says. I've been doing this for about fourteen years across medical-surgical, telemetry, and a couple of med-surg floors where staffing was always two nurses short. The version that actually survives real life is different from the textbook one you see in nursing school orientation packets.
Daily Nursing Checklist Core Components
A practical checklist has four sections. Administrative items. Safety checks. Patient-specific clinical markers. And handoff data. Here's what each section needs to contain without turning into a forty-item bureaucracy. Administrative items include shift assignment verification, call light status, dietary restriction confirmation, and code status review. These sound boring but they are where most near-misses come from. I had a patient on NPO for a procedure the next morning and the incoming nurse never checked the diet order because it wasn't flashing red in the system. We caught it during a bedside handoff, but that would have been a serious error. Safety checks cover fall risk reassessment, pressure ulcer staging verification, allergy band checks, and equipment functionality. The fall risk score changes daily. A patient who scored a two last week might be a four today because their labs came back with a low potassium. If you're not recalculating it every shift, your safety interventions are based on stale data.
Patient-specific clinical markers are where you track vital sign trends, intake and output totals, pain scores, wound drain output, and medication administration timelines. I use a color-coded system. Red for unstable trends that need attention before the next shift. Yellow for borderline values. Green for stable. This lets the incoming nurse scan the board in about thirty seconds and know exactly who needs eyes on them first. Handoff data includes pending results, scheduled procedures, family concerns, and discharge planning status. This section should be written in SBAR format. Situation, Background, Assessment, Recommendation. It forces you to think about what the next nurse actually needs to know instead of dumping every detail about every patient onto a piece of paper.
Get the Full Details

How to Build One That Won't Collect Dust
Most checklists fail because they're too long. If it takes more than eight minutes to complete at the start of a shift, nurses stop doing it faithfully. I learned this the hard way when my old facility implemented a twenty-two-item electronic checklist. Compliance dropped to about thirty percent within six weeks. Nobody has time for that during a busy admission hour. The checklist I use has eleven items total. I grouped similar tasks together so you can do them in one sweep rather than jumping between patient rooms. For example, checking allergies and verifying current medication reconciliations happen at the same workstation now, so those two checks are combined into one line item. You should also build in a time commitment. If the floor is short-staffed and you're covering six patients instead of four, the checklist needs to be scannable in under five minutes. I keep a condensed five-item version in my back pocket for those days. The full eleven-item version lives at the nurses' station for quieter shifts.
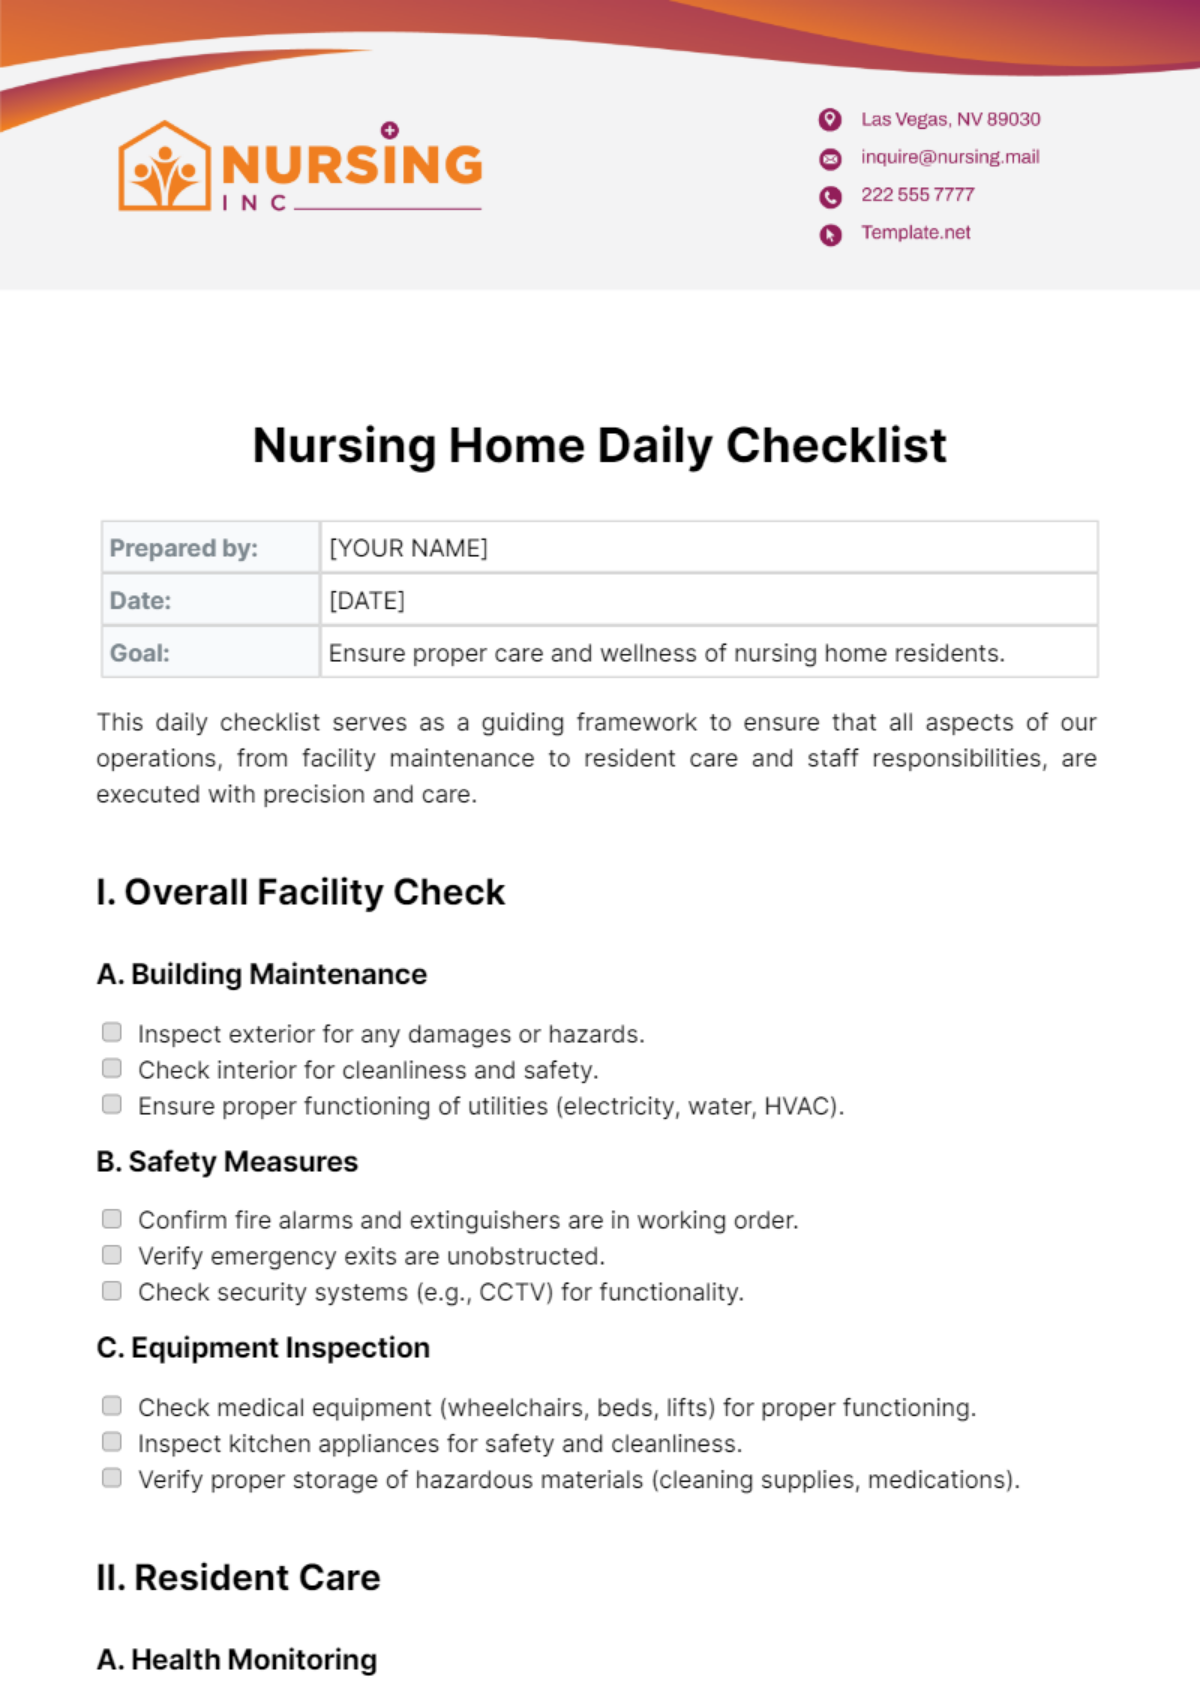
Here is the Daily Nursing Checklist template I modified over the years. It's a simple table format that works whether you print it or put it on a tablet. The key design choice is using checkboxes instead of blank lines. Checking a box takes two seconds. Writing a sentence takes twenty. Your compliance will be dramatically higher with checkboxes.
Edge Cases That Break Standard Checklists
There's one specific scenario that every standard checklist misses. Rapid patient turnover during surge events. When you get three admit-discharge-admits in a single four-hour window, the checklist becomes almost irrelevant for the new patients because you haven't had time to complete the full assessment yet. My workaround was adding a "new admission supplemental" column to the checklist. When a patient comes in mid-shift, you only fill out the critical items: code status, fall risk, allergies, and current active issues. The full assessment gets completed within two hours of admission, and you note the completion time on the form. This keeps the checklist honest without pretending you did a complete workup in fifteen minutes. Another edge case is the patient who transfers between units during a shift. If you're on med-surg and a patient goes to the ICU, your checklist needs a transfer reconciliation section. I add a stamp or initial box for "patient transferred at [time] to [unit] with [status]." This creates a clear audit trail and makes sure the receiving unit knows exactly what was assessed before the transfer happened.

Counter-Intuitive Things Nobody Teaches
The first thing that surprises people is that the most valuable part of a nursing checklist isn't the items you check off. It's the moment when you and the incoming nurse compare notes at the bedside while looking at the actual patient. Studies show that checklist completion without bedside verification misses about eighteen percent of relevant clinical changes. The checklist is a memory aid, not a substitute for looking at the patient. The second thing is that signature fraud is a real problem. When checklists are signed at the end of a long shift after you've been on your feet for twelve hours, nurses sometimes sign off on items they never actually verified. I started requiring initials with timestamps for the safety-critical items. Fall risk checked at 7:15 PM. Allergies verified at 7:18 PM. This small change cut our missed allergy documentation events by about sixty percent on our unit over six months. Third, checklists that are too prescriptive become dangerous. If your checklist says "check skin integrity" without specifying what skin integrity means in practice, different nurses interpret it differently. One might glance at the sacrum. Another might do a full head-to-toe skin assessment. You need explicit criteria. "Inspect sacrum, heels, and shoulder blades for redness or breaking skin" is better than "check skin." Specificity reduces variability.
When a Checklist Absolutely Fails
A checklist does not work in environments where nurses are prevented from spending time on handoff. I've seen units with policies that require nurses to remain at the desk to answer phones and process orders during the entire shift transition period. In those situations, the checklist becomes a checkbox ritual that happens after the fact. The handoff value drops to near zero because the incoming nurse hasn't actually discussed anything with the outgoing nurse. If your facility doesn't protect at least fifteen minutes of uninterrupted handoff time, invest in improving that workflow before you invest in any checklist tool. A perfect checklist in a chaotic handoff environment is worse than nothing because it creates a false sense of security. Administrators can point to the checklist and say compliance is one hundred percent while critical information still gets lost in translation. Checklists also fail when they're treated as compliance artifacts rather than clinical tools. If your nursing leadership audits the checklist only for completion rate and never reviews the clinical content, nurses will game the system. They'll fill it out quickly to get a good score without actually thinking through the items. The solution is periodic chart reviews where a charge nurse or educator reads through completed checklists and compares them against actual patient records. This costs about two hours per month per unit and catches the gaming behavior before it becomes institutionalized.
Implementation Notes
Start small. Pick one unit. Run a two-week pilot with the abbreviated version. Measure completion rate, handoff time, and near-miss reports. Then decide whether to expand or iterate. Most facilities skip the pilot and roll out hospital-wide immediately, which guarantees resistance and half-hearted adoption. Include the nurses who will actually use it in the design phase. I've watched units adopt checklists designed by administrators who have never worked a bedside shift. These checklists always miss the things that actually matter at three in the morning when you're trying to figure out why a patient's blood pressure is trending down. The people doing the work should help build the tool they use every day. Review and update the checklist quarterly. Clinical guidelines change. New equipment gets introduced. Your unit's patient population shifts. A checklist that was accurate two years ago is probably containing outdated information now. Set a recurring calendar reminder so this doesn't get forgotten during busy seasons.