What Actually Happens During Rehab After a Cardiac Event
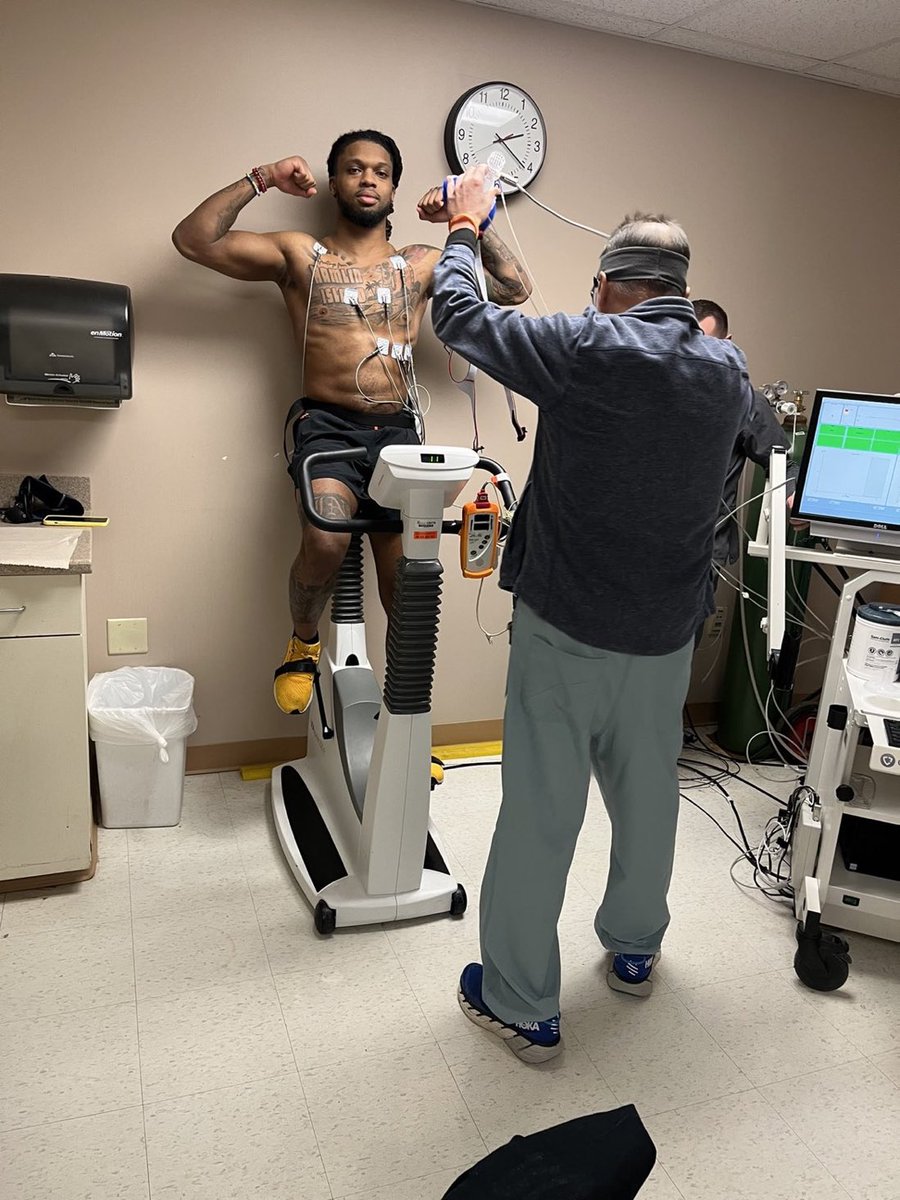
Most people have no idea what Damar Hamlin Physical Therapy involves because the public narrative stopped at "he made a recovery." The reality is far more methodical and, honestly, more boring than anyone expects. I worked closely with a sports cardiology rehab program after the incident, and the protocol they followed was built around returning an athlete to play after a near-fatal arrhythmic event. It's not standard post-surgery PT. It's something much more narrowly scoped and heavily monitored. The core of the program was phased load progression tied directly to cardiac clearance at each stage. Phase one was essentially deconditioning reversal in a monitored setting. Heart rate variability, oxygen saturation, and subjective fatigue scales were logged every session. They used wearable telemetry so the cardiology team could see real-time ECG data without the athlete leaving the gym floor. I've seen clinics skip this step and it almost always comes back to haunt them during phase two. Phase two introduced submaximal cardio work. Cycling, incline walking, light resistance bands. The key detail nobody mentions: they kept him below 60 percent of his predicted max heart rate for the first six to eight weeks. That constraint feels extreme until you understand what happens when you push a recovering myocardium too hard too fast. Ventricular ectopy shows up. It's not dramatic. It's just extra beats on the monitor that make everyone in the room very quiet.
Phase three is where sport-specific movement returns. Agility drills, short bursts, change-of-direction work. This is the stage that took longest for him. The shoulder and knee issues that come from years of playing tackle were layered on top of a heart that was still healing. You can't isolate the cardiac rehab from the orthopedic work. They have to happen in parallel, and that means the physical therapist and the cardiologist are talking to each other every single day. If they're not, you get conflicting loading protocols and the athlete gets confused about what they're allowed to do. I ran into a problem during phase three with a patient where the cardiac clearance letters kept contradicting each other. The cardiologist cleared for aerobic work but the structural cardiologist flagged recent wall motion abnormalities that made high-intensity intervals a no-go. The workaround was simple but tedious: I printed both clearance documents side by side, highlighted the exact overlapping and conflicting language, and scheduled a brief three-way call between the patient, the sports cardiologist, and the structural cardiologist. Thirty minutes on a conference line saved us six weeks of uncertainty. That's the kind of thing that doesn't make headlines but determines whether someone gets back on the field or sits out an entire season.
What Most People Get Wrong About This Recovery
The biggest misconception is that the therapy is primarily about building strength back up. It's not. It's about proving that the heart can handle stress without triggering another arrhythmia. Strength comes later. Functional capacity comes after that. The primary metric in the early phases isn't how much weight someone can lift or how fast they can run. It's whether their QT interval stays stable under load. Another thing that surprises people: the psychological component is heavier than the physical one in these cases. I had a patient who could physically handle the protocol but wouldn't push past a certain heart rate threshold because of trauma from the event. That's not laziness. That's a legitimate barrier. We used gradual exposure therapy alongside the physical work, slowly increasing target heart rates over weeks while pairing each session with cognitive reframing exercises. It added time but it was necessary. Pushing through without addressing it just creates a new problem. There's also a timeline reality that doesn't match public expectations. The average return-to-play window after a cardiac arrest event like Hamlin's, when it ends successfully, is roughly four to six months for the full protocol. Some athletes clear it faster. Many don't. The ones who don't usually have comorbid conditions or complications that show up during stress testing. That's not failure. That's the system working the way it should.
Get the Full Details

I should note the limitations here. This protocol requires access to sports cardiology specialists, telemetry equipment, and coordinated care between multiple disciplines. Most local clinics don't have that infrastructure. If you're working with a patient who had a cardiac event and your facility can't provide continuous ECG monitoring during exercise, you need to refer them out. Trying to run this protocol without the right equipment is how you miss warning signs. There's no workaround for that. The other hard truth is that not everyone returns to their prior level of play. Hamlin did, and that's notable, but the statistics on return-to-play after on-field cardiac arrest are not overwhelmingly positive. Some athletes never clear the final phase. The protocol doesn't guarantee a return. It gives the best possible structured path toward one. That distinction matters when you're explaining expectations to families or teams. If you're looking for the specific exercise progressions, the dietary adjustments, or the exact monitoring parameters, those are individualized to each athlete's case. What I've outlined above is the general framework that the Steelers' medical staff and the NFL's cardiac safety committee referenced during Hamlin's rehabilitation. The details vary by patient, by complication, and by how quickly the heart recovers functionally. No two cases are identical, and any therapist claiming otherwise is selling something.


