What You Should Actually Know Before Going Into EMDR
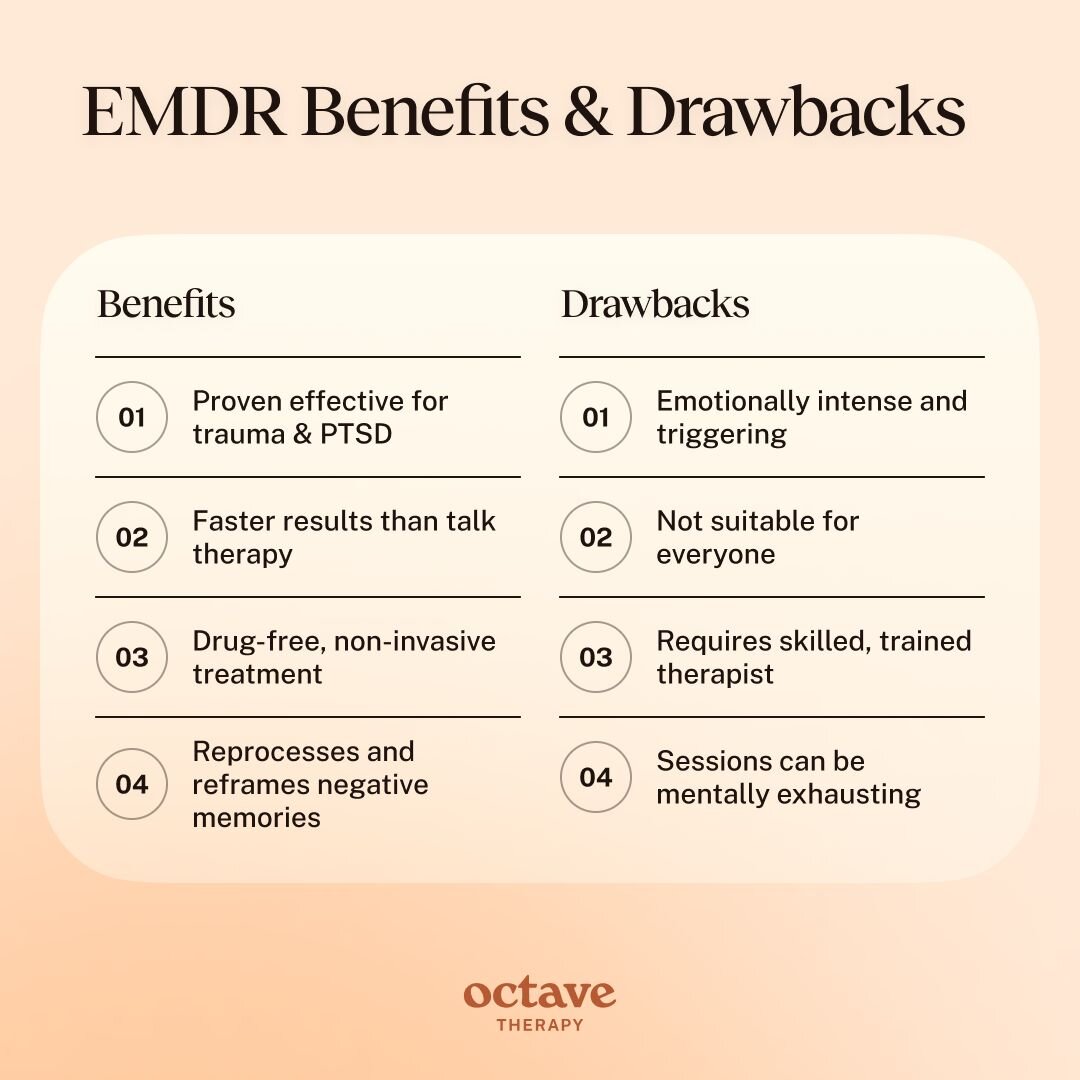
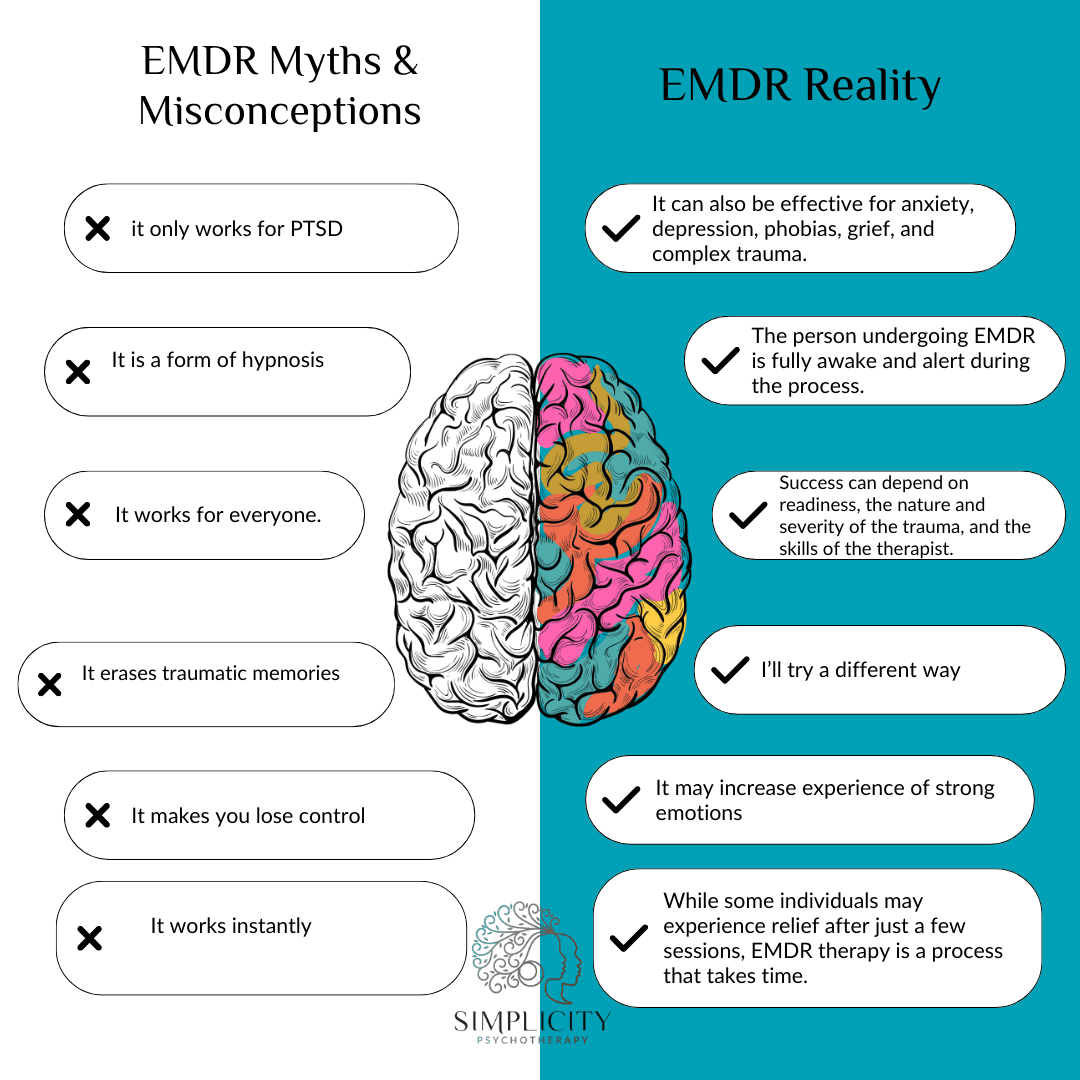
EMDR was designed in the mid-1980s by Francine Shapiro after she noticed a connection between eye movements and reduced emotional distress. It has since been used by millions of people worldwide for trauma and PTSD treatment. The standard protocol involves a therapist guiding you through a series of bilateral stimulation sets — typically eye movements, but sometimes taps or tones — while you focus on a traumatic memory. Most licensed clinicians will tell you it is safe. Most licensed clinicians will also tell you it is not right for every client, and that is where the conversation usually stops. The most common issue I see is that EMDR can surface memories faster than a person's nervous system can process them. When desensitization moves too quickly, clients often report heightened anxiety, sleep disruption, and vivid dreams that last for days or sometimes weeks after a session. A standard EMDR session is 60 to 90 minutes, but the aftereffects do not end when the session ends. Many people need follow-up care, grounding strategies, and sometimes a reduction in session intensity to manage the residual activation. Another problem area is dissociation. Clients with a history of complex trauma or borderline personality traits can dissociate during bilateral stimulation. The therapist needs to recognize this and slow down or stop. I once had a client who began derealizing during a routine desensitization phase. We had been tracking well for three sessions, and then something shifted. The bilateral stimulation triggered a severe dissociative episode that lasted nearly an hour and a half after the official session ended. We had to switch to a completely different approach, spending six more sessions just on stabilization before we could even consider returning to the trauma work. That was a two-month delay caused by not doing a thorough enough pre-treatment assessment.
Headaches and visual disturbances are also more common than most people realize. These usually show up within 24 hours of a session and can last anywhere from a few hours to a couple of days. They are not dangerous in themselves, but they are a signal that the brain is working harder than expected. Adequate hydration, rest, and reduced screen time after a session help significantly. Some practitioners dismiss these complaints. They should not be dismissed. There is also the issue of false memories. This is a sensitive topic, but it is real. During EMDR, the associative nature of memory reconsolidation can sometimes blend separate events or introduce details that were never part of the original experience. This does not happen in every case, but it happens enough that therapists need to be careful about leading questions and must document what the client is recalling versus what may have been suggested. I have seen this occur when a therapist accidentally introduced a frame of reference that the client then incorporated into their memory network. One thing that is not talked about enough is the timing. EMDR works best when the client has established coping skills and emotional regulation tools beforehand. Starting EMDR without adequate grounding techniques is like opening a valve on a pressurized system without having anything to contain the flow. Pretreatment should not be rushed. The resource development and installation phase is not optional. Skipping it increases the risk of complications significantly.
Finally, there is the question of who should not do EMDR. People with certain seizure disorders, severe instability in their current life situation, active substance dependence, or untreated psychosis are generally poor candidates. Some of these are absolute contraindications. Others require modification of the standard protocol. A qualified practitioner will screen carefully and be honest about fit. If a therapist is pushing EMDR as the first-line treatment without a thorough intake, that is a red flag.
Get the Full Details