Darzalex FDA Approval History
Darzalex Fda Approval History and What It Actually Means for Prescribers
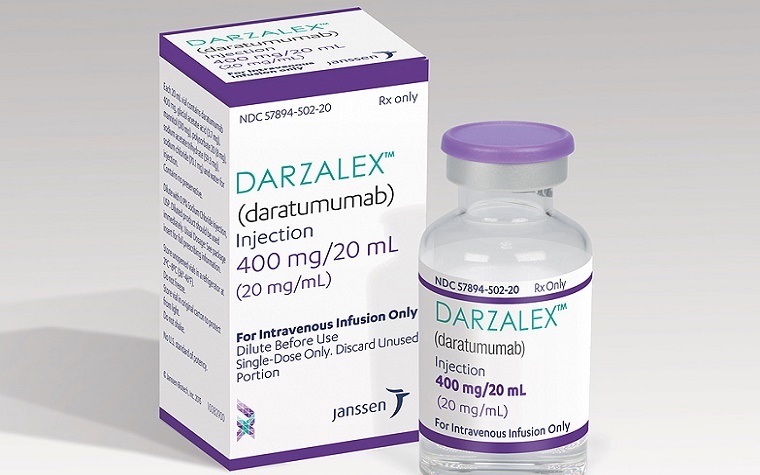
When daratumumab first got FDA clearance, the whole oncology world was paying attention. It was the first CD38-targeting monoclonal antibody to get the green light for multiple myeloma, and it happened in March 2015. The label was narrow though. It was approved only for patients who had already received three or more prior therapies, including a proteasome inhibitor and an immunomodulatory drug, or who had failed both of those classes. That meant the drug was being saved for people who had exhausted most other options. The pivotal trial that drove that initial approval was a study called MAIA, but that was actually for the later indication. The first one was based on a trial called PERRIN, which showed response rates in heavily pretreated patients. It wasn't a cure. Most of those folks responded for a while, but the disease came back. Still, the response rates were meaningful compared to what was available at the time. Then things started moving faster. In November 2016, the FDA expanded the label to include newly diagnosed patients who were going to get an autologous stem cell transplant. That was a big deal because it moved daratumumab earlier in the treatment sequence. You could now give it as part of the upfront regimen, typically combined with bortezomib and dexamethasone. The approval came from data showing improved progression-free survival in that setting. Once it moved into the front line, the way people talked about daratumumab changed completely. It went from a rescue drug to a backbone therapy.
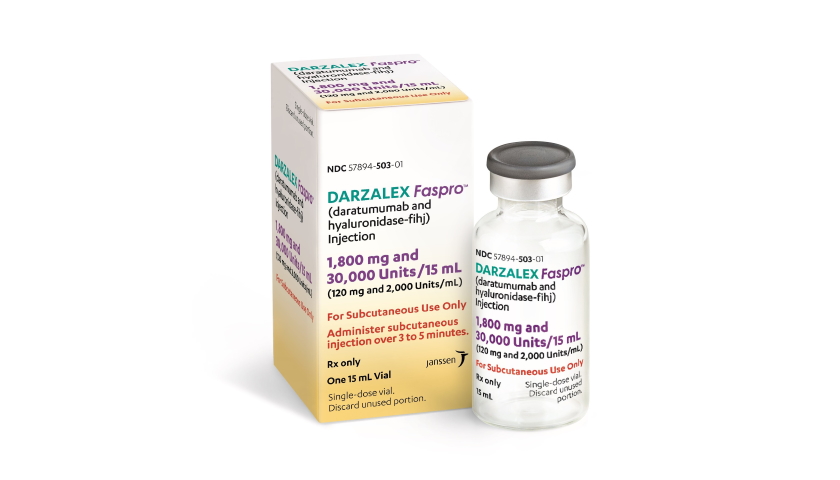
The next expansion came in December 2018, when the label was broadened again to cover newly diagnosed patients who were not candidates for transplant. This one used the combination of daratumumab, lenalidomide, and dexamethasone, which became known as the DRd regimen. That approval was based on the MAIA trial, and the results were solid enough that this combination became a standard first-line option for a large chunk of the myeloma population. We're talking maybe 60 to 70 percent of newly diagnosed patients who wouldn't be heading straight for a transplant. In September 2022, there was another milestone. The FDA approved a subcutaneous formulation of daratumumab. Instead of the two-hour IV infusion, patients could get the drug as a 5-to-10 minute injection. The first dose was still given intravenously to monitor for infusion reactions, but after that, the subcutaneous route was an option. This changed logistics in infusion centers more than almost anything else on the label. We saw wait times drop dramatically and throughput pick up. Some clinics were able to schedule twice as many patients per day on daratumumab once the subcutaneous option became available. Here's a practical problem I ran into that nobody talks about much. When the subcutaneous formulation first came out, a lot of pharmacists and infusion coordinators weren't clear on the billing codes. The IV version uses J-ex codes like J9079, but the subcutaneous version has a different HCPCS code, J3490, and the dosing calculation is completely different. I had a patient who transitioned from IV to SC and their insurance denied three claims in a row because the clinic kept billing the old code. It took me about two weeks and a lot of phone calls before we got it sorted. The workaround was straightforward once I found it — you have to use the weight-based dosing table that came with the subcutaneous approval and make sure the unit count matches the syringe configuration exactly. The vials and prefilled syringes are different, and mixing them up in the billing system causes headaches.
One thing most people miss about this approval history is that each indication expansion didn't just add a new patient group, it also came with different dosing schedules. The IV formulation is dosed weekly for the first eight weeks, then every two weeks, then every four weeks. The subcutaneous version follows a similar schedule but the maintenance phase can start sooner for some patients. If you're tracking treatment duration across a patient population, mixing up the schedules between indications will throw off your data. I've seen it happen in chart reviews where someone assumed all daratumumab patients were on the same cadence. There's also a nuance around companion diagnostic testing. Daratumumab binds to CD38 on red blood cells, which causes a positive direct antiglobulin test across all immunoglobulin classes. This doesn't mean the patient is having an allergic reaction or that the drug isn't working. It's just the mechanism of action. But it complicates blood banking. If a patient on daratumumab needs a transfusion, the crossmatch can be incompatible even though the blood is fine. I had to work with our transfusion service to establish a protocol where they hold off on crossmatching for at least 18 hours after the last daratumumab dose when possible. It adds time to the process but prevents unnecessary delays in emergency situations. The approvals also came with boxed warnings and safety communications. The most notable one involves tumor lysis syndrome, which is a real risk in patients with high tumor burden, especially when daratumumab is used in combination regimens for newly diagnosed disease. There have been postmarketing reports of infusion reactions that were severe enough to require ICU admission, though they're uncommon. The subcutaneous formulation actually has a lower rate of infusion reactions compared to IV, which is one of the reasons the switch got so much traction clinically.
Get the Full Details
If you're looking for the official FDA label and the full prescribing information, that's available through the FDA's database under the brand name Darzalex. The approvals are documented in the FDA Drug Approvals database, and each indication change has a separate announcement with the clinical trial data referenced. CIGNITY Biotech was the original developer, and Juno Therapeutics was involved in the early development before the commercial rights shifted. The current marketing authorization holder is Johnson & Johnson's oncology division. One more thing worth noting about the regulatory pathway. Daratumumab received fast track designation and breakthrough therapy designation at different points, which accelerated the review process for the later indications. The initial 2015 approval went through the standard review timeline, but by the time the subcutaneous formulation came up, the FDA was moving faster. The whole approval-to-label process for the SC version took less than six months from submission to final approval. That's notably quicker than most biologic applications in oncology. The drug itself is a fully human IgG kappa monoclonal antibody. It targets CD38, which is expressed on plasma cells and myeloma cells at high levels. The mechanism involves antibody-dependent cellular cytotoxicity, complement-dependent cytotoxicity, and direct induction of apoptosis. That's why it works across different lines of therapy and in combination with other agents. It's not dependent on a single pathway, which is partly why resistance develops more slowly than with some targeted therapies.
I could keep going, but the approval timeline is pretty much laid out above. March 2015 for relapsed refractory, November 2016 for transplant-eligible newly diagnosed, December 2018 for transplant-ineligible newly diagnosed, and September 2022 for the subcutaneous formulation. Each step expanded the patient population and changed how the drug gets administered in practice. That's the Darzalex FDA approval history in a nutshell.