Fall Risk Assessment in Clinical Practice
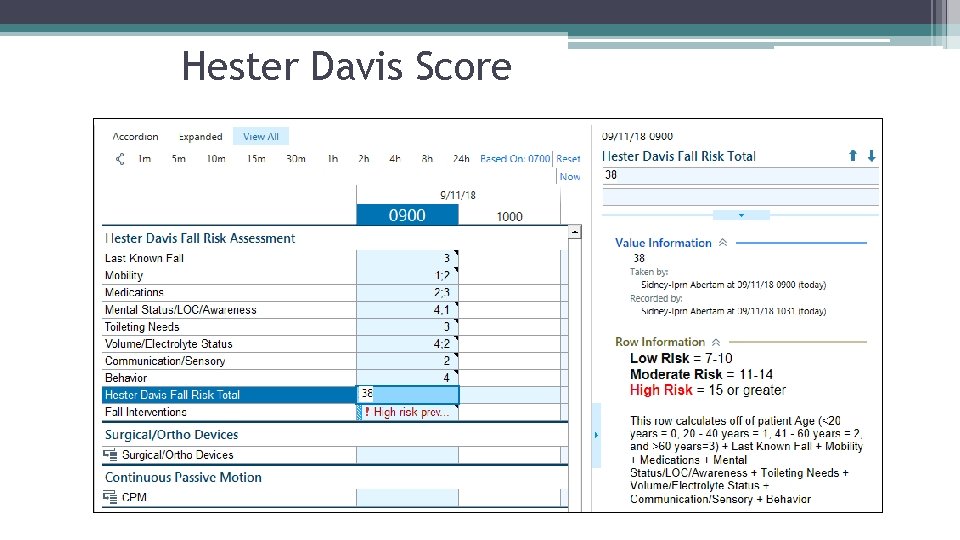
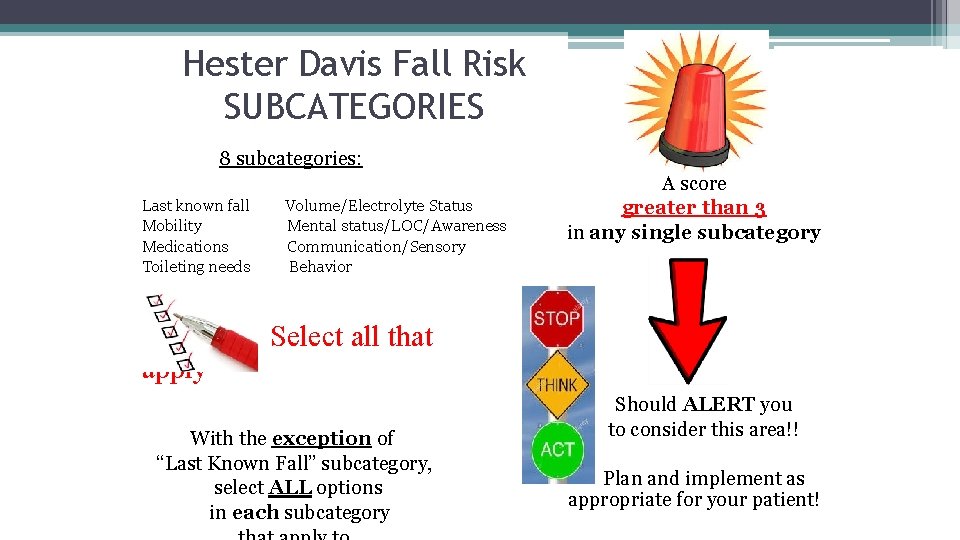
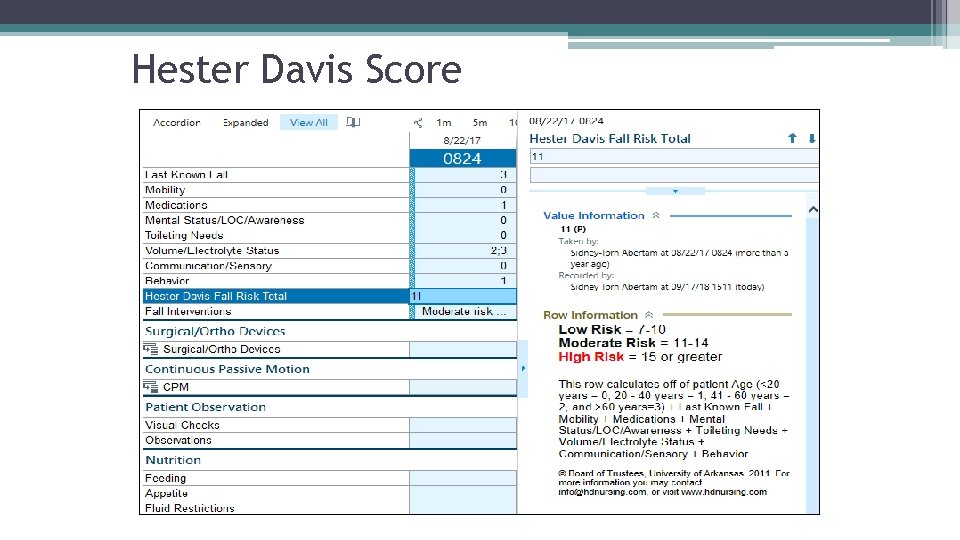
Fall risk tools are everywhere in hospital discharge planning. I've been working in geriatric care for years, and I've seen how these instruments get used—sometimes well, sometimes barely at all. The Davis Fall Risk Assessment Tool sits in that crowded space alongside Morse, STRATIFY, and Hendrich II. It's not magic. It's a checklist with some predictive weight behind it. The Davis tool breaks down into categories you'd expect: mobility status, cognitive function, medication review, and history of prior falls. Each category gets scored, and the total points land you in a risk tier—low, medium, or high. That tier then triggers a care plan. Simple on paper. What nobody tells you is how much the scoring varies depending on who's doing the assessment. I had a case where two nurses scored the same patient four days apart and got completely different risk tiers. The patient was on midazolam, had mild confusion, and walked with a walker. One nurse gave him low risk because he "looked steady." The other caught the medication interaction and flagged high risk. He fell two hours later.
The workaround I settled on is to always run the assessment twice—once within the first four hours of admission, once after the morning med pass. The drug landscape changes overnight. That second window catches things the first one misses.
What the Davis Tool Actually Measures
Beyond the surface categories, the Davis instrument is really measuring three things: motor control under load, cognitive processing speed, and pharmacological risk. The mobility items look at gait speed and balance transitions. The cognitive items screen for attention and executive function—the kind of thinking that prevents someone from stopping when they hit an obstacle. The medication review is usually the heaviest weighted section, and for good reason. I've found that the tool's blind spot is environmental adaptability. A patient can score medium risk on paper and still be safe in a familiar room. Or they can score low and fall immediately after a transfer to an unfamiliar ward. The Davis tool doesn't account for whether the patient has navigated that exact floor layout before. Nobody does, really. Most tools have that gap. Another thing the literature undersells: the tool's predictive power drops sharply after 48 hours. It was validated on acute admission populations, but if you're using it for discharge planning three days into a stay, you're working with stale data. Reassess, or don't rely on the number.
Get the Full Details
When the Davis Tool Fails Completely
Don't use it for patients with acute neurological events. Stroke patients, especially on the left side, can have intact mobility but profound spatial neglect. They'll score decent on gait and balance but walk into walls. The tool doesn't capture unilateral attention deficits. It also struggles with dementia patients who have good motor function but poor judgment. A patient with early-stage Alzheimer's might nail every mobility item but regularly try to get up during the night because they think they need to "get to work." The risk isn't in their legs. It's in their decision-making loop. Davis doesn't weight that heavily enough. If you're working with Parkinson's or Lewy body disease, supplement with the UPDRS motor scale or at least track freezing of gait episodes separately. The Davis tool will underestimate these patients consistently.
Practical Workflow I've Stuck With
Rather than relying on the Davis score alone, I layer it with three things: a actual walk test (not the tool's simulated assessment, a real 10-meter walk with usual assistive device), a medication reconciliation check for QT-prolonging drugs and sedatives, and a bathroom proximity audit. The bathroom distance matters more than most people admit. A high-risk patient who has to cross a 50-foot hallway to use the restroom is a liability waiting to happen. The Davis tool gives you a starting line. It doesn't finish the race. Use it, question it, and then go look at the actual person again.