Understanding DBT Therapy for BPD
Dialectical Behavior Therapy (DBT) was developed by psychologist Marsha Linehan in the late 1980s specifically for treating borderline personality disorder (BPD). It's now considered one of the gold-standard treatments for BPD and has been adapted for other conditions involving emotional dysregulation. DBT is a type of cognitive-behavioral therapy that combines individual psychotherapy with skills training. The therapy is built around the concept of dialectics—finding balance between acceptance and change. For people with BPD, this often means learning to accept their emotions while simultaneously working to change harmful behaviors. The standard DBT program includes four components: individual therapy, group skills training, phone coaching, and therapist consultation teams. Treatment typically lasts about one year, though some people benefit from longer engagement. Sessions are usually weekly and last 45-60 minutes each.
I've worked with enough clients through DBT programs to know that the skills modules can feel abstract at first. The mindfulness component, in particular, often frustrates people who struggle with emotional regulation. One client couldn't sit through even five minutes of breathing exercises without becoming agitated. We ended up modifying the approach—starting with movement-based mindfulness and gradually building up to stillness. That adaptation made the therapy accessible for her where the standard protocol wouldn't have.
Core Components of DBT
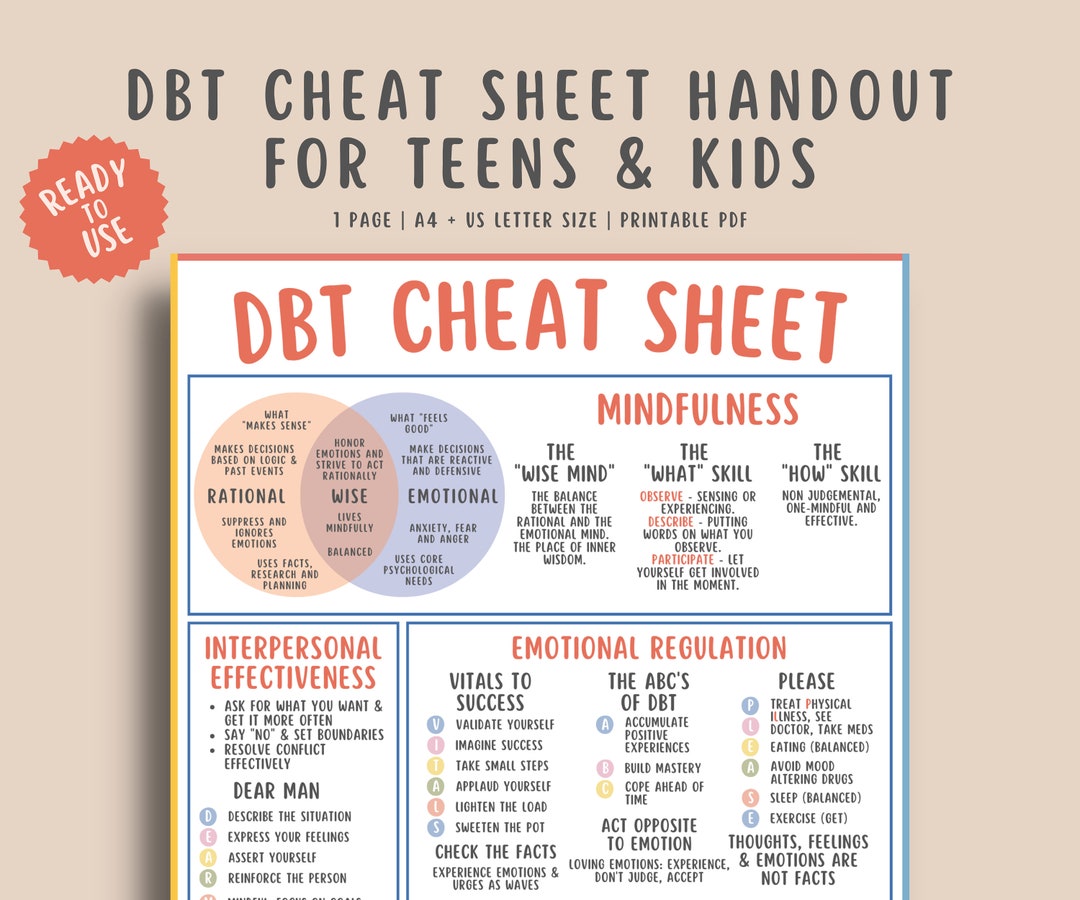
DBT teaches four skill sets: mindfulness, distress tolerance, emotion regulation, and interpersonal effectiveness. Each module addresses specific challenges people with BPD face. Mindfulness focuses on being present in the moment without judgment. This seems simple but is genuinely difficult for someone whose thoughts race and emotions shift rapidly. Skills include observing thoughts, describing experiences, and participating fully in activities. Distress Tolerance helps people survive crisis situations without making things worse. Techniques include self-soothing, improving the moment, and accepting reality. These skills matter most during the early stages of treatment when emotional episodes are frequent and intense.
Get the Full Details
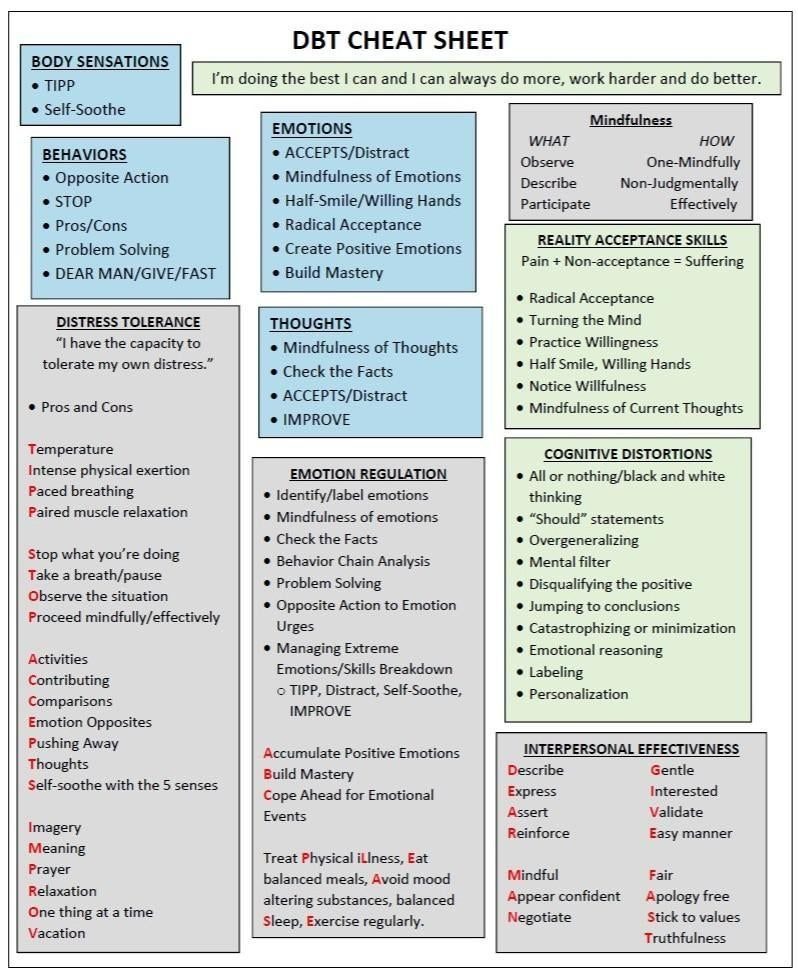
Emotion Regulation addresses the core difficulty in BPD—managing intense emotional responses. Skills include identifying emotions, reducing vulnerability, and changing emotional responses. People learn that emotions are data, not directives. Interpersonal Effectiveness teaches assertive communication while maintaining self-respect and relationships. This matters because people with BPD often struggle with relationships, experiencing them as either perfect or terrible with no middle ground.
How DBT Actually Works in Practice
Individual therapy sessions focus on motivation and applying skills to specific situations. The therapist helps clients identify target behaviors and develop strategies for change. Phone coaching provides real-time support between sessions when clients face crises. Skills training groups meet weekly and follow a structured curriculum. Participants learn techniques through instruction, role-playing, and homework assignments. Groups typically run for about 24 weeks per module cycle. Therapist consultation teams support the clinicians working with BPD patients. This component often gets overlooked but is essential—treating this population is emotionally demanding work. Without consultation, therapists burn out or become ineffective.
One thing beginners miss is that DBT isn't just talk therapy. The homework assignments and skills practice between sessions are where most of the change happens. Clients who skip the practice often plateau or regress. The therapy demands active participation, not passive attendance.
Limitations and When DBT Falls Short
DBT doesn't work for everyone. Some people don't respond to the skills-based approach or prefer more insight-oriented therapies. Access remains a significant barrier—certified DBT providers are concentrated in urban areas, and treatment isn't always covered by insurance. The therapy requires commitment to skills practice and diary cards documenting emotions and behaviors. People who can't maintain this structure often don't complete treatment. Additionally, DBT focuses primarily on reducing self-harm and crisis behaviors. It may not address all aspects of BPD, particularly personality structure and deeper relational patterns. If DBT isn't available or suitable, other evidence-based treatments for BPD include Mentalization-Based Treatment (MBT), Transference-Focused Psychotherapy (TFP), and Schema Therapy. Each has its own strengths and appropriate patient profiles.
Getting Started with DBT
Finding a qualified DBT provider involves checking credentials through the Behavior Technology Training Institute or local professional organizations. Look for therapists trained in comprehensive DBT, not just skills modules. Assessment typically involves evaluating suicide risk, self-harm behaviors, and treatment history. This screening ensures the therapy matches the person's needs and severity level. Treatment decisions should involve collaborative discussion between client and provider. Medication may accompany DBT for co-occurring conditions like depression or anxiety, but there's no FDA-approved medication specifically for BPD. Medication management should be coordinated with DBT treatment rather than replacing it.
Progress in DBT isn't linear. Clients often experience setbacks, especially when facing stress or relationship conflicts. The therapy teaches that recovery involves skill practice, not elimination of all emotional difficulties. Measurement through diary cards and session ratings helps track progress objectively. The research supports DBT's effectiveness for reducing self-harm, hospitalizations, and treatment dropout rates compared to treatment as usual. Studies show sustained benefits at one-year follow-up for many participants, though maintenance skills practice matters most for long-term outcomes.