Group Cognitive Behavioral Therapy: What It Actually Looks Like When You Sit in a Circle
I used to think CBT was just worksheets and homework assignments, then I facilitated my first group format. It was nothing like the solo sessions I had read about in textbooks. The dynamics shift completely when you put six people in a room with a therapist and one of them starts dissecting their catastrophic thinking patterns at 7 PM on a Tuesday. Let me explain how De Terapia Cognitiva Conductual Formato Grupo actually works, because most guides get this wrong. They describe the theory perfectly but skip the messy human details that determine whether a group flies or implodes.
The Core Mechanism Nobody Mentions
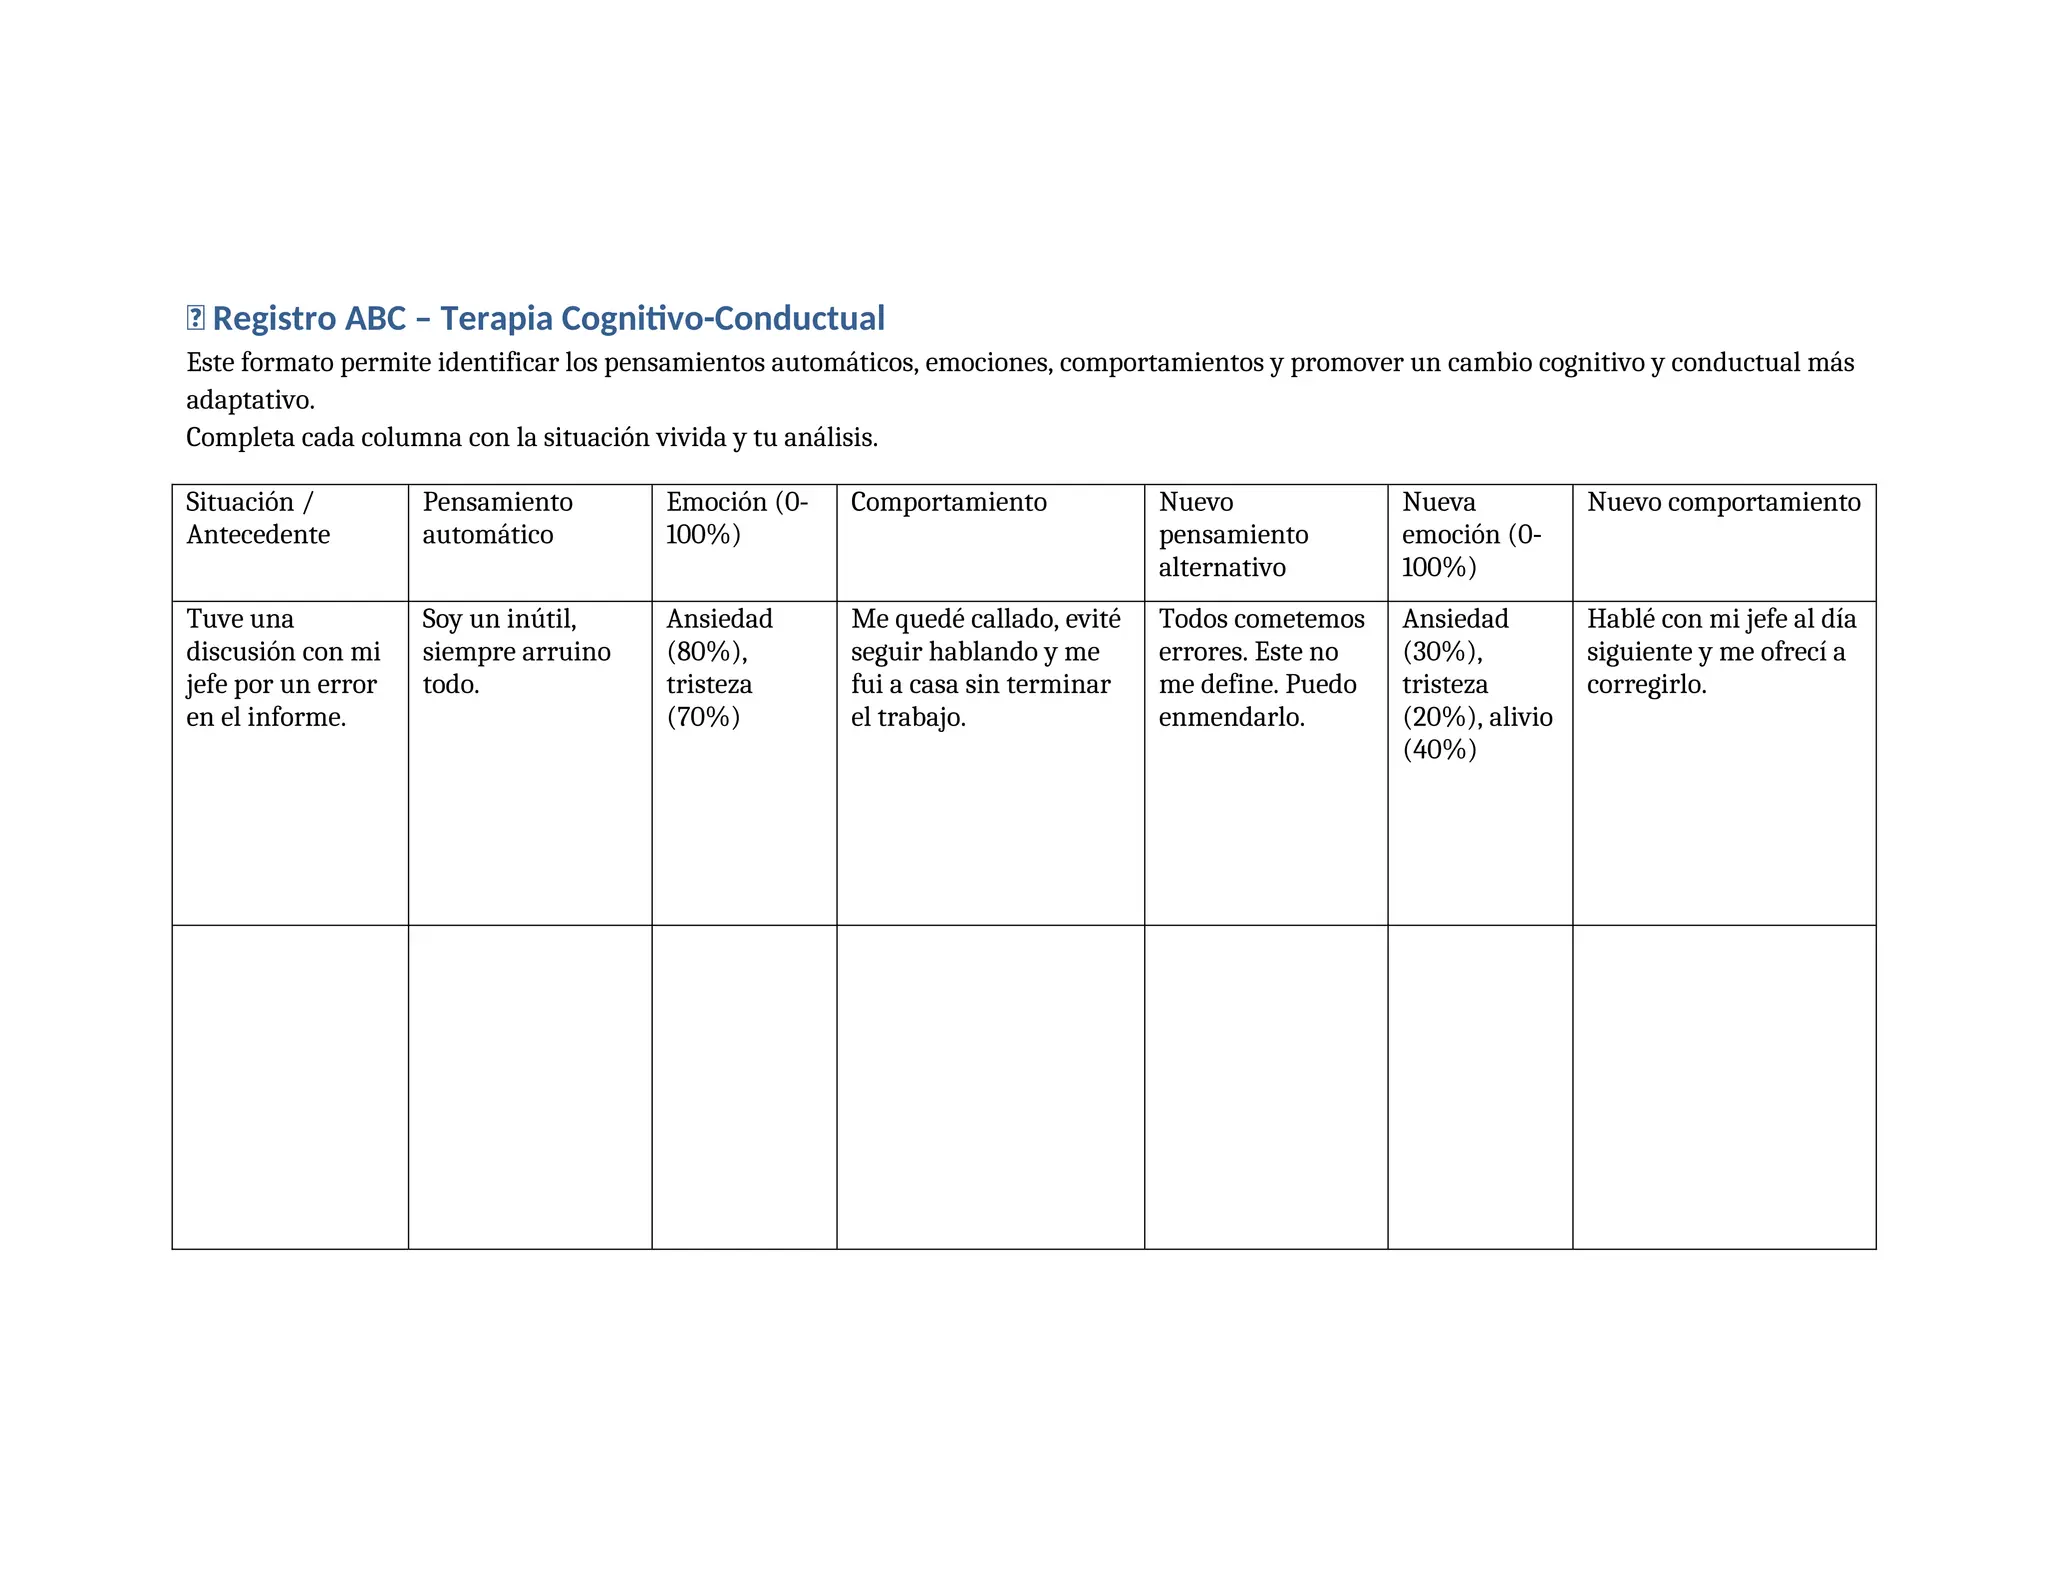
CBT in individual format follows a pretty linear path: identify the automatic thought, examine the evidence, generate a balanced alternative. In group format, you add something called the generalization effect. That is the phenomenon where a participant realizes their cognitive distortion is not unique to them when they hear someone else describe nearly identical thinking patterns five minutes earlier. This creates a double mechanism. You get the standard cognitive restructuring that happens in solo work, plus a normalization component that individual therapy simply cannot replicate. The person who walks in thinking their anxiety makes them broken often leaves realizing seven other people have exactly the same catastrophic predictions about routine social situations. I remember one specific session where a client named Marcus kept describing his social anxiety as if it were some bizarre personal failing. Three other group members quietly raised their hands and said they did the exact same mental rehearsal before entering any workplace. Marcus basically cried. Not in a dramatic way, just those quiet tears where someone finally stops being ashamed of something they thought was invisible.
Structural Components That Make or Break a Group
The format itself matters enormously. Standard group CBT runs 8 to 12 weeks with sessions of 90 to 120 minutes. You typically see 6 to 10 participants. Anything above 10 and the cognitive work gets shallow because there is no time to dig below surface-level complaints. Anything below 5 and you lose the generalization effect I mentioned earlier. The structure within each session usually follows this pattern: check-in, agenda setting, focused skill work, group discussion, homework assignment. The check-in takes about 15 minutes. Agenda setting another 10. The actual skill work and discussion occupies the bulk of the session. Homework explanation wraps up the final 15 minutes. I learned the hard way that skipping the agenda setting segment is a catastrophic mistake. Without it, the session drifts into what I call trauma dumping mode, where one or two dominant personalities monopolize the time with personal stories that have zero connection to cognitive restructuring. The group leaves feeling heard but fundamentally unchanged.
Get the Full Details

Homework: The Actual Work
Here is a counterintuitive insight that beginners consistently miss. The cognitive work does not primarily happen during the session. It happens during the week when participants complete their thought records and behavioral experiments. The session is where you troubleshoot the homework, refine the techniques, and benefit from the group's collective perspective. Typical homework includes daily thought records, behavioral activation schedules, exposure hierarchies, and sometimes digital mood tracking. A compliant participant might spend 20 to 30 minutes per week on this work. Non-compliance rates in groups average around 40 to 60 percent, which is significantly higher than individual therapy homework completion rates. I had a workaround for the homework compliance problem that I now use consistently. Instead of assigning generic thought records, I ask each participant to pick one specific upcoming situation and complete a predicted outcome versus actual outcome analysis for that event. The specificity makes it feel less like homework and more like an experiment. Completion rates jumped from roughly 45 percent to about 75 percent with this approach.
Who This Format Actually Helps
Group CBT shows strong evidence for anxiety disorders, depression, obsessive-compulsive patterns, and certain personality disorder traits. The research base is strongest for generalized anxiety and recurrent depressive episodes. Social anxiety shows moderate-to-strong results, particularly when the group format directly targets the avoidance behaviors that maintain the disorder. It is less effective for acute crisis situations, active substance dependence, severe personality disorders with borderline features, and anyone currently experiencing psychosis. These populations typically require individual intervention or a different therapeutic modality altogether. I encountered an edge case last year where I incorrectly placed a participant with undiagnosed bipolar disorder into a standard anxiety group. The manic episodes disrupted the group cohesion significantly and the cognitive work became secondary to damage control. We transferred that participant to individual therapy within two weeks and the group stabilized immediately. I now screen more rigorously before admission.
Pitfalls That Damage the Process
One common failure mode is the dominance problem. Two or three verbose participants can consume 70 percent of the session time, leaving the quieter members with minimal opportunity for cognitive work. The skilled group therapist learns to interrupt gently but firmly, redirecting back to the agenda and explicitly inviting quieter members into the discussion. Another failure mode I see frequently is the advice-giving trap. Participants love giving each other advice, but advice is the enemy of cognitive restructuring. When someone says "you should just try breathing exercises," they are bypassing the cognitive work entirely. I explicitly state at the beginning that the group is not an advice-giving circle and redirect any advice-giving toward examining the thinking patterns underneath it. A third pitfall is premature closure. When a participant shares something vulnerable and the group responds with genuine empathy, there is a temptation to linger in that emotional moment. But CBT groups need to move toward cognitive work. I learned to acknowledge the emotional response briefly, then pivot explicitly: "That sounds really difficult. Let me ask you something about the thinking pattern behind that reaction."

How to Find a Qualified Group
Look for credentials first. The facilitator should hold licensure in psychology, clinical social work, or counseling, with specific training in CBT group formats. Membership in professional organizations like the Academy of Cognitive Therapy or local CBT chapters is a reasonable signal of ongoing education. Ask about the structure explicitly. A well-run group will describe the session format, homework expectations, group size limits, and screening process upfront. If they cannot articulate these details or seem vague about the structure, that is a red flag. Quality groups are transparent about logistics because transparency itself builds the therapeutic alliance. Check whether they offer an initial consultation. Good therapists will want to assess whether group format is appropriate for your specific concerns before committing you to a full cycle. If someone accepts you immediately without any screening conversation, be cautious.
The Honest Downsides
Group CBT is not a perfect solution. It requires a level of verbal flexibility and emotional regulation that some participants simply do not possess at the point of entry. The peer feedback, while powerful, can sometimes be inaccurate or unhelpful, and less experienced groups may reinforce maladaptive patterns rather than challenge them. The time commitment is substantial. Ninety to 120 minutes weekly for eight to twelve weeks, plus homework time, adds up to roughly 12 to 20 total hours of engagement. This is more demanding than many individual therapy arrangements and creates practical barriers around transportation, childcare, and scheduling. If group format does not feel like the right fit, individual CBT remains the gold standard with equally strong evidence bases. Some people simply need the focused attention of one-on-one work, and that is completely valid. There is no shame in opting for individual therapy when group dynamics feel overwhelming or unproductive.