How the Kübler-Ross Model Actually Works in Practice
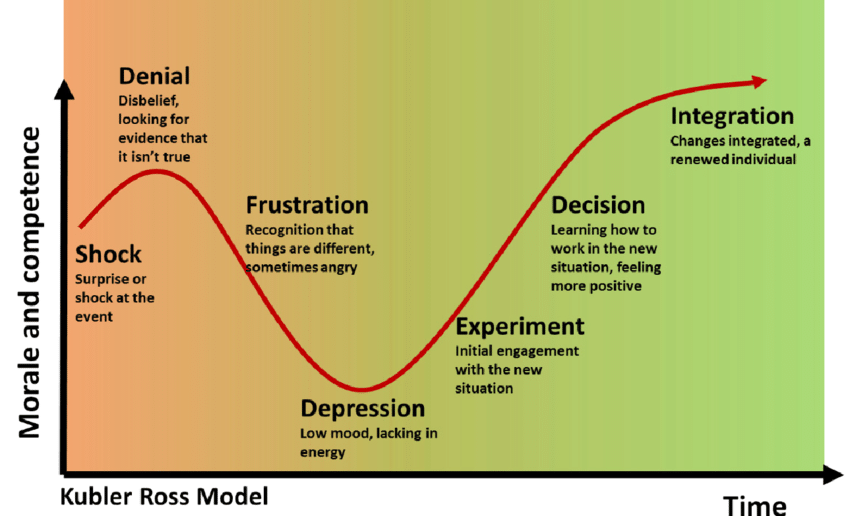
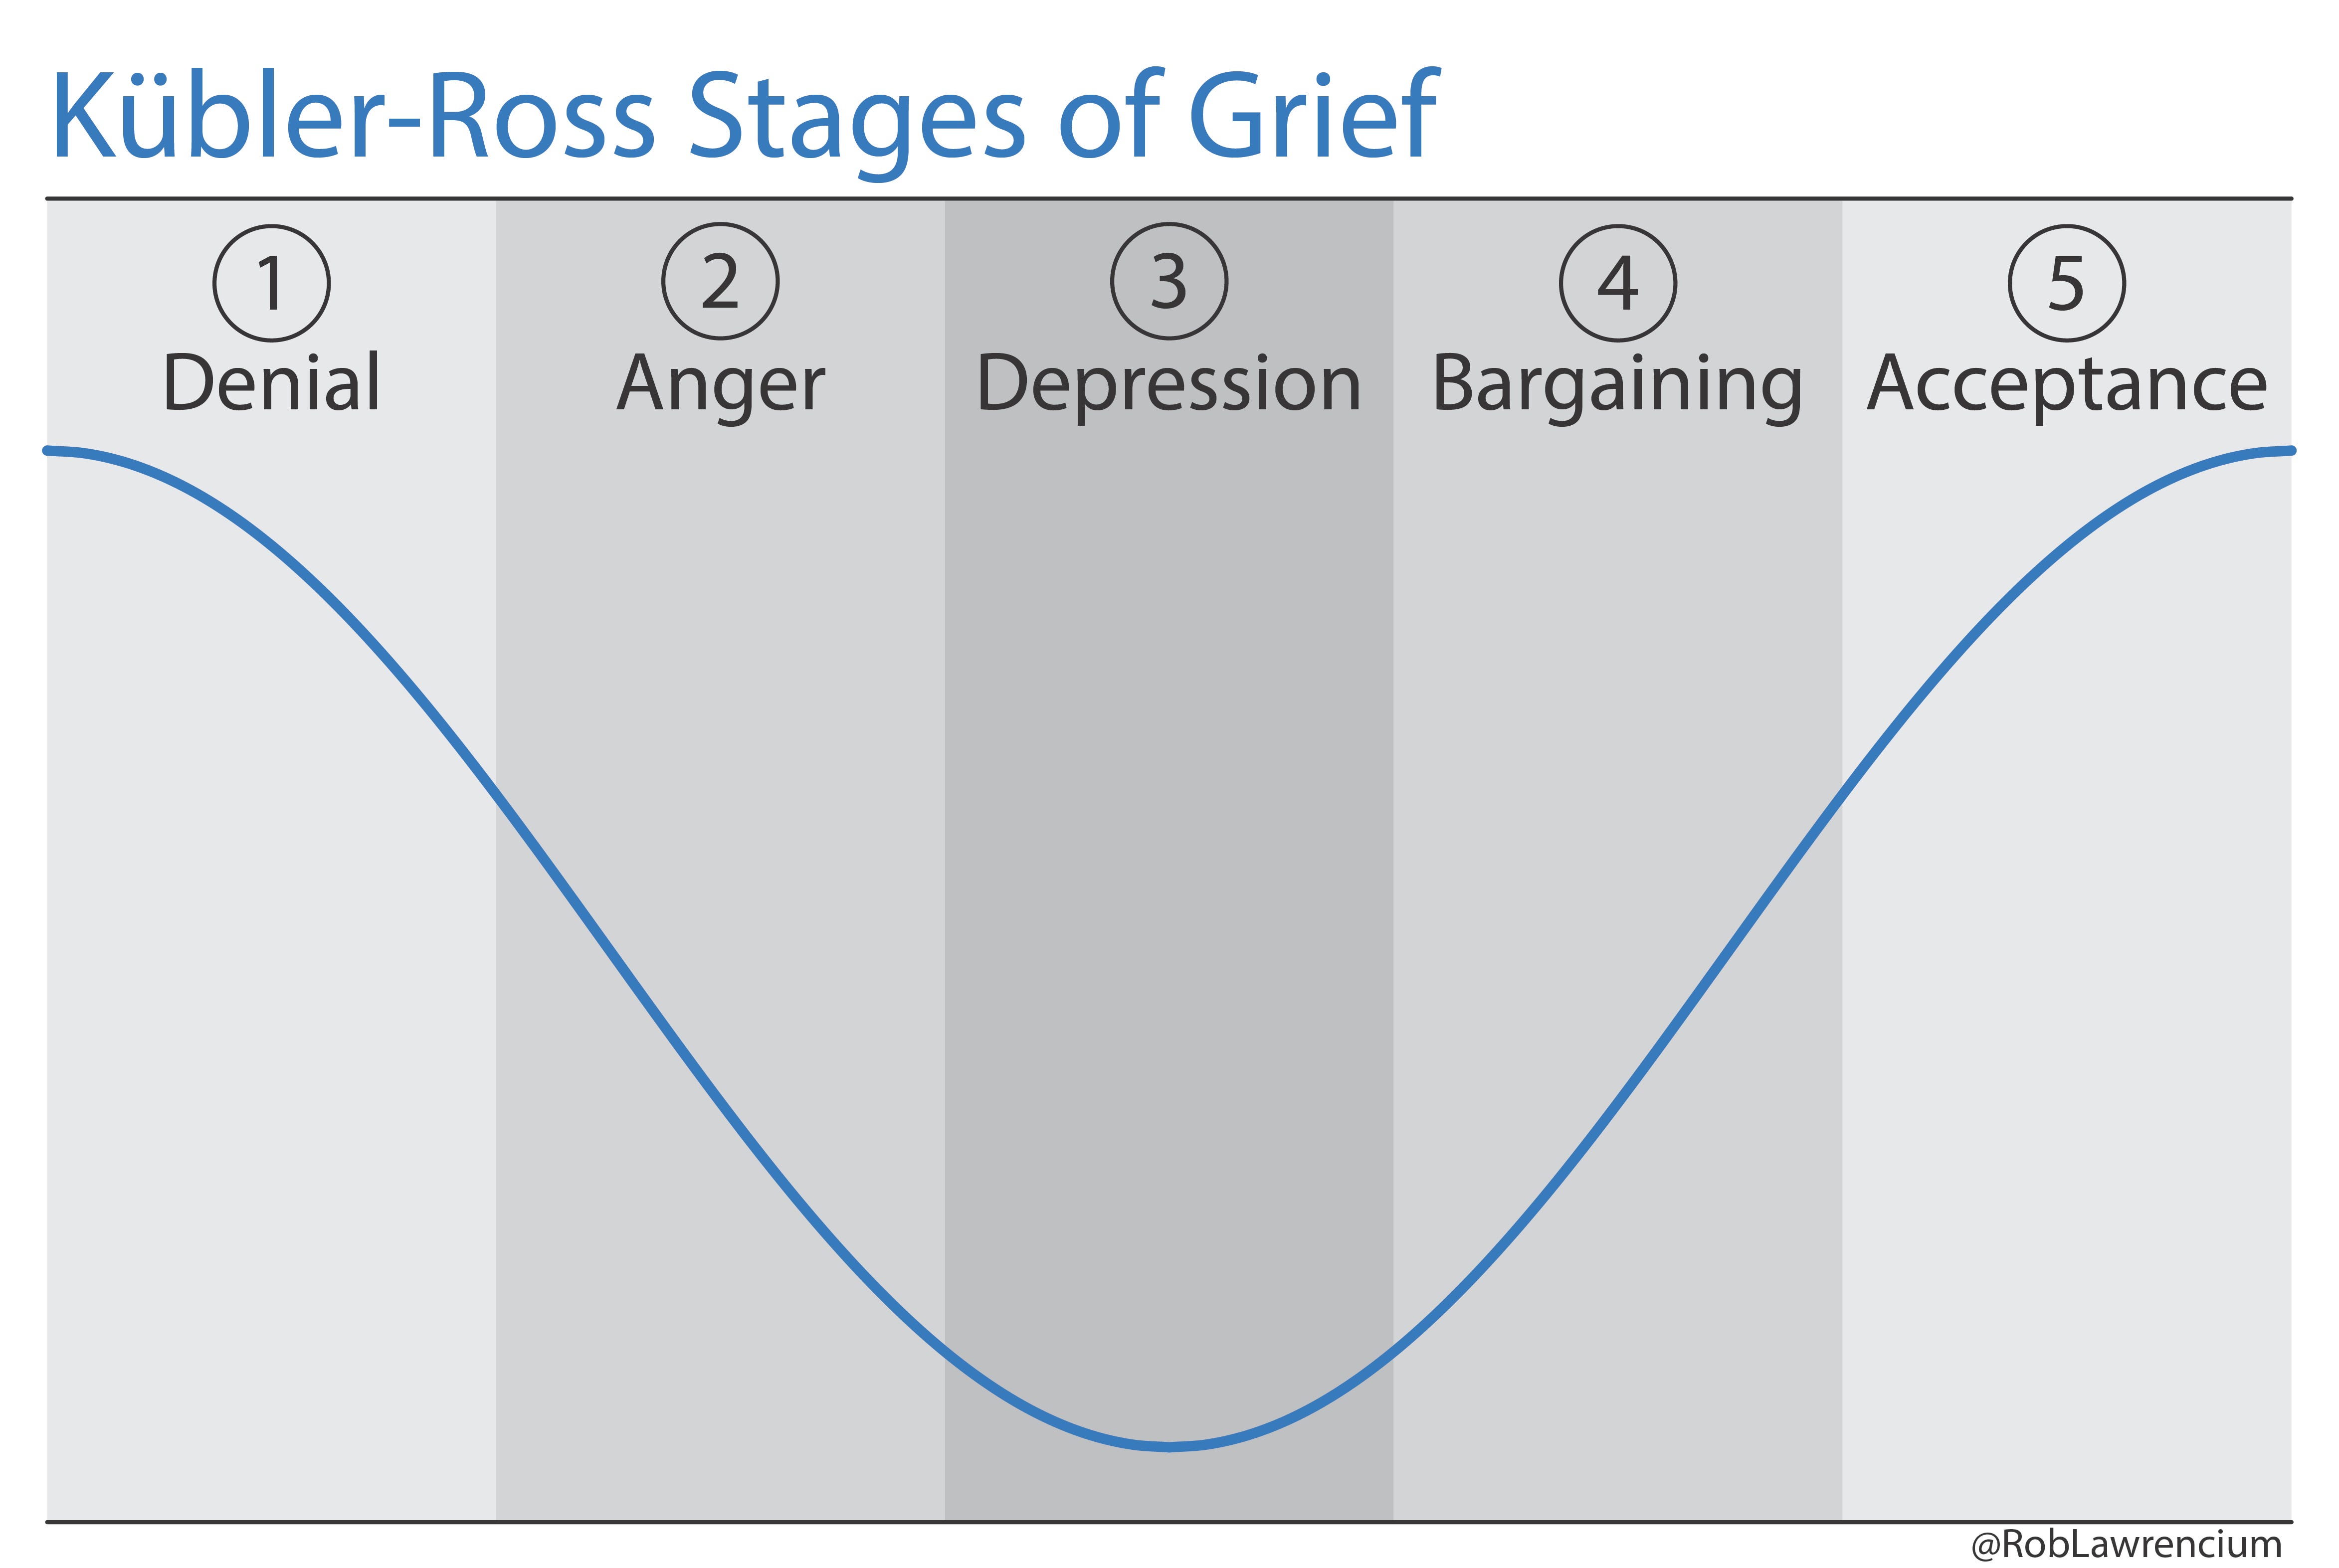
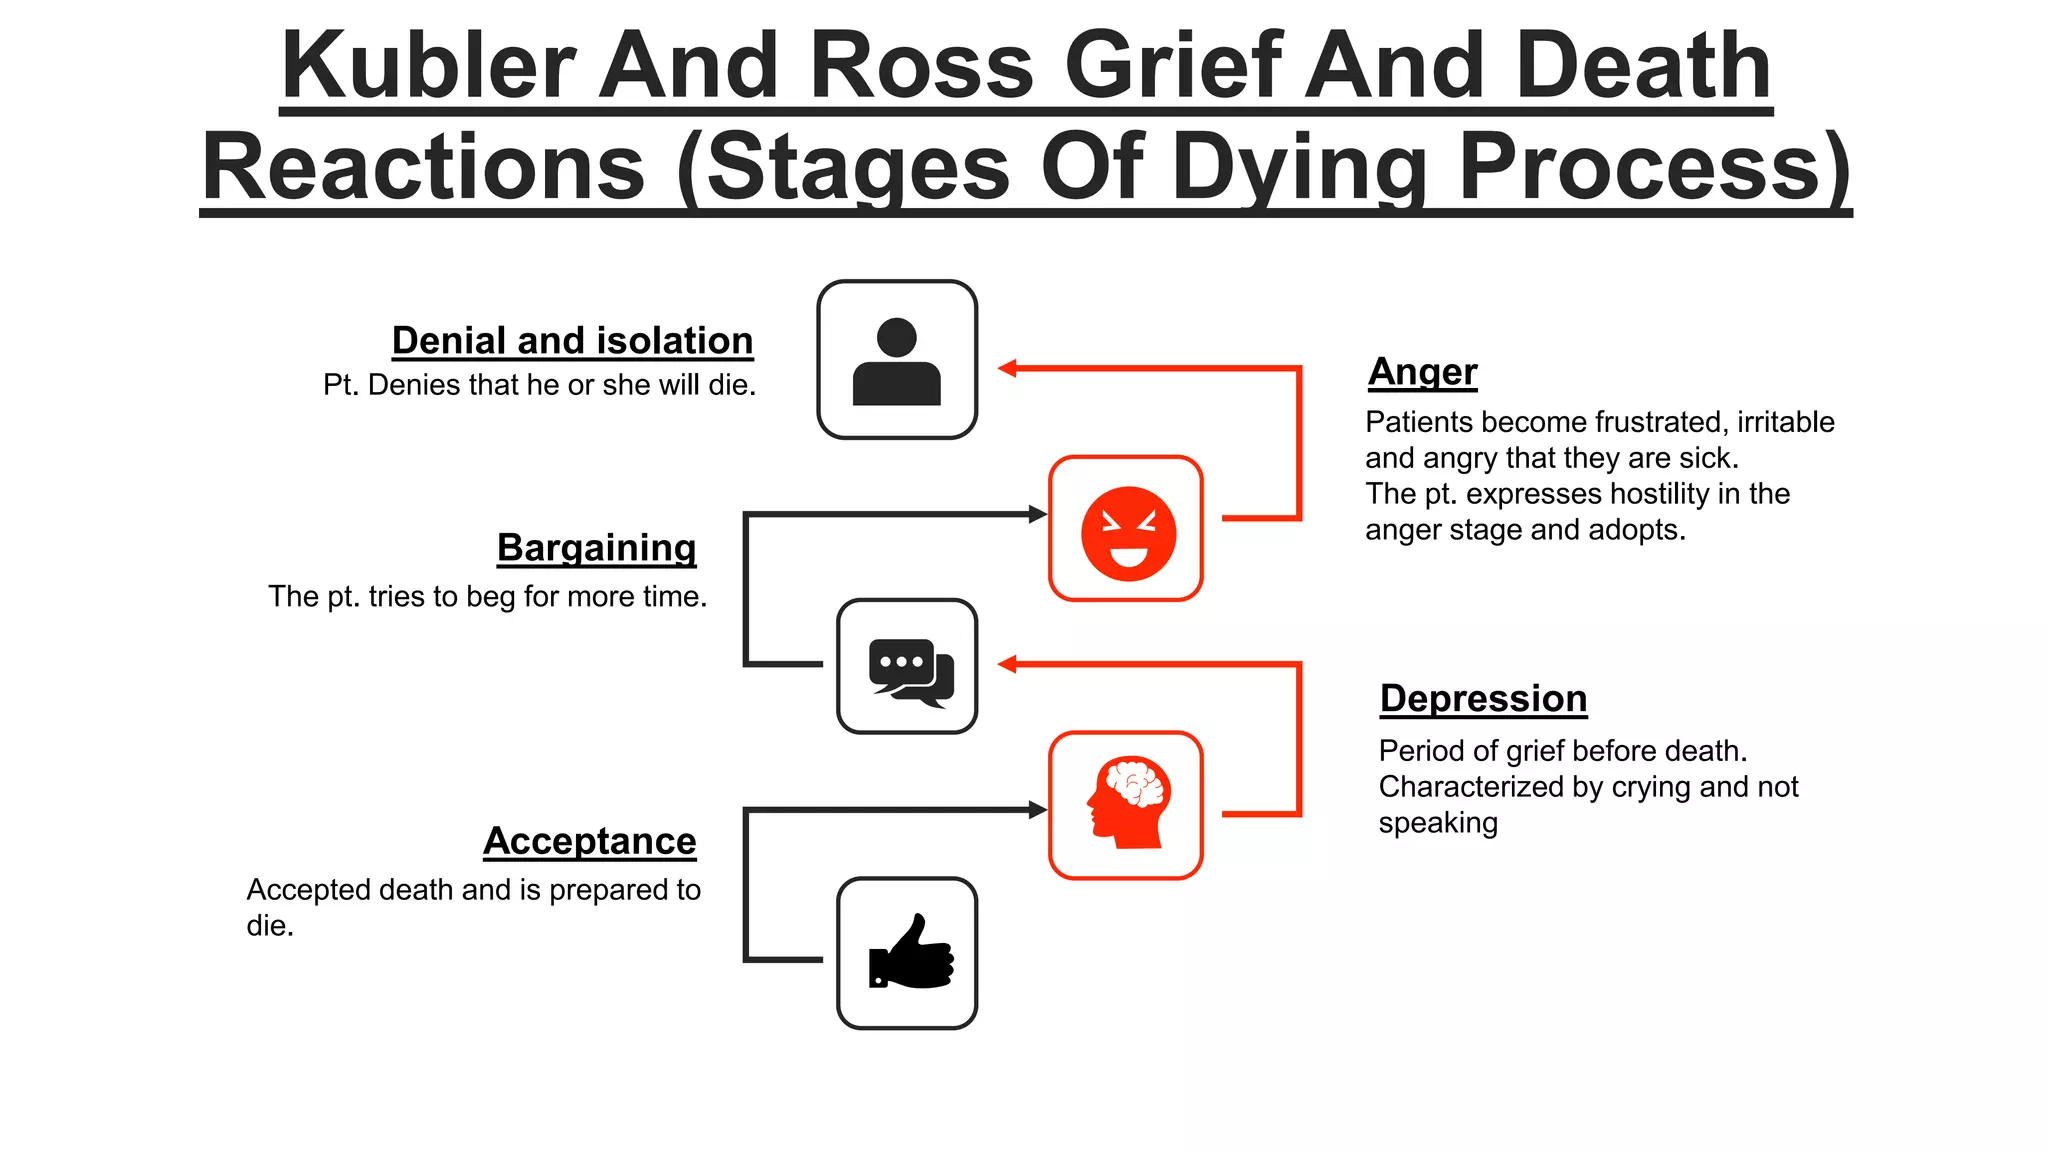
The five-stage model came out of Elisabeth Kübler-Ross's 1969 book On Death and Dying. She interviewed terminally ill patients at a Chicago hospital and noticed they tended to move through a set pattern of emotional responses. The stages are denial, anger, bargaining, depression, and acceptance. That's the shorthand version. The reality of working with people who are actually going through this is a lot messier. When I started working in palliative care, the first thing they drilled into you was the model. It's on the wall in the break room. You hear it referenced constantly. But the patients don't read the wall. I remember one patient, a man in his fifties with metastatic pancreatic cancer, who went straight to anger and stayed there for weeks. He didn't do any of the other stages in any recognizable order. His wife was convinced he was "doing it wrong." The model isn't a checklist. It's a framework for recognizing that people process the fact that they're dying in highly individual ways. The common mistake beginners make is treating the stages as sequential. They aren't. People cycle through them, skip them entirely, or get stuck in one for months. I had a case where a patient oscillated between bargaining and depression for six weeks before anything resembling acceptance emerged. Not linear. Not neat. Just what happened.
Here's something most introductory courses won't tell you: the original study had serious methodological limitations. Kübler-Ross only studied patients in a single hospital in Chicago. The sample size was small, and she was looking at people who were already engaged in the therapeutic process. The model has been heavily criticized since the 1990s, and subsequent research hasn't really supported the idea that most people move through all five stages in order. A 2014 study published in the Journal of Palliative Medicine found that depression and acceptance were the most commonly reported responses, while denial and anger were less frequent than the model predicts. Bargaining, in particular, doesn't show up in the data the way people expect. Still, the model persists. It's useful as a starting vocabulary for conversations about grief, and it gives families a way to understand what might otherwise feel random and frightening. The trick is knowing when it helps and when it gets in the way. I learned the hard way how damaging it can be to force the model onto someone. A colleague once told a family that their father wasn't "accepting" his diagnosis because he was still angry, and that he needed to move on to the next stage. The father heard this through the grapevine and stopped talking to the nursing staff entirely. He wasn't resisting the model. He was angry because people kept telling him how to feel. We had to spend weeks rebuilding that trust, and the model was partly responsible for the breakdown.
The workaround I use now is simple. I reference the stages only when a patient or family brings them up. Otherwise, I just listen. If someone says, "I think I'm in the anger stage," I ask what that looks like for them specifically. What does anger feel like in their body? When does it come and go? What triggers it? That conversation is usually far more informative than checking a box on a stage inventory. One more practical note: the model was designed for people facing their own mortality. Applying it to bereaved family members or caregivers is a different thing entirely, and the research support for that application is even thinner. Spousal grief, for example, follows different patterns. The Kübler-Ross framework doesn't map well onto complicated grief or prolonged grief disorder, which have their own diagnostic criteria and treatment pathways. If someone is stuck in what looks like denial six months after a loss, the model won't help you figure out whether that's normal or pathological. You'd need a proper clinical assessment for that. There's no downloadable toolkit or certification for using this model correctly. It's not a product. It's a concept that you either understand well enough to use thoughtfully or you don't. The best practitioners I've worked with treat it like a rough sketch, not a blueprint. They keep it in the back of their mind and pull it out when it's actually useful, which is less often than you'd think.
Get the Full Details