How Spinal Decompression Actually Works
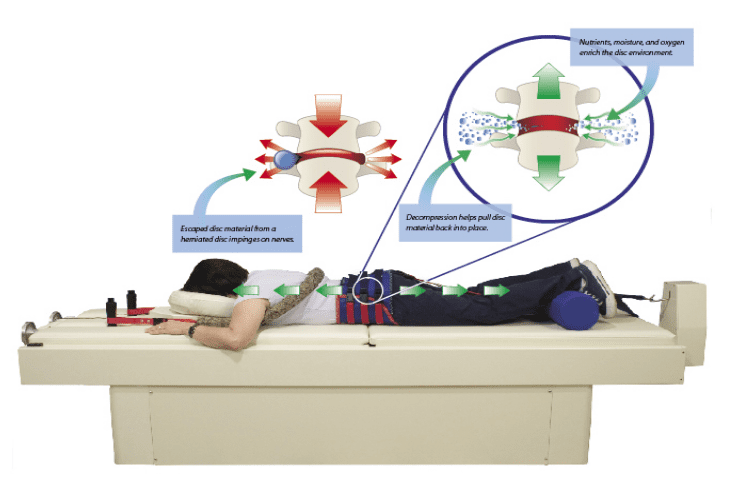
Most people have no idea what happens mechanically during decompression therapy. The idea sounds simple: pull on the spine to create space between vertebrae. The reality is that traction force needs to be precisely calibrated to the patient's weight, the angle of pull, and the specific disc level being treated. Get any of those variables wrong and you're just stretching ligaments without meaningful intradiscal pressure reduction. Here's the part nobody tells you clearly. When a disc herniates, the nucleus pulposus has pushed through a tear in the annulus fibrosus and is pressing on nearby nerve roots. Non-surgical decompression aims to create negative pressure inside the disc space, which can help retract that protruding material away from the nerve. It's not magic, and it doesn't work for every type of herniation, but when it does work, it does work well.
What to Expect During Decompression Therapy For Herniated Disc
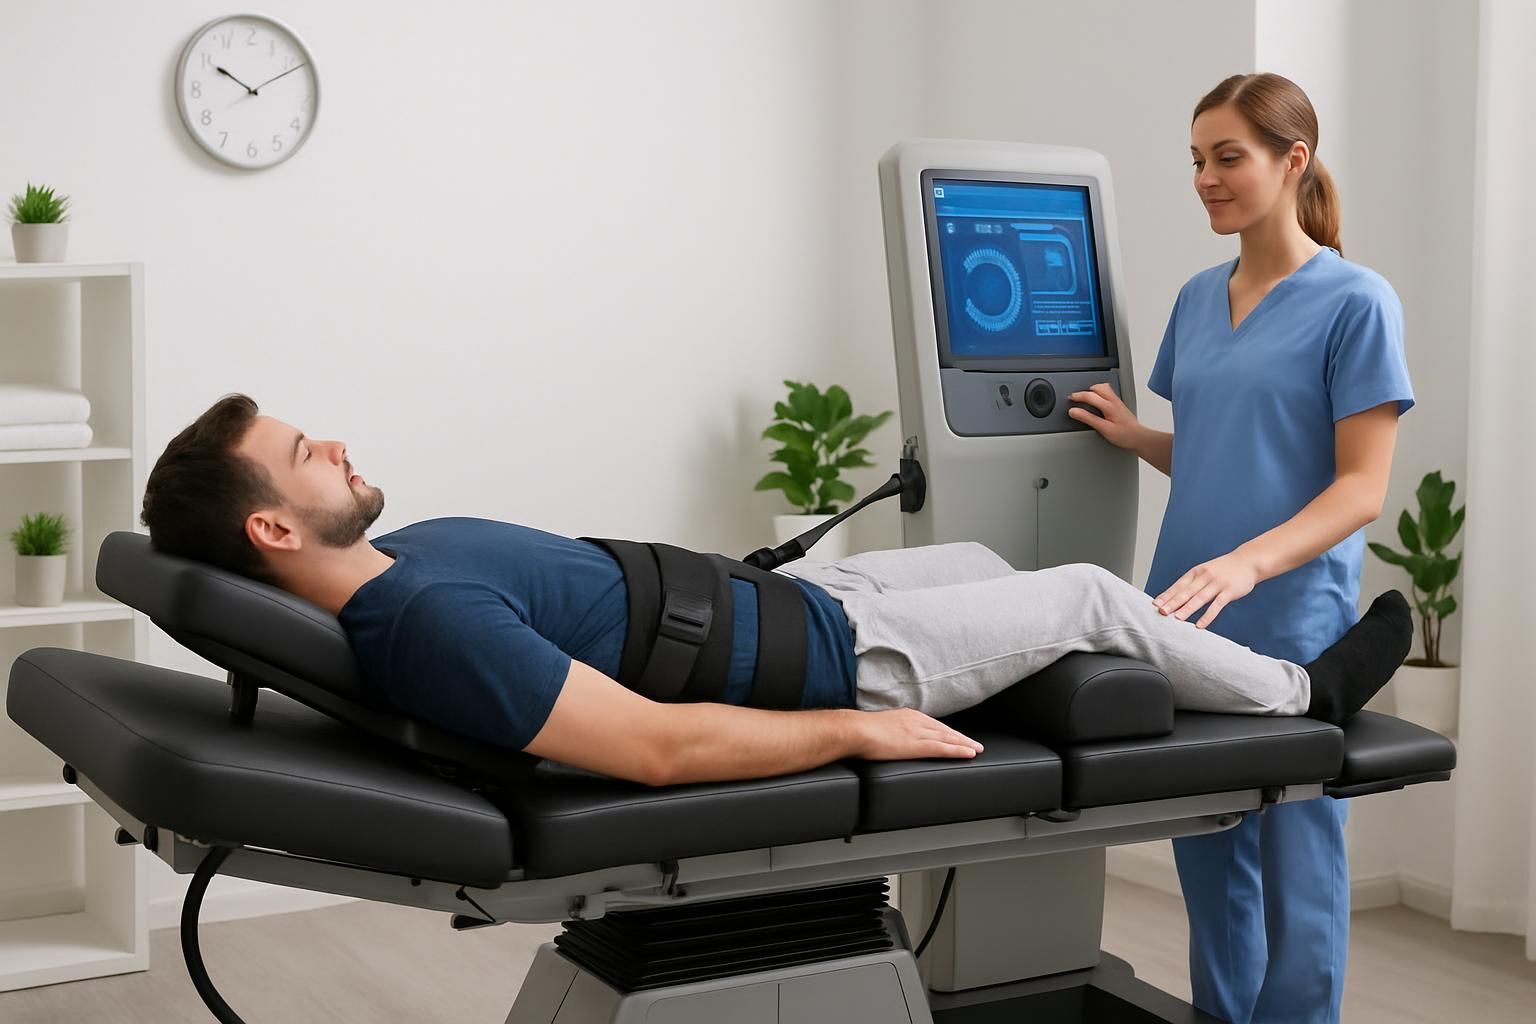
A typical session runs between 20 to 45 minutes on a motorized decompression table. You lie on your back or stomach, harnesses are positioned around your pelvis and sometimes your upper torso, and the machine applies a controlled pulling force. The force cycles — it pulls, holds briefly, then releases. That cycling pattern is what separates actual decompression therapy from old-school static traction. Static traction stretches tissues linearly and tends to cause muscle guarding after a few minutes. The body clamps down because it interprets the constant pull as a threat. Cycled decompression avoids that reflex by giving the muscles periodic rest, which means you can safely apply higher forces without triggering spasms. I've seen clinics use forces up to 60% of the patient's body weight on lower lumbar segments, which would be intolerable under continuous static loading.
The Setup Process and Patient Positioning
Positioning matters more than most providers emphasize. For L4-L5 and L5-S1 issues, which account for roughly 90% of herniated disc cases, supine positioning with hips and knees flexed at about 90 degrees tends to relax the psoas muscle and reduce lumbar lordosis. That neutral spine position lets the traction force translate more directly into disc separation rather than just pulling on the paraspinal muscles. The pelvic harness should sit low on the iliac crests, not higher up around the lower rib cage. A common mistake I see is placing the harness too high, which shifts the pull axis upward and creates shear forces at the thoracolumbar junction instead of the intended lumbar segments. Double-check that strap placement before every single session. One misaligned harness and you're wasting time while potentially irritating the wrong area. Upper body harnesses are sometimes added for distraction at higher lumbar levels or for cervical cases. For a standard lower lumbar herniation, a pelvic-only setup handles the job fine. Don't overcomplicate it.
Get the Full Details
Force Parameters and Treatment Protocols
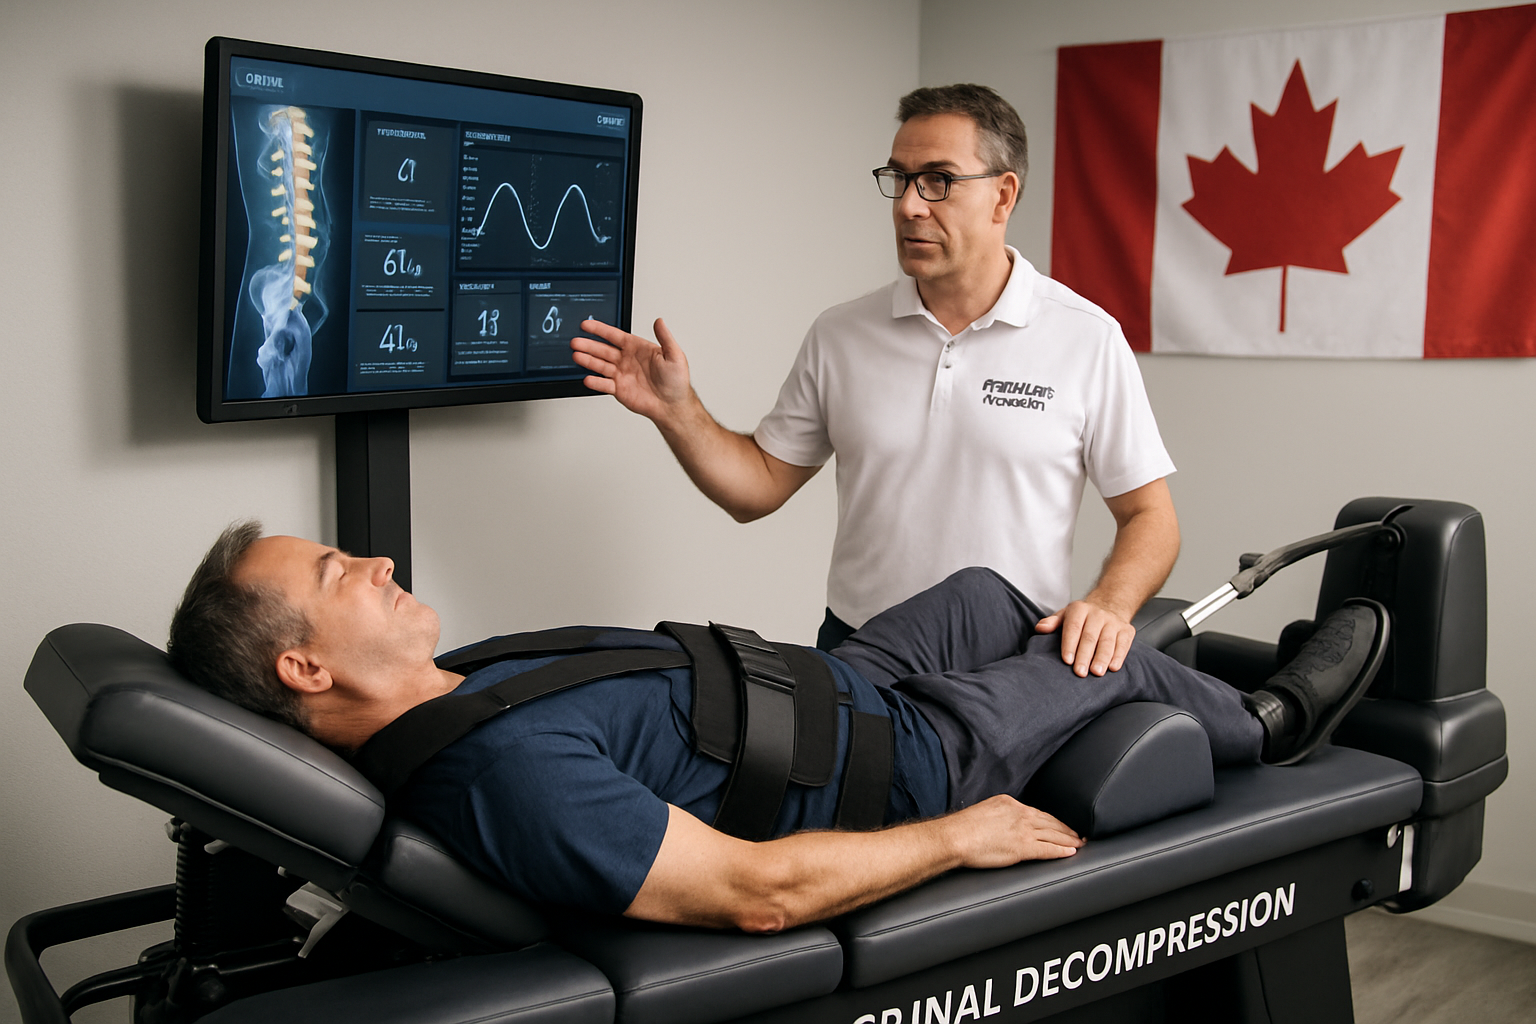
Starting force is usually 25 to 30 percent of body weight. From there, you increase in 5 percent increments every few minutes until you find the patient's threshold. The target is typically 40 to 60 percent of body weight for lumbar cases, held for 2 to 4 seconds at peak, then released for 8 to 12 seconds. That ratio of hold-to-release time is important — longer release phases let the disc rehydrate slightly between cycles. Frequency matters too. Two to three sessions per week for four to six weeks is the standard protocol most studies reference. Some patients feel relief after one session, others need the full course. There's no reliable way to predict which group they fall into beforehand.
Edge Case: When Patients Can't Tolerate the Force
I dealt with a patient a while back who had a confirmed L5-S1 herniation but couldn't tolerate more than 20 percent of his body weight before his paraspinal muscles would spasm. We tried adjusting the angle, switching to prone positioning, adding heat beforehand, even breaking the session into shorter intervals. Nothing moved the needle past that 20 percent ceiling. What finally worked was a hybrid approach — starting with very gentle mechanical decompression at 15 to 20 percent for about 10 minutes to calm the area, followed immediately by manual McKenzie-based extension movements and nerve gliding exercises. The decompression created the initial space, and the mobilization maintained it while also addressing the mechanical component driving the herniation forward. He progressed from there over the next three weeks and avoided surgery. The takeaway: if you're hitting a force ceiling early, don't just push harder or cancel the treatment. Modify the approach. Decompression is one tool in the toolkit, not the entire toolkit.
Who This Actually Works For
Patients with contained disc herniations — where the outer annulus layer is still intact but bulging — tend to respond best. The negative pressure generated during decompression can actually pull the bulge back toward the center. Studies show response rates in the 70 to 90 percent range for this subgroup. Sequestrated herniations, where a fragment has broken off entirely into the spinal canal, are a different story. The freed fragment isn't held in place by an intact annulus anymore, so negative pressure inside the disc won't necessarily draw it back. These cases sometimes benefit from decompression for symptom relief, but you shouldn't expect the fragment to resorb through traction alone. Surgical evaluation is often warranted if neurological deficits are present. Stenosis with spondylolisthesis is another scenario where decompression can backfire. Pulling on an already unstable segment can increase the slippage. In those cases, stabilization-focused treatment is usually the safer route.
Common Pitfalls That Waste Time and Money
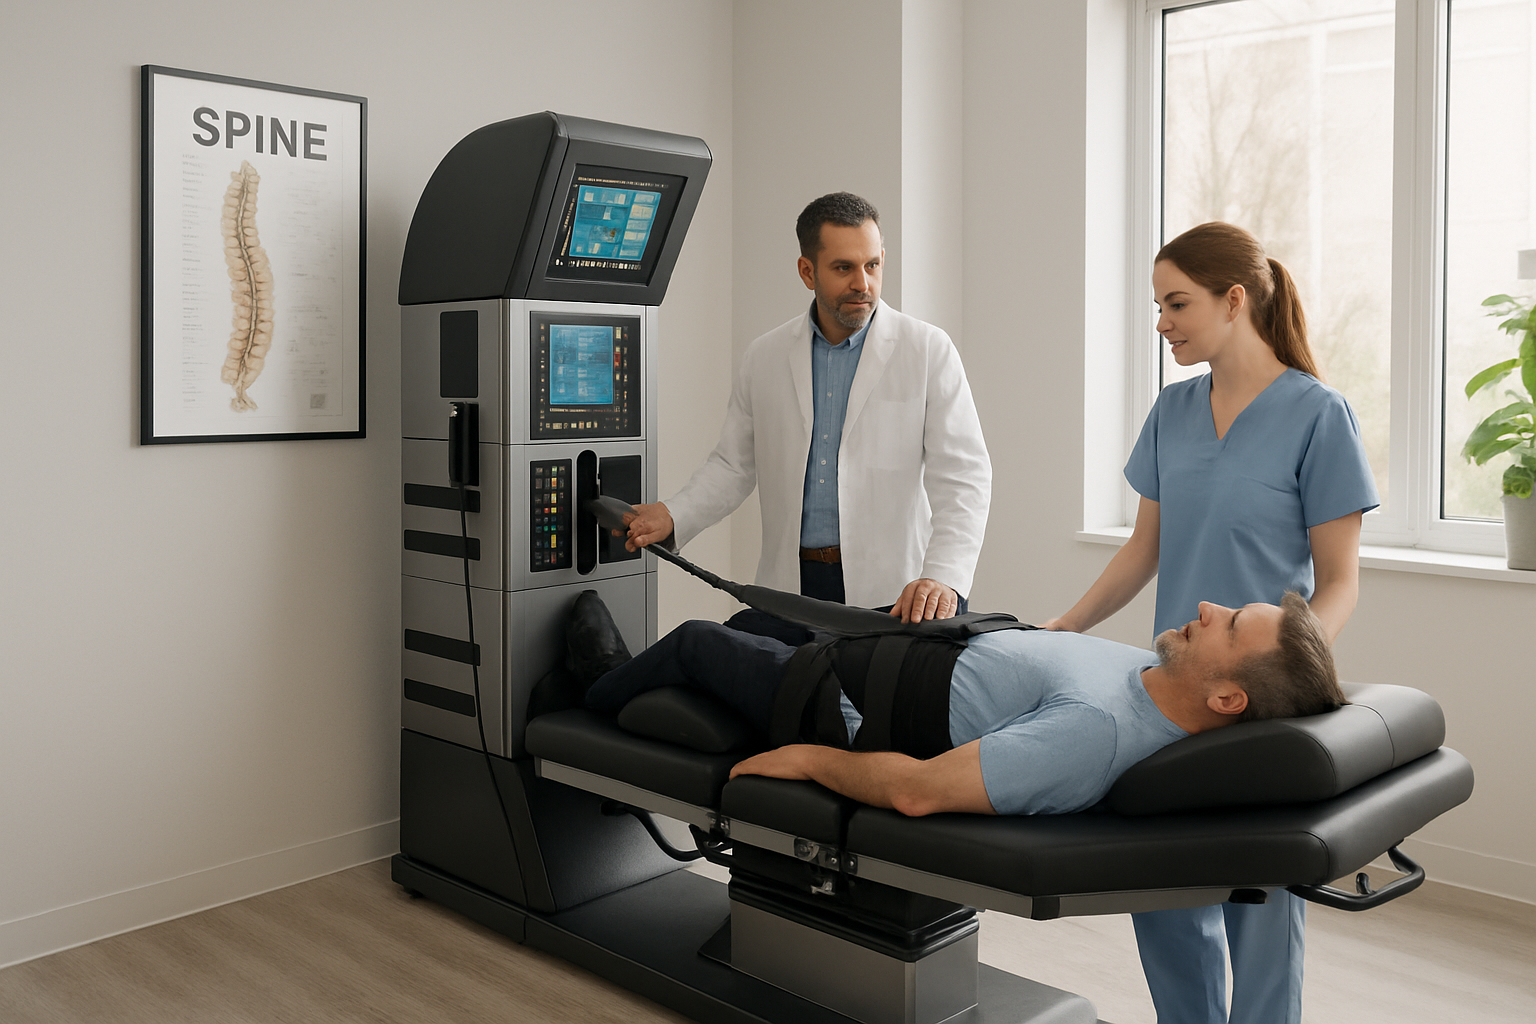
One of the biggest issues is underpowered equipment. Consumer-grade home traction devices typically max out at 30 to 40 pounds of force regardless of patient weight. A 200-pound patient needs significantly more than 40 pounds of distraction force to achieve meaningful intradiscal pressure changes. Commercial clinic machines can generate forces proportional to body weight precisely because they need to, not because they're fancy. Another problem is treating without a confirmed diagnosis. Back pain with radiating symptoms gets labeled as a herniated disc all the time when it might be facet joint irritation, sacroiliac dysfunction, or piriformis syndrome. Decompression won't help any of those and might make them worse by irritating already-inflamed structures. Imaging confirmation, especially an MRI, is worth the expense if surgical intervention is on the table. A third issue is expecting decompression to be a standalone cure. Most patients who get lasting relief combine it with core stabilization work, posture correction, and activity modification. The decompression creates the window of opportunity by reducing pressure on the nerve. What keeps the improvement going is addressing the biomechanical reasons the herniation happened in the first place. Ignoring that second part is how people relapse.
At-Home Options and Their Realistic Limitations
Inversion tables are the most common home alternative, and they're not the same thing as clinical decompression. Inversion uses gravity to create traction, which works to some degree, but the force is fixed by your body weight and the angle of inversion. You can't fine-tune the pull the way a motorized table lets you. Most people operate at 60 to 70 degrees of inversion, which generates roughly 30 to 40 percent of body weight in traction force at the lumbar spine. Decompression belts and portable devices that strap around the waist and use manual leverage are even less effective. The force vectors are poorly controlled and the magnitude is too low to create meaningful intradiscal changes. They might provide temporary symptom relief through mild stretching, but they're not equivalent to clinical-grade treatment. If you're considering a home setup, be honest about what you're getting. A used inversion table from a resale site for a couple hundred dollars can be reasonable for mild cases or maintenance after clinical treatment. Don't expect it to replace a full course of supervised decompression therapy for an acute herniation.
Red Flags That Mean You Should Stop and Reassess
Increased radiating pain during or after a session is a warning sign. Some mild discomfort from tissue stretching is normal. Sharp shooting pain down the leg that worsens after treatment suggests the nerve is being irritated further rather than relieved. That sometimes means the force is too high, the angle is off, or the diagnosis needs revisiting. New weakness in the legs, bowel or bladder dysfunction, or saddle anesthesia are emergency red flags that require immediate medical attention regardless of where you are in a treatment plan. Cauda equina syndrome is rare but serious, and no amount of decompression therapy will fix it. Time is the critical factor there. If symptoms plateau after four to six sessions with no improvement at all, it's worth re-evaluating the treatment plan. Continuing the same approach indefinitely without adjustment isn't evidence-based practice. Switching modalities or seeking a second opinion at that point is the reasonable move.