The Two Bone-Building Pathways
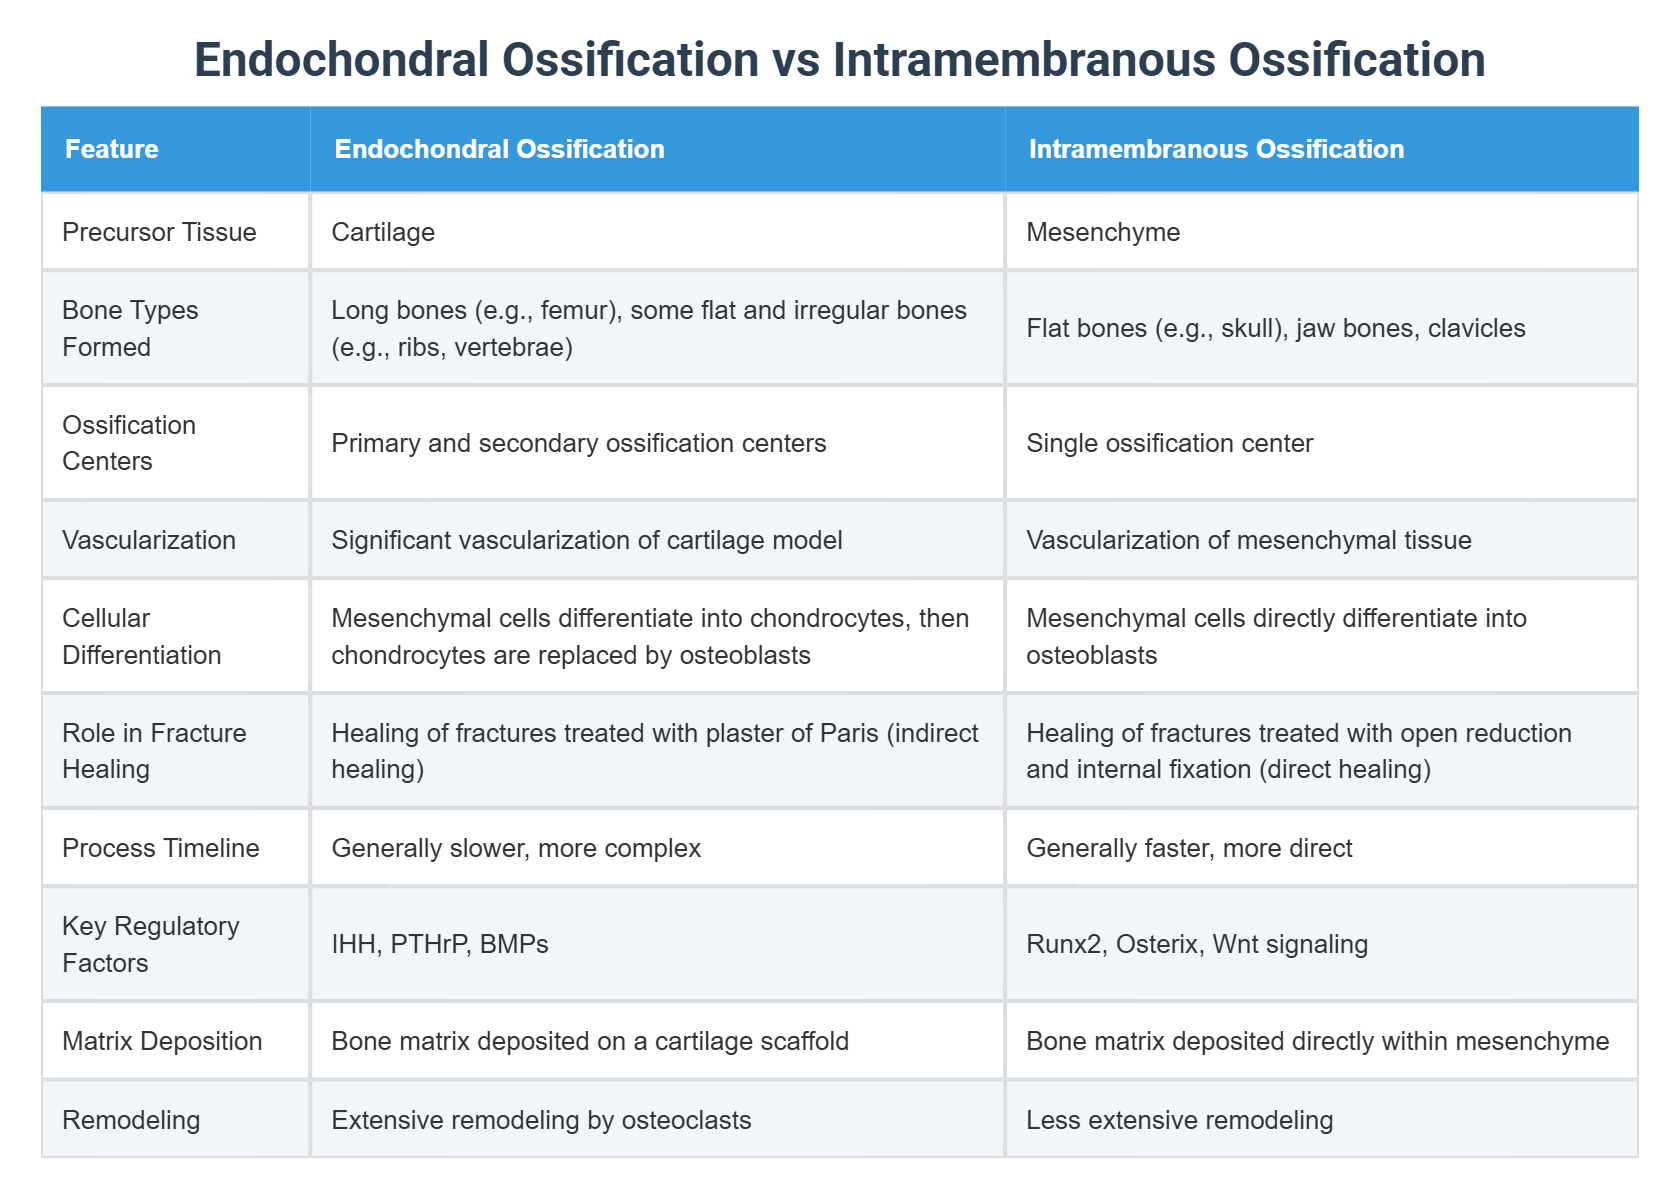
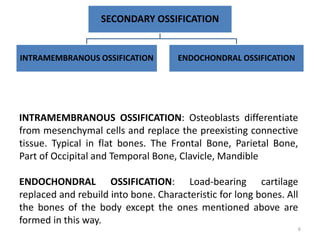
Bone formation happens in two fundamentally different ways, and mixing them up will cost you points on every histology exam and mess up your radiology reads. The distinction matters more than people let on. One path builds flat bones. The other builds everything else. That's the short version. The long version involves mesenchymal condensations, cartilage templates, and vascular invasion timelines that determine whether you end up with a skull plate or a femur shaft. Intramembranous ossification is direct bone formation. Mesenchymal stem cells cluster together, differentiate straight into osteoblasts, and start laying down osteoid without any intermediate cartilage stage. The osteoid mineralizes, blood vessels grow into the space, and osteoclasts carve out the trabecular network. This is how the skull vault, clavicles, and mandible form. You see it most clearly in fetal development around the eighth week, though it continues throughout life for fracture repair when you need quick stabilization. Endochondral ossification is the indirect pathway. A hyaline cartilage model forms first, shaped roughly like the bone it will become. Chondrocytes in the center hypertrophy, the matrix calcifies, and the cells die. Blood vessels then invade through the primary ossification center, bringing in osteoprogenitor cells that replace the cartilage scaffold with spongy bone. Secondary ossification centers appear later at the epiphyses. Almost all long bones, the vertebral column, ribs, and the base of the skull go through this process. It's slower but produces structurally superior bone architecture.
The key difference isn't just which bones are involved. It's about the mechanism. Intramembranous is fast and direct. Endochondral is methodical and complex. The cartilage template in endochondral ossification acts as a temporary scaffold that guides bone shape before being resorbed. Without that template, you don't get proper long bone geometry. The growth plate itself is remnant endochondral tissue that persists through adolescence. I spent three months tracking delayed union fractures in tibial shafts, and the ossification pathway distinction came up more often than expected. A 34-year-old patient with a comminuted fracture that wasn't bridging past nine weeks had imaging that looked ambiguous. The callus was there, but it wasn't mineralizing properly. Standard protocol would push for surgical intervention at that point. Instead, I reviewed the original X-rays and noticed subtle signs that the fracture had actually disrupted the endochondral pathway rather than impairing the intramembranous callus response. The periosteal reaction was active, meaning intramembranous repair was happening. The problem was localized to the medullary canal where endochondral replacement should have been taking over. We delayed surgery another three weeks, started low-intensity pulsed ultrasound, and the bridging finally occurred. Surgery would have been unnecessary. Most clinicians miss this nuance because they're taught to treat both pathways as a single healing process. Here's something most textbooks gloss over. The boundary between these two pathways isn't always clean in clinical practice. When you do an intramedullary nail fixation, you're essentially forcing the body to heal via intramembranous pathways around the implant while the endochondral process continues internally. That's why callus formation looks asymmetric on post-op X-rays. The implant creates a zone where blood supply is altered, and osteoblasts bypass the cartilage intermediate entirely in the periosteal region. This is actually advantageous for stiffness but can lead to delayed remodeling if the endochondral component stalls.
Another counter-intuitive point: intramembranous ossification isn't limited to flat bones in adults. When you fix a fracture with a rigid plate and absolute stability, the healing occurs purely through intramembranous bone formation across the fracture gap. No callus forms. Direct haversian reconstruction crosses the line. This is called primary bone healing, and it's technically intramembranous ossification happening at a fracture site where endochondral would normally dominate. Surgeons use this principle intentionally with compression plating. The trade-off is that it requires perfect anatomical reduction and stable fixation. Miss either one and you get nonunion. The growth plate deserves special attention here. It's exclusively endochondral tissue. Every inch of long bone length comes from chondrocyte proliferation, hypertrophy, and matrix replacement happening in discrete zones. The proliferative zone, the hypertrophic zone, the calcified zone, and the ossification front. Damage to any of these zones during childhood creates asymmetric growth. That's why pediatric proximal tibial fractures near the physis are taken so seriously. Even a millimeter of premature physeal closure can create a leg length discrepancy that compounds over years. Both pathways share the same cellular players but deploy them differently. Osteoblasts, osteoclasts, osteocytes, and mesenchymal stem cells are present in both. The difference is in the sequence and the intermediate structures. Intramembranous skips the cartilage step entirely. Endochondral depends on it. Vascular invasion timing is another critical variable. In intramembranous ossification, vessels penetrate the mesenchymal aggregate as osteoblasts begin secreting osteoid. In endochondral ossification, vascular invasion is triggered specifically by chondrocyte hypertrophy and matrix calcification, which creates chemotactic signals like VEGF that attract blood vessels from the perichondrium.
Get the Full Details

Pathological conditions expose the fragility of each pathway. Osteogenesis imperfecta primarily affects intramembranous-derived bones because type I collagen is the structural backbone of both woven and lamellar bone matrices. But it affects endochondral bone too, just differently. The cartilage template forms normally. The problem appears when the mineralized cartilage should be replaced by bone. The osteoid that replaces it is defective. So both pathways produce bone, but the output quality differs depending on which genetic defect is present. Rickets and vitamin D deficiency demonstrate the endochondral pathway's vulnerability. The growth plate becomes disorganized because chondrocytes can't properly calcify their matrix. The hypertrophic zone widens abnormally, creating the classic rachitic rosary at the costochondral junctions. Intramembranous bone formation is less affected because it doesn't rely on the same calcification cascade, which is why skull bones in rickets show different deformities, like craniotabes, rather than growth plate widening. If you're studying this for an exam, focus on the timelines. Intramembranous ossification begins around week 8 of gestation. Endochondral ossification starts slightly earlier, around week 6 to 8, depending on the bone. The first endochondral bone to form is the clavicle. The last to complete is the distal femoral epiphysis, which doesn't finish until around age 18 to 20. That late completion is clinically relevant for athletes. Stress fractures in the distal femur during adolescence can disrupt the remaining endochondral activity.
The clinical imaging distinction is straightforward once you know what to look for. Intramembranous bone appears as dense, trabecular patterns directly within soft tissue on X-ray. Endochondral bone shows a transitional zone where calcified cartilage shadows gradually give way to trabecular bone. On CT, the cartilage model has a characteristic density between soft tissue and bone, roughly 50 to 150 Hounsfield units, which helps identify the endochondral pathway in developmental imaging. MRI is even better for visualizing the cartilage intermediate before it calcifies. One practical consideration I haven't seen emphasized enough: bisphosphonates affect both pathways but through different mechanisms. They inhibit osteoclast-mediated resorption, which is critical in the endochondral pathway where osteoclasts remove calcified cartilage to allow bone replacement. In intramembranous ossification, osteoclasts are involved in remodeling the initial woven bone lattice into compact bone. So bisphosphonate treatment in growing children can theoretically slow both ossification types, but the endochondral pathway is more immediately impacted because the resorption step is non-negotiable for cartilage-to-bone transition. This is why bisphosphonates are used cautiously in pediatric bone disorders despite their utility in osteogenesis imperfecta. Understanding which pathway is operating in any given situation lets you predict healing patterns, interpret imaging correctly, and recognize when something is off. The two processes are not interchangeable. They serve different structural purposes and respond differently to trauma, disease, and intervention. That's the core of it.