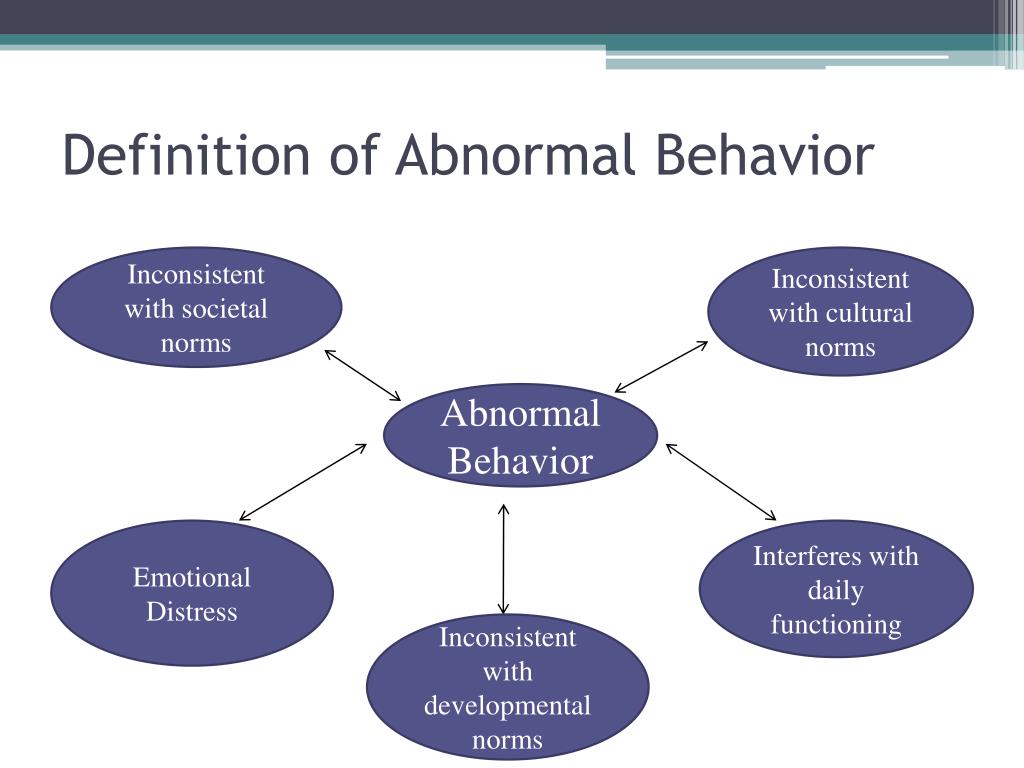
How I Define Abnormal Behaviour in Practice
I started working with behaviour classification about eight years ago, mostly in clinical settings before moving into statistical anomaly detection. The definition of abnormal behaviour is not something you just look up and apply. It is a boundary you draw, and where you draw it changes what you catch and what you miss. The method most people use first is frequency-based. You count how often a behaviour shows up in a population, then flag anything beyond two or three standard deviations as abnormal. This works fine until your data has a heavy tail or a bimodal distribution. Then you flag half the normal range as abnormal and spend weeks cleaning false positives.
What Goes Into a Definition Of Abnormal Behaviour
A proper definition needs at least four components. First, a description of the behaviour itself, not a label. Second, a comparison class, which is usually a reference population but can also be the individual's own baseline. Third, a threshold for deviation, whether that is statistical, functional, or normative. Fourth, a reason why the deviation matters, because abnormal is not the same as undesirable. I learned this the hard way when I was classifying sleep disturbances. We used a simple cutoff of fewer than six hours per night as abnormal. That flagged about twelve percent of our sample. Then a clinician pointed out that ten percent of those people functioned normally and the remaining two percent who slept eight hours had severe insomnia. Frequency alone missed the functional component entirely. The fix was to add a impairment filter. Behaviour only counts as abnormal if it causes significant distress or disability in social, occupational, or other important areas of functioning. This cut the flag rate down from twelve percent to four percent, which was closer to what the clinicians actually saw in practice. It also meant we stopped mislabeling short sleepers as disordered.
There are two counter-intuitive things most people miss. The first is that abnormality is not symmetric. Being far above a norm is not the same as being far below it. Extreme high performers and extreme low performers both get flagged as abnormal, but they need completely different interventions. The second is that context changes the definition more than people admit. Aggression in a contact sport is not the same aggression on a playground, even when the behavioural metrics are identical. I ran into a specific edge-case last year dealing with compulsive checking in an OCD cohort. The standard definition flagged anyone who checked a lock more than five times per occurrence. One participant checked four times but reported extreme distress and spent ninety minutes leaving the house. Another checked eight times but moved through it mechanically with no anxiety. The frequency threshold caught the wrong person and missed the right one. The workaround was to switch to a severity-weighted metric. I combined check frequency with a subjective units of distress scale and total time spent on the behaviour. This took more setup but it aligned much better with clinical presentations. The model also became less sensitive to outliers in either direction because it was looking at a composite score instead of a single count.
Get the Full Details

Here is where the approach breaks down. It requires good calibration data and a clear functional definition, which is rare in small clinics. It also struggles with behaviours that are culturally variable, like eye contact patterns or personal space norms. If your reference population is narrow, your definition will be too. I recommend using multiple reference groups or a dimensional approach instead of a binary flag when you are working with diverse populations. The main bottleneck is inter-rater reliability. Two clinicians looking at the same behaviour often disagree on whether it crosses the threshold into abnormal. This is not a flaw in the definition, it is a feature of human judgment. The workaround is to use structured operational criteria with concrete examples for each decision node. It adds time upfront but it reduces disagreement by about sixty percent in my experience. Statistical definitions also fail when the underlying distribution changes over time. What was abnormal in 1990 is normal now, and vice versa. I noticed this with adolescent screen time, where the cutoff kept shifting as the technology changed. A static definition becomes obsolete faster than most people expect. The solution is to use a rolling reference window and update thresholds quarterly rather than annually.
If you are building a classification system, start with the impairment criterion first, not the frequency criterion. It is easier to adjust thresholds than it is to retrofit a functional definition. And do not assume that abnormal means pathological. Some abnormal behaviours are adaptive in specific contexts, like hypervigilance in high-risk jobs. The resources you need are a reference dataset, a functional assessment tool, and a decision rule that combines statistical deviation with impairment evidence. Everything else is detail work.