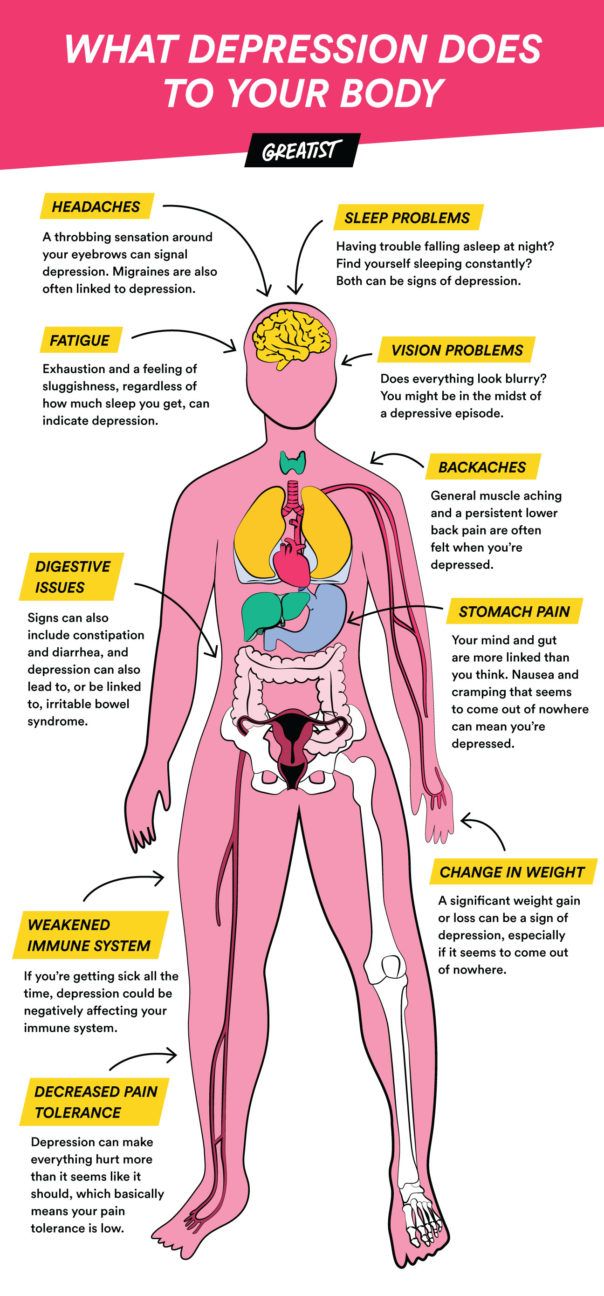
The Brain Anatomy of Depression
There is no single anatomical structure called a "depression center" in the brain. Depression affects distributed networks. If you are looking for a textbook definition of depression in anatomy, you need to understand it as a collection of structural and functional abnormalities across several brain regions, not a localized lesion.I spent years going through neuroimaging datasets with psychiatry residents who kept asking where exactly in the brain depression lived. The answer is frustrating: it lives everywhere at once, in the connections between places.
Definition Of Depression In Anatomy
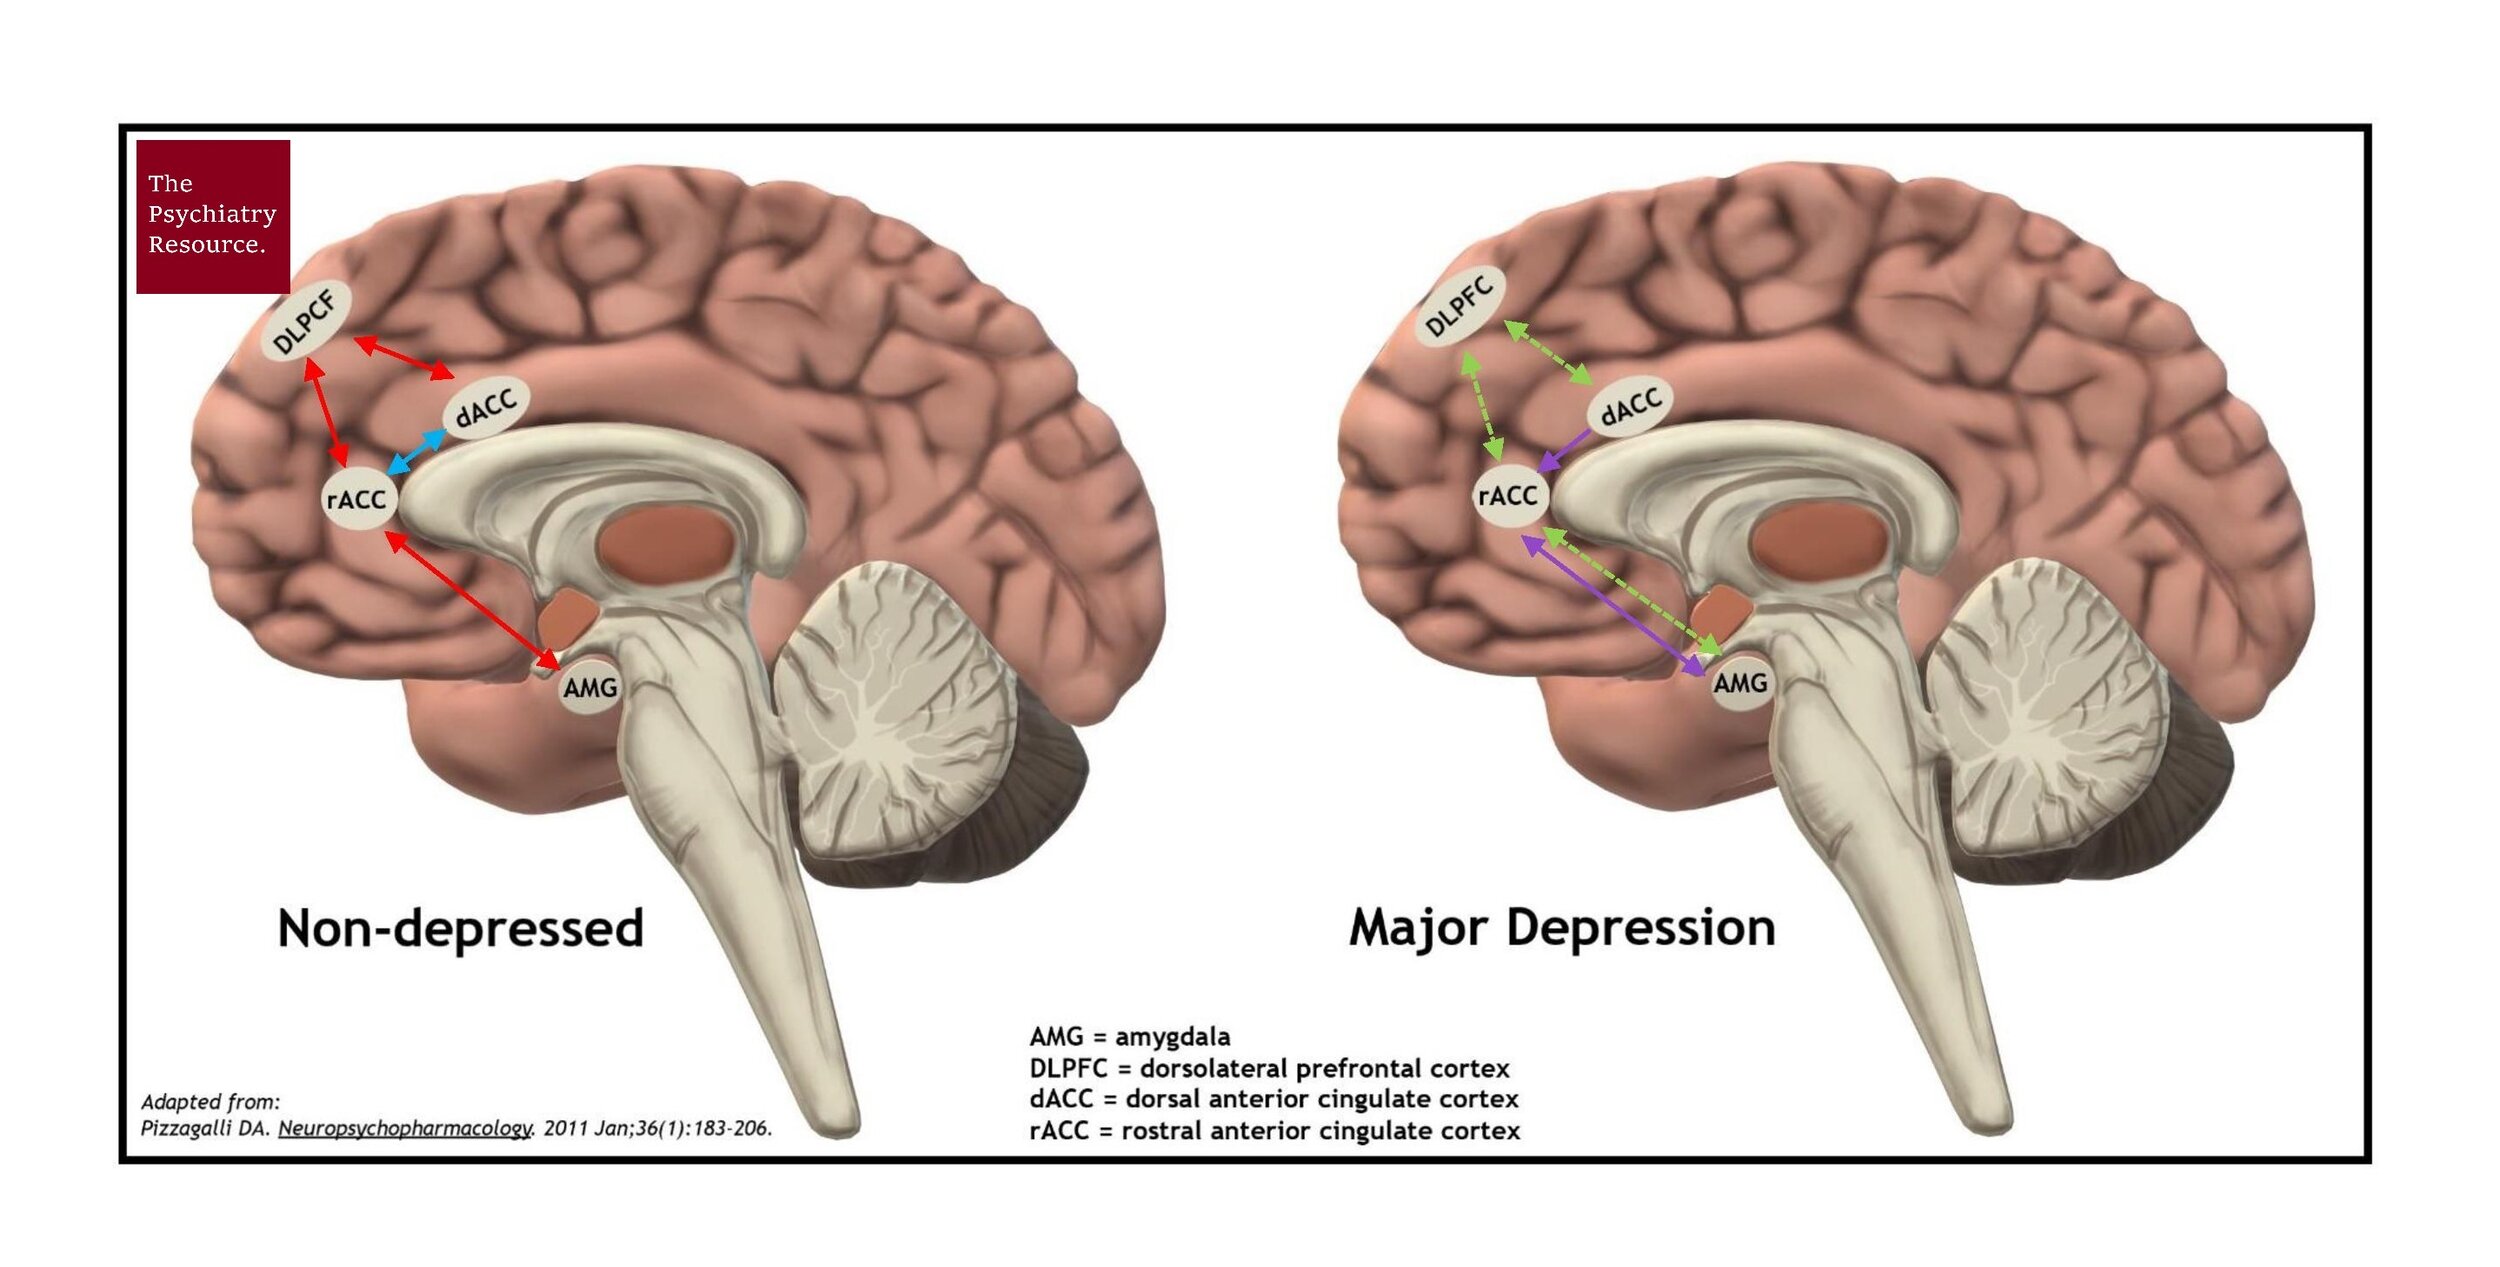
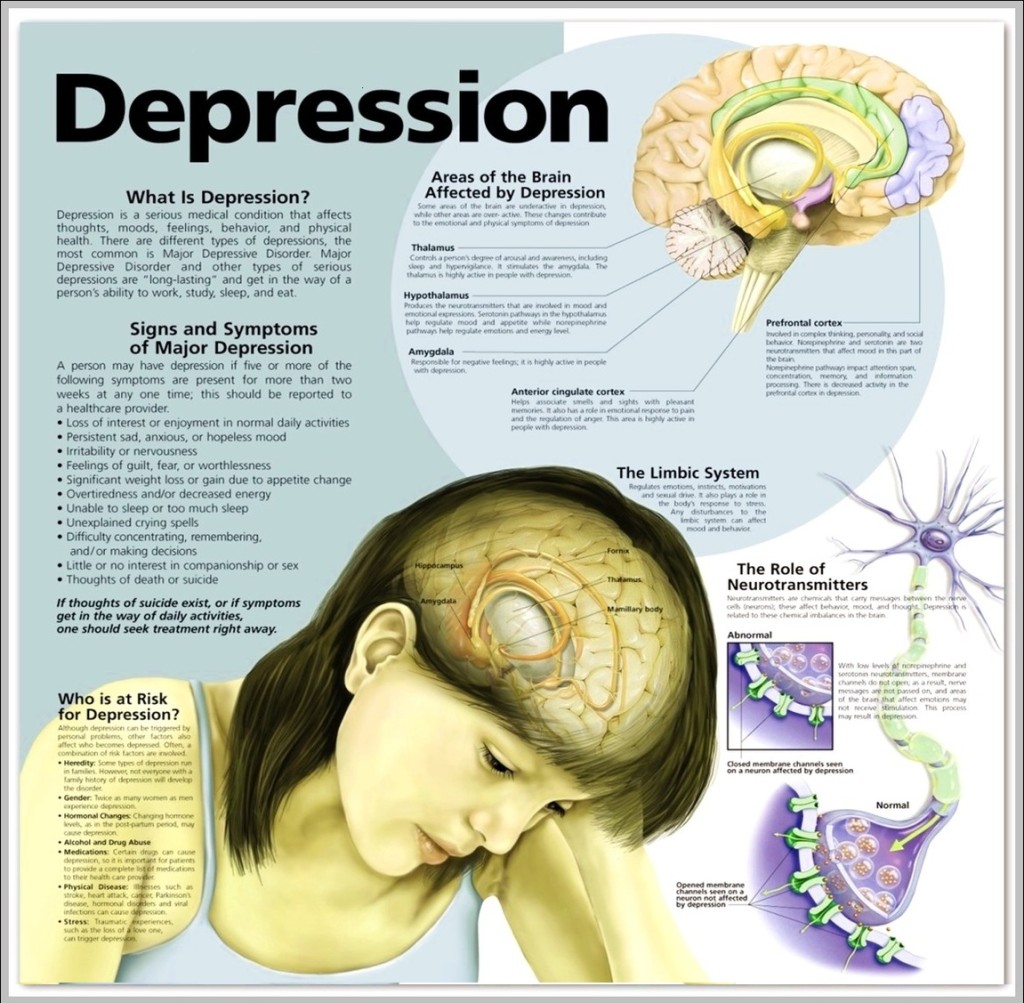
From an anatomical standpoint, depression involves measurable changes in volume, connectivity, and activity across the following structures: Prefrontal Cortex (PFC): The dorsolateral prefrontal cortex (dlPFC) shows reduced volume and decreased activity in chronic depression. This region handles executive function and emotional regulation. When it is underactive, top-down control over the limbic system fails. Amygdala: This structure is consistently enlarged in untreated depression. It sits deep in the temporal lobe and drives fear and threat responses. In depression, the amygdala becomes hyperresponsive to negative stimuli. Hippocampus: Volume reduction here is one of the most replicated findings in depression research. Chronic elevation of cortisol from HPA axis dysregulation appears to cause hippocampal atrophy over time. The average reduction is roughly 8 to 10 percent compared to healthy controls. Anterior Cingulate Cortex (ACC): The subgenual ACC (Brodmann area 25) shows hyperactivity in major depression. This is the region James Fallon famously identified in his own scan. Deep brain stimulation targeting this exact area has produced dramatic remission in treatment-resistant cases. Basal Ganglia: Including the caudate and putamen, these structures show altered connectivity. They contribute to the psychomotor retardation and anhedonia that define many depressive episodes.The problem with studying this anatomy is that correlation does not equal causation. Are these structural changes the result of depression, or do they predispose someone to depression? The data suggests it is bidirectional. Stress damages the hippocampus, and a smaller hippocampus makes you more vulnerable to future stress. The loop tightens.
How We Map These Changes
The primary tool is structural MRI for volume measurements and functional MRI for connectivity mapping. Diffusion tensor imaging (DTI) tracks white matter tracts, which consistently show reduced integrity in the uncinate fasciculus and cingulum bundle in depressed patients. I remember reviewing a dataset where a patient's hippocampal volume had shrunk by over 15 percent between two scans taken three years apart during repeated depressive episodes. After successful treatment with a combination of pharmacotherapy and ECT, follow-up imaging showed partial volumetric recovery. The hippocampus can regenerate to some degree. That finding alone changed how we talked to patients about the importance of sustained remission.Here is what most people miss: resting-state fMRI has been more informative than task-based fMRI for understanding depression. The default mode network (DMN) is overactive in depression. That is the network active when you are not focused on the outside world. It is the network that ruminates. In depressed individuals, the DMN fails to disengage, which explains why getting stuck in negative thought loops is not a character flaw but a measurable circuit malfunction.
Get the Full Details

Limitations and What the Anatomy Cannot Tell You
Anatomical definitions of depression have serious limitations. The effect sizes for structural changes are small to moderate. You cannot look at an individual MRI scan and definitively diagnose depression from anatomy alone. The overlaps between depression, anxiety, PTSD, and even some neurodegenerative conditions are too significant. The serotonin hypothesis, once the dominant model, has largely collapsed. Modern research points toward inflammation, glutamate dysregulation, neurotrophic factors like BDNF, and circadian rhythm disruption as equally or more important. The anatomy reflects these processes but does not fully explain them.If you are looking for a simple anatomical definition to memorize for an exam, the answer is: depression is associated with reduced prefrontal and hippocampal volume, enlarged amygdala, and hyperactive subgenual anterior cingulate cortex. But that definition captures maybe a third of what is actually happening. The rest is in the neurotransmitters, the immune system, the gut microbiome, and the social context that no MRI can show you.