What Gene Variation Actually Means in Practice
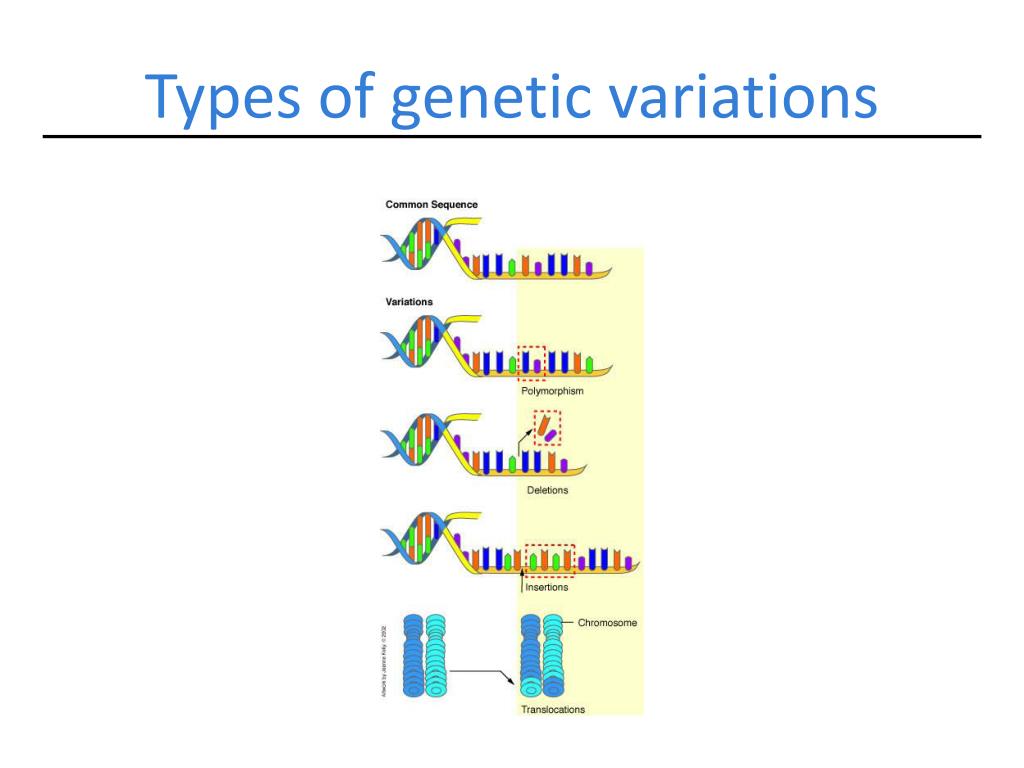
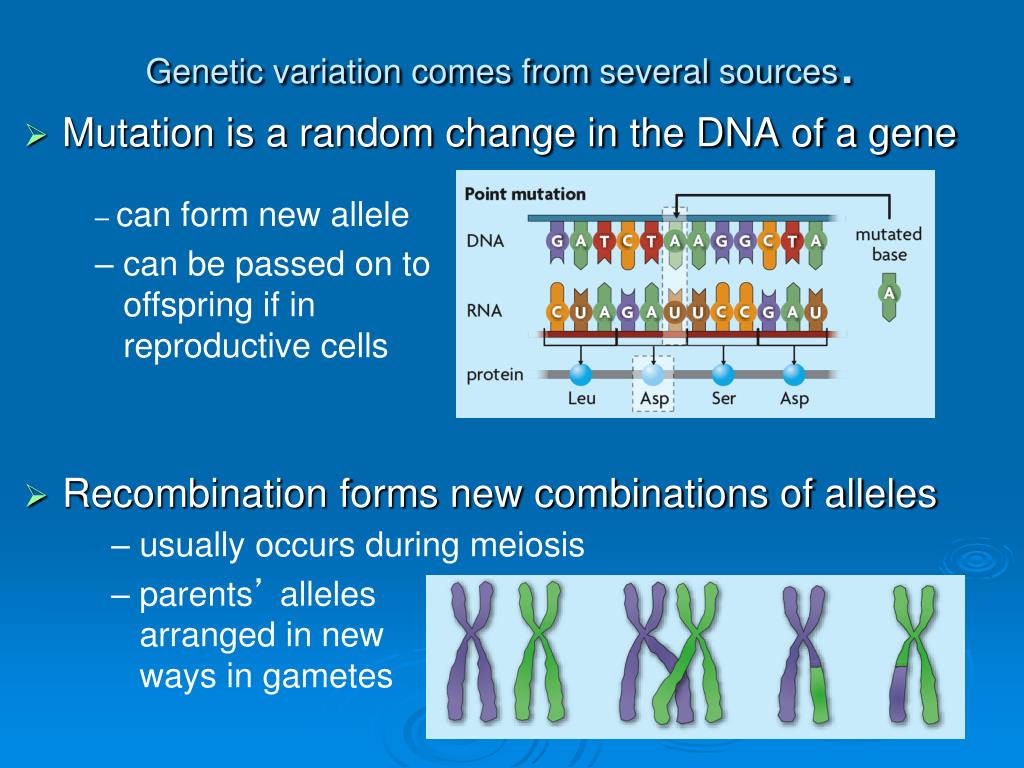
When people ask about the Definition Of Gene Variation, they usually want a textbook answer. The textbook says it's any difference in DNA sequence among individuals of a species. That's technically correct and completely useless if you've ever opened a VCF file and watched your pipeline crash because a region of the genome refuses to map cleanly. Gene variation is not just differences. It's SNPs, indels, copy number variations, structural rearrangements, and repeat expansions, each with its own set of artifacts waiting to trip you up. Start with what you're actually trying to detect. If you're calling germline variants from whole-exome sequencing, you need GATK's HaplotypeCaller in GVCF mode, then joint genotyping across your cohort. I learned this the hard way two years ago when a client sent me five hundred single-sample VCFs and expected me to find rare recessive variants. Single-sample calling missed half the heterozygotes in low-coverage regions because the algorithm couldn't distinguish real variants from sequencing errors without population-level context. Joint calling collapsed the runtime from three days to about six hours on a modest cluster and recovered those missing genotypes. If you're working with somatic variants from tumor samples, the rules change entirely. You need matched normal tissue, Mutect2 or a similar somatic caller, and you have to worry about contamination estimates and panel of normals filtering. I've seen people skip the PON step and end up with thousands of false positives in repetitive regions. It sounds obvious now, but in the middle of a rush project it's easy to skip what feels like an extra step.
Common Pitfalls Nobody Warns You About
Reference genome bias is the thing that gets people quietly. The standard GRCh38 reference is a mosaic from a few donors, and if your sample carries alleles that don't exist in that reference, they'll either fail to align or show up as false variants. This matters most in highly polymorphic regions like the MHC locus, where variant density is so high that even good callers struggle. I spent two weeks debugging what looked like an inflated variant count in HLA genes before realizing the issue was reference mismatch, not a bad sample. Switching to a decoy-aware alignment and using a graph-based reference like the one from the pangenome project cleaned it up immediately. Another thing that surprises people is that variant quality scales non-linearly with coverage. Going from 30x to 60x doesn't give you twice the confidence. It gives you diminishing returns for common variants but significant improvements for somatic variants with low allele fractions. If you're doing liquid biopsy or minimal residual disease work, depth matters way more than you'd expect from a standard clinical sequencing workflow. Coverage uniformity is the silent killer in exome data. Even with modern capture kits, you'll have regions that consistently fall below 20x. These are often GC-rich or contain long homopolymer runs. Calls in those regions are unreliable, and most pipelines don't flag them explicitly. I always run a breadth-of-coverage metric after alignment and mask anything below a threshold before variant calling. It costs almost nothing and prevents a lot of downstream noise.
Structural Variants and the Hard Cases
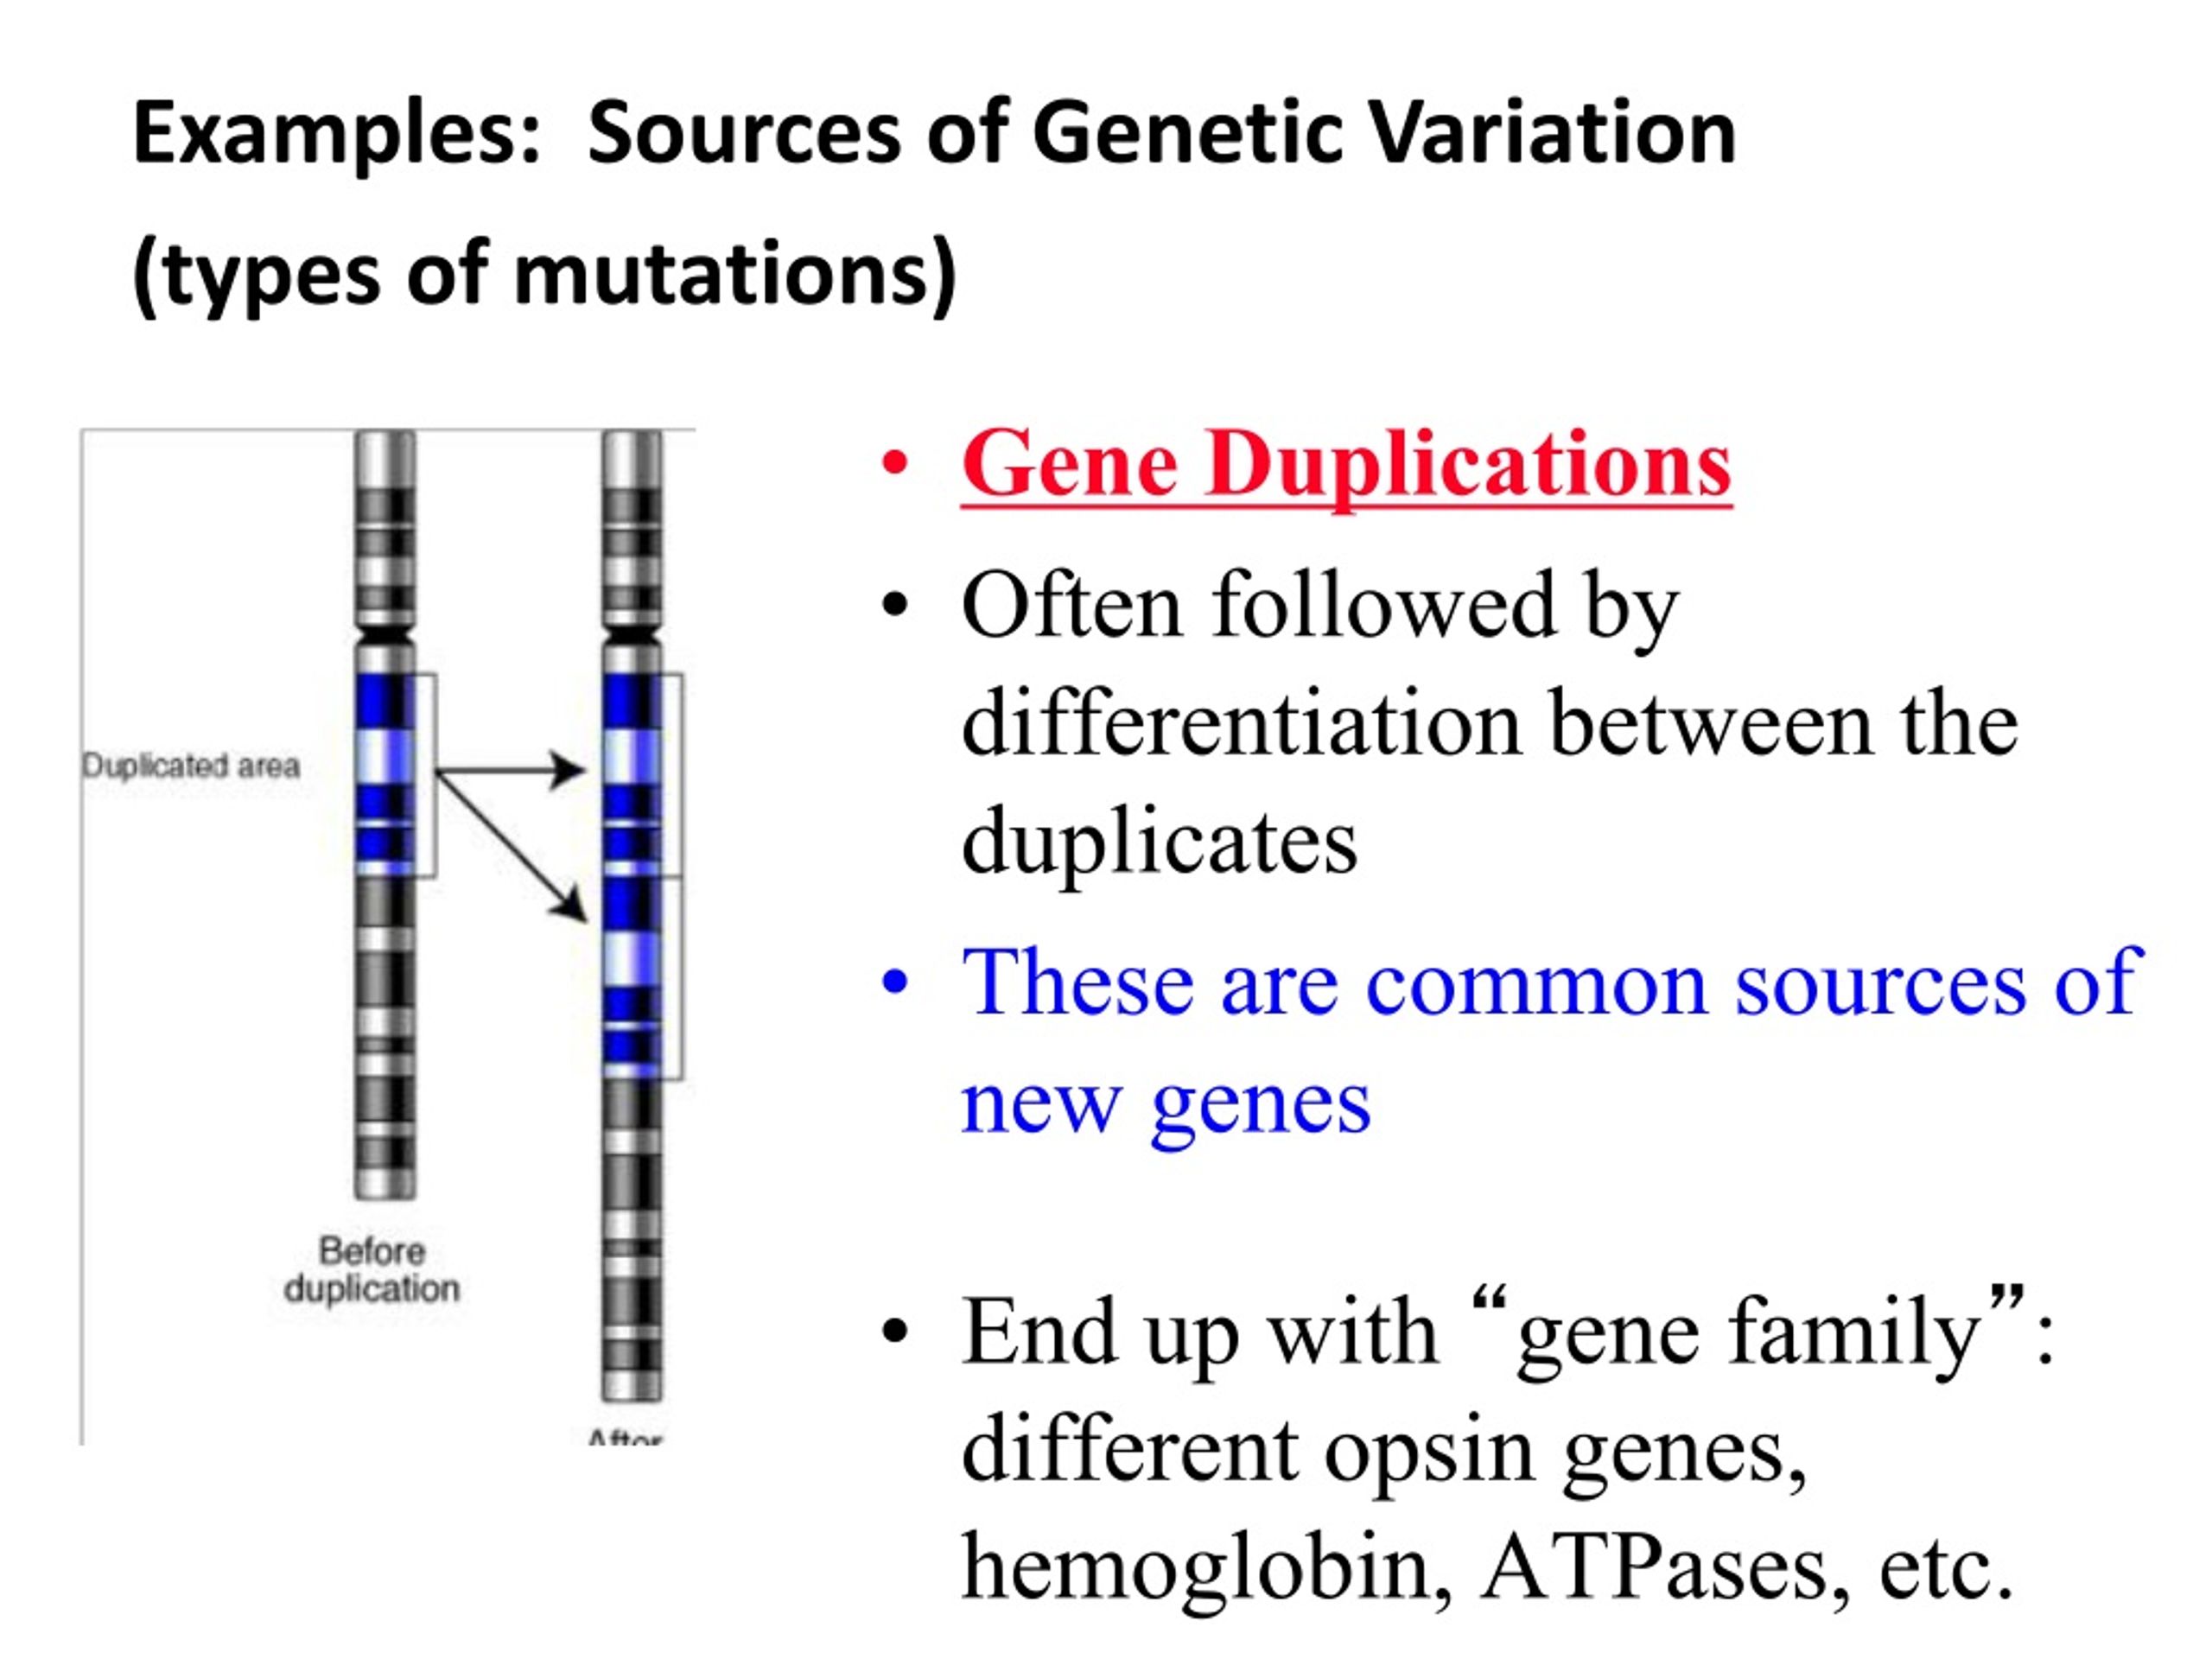
SNPs and small indels are relatively solved problems. Structural variants are where most pipelines break. Copy number variations, inversions, translocations, and mobile element insertions require different algorithms entirely. Tools like Manta, Delly, or Sniffles for long-read data each have tradeoffs. Short-read SV callers tend to miss events smaller than a few hundred bases or those in repetitive sequences. Long-read technologies like Oxford Nanopore and PacBio HiFi help but introduce their own error profiles that need specialized filtering. I worked on a project last year involving hereditary cancer screening where we detected a pathogenic Alu insertion in BRCA1 that no short-read pipeline caught. Standard read-depth and split-read approaches couldn't resolve the insertion because the Alu element created ambiguous mappings. Only when we added a long-read validation step did the variant become visible. This isn't a edge case I mention often. Clinically relevant structural variants are systematically undercalled in standard workflows, and most diagnostic labs still rely on Sanger sequencing or targeted long-range PCR to catch them.
Get the Full Details
Annotation and Interpretation Are Where Things Get Messy
Calling variants is only the first step. You then have to annotate them, which means mapping each variant to genes, predicting functional impact, checking population frequency databases, and cross-referencing with clinical databases like ClinVar and gnomAD. Each of these steps introduces its own failures. Annotation pipelines often disagree on whether a variant is pathogenic. A variant classified as likely pathogenic by one tool might be benign in another because they use different training data or algorithms. The ACMG guidelines help standardize interpretation, but they leave room for human judgment, and that judgment varies between labs. I've seen the same variant classified as VUS in one report and pathogenic in another from a different lab. This isn't a bug in the system. It's a feature of how complex variant interpretation is, and it's something clinicians need to understand before acting on a report.
Practical Workflow Summary
For germline variant discovery from short-read WES or WGS data, here's what actually works without burning a week on debugging: Align with BWA-MEM2 using a decoy-aware reference genome. Mark duplicates with Picard. Base recalibration is worth doing if you have known variant sites available, though the gain is modest for well-controlled Illumina runs. Run HaplotypeCaller in GVCF mode per sample, then joint genotyping across the cohort. Filter with VQSR if you have enough variants to train the model, otherwise use hard filters based on QD, FS, MQ, and DP. Annotate with VEP or SnpEff. Cross-check against gnomAD for allele frequencies and ClinVar for clinical significance. This pipeline typically takes about 4 hours per WGS sample on a standard 32-core machine for alignment and variant calling, plus another hour for annotation. Exome data runs faster, roughly 30 minutes per sample, because the capture reduces the effective genome size substantially. Raw storage per WGS sample is around 100GB of aligned reads and a few gigabytes of VCF data, which adds up fast at scale.
The biggest bottleneck is almost always interpretation, not computation. A single WGS can produce 4 to 5 million variants. Even after aggressive filtering for rarity and predicted impact, you're left with hundreds of candidates that require manual review. Automation helps, but someone needs to look at each one and decide whether it's worth pursuing. That's the part that doesn't scale well, and it's the part that will matter more than any algorithmic improvement in the near future.