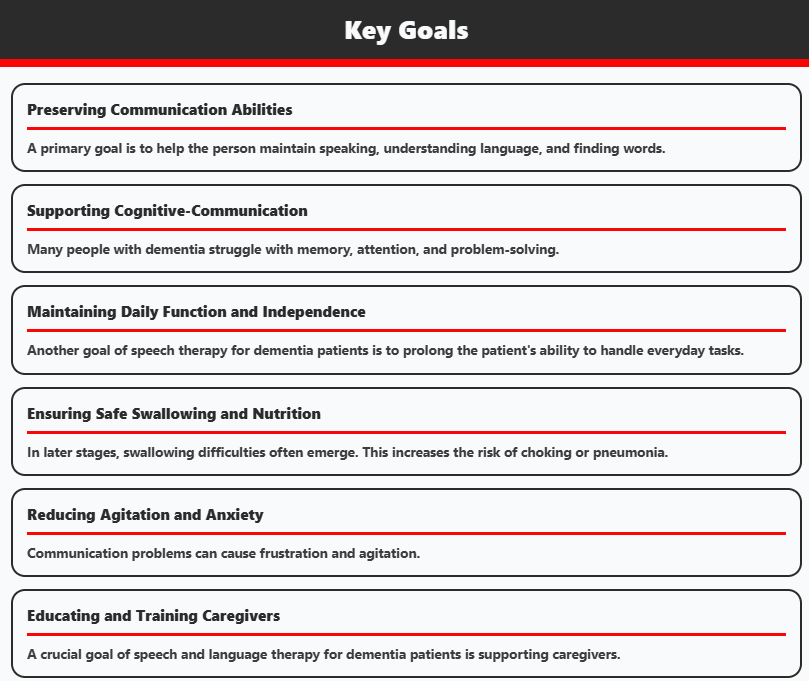
What You Actually Do When Setting Speech Therapy Goals for Dementia
Dementia speech therapy goals look completely different from what you'd write for a post-stroke aphasia patient or a pediatric speech sound disorder. The framework is built around preservation and compensation rather than restoration. Most clinicians I know who transition from neurogenic aphasia work into dementia end up frustrated within the first six months because their goal-setting habits don't translate. The patient isn't going to relearn verb conjugation. The goal isn't rehabilitation in the traditional sense—it's maintaining whatever functional communication capacity exists and building a support structure around what's left. Dementia Speech Therapy Goals should be written as measurable, observable behaviors tied to daily life, not as clinical abstractions. "Patient will use a communication board to request three items during meals" is a goal. "Patient will improve naming abilities" is not a goal, it's a wish that will sit on your paperwork forever. I've seen countless IEP and treatment plan reviews where the goals were so vague they couldn't be measured even in principle. That's not helpful to anyone, least of all the family members trying to figure out if therapy is actually doing anything.
Measurable Dementia Speech Therapy Goals You Can Actually Track
Let me give you the framework I use. It's borrowed from cognitive-linguistic approaches but stripped down to what actually works in real-world settings. The four domains are comprehension, expression, pragmatics, and compensatory strategy use. Within each domain, you write goals using this template: observable behavior, condition, criteria, and timeframe. That last part is where most people fail. "Within 8 weeks, under low-distraction conditions, patient will identify the purpose of five common household objects with 80% accuracy across three consecutive sessions." Every single component is there. For comprehension, you're usually targeting following one-step and two-step commands in meaningful contexts. This sounds simple until you try to measure it across varying levels of background noise and competing visual stimuli. A realistic goal might look like: "Patient will correctly follow one-step commands involving common daily routines (e.g., 'give me the cup,' 'pick up the napkin') in 4 out of 5 trials with verbal cueing and in 3 out of 5 trials without cueing." The no-cueing target is important because that's what happens at the dinner table, not the therapy room. Expression goals in dementia are tricky. Word-finding difficulties are universal at some stage, but writing a goal around "improved word retrieval" is meaningless. Instead, focus on strategies. "Patient will use at least one compensatory strategy (circling, describing the function, using a picture card) when unable to retrieve a target word in 70% of attempted exchanges during structured activities." This is measurable, it's practical, and it gives the family something concrete to reinforce at home.
Pragmatics and social communication often get overlooked because they feel squishy. They're not. "Patient will maintain eye contact and orient toward conversation partner during a 5-minute structured interaction without physical redirection more than 3 times per week" is specific and trackable. Turn-taking breakdowns, perseveration, and loss of topic maintenance are all addressable with well-written goals. The key is picking one or two pragmatics targets at a time rather than trying to fix everything at once. Here's something most people don't tell you: the rate of decline matters more than the absolute level when you're setting goals for dementia. A patient who was conversational and living independently at diagnosis will have very different therapy goals than someone diagnosed at a moderate stage who already needs prompting for basic needs. I had a patient, early-mid stage, who could carry on a twenty-minute conversation but would lose the thread completely if someone mentioned a word she couldn't access. We wrote a goal around redirecting back to the main topic with minimal verbal cues, and she met it for about three weeks. Then the disease progressed just enough that even the cues didn't work anymore. We rewrote the goal that week. That's the reality—your goals are always slightly behind the curve, and that's normal. Don't frame it as failure. Frame it as you doing your job correctly. Another thing nobody warns you about is the mismatch between what families expect and what the evidence actually supports. Families often want their loved one to "get better at talking" or "stop forgetting words." The honest answer is that speech therapy doesn't reverse the underlying pathology. What it can do is slow the functional communication decline by building routines, teaching compensatory strategies, and training communication partners. I've had to have that conversation more times than I can count, and it usually goes poorly if you lead with the negative. Start with what's possible, then clarify what isn't.
Get the Full Details

The Documentation Problem
Writing goals that satisfy insurance reviewers, family members, and clinical standards simultaneously is its own specialty. The trick is to make them strict enough to pass audit but flexible enough to account for variability. Using data ranges instead of single-point targets does this well. "3 out of 5 trials" instead of "5 out of 5 trials." "With verbal cueing" and "without cueing" as separate benchmarks. This reflects the actual day-to-day reality of dementia communication, which fluctuates based on sleep quality, medication timing, mood, and the time of day. I've found that scheduling therapy sessions at the same time each week actually helps with measurement consistency. Randomizing session times introduces a confounding variable that makes it impossible to tell whether a goal wasn't met because the patient regressed or because you happened to show up during their post-lunch dip. There's also a specific documentation angle that catches people off guard: distinguishing between baseline and current performance. Many clinicians write a goal, test the patient once at the start, and never go back to that baseline number. When the patient hasn't improved after twelve weeks, the documentation looks like therapy failed. In reality, the baseline was never locked in. I keep a separate tracking sheet now where the initial assessment scores are frozen and every subsequent data point is compared against that fixed reference. It makes the progress—or the lack of it—much clearer to everyone reading the chart.
When Speech Therapy Goals for Dementia Don't Work
I need to be blunt about the limitations. In moderate to severe stages, structured goal-directed therapy produces diminishing returns very quickly. A patient who can no longer produce single words consistently won't benefit from a goal about using sentence frames. At that stage, the focus should shift almost entirely to communication partner training. The therapy isn't for the patient anymore, it's for the people around them. This is counter-intuitive to clinicians who were trained to think of therapy as something you do to a patient. You're not doing it to them. You're changing the environment and the interaction patterns so that whatever communication capacity remains can actually get expressed. Another scenario where traditional goals fall apart is when the patient has significant behavioral and psychological symptoms of dementia alongside the communication disorder. Agitation, aggression, apathy, and psychosis aren't just comorbidities—they directly interfere with goal attainment in ways that have nothing to do with cognitive-linguistic ability. I once worked with a patient who could follow two-step commands in a quiet room but would scream and bolt the moment someone tried to introduce a picture board. No amount of goal-writing would fix that. The correct intervention was environmental modification and possibly pharmacological support, not another speech therapy objective. Knowing when to step back from the therapy framework entirely is a skill that takes years to develop. Advanced patients with concurrentapraxia of speech, dysarthria, or motor neuron disease components present an even harder challenge. The communication assessment needs to differentiate between impaired motor planning, impaired motor execution, and impaired linguistic processing before you write a single goal. Treating all three as one problem leads to interventions that address the wrong layer. I use a quick screen—repeated syllable production, sustained phonation, and auditory-verbal matching—before committing to a goal set. It takes about ten minutes and prevents months of misdirected therapy.
Practical Example of a Full Goal Set
Here's what a complete, realistic package looks like for a patient in the mild-to-moderate stage of Alzheimer's disease who previously held a professional job and had strong verbal skills: Comprehension: Patient will correctly identify the function of ten common household items presented verbally (e.g., "Show me the thing you cut with") in 4 out of 5 trials with no visual cues, across three consecutive sessions. Timeframe: 6 weeks. Expression: Patient will use a prescribed communicative strategy (circumlocution, gesture, or picture board selection) to convey a desired object or action in 60% of opportunities across meal and medication routines, as recorded by a designated communication partner. Timeframe: 8 weeks.

Pragmatics: Patient will remain engaged in a dyadic conversation for a minimum of 3 minutes with no more than two physical redirections from the therapist, during a familiar topical discussion, in 4 out of 5 sessions. Timeframe: 6 weeks. Compensatory Strategy (Partner Training): The primary family caregiver will correctly implement three structured communication strategies (reduced distractions, one-step instructions, yes/no confirmation checks) in 80% of observed interactions during weekly home visits. Timeframe: 4 weeks. This set is tight. It covers the domains, it's measurable, it involves the support network, and it accounts for the fact that the patient will have good days and bad days. If the patient meets all four goals, that's a successful block. If they meet two and the other two stall, you adjust and re-assess. The disease progression rate determines how aggressive you can be with the timeframe.
What I Wish I Knew Earlier
The biggest blind spot I had was underestimating the role of routine. Dementia patients thrive on predictable interaction patterns far more than they respond to novel therapeutic exercises. A goal that's embedded in an existing daily routine—morning medication, breakfast, evening wind-down—will produce measurably better outcomes than an identical goal practiced in an isolated clinic session. The retention and generalization gap between those two contexts is substantial. I restructured my entire approach around routine-embedded practice after watching a patient who nailed a goal in therapy but never once used the skill at home. The skill was there. It just couldn't cross the threshold from the clinic to the kitchen. Auditing your own goals every eight to ten weeks is non-negotiable. Not because the patient necessarily failed, but because dementia moves at different rates for different people and your targets need to reflect the current reality, not the one from six weeks ago. I run a quick diagnostic assessment at the start of each new cycle and compare it against the previous one. If the baseline has shifted, the goals shift with it. Sticking to outdated targets wastes everyone's time and produces documentation that doesn't hold up to scrutiny. One final thing that takes experience to learn: learn to recognize when a goal is structurally unsound before you invest weeks in it. If a patient can't independently follow a one-step command in a quiet environment, writing a goal about conversational turn-taking isn't just optimistic, it's counterproductive. Start at the skill level where the patient is already succeeding ninety percent of the time and build from there. The zone of proximal development concept applies here just as much as it does in any other area of rehabilitation. Skipping foundational levels creates gaps that compound over time.



