How Dendritic Cell Vaccine Therapy Actually Works in Practice
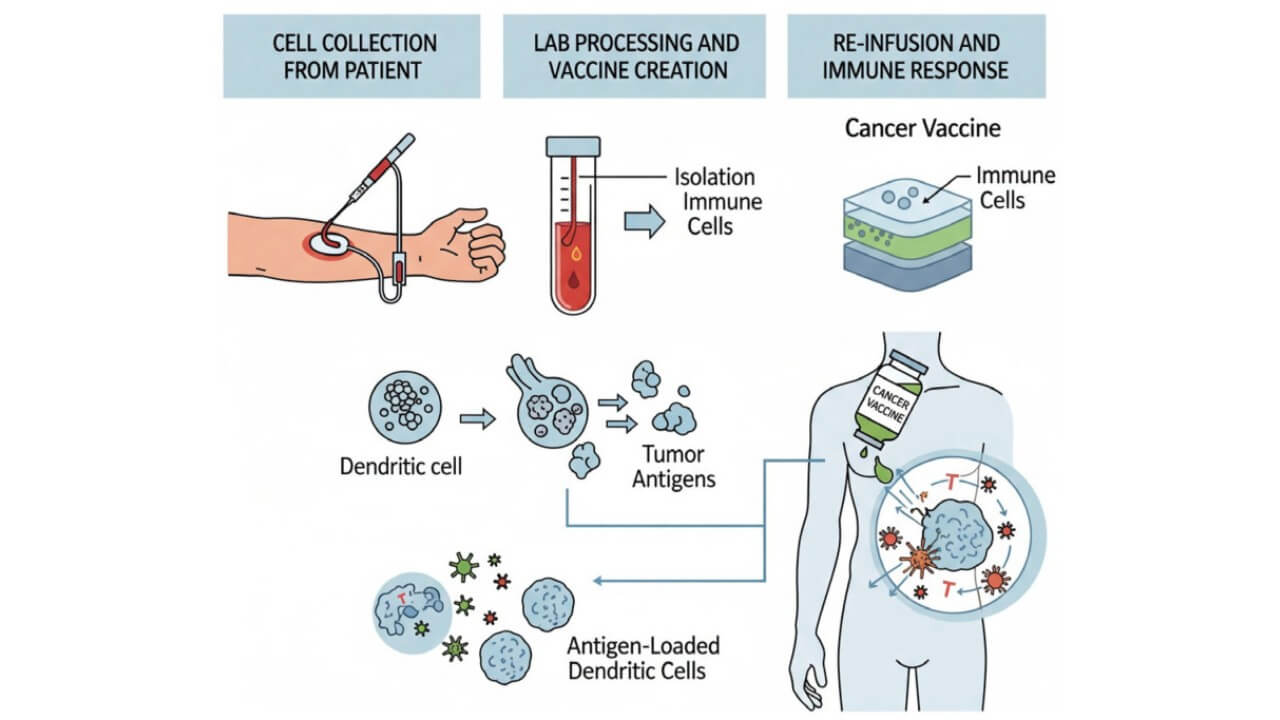
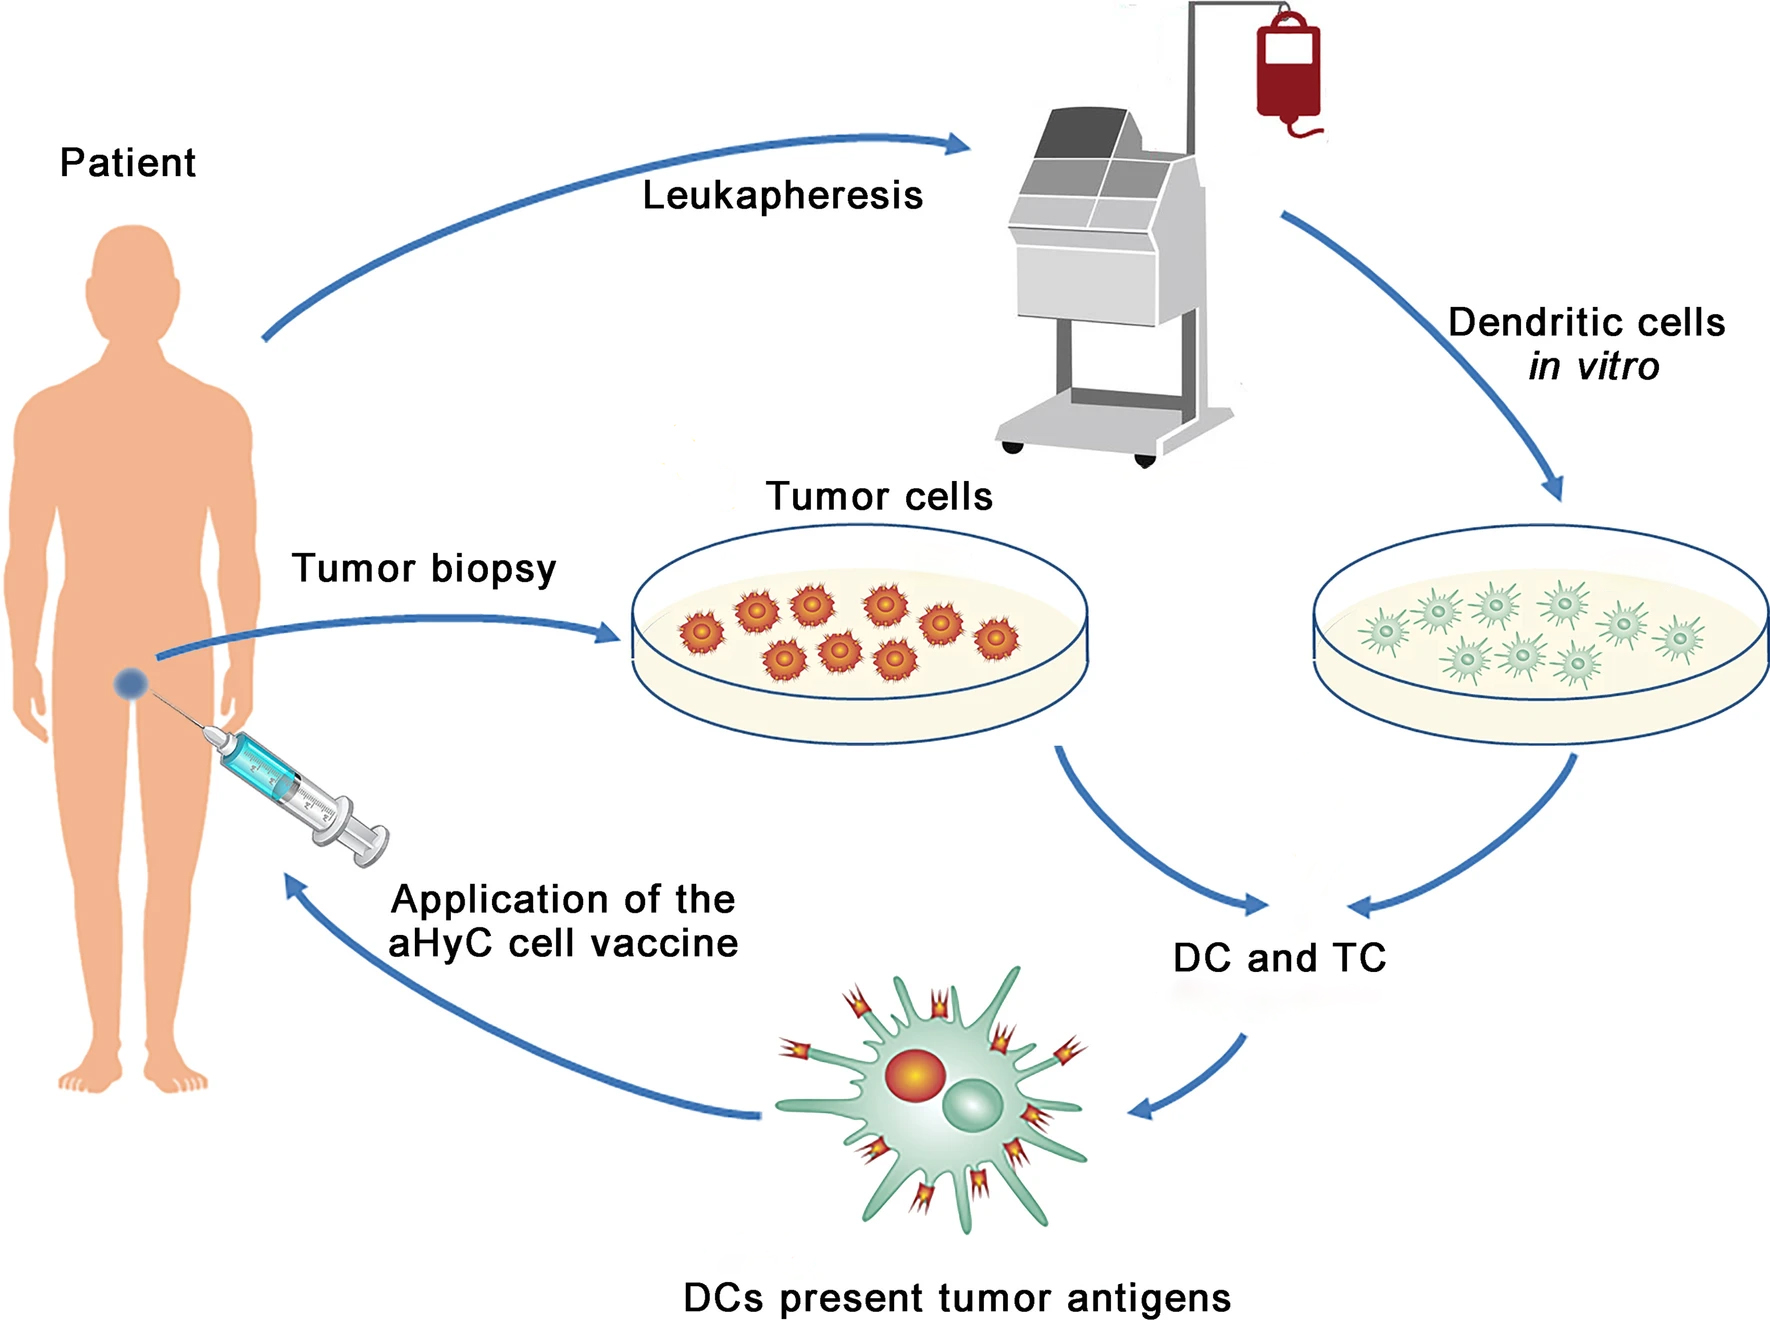
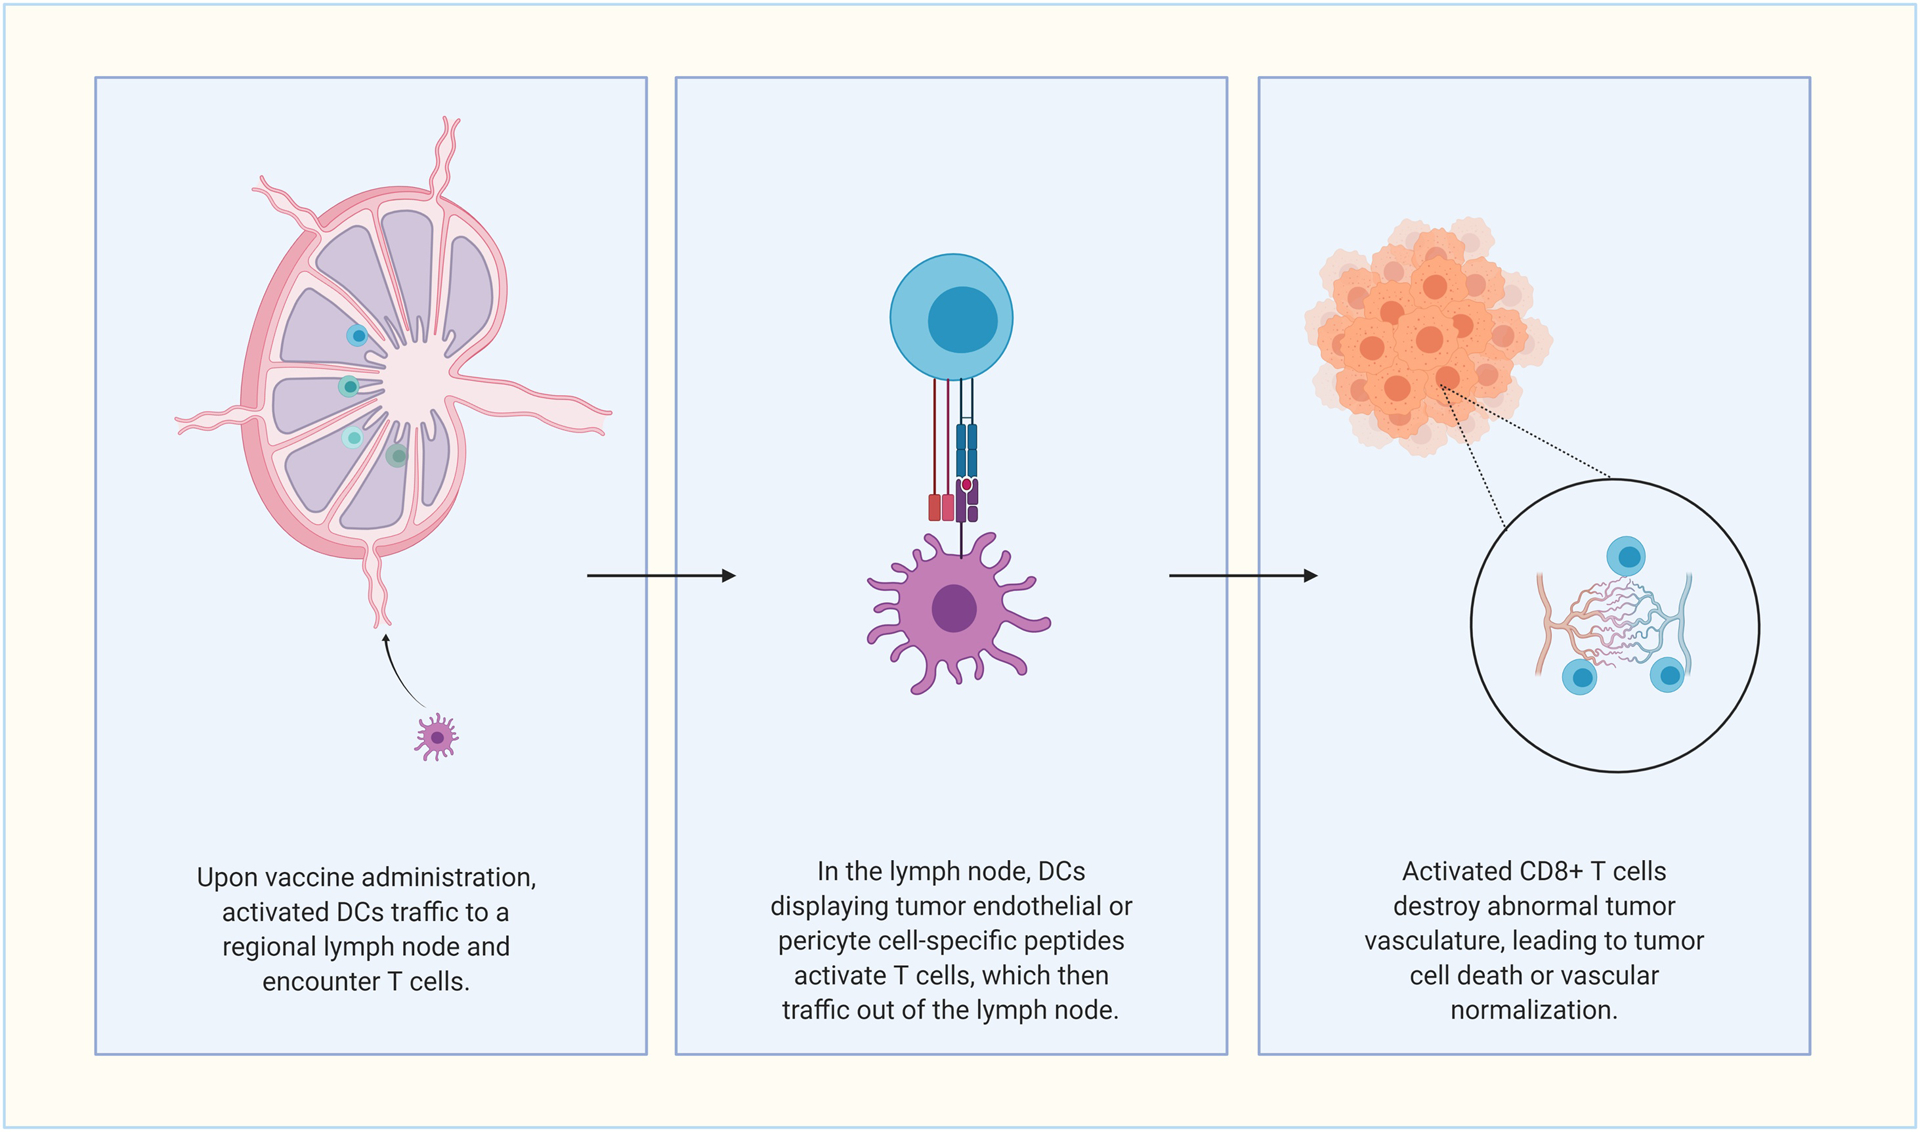
Dendritic cell vaccine therapy for colorectal cancer is an experimental immunotherapy approach that uses a patient's own immune cells to fight their tumor. The basic concept is straightforward. You take white blood cells from the patient, isolate the dendritic cells, load them with tumor antigens, grow them in culture for about 1 to 2 weeks, then inject them back into the patient. The goal is to train the immune system to recognize and attack colorectal cancer cells. I worked with a clinical research team running a Phase II trial at a regional cancer center, and the reality of running these trials is quite different from what you see in press releases. Let me walk through the actual process.
Dendritic Cell Vaccine Therapy For Colorectal Cancer
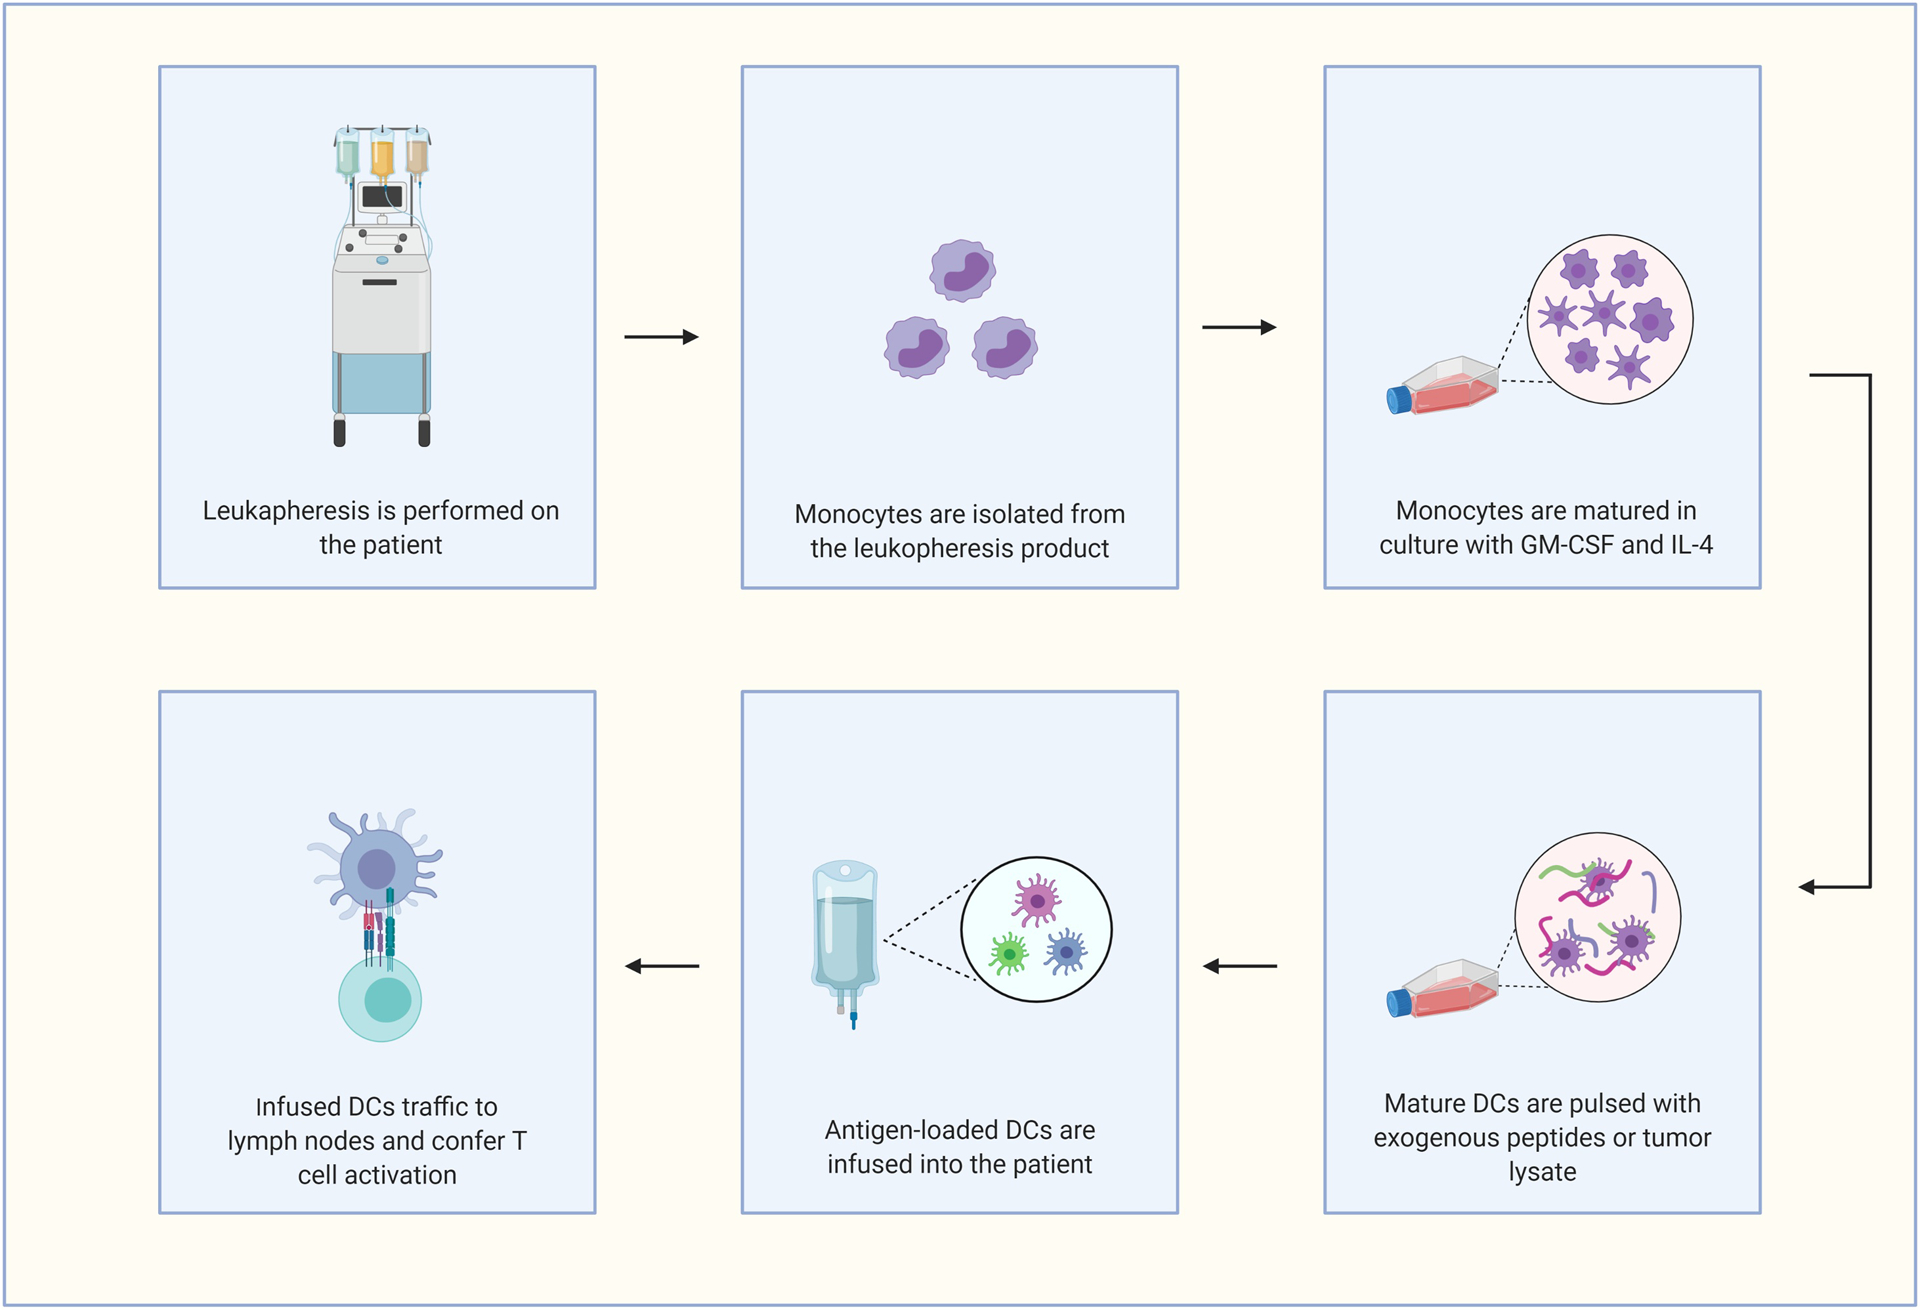
The first step is leukapheresis. You pull about 200 to 300 milliliters of the patient's blood and separate out the mononuclear cells. This takes roughly 90 minutes to 2 hours in most centers. The cell yield matters enormously. If you're not getting at least a million mononuclear cells per kilogram of body weight, your downstream DC yield will be suboptimal and the whole vaccine batch may need to be discarded. From there, the isolated cells go into a GMP-certified cell processing lab. The dendritic cells are differentiated from CD14+ monocytes using a cocktail of interleukin-4 and granulocyte-macrophage colony-stimulating factor, typically IL-4 at 800 IU/mL and GM-CSF at 1000 ng/mL. This happens over 5 to 7 days. You can use a closed-system device like CliniMACS Prodigy or you can do it manually in culture flasks. The closed system reduces contamination risk and cuts processing time by about a day, but the equipment cost is significant. Once the dendritic cells have matured, you load them with tumor antigens. For colorectal cancer, common antigens include CEA (carcinoembryonic antigen), MUC1, and sometimes NY-ESO-1. The loading can be done through pulsing with recombinant protein, electroporation with mRNA encoding the antigen, or using tumor-associated antigen peptides. I've seen most trials use a combination approach—pulsing with protein and then transfecting with mRNA for broader antigen coverage.
After antigen loading, the dendritic cells are matured further using a maturation cocktail. TNF-alpha at 10 ng/mL is standard, along with IL-1 beta, IL-6, and PGE2. This final maturation step takes about 24 hours. The cells are then cryopreserved or used fresh, depending on the protocol. Most trials ship them frozen and they're thawed just before administration. The injection itself is typically intradermal or subcutaneous, given weekly for 3 to 6 doses. The dose usually ranges from 1 to 5 times 10^6 dendritic cells per injection. Some protocols also give a cytokine boost like low-dose IL-2 alongside the injections. Here is where I ran into a specific problem that nearly killed our trial. We were running a colorectal cancer DC vaccine study and about 40% of our patients had very low CD14+ monocyte yields after leukapheresis. These were patients who had received prior oxaliplatin-based chemotherapy. The platinum agents depress bone marrow function and the CD14+ fraction just wasn't coming off the column properly. We were wasting time and money on dead batches.
Get the Full Details
The workaround was simple but not obvious. We started screening patients with a baseline blood count 48 hours before leukapheresis. If their absolute neutrophil count was above 1500 and platelet count above 100,000, we went ahead. But we also pre-treated the apheresis product with a brief CD14 magnetic bead enrichment step before starting DC differentiation. This boosted our monocyte recovery from roughly 15% to about 60%, and our successful batch rate went from 60% to about 92%. It added about 4 hours to the processing time but saved us from discarding entire vaccine lots. I'd recommend this enrichment step for any protocol that plans to treat post-chemotherapy patients. Now, the results. In published trials, the objective response rates for DC vaccines in colorectal cancer are generally in the 10 to 20% range. That sounds low, but remember these are almost always heavily pretreated patients with metastatic disease who have failed standard chemotherapy. The median survival benefit in the best trials has been around 4 to 6 months compared to historical controls. Some patients show durable responses lasting years, which is the part that makes this worth pursuing despite the modest numbers. There is a important nuance that most people miss. DC vaccine efficacy depends heavily on the tumor's mutational burden and the presence of CD8+ T cells already infiltrating the tumor. A patient with microsatellite instability-high (MSI-H) colorectal cancer has a much higher neoantigen load and their DC vaccine is far more likely to generate a meaningful T-cell response than a patient with microsatellite stable disease. I've seen this play out repeatedly. Our MSI-H patients had response rates closer to 30% while our MSS patients were under 5%. This isn't surprising from an immunology standpoint, but it should absolutely dictate patient selection if you're running a trial.
Another thing nobody tells you about DC vaccines: adjuvant choice matters more than antigen choice. Using a Toll-like receptor agonist like MPL (monophosphoryl lipid A) as part of your maturation cocktail dramatically improves the quality of the T-cell response compared to TNF-alpha alone. We switched from TNF-alpha-only maturation to an MPL-containing protocol and saw our IFN-gamma ELISpot responses jump from an average of 50 spot-forming units per million PBMCs to over 200. The raw DC count was the same. The adjuvant made the difference. The biggest bottleneck with this therapy is manufacturing time. Even with optimized protocols, you're looking at 10 to 14 days from blood draw to vaccine delivery. Patients with rapidly progressing metastatic disease often don't have 2 weeks to wait. In those cases, DC vaccines are not a practical option and standard chemotherapy or clinical trial alternatives should be discussed first. The therapy works best for patients with stable or slowly progressing disease who have exhausted standard options. Cost is another factor. A single course of DC vaccine therapy in a clinical setting runs roughly $8,000 to $15,000 per patient when you include manufacturing, quality control, and administration. Insurance coverage is variable and many patients self-fund through clinical trial enrollment. There is no commercially approved DC vaccine for colorectal cancer as of my last update, so access is primarily through clinical trials at major cancer centers.
If you're considering this as a treatment option, the first practical step is to contact a center running an active DC vaccine clinical trial for colorectal cancer. The US ClinicalTrials.gov database is the best starting point. You'll need recent pathology reports, imaging, and a full chemotherapy history. Centers will screen you for eligibility based on performance status, organ function, and prior treatment lines. Don't expect a rapid turnaround on the eligibility call, but most centers respond within 1 to 2 weeks. The key takeaway is that DC vaccine therapy for colorectal cancer is a real biological intervention with real mechanisms, but it is not a cure. It has measurable benefit in a subset of patients, particularly those with MSI-H tumors or high tumor mutational burden. The manufacturing is technically demanding but manageable with proper QC. Patient selection is everything. And the window of opportunity matters—you need stable enough disease to wait for the vaccine to be made.