Why Your Tendon Specimen Keeps Peeling Apart at the Edges
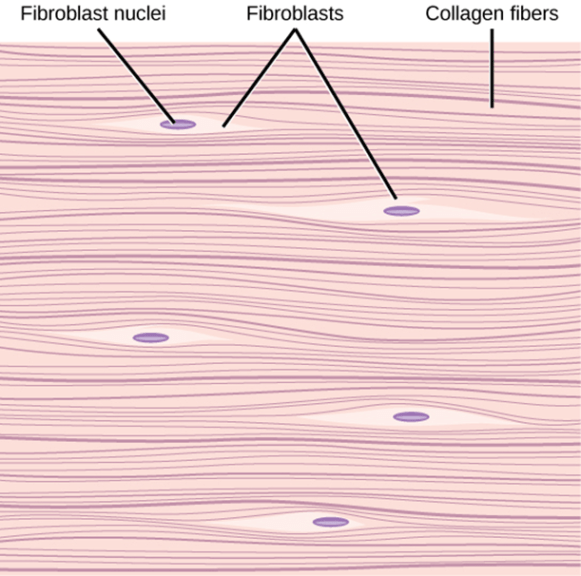
I spent three weeks last year fighting with histology slide prep on human Achilles tendon samples. The issue wasn't the staining. It was the sectioning. Dense regular connective tissue loves to delaminate along the parallel fiber planes when you try to cut it thin enough for light microscopy. I eventually solved it by embedding the tissue in a 1:1 mixture of OCT compound and agarose at 4%, then letting it sit at -20°C for a full 24 hours before sectioning. The added matrix support keeps the collagen bundles locked together. Standard embedding protocols fail here because there's so little ground substance to begin with. Dense regular connective tissue is exactly what it sounds like. You've got collagen fibers packed tight, all oriented in the same direction, with fibroblasts squeezed into narrow lanes between them. That's essentially the whole deal. The parallel alignment gives it enormous tensile strength along the axis of the fibers. It's not designed to handle stress from multiple directions. That's a different tissue's problem.
Dense Regular Connective Tissue: Structure and Function
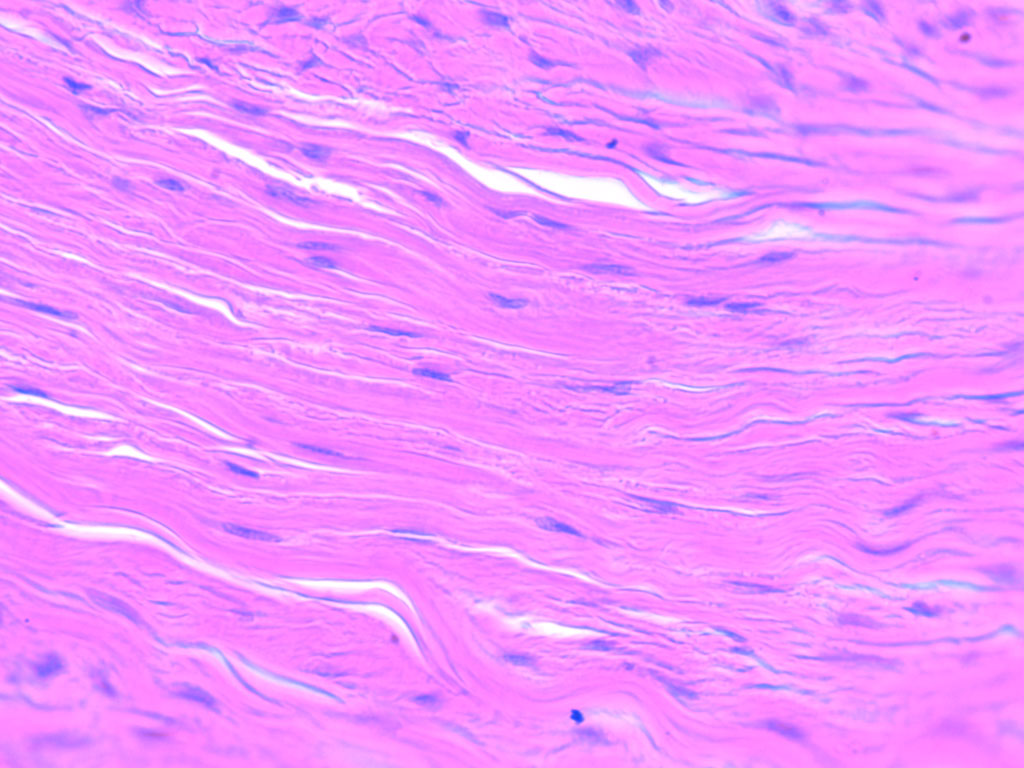
The collagen types involved matter more than people admit. Type I collagen dominates, making up roughly 80 to 90 percent of the dry weight. In some locations like the dermal papillae of certain animals, you'll see type III mixed in, which changes the mechanical profile slightly. The fibroblasts in tendons are sometimes called tendocytes because they have a flattened, elongated shape that follows the fiber orientation. Their nuclei show up as dark purple ovals in H&E stains, compressed between the eosinophilic collagen bundles. Here's something most textbooks gloss over. The vascular supply in dense regular connective tissue is remarkably sparse. A tendon might have blood vessels only at its peritendinous sheath and near the bone insertion points. The midsubstance relies on diffusion through the tightly packed matrix. This has real consequences for healing. A complete tear in the hypovascular zone of a tendon doesn't just take longer to heal. It may never heal on its own because the cellular machinery literally can't get there in sufficient numbers. The tenocytes don't just sit there. They're actively remodeling the collagen network throughout life, turning over fibers on a timescale of months to years depending on the load environment. That's why progressive loading matters in rehabilitation. Sudden excessive stress overwhelms the matrix because the cells can't adapt fast enough.
What Happens Under Load
The stress-strain curve of dense regular connective tissue tells you everything you need to know about its behavior. There's a toe region where the initially wavy collagen fibers straighten out, followed by a linear region where the tissue bears load efficiently, and finally a failure point. The toe region accounts for maybe 2 to 5 percent strain. The linear region extends up to about 8 to 10 percent strain before microtears begin. Rupture typically occurs around 12 percent strain in human tendon. Ligaments follow a similar pattern but they're slightly more compliant than tendons because their collagen organization isn't quite as uniformly parallel. That's a key distinction. Both are dense regular connective tissue, but the degree of alignment differs based on the mechanical demands of the joint they're stabilizing. One counter-intuitive thing that trips people up regularly. Stiffness in dense regular connective tissue actually increases with loading rate. This is strain-rate dependency. If you pull a tendon quickly, it appears stiffer and stronger. Pull it slowly and it deforms more at lower stress levels. This is why acute injuries from sudden movements often happen at lower overall forces than you'd expect from a slow pull test. The tissue hasn't had time to redistribute the strain across the collagen network through viscoelastic creep.
Get the Full Details

Practical Workarounds and Limitations
Masson's trichrome stain is the standard go-to for visualizing collagen in these tissues. It turns collagen blue or green while cytoplasm stains red. But here's what I learned the hard way. If you overstain with acid fuchsin before the trichrome step, the collagen fibers take up some of the red dye and you lose contrast. The differentiation step in the protocol is where most people mess up. I recommend checking under the microscope after each differentiation bath rather than timing it strictly. Two minutes might be too long for one specimen and too short for another depending on fixation quality and section thickness. The biggest limitation of dense regular connective tissue is its directional weakness. It handles unidirectional tension beautifully. Try pulling it perpendicular to the fiber orientation and it fails at a fraction of the parallel load capacity. That's not a design flaw. It's the reason tendons are structured the way they are. But it means injury patterns are predictable. Shear injuries across the fiber axis, even at modest forces, can cause significant structural damage. If you're working with this tissue for research purposes and need three-dimensional architecture data, confocal microscopy on cleared specimens gives you far better information than serial sectioning. Cleared specimens also preserve the native collagen orientation without the artifacts introduced by mechanical sectioning. The trade-off is time. A single cleared specimen takes roughly 48 hours to process through the clearing and imaging pipeline versus 4 hours for a standard histology workflow.