The Real Stuff About Dermal Piercings
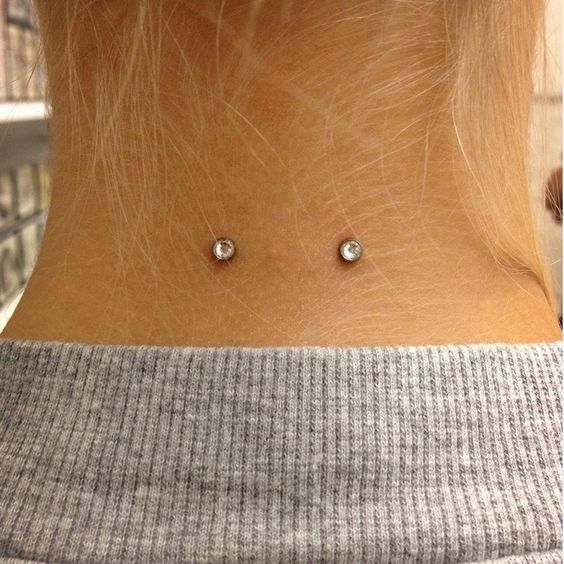
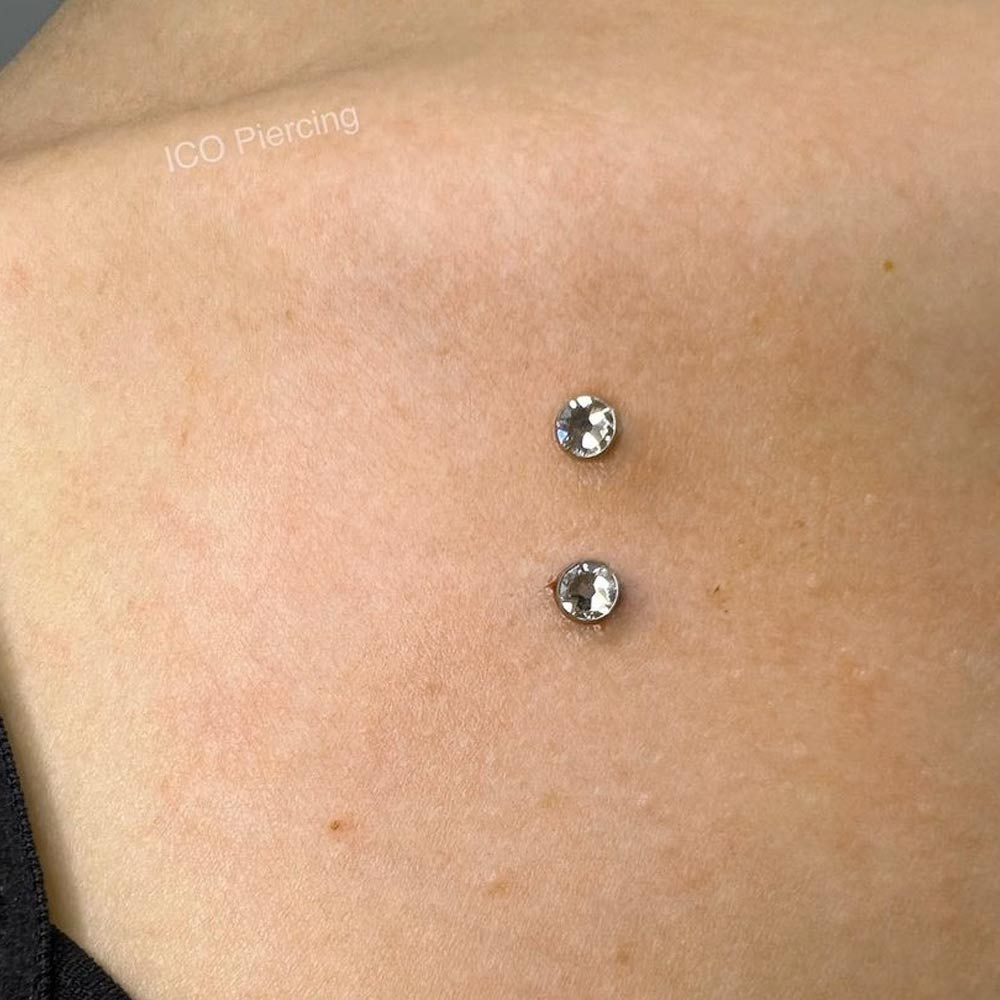
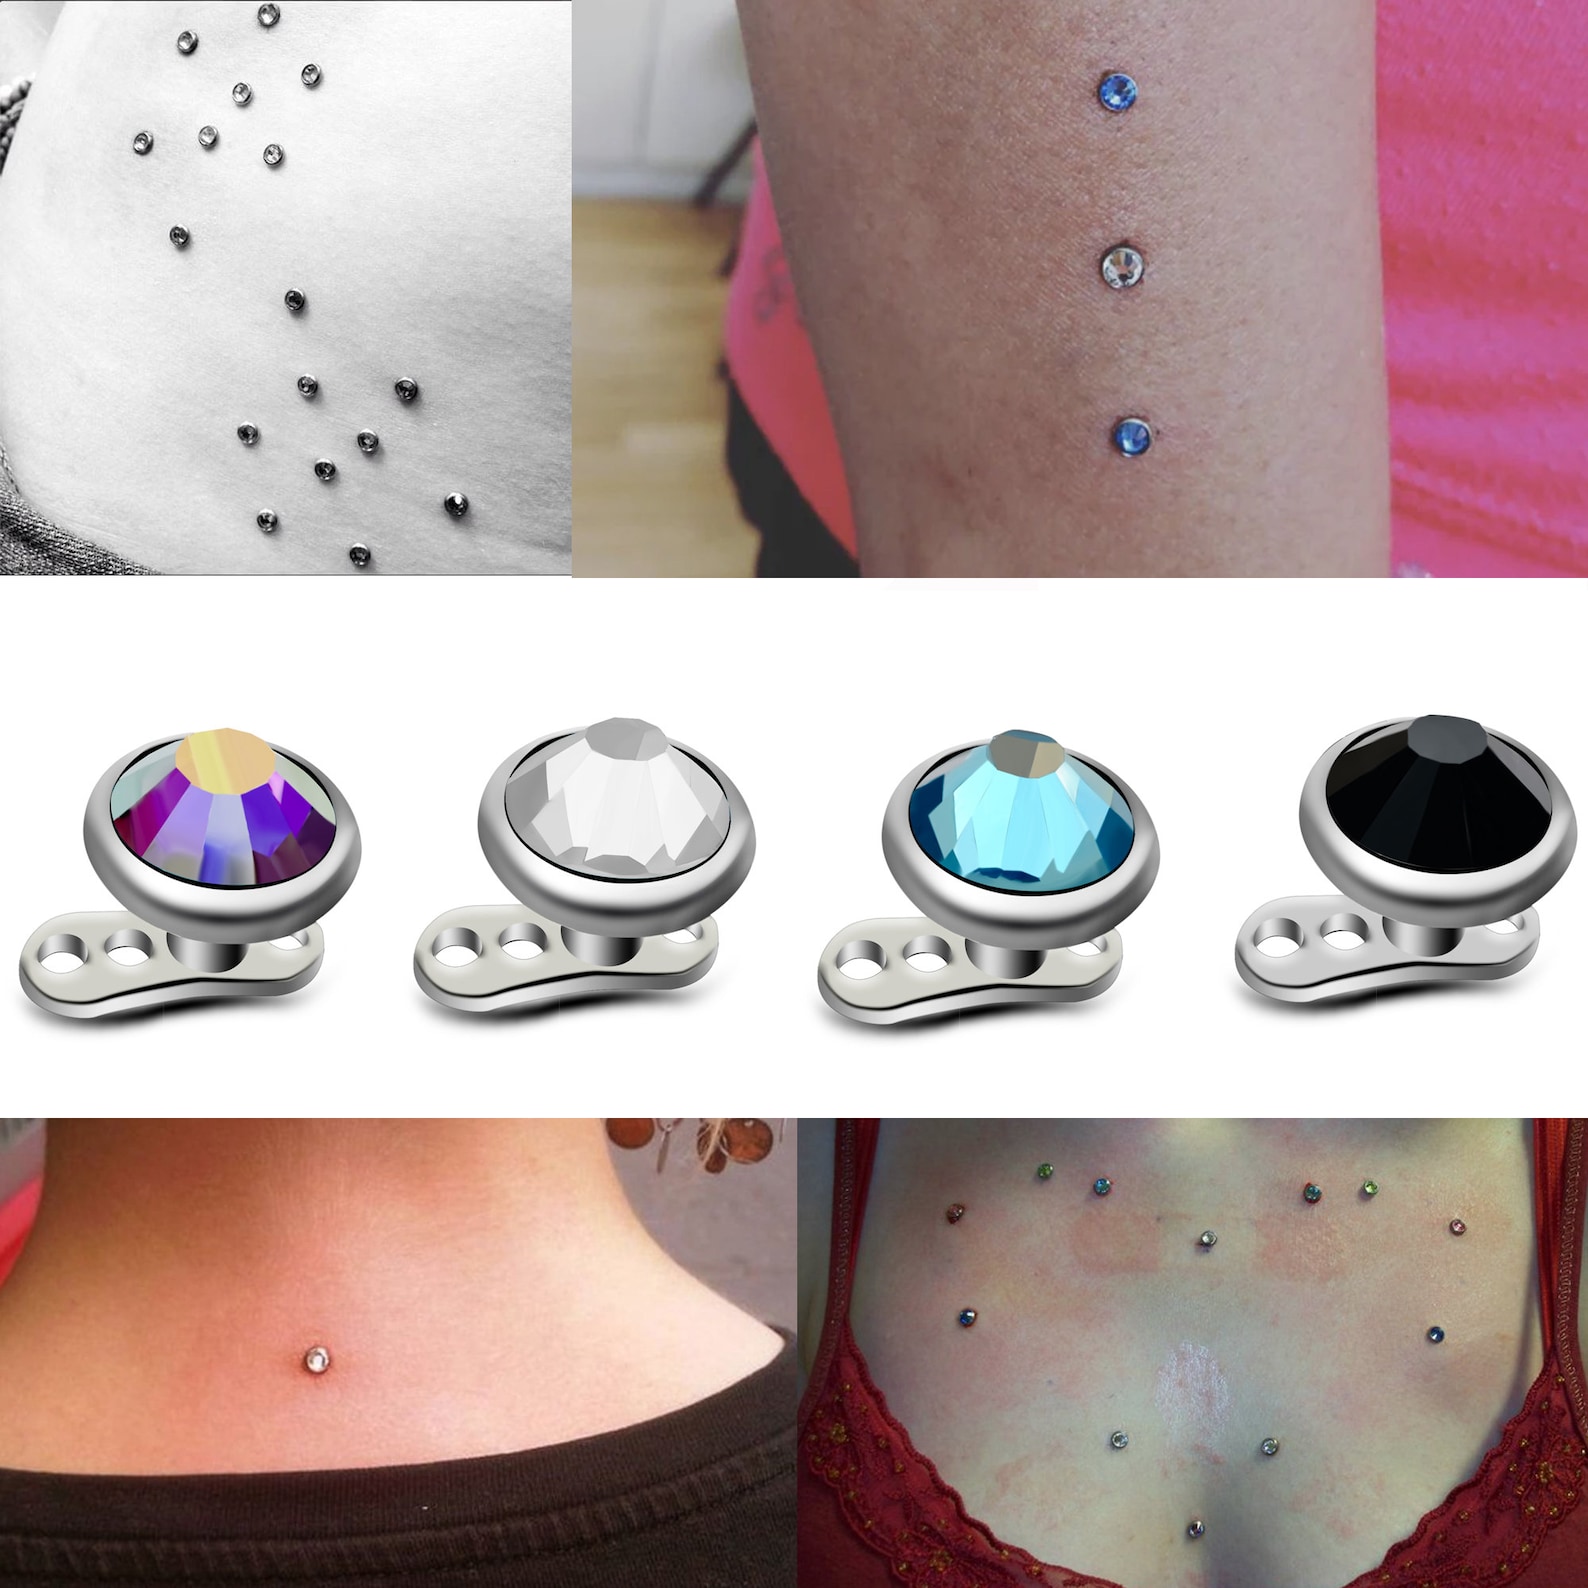
I got one on my forearm about three years ago and took it out six months later because the jewelry kept migrating. That's not a warning, just context for where I'm coming from. I've since done probably a dozen more on other people's bodies in a studio setting, so I'm writing this from someone who's actually held the tissue while drilling, not someone who read a wiki. Dermal Piercing, or a single-point piercing, is a surface anchor inserted at a 90-degree angle into the dermis layer of the skin. The base sits under the skin while the top post or head protrudes outward. It's fundamentally different from a traditional piercing because there's no through-and-through channel. The entire retention mechanism depends on the healing tissue growing around that flat base plate. That difference matters enormously for placement, aftercare, and long-term success rates.
The Procedure Itself
Here's what the actual process looks like on the table. I mark the spot first with a surgical pen while the client is upright, because gravity shifts the tissue and a spot that looks fine lying down can end up on a fold or stretch point once they're standing. Then I numbing cream if they've asked for it — most do. Lidocaine 5% for about 45 minutes under occlusion wrap. Doesn't change the anatomy, just takes the edge off. I use a hollow dermal punch, typically 1.2 to 1.6 millimeters depending on the anchor size. The punch goes in straight, twist motion, not jabbing. You feel a slight resistance when you hit the subcutaneous fat layer and then a soft give when you breach into the dermis plane. That's your depth cue. Most beginners punch too deep and end up with the anchor sitting in fatty tissue that won't hold it. Or too shallow and the base plate catches on clothing during healing. Either way, rejection starts within weeks. Once the puncture is clean, I insert the anchor with a dermal implanter tool. The foot of the anchor should sit flush against the underside of the dermis, not buried deeper. Then I clean out any blood or tissue debris from the channel with saline, insert the top jewelry, and close. The whole thing from mark to dress takes about eight minutes for a straightforward placement.
I ran into a specific problem last year with a client who wanted a dermal on the back of their hand. Standard placement, looks clean. Two weeks in, the anchor was pushing out through the top of the skin. What I hadn't accounted for was that their hand had significant fascial tension from years of manual labor. The skin was literally being pulled apart at a microscopic level every time they made a fist. The workaround was swapping to a longer post initially and having them wear a light compression sleeve for the first three weeks of healing. Slowed the tension enough for the fistula to form. Still rejected at month four, but that's sometimes just the math of hand dermals.
Get the Full Details
Why Most Dermal Piercings Fail and How to Avoid It
The rejection rate for dermal anchors is honestly somewhere between 20 and 40 percent depending on placement. That's not a typo. A navel dermal will last. A wrist or hand dermal is basically a temporary project by design. People don't usually know that. The counter-intuitive part is that migration isn't always a bad sign in the first two weeks. Some amount of apparent movement is normal as the body forms the encapsulation scar tissue around the base plate. The question is direction and speed. If the anchor is visibly shifting millimeters per day over a two-week period, that's rejection, not settling. If it's barely perceptible and the surrounding tissue is calm and not red, you're probably fine. Watch it. Don't touch it. Another thing beginners miss: aftercare with dermals is entirely about keeping the area clean and dry, not about twisting or cleaning the jewelry. The top post should not be moved during healing. Every time you tug on it, you're micro-tearing the fresh fistula forming around the base plate underneath the skin. Saline spray twice daily, gentle pat dry, and leave it alone. No ointments. Ointments trap moisture and create a breeding ground for bacteria under an area you can't properly ventilate.
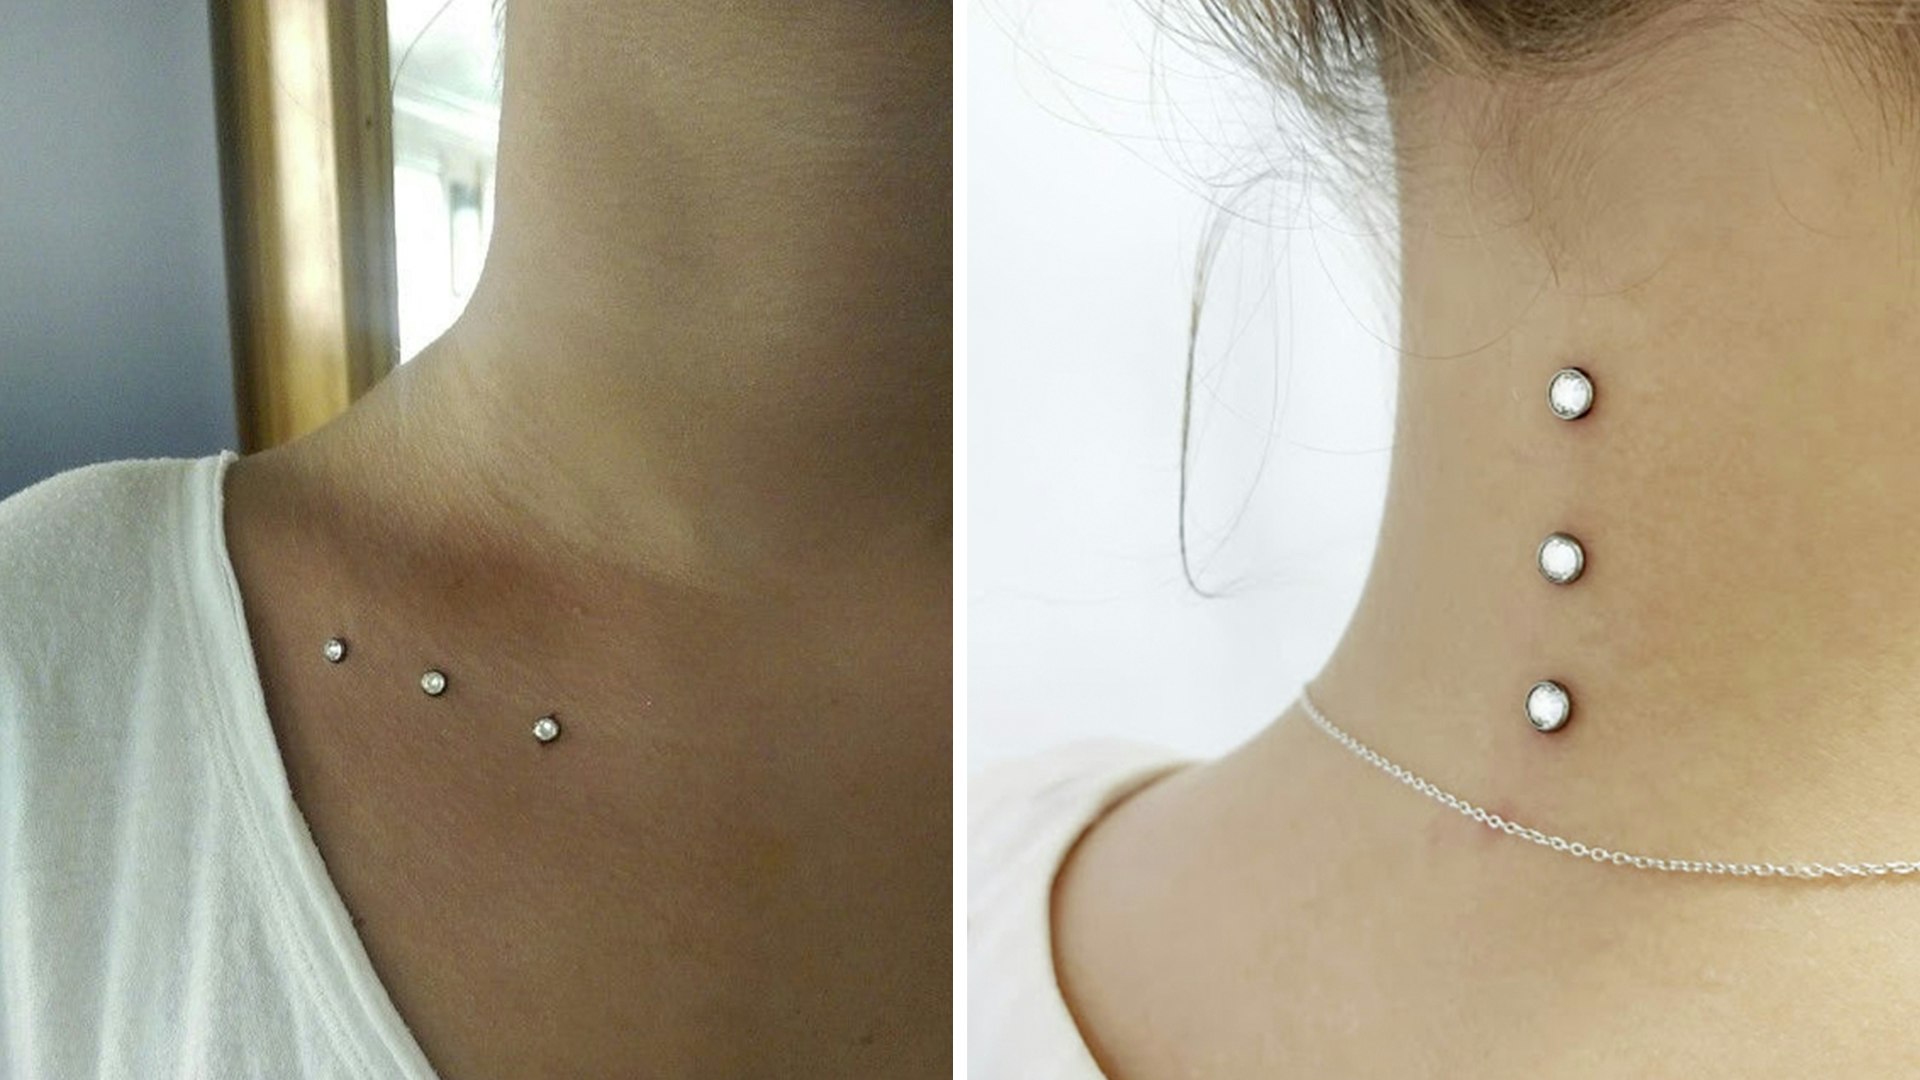
Placement is the single biggest factor in longevity. The ideal sites have thick dermis with minimal subcutaneous fat and low mechanical tension. The collarbone area, the flat of the hand near the thumb base, the sternum — these tend to hold. Anything over a joint, on a stretch-prone area like the waist or ankle, or on skin that moves significantly with facial expressions if you're going near the face — those are all problematic zones. I've turned down more clients for bad placement ideas than I've completed dermals in questionable spots. Not being stubborn about it saves you from an infection story.
Removal When It Goes Wrong
Sometimes you just need to remove it. If the anchor is fully rejected and sitting just under the surface, you can sometimes express it like a pimple with sterile pressure. If it's still embedded and healing, a qualified piercer can lift the base plate with a small incision tool and remove it. The hole closes on its own in most cases within a few days to a week. There's usually a small indent where the base plate was for a while, but it fades. Scarring is minimal if the body was rejecting it, actually — the trauma of removal is far less than the trauma of months of inflammation. I don't recommend trying to dig it out yourself with tweezers. That's how you tear the channel and create a real wound instead of a small puncture. If you're dealing with a rejecting dermal and can't get to a piercer, warm compresses three times a day can help encourage natural expulsion. Wait until it's ready.