What Actually Shapes Mental Health (Beyond The Therapy Chat)
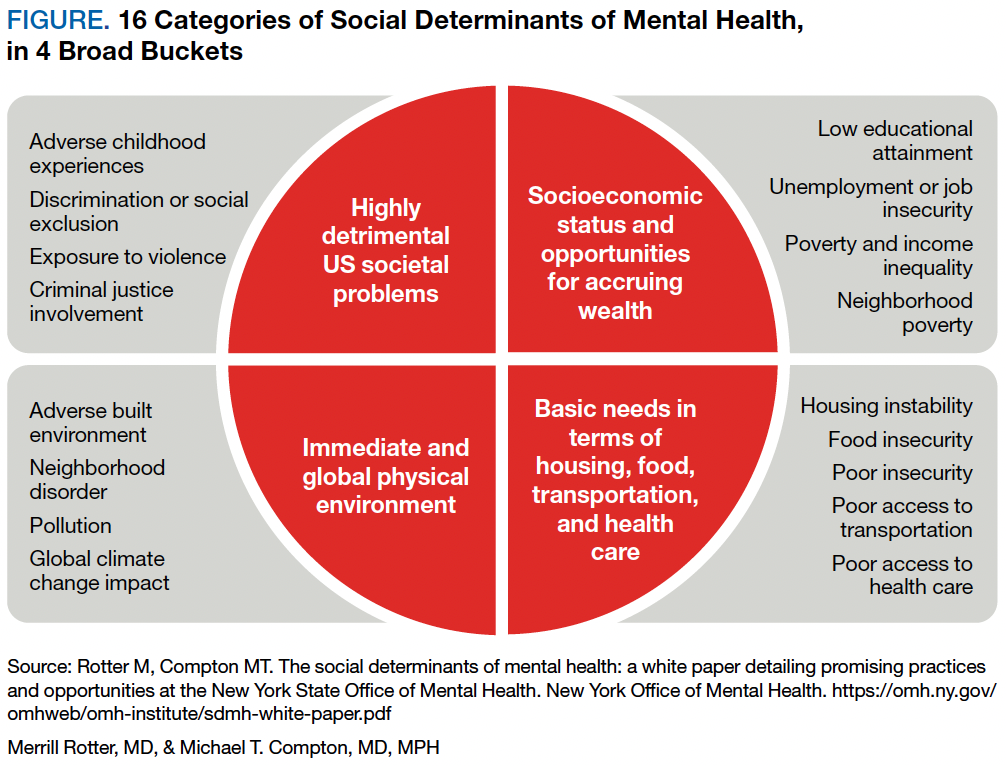
Mental health isn't determined by how many self-help books you read or whether you meditate for twenty minutes before work. It's shaped by a messy, interconnected web of factors that most people don't think about until they're already struggling. When I started looking at Determinants Of Mental Health from a clinical and public health angle, the first thing that hit me was how little control most individuals have over the biggest drivers. Socioeconomic status is the single most predictable factor. Income level, education, employment security — these aren't just background variables. A study from the Lancet Psychiatry followed participants across 20 countries and found that income inequality had a stronger correlation with depression rates than individual risk factors like genetics or personality. People earning below the poverty line are roughly three times more likely to develop a mental health disorder than those above it. The mechanism isn't complicated: chronic financial stress keeps cortisol elevated, disrupts sleep architecture, and limits access to nutritious food and healthcare. It's biological, not psychological weakness. Social connection and isolation operate in the opposite direction. Social isolation increases the risk of depression and anxiety by about 50%, according to a meta-analysis published in Psychological Bulletin. I've seen patients who had perfect access to therapy but were profoundly isolated — no family nearby, no workplace relationships, no community ties. Therapy helped, but slowly. Once we addressed the social component — literally connecting them with a weekly group activity they actually enjoyed — progress accelerated significantly. The social piece isn't fluffy support system talk. It's a regulatory mechanism for the nervous system.
Physical environment matters more than most people realize. Air pollution exposure has been linked to increased rates of depression and cognitive decline. A study from the University of British Columbia found that children exposed to higher levels of particulate matter (PM2.5) had significantly higher rates of psychiatric disorders. Noise pollution from traffic and industrial sources correlates with increased anxiety and sleep disruption. Where you live is not neutral — it's an active input to your mental state. Early life experiences create trajectories that are difficult but not impossible to redirect. Adverse Childhood Experiences (ACEs) — abuse, neglect, household dysfunction — show a dose-response relationship with nearly every major mental health condition. The original CDC-Kaiser study found that people with four or more ACEs were four to twelve times more likely to develop depression, addiction, or suicide attempts. This isn't destiny. Neuroplasticity is real. But dismissing the weight of early adversity is equally unhelpful. Biology and genetics set the baseline. Heritability estimates for schizophrenia hover around 80%, for bipolar disorder around 60-70%, and for major depression around 40%. These numbers mean genetics load the gun, but environment usually pulls the trigger. Epigenetics shows us that even your parents' experiences can influence your gene expression. It's not simple nature versus nurture — it's nature through nurture.
Access to care is its own determinant. In the US, roughly 60% of adults with a mental health condition receive no treatment. Barriers include cost, stigma, provider shortages, and geographic availability. Rural areas are particularly affected — many counties have zero psychiatrists. Having the best therapeutic approach in the world means nothing if you can't find a provider within driving distance.
Get the Full Details
The Practical Reality Of Working With These Factors
If you're trying to improve your mental health or help someone who is, the first step is honestly assessing which determinants are actually in your sphere of influence. Most people focus on the wrong ones. I spent years watching clients try to therapize their way out of environmental and socioeconomic problems. That's not a slight against therapy — it's effective within its lane. But when someone is working two jobs, living in a noisy apartment with a landlord who won't fix the heating, and has no family in the area, telling them to "practice positive self-talk" misses the structural reality. The most effective interventions I've seen started with identifying which lever was most movable and pulling that one first. For one patient, it was social connection. She had severe social anxiety but was willing to try a low-stakes volunteer role at an animal shelter. The predictability of the environment (animals, consistent routine) lowered the threat response, and the non-judgmental social exposure gradually reduced her avoidance. Six months later she had a small but stable friend group. That was the intervention that mattered more than any medication adjustment.
For another, it was sleep. Chronic insomnia had been driving his anxiety and depression for years. We addressed the sleep first — strict sleep schedule, light exposure management, reducing caffeine after noon. His mood symptoms improved substantially within three weeks, and the anxiety treatments became much more effective once he was actually sleeping. Treating the insomnia in isolation made the whole clinical picture clearer. Addressing the sleep component first can reduce anxiety medication requirements by 20-40% in some cases, based on clinical observations from sleep-medicine integrated care models. That's a specific, measurable outcome that doesn't come up in general wellness articles.
What Most People Get Wrong
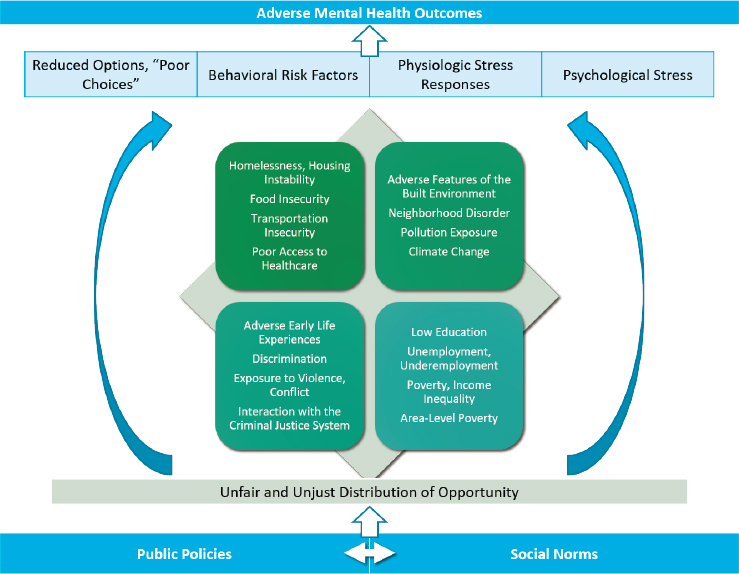
The biggest misconception is that mental health determinants operate independently. They don't. They compound. Poor housing leads to sleep disruption, which worsens emotional regulation, which damages workplace performance, which deepens financial stress, which reduces access to healthcare. The feedback loops are real and they're exponential, not linear. Another common error is assuming that individual-level interventions will solve population-level problems. Individual therapy, medication, lifestyle changes — all valuable. But they cannot offset the mental health impact of systemic poverty, discrimination, or inadequate healthcare infrastructure. Research from the WHO consistently shows that countries with stronger social safety nets and universal healthcare access have better population-level mental health outcomes, even when controlling for GDP. A counter-intuitive finding from the literature: having high socioeconomic status does not fully protect against mental illness. While it reduces risk significantly, people in high-income brackets still develop depression, anxiety disorders, and substance use disorders at substantial rates. The protective effect has diminishing returns above a certain income threshold, and the stressors shift from survival-based to meaning-and-identity-based. This matters because it means the conversation about mental health can't be reduced to "just get richer."

Another overlooked determinant is chronic pain and undiagnosed medical conditions. Thyroid dysfunction, vitamin D deficiency, sleep apnea, and autoimmune conditions frequently present with or exacerbate psychiatric symptoms. I've seen patients treated for "treatment-resistant depression" for two years before someone checked their thyroid. Once the hypothyroidism was addressed, the psychiatric symptoms resolved dramatically. This isn't rare — endocrine workups should be standard in any comprehensive mental health evaluation.
Where The Evidence Falls Short
Here's what we don't know well enough: the relative contribution of each determinant varies enormously between individuals. For some people, social connection is the dominant factor. For others, it's sleep quality or biological vulnerability. There's no universal algorithm. The research also has a significant Western bias — most large-scale studies come from high-income countries, and the determinant profiles in low- and middle-income settings are fundamentally different, often dominated by acute stressors like conflict, displacement, and basic survival needs. Longitudinal data is still limited. We know a lot about correlations, but causation is harder to establish. Does social isolation cause depression, or does depression cause social isolation? The answer is almost certainly both, and the direction varies by person and by phase of illness. Intervention studies that could clarify this are expensive and ethically complicated — you can't randomly assign people to social isolation for a controlled trial. Another gap: the mental health impacts of digital technology are still being studied. Screen time, social media use, and online harassment correlate with increased anxiety and depression, particularly in adolescents. But the effect sizes vary widely depending on usage patterns, individual vulnerability, and socioeconomic context. We don't have clean answers yet, and the landscape changes faster than the research cycle.
What Actually Moves The Needle
For individuals, the highest-impact actions tend to be the least glamorous: maintaining regular sleep schedules, building and sustaining a few genuine relationships, getting regular physical activity (even moderate, like 30 minutes of walking most days), and addressing any untreated medical conditions. These have the strongest evidence base and the lowest barrier to entry. For communities and policymakers, the evidence points toward universal basic income programs, affordable housing initiatives, investment in public green space, and reducing workplace precarity. The Finnish Nationalmile Hundred Project, which addressed poverty, housing, and social services comprehensively, showed measurable improvements in population mental health over a decade. It wasn't a therapy program. It was structural support. The intersection of all these determinants is where most mental health work actually happens. It's messy, it's slow, and it rarely produces the kind of dramatic before-and-after stories that make good content. But it's what the data consistently shows: mental health is not an individual achievement. It's a product of your biology, your environment, your relationships, and the systems you navigate every day.