
What Actually Happens During a Developmental Assessment Of Young Children
A developmental screening isn't a test the child passes or fails. It's a structured observation session where a trained clinician watches how a child interacts with toys, responds to questions, and handles transitions. The whole thing usually takes 30 to 45 minutes for a standard screening. A full assessment can run two to four hours and requires multiple tools. I've been doing this work long enough to know that the paperwork often takes more time than the actual observation. That's just how it is.
Developmental Assessment Of Young Children: Tools and Procedures
There are three main categories of tools you'll encounter in practice. Standardized norm-referenced instruments like the ASQ-3 (Ages and Stages Questionnaire), the M-CHAT-R/F for autism screening in toddlers, and the Bayley Scales of Infant and Toddler Development. These give you scores you can compare against large population norms. They're useful, but they're also expensive to administer properly and require training certificates you need to maintain. Clinical observation checklists come next. Things like the CDC's Milestone Tracker, the Denver Developmental Screening Test, and various therapist-made rubrics. These are faster and cheaper. They catch obvious red flags. They miss subtleties. Then there are parent-reported questionnaires. The ASQ is the most common example. Parents fill them out at home or in the clinic waiting room. This method works well because parents see the child in more environments than any clinician ever will. It also means you're relying on parental recall accuracy, which varies wildly depending on the caregiver's stress level, education, and cultural background.
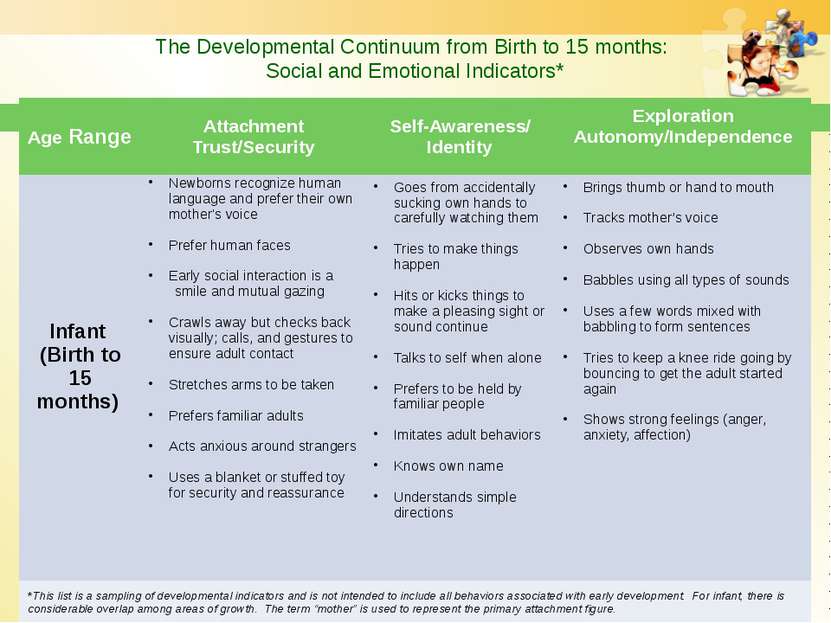
Here's something most beginners don't understand: the best assessments combine at least two of these methods. Relying on just one gives you a narrow and often misleading picture. I once had a case where a child scored solidly in the expected range on a parent report but showed significant delays across all domains during direct observation. The child had learned to perform on command in clinic settings but couldn't demonstrate those skills naturally. That gap between tested ability and real-world ability is one of the most important things to track. The process itself follows a fairly standard flow. You start with a developmental history — when did the child first sit up, walk, say words, show social engagement? You interview the parents or caregivers about concerns, pregnancy history, birth complications, family history of developmental disorders, and any previous evaluations. Then you move into the observation portion. You use play-based activities designed to elicit specific milestones. A 24-month-old might be asked to build a tower of blocks, point to body parts, follow two-step commands, and engage in pretend play. Each activity maps to a domain: gross motor, fine motor, language, cognitive, and social-emotional. You document everything in real time. Not just whether the child succeeded or failed a task, but how they approached it. Did they give up after one try? Did they seek adult help? Did they avoid eye contact? These behavioral observations often matter more than the raw score.
Get the Full Details
Common Pitfalls That Skew Results
I've seen assessments go wrong in ways that feel almost funny until you realize a family just got sent home without the services they needed. The most common error is administering a tool outside its validated age range. The ASQ-3, for example, covers ages 1 month to 5½ years in five-month intervals. If you slap it on a 6-year-old because it was the only thing in the drawer, you're not getting data. You're getting noise. Another frequent mistake is letting the child's mood dictate the session length without adjusting expectations. A tired, hungry, or anxious toddler will perform significantly below their actual ability. I had a case last year where a 30-month-old couldn't identify a single body part during the initial observation. She was having a rough morning. We paused, gave her a snack, switched to a quieter corner, and came back 20 minutes later. She passed every item on the second attempt. The difference wasn't in her development. It was in the conditions. Cultural bias in standardized tools is a real and under-discussed problem. Many instruments were normed on predominantly white, middle-class, English-speaking populations. A bilingual child who hears two languages at home may appear to have a language delay on an English-only expressive language subtest when they're actually developing normally. I learned this the hard way after referring a child for speech therapy based on a screening result, only for the speech-language pathologist to discover the child was simply code-switching between Spanish and English and had age-appropriate vocabulary in both languages combined. That referral caused unnecessary anxiety for the family and delayed the family getting the right support.
Equipment failure is another thing nobody warns you about. I once lost an entire afternoon because the clip-on timer on the Bayley scale stopped working mid-session and I didn't notice until I was trying to time a response window. You need backup methods. A phone stopwatch works. Paper and pen works. Just don't rely on one piece of technology.
What the Scores Actually Mean
Standardized tools typically produce a scaled score, a percentile rank, and a category like "expected," "monitoring," or "needs further evaluation." The monitoring category is where most uncertainty lives. It means the child scored below the expected range but not low enough to definitively indicate a delay. This is the gray zone where clinical judgment matters most. A child in the monitoring range with strong protective factors — responsive caregiving, no family history of delays, good nutrition, stimulation at home — may simply need another screening in three months. A child in the same range with risk factors — prematurity, known genetic conditions, limited early stimulation — should probably move straight to a comprehensive evaluation. Percentile ranks are easy to misinterpret. A 25th percentile doesn't mean the child is delayed. It means they scored above 25 percent of children in the norming sample. That's still within the normal range for most tools. Clinicians sometimes call the 15th or 16th percentile the cut-off for "below expected," which comes from treating a continuous distribution as if it has a hard boundary. Development doesn't work that way. There's no biological switch that flips at the 16th percentile. The Bayley Scales use a mean of 100 with a standard deviation of 15. Scores below 85 are generally flagged. That's about the 16th percentile. But here's the thing: test-retest reliability on the Bayley for children under two is moderate at best. A score of 82 today could be 90 in six months without any intervention. The child didn't change dramatically. The measurement did. This is why repeating screenings over time is standard practice, not optional.

When to Refer and What Comes Next
If the screening indicates a possible delay, the next step is a comprehensive evaluation by a specialist. That might mean a developmental pediatrician, a pediatric neurologist, a speech-language pathologist, or an audiologist. Hearing screenings should always be part of the workup for any child flagged for language delay. I've seen too many children sent for speech therapy when the real issue was untreated otitis media with effusion — fluid in the middle ear that muffled sound. The fluid cleared up after six weeks and the language gap narrowed significantly without any therapeutic intervention. Early intervention services in the United States are available for children under three through state-partnered programs. You don't need a medical diagnosis to qualify. A documented developmental delay is sufficient. Parent training is a huge component of these services, and that's where the actual progress happens. Therapy once a week for an hour won't move the needle the way consistent daily practice at home will. For children over three, the pathway usually goes through the public school system under IDEA Part B, with an Individualized Education Program determining what services the child receives. The transition from early intervention to preschool services is one of the most stressful periods for families. Documentation from the developmental assessment you conducted will be critical here. Keep your records thorough and organized.
What These Assessments Can't Tell You
A developmental assessment captures a snapshot. It tells you what a child can do on a given day with a given set of tools and a given clinician. It doesn't tell you why. It doesn't tell you what the child will look like at age eight. It doesn't capture the child's potential, their resilience, or the impact of their home environment on their trajectory. Two children can score identically on the ASQ-3 and have completely different life outcomes based on factors no screening tool measures. There's also the issue of false negatives. A child who scores in the expected range on a screening can still have significant difficulties that only become apparent in more demanding environments. A child might handle one-on-one interaction in a quiet room but struggle profoundly in a classroom with twenty other kids and constant sensory input. That's not a failure of the assessment. It's a limitation of the context. If you're only assessing in a clinic, you're missing half the picture. Screening tools are designed to be sensitive, not specific. They catch more problems than they confirm. That's intentional. Missing a real delay is worse than flagging a false alarm. But it does mean every positive screen needs follow-up, and that follow-up capacity is often the bottleneck in any system. I've worked in clinics where the wait for a comprehensive evaluation after a positive screen was four to six months. Four to six months is a long time in early brain development.
The practical workaround I use is staging. I don't wait for the full evaluation to begin supporting the family. If a screening raises concerns, I provide the parents with targeted activities for the specific domains that need attention, connect them with early intervention paperwork immediately, and schedule a follow-up screening in eight to twelve weeks. That way the child isn't idle while waiting. The parents aren't sitting with uncertainty. And the next screening gives us data on whether the gap is closing, staying the same, or widening.



