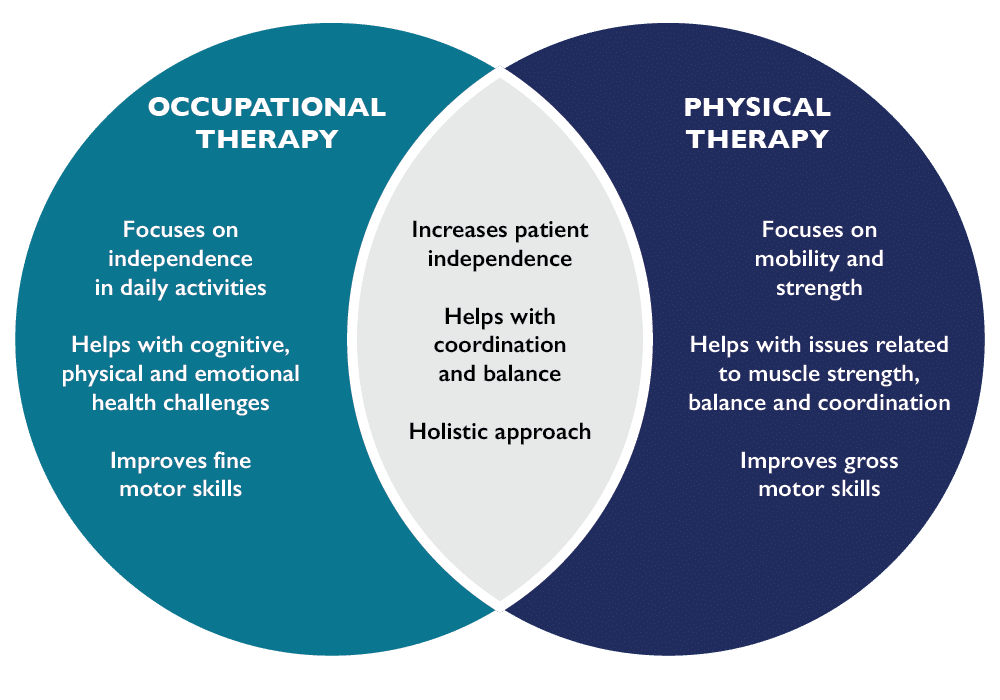
The confusion starts because both therapies work on similar goals but approach them from completely different angles.
I spent years watching families get sent in circles between pediatricians, developmental pediatricians, and OTs because nobody could agree on where one service ended and the other began. The paperwork alone was exhausting. Here is what actually separates them in practice. Developmental therapy targets the foundational skills that children need to reach milestones. This includes cognition, communication, social-emotional development, and motor planning. A developmental therapist works on things like joint attention, symbolic play, early language comprehension, and how a child processes sensory information in a way that supports overall growth. The approach is typically therapy within a play-based framework. Sessions look less like drills and more like structured interaction where the therapist uses routines, games, and guided activities to scaffold development. It is broader in scope and often more concerned with developmental delays than with specific functional tasks.
When to choose Developmental Therapy over Occupational Therapy
If a child has global developmental delays, autism spectrum disorder with significant social-communication deficits, or is falling behind across multiple developmental domains, developmental therapy is usually the better starting point. It treats the whole developmental picture rather than isolating individual skills. Occupational therapy is focused on functional independence. The central question an OT asks is whether a person can complete the activities they need or want to do during their day. This covers fine motor coordination, self-care routines like dressing and feeding, handwriting, sensory processing that interferes with daily tasks, and environmental modifications. An OT session might look like working on buttoning a shirt, using utensils, managing a sensory diet, improving pencil grip, or reorganizing a classroom so a child can focus. The work is task-oriented and very practical. If it does not translate into something the person can do better in their daily routine, an OT typically will not pursue it.
Where the overlap creates real problems
The biggest friction point between Developmental Therapy Vs Occupational Therapy is sensory processing. Both disciplines address sensory issues, but they handle them differently. A developmental therapist might work on how sensory input affects a child's overall regulation and social engagement. An OT will design a specific sensory diet with weighted blankets, swinging, or proprioceptive input to improve task performance. Neither approach is wrong. They just serve different purposes in the same child's treatment plan. I ran into this exact problem with a seven-year-old who had been in both types of therapy for over a year with minimal progress. The developmental therapist was focusing on social communication through play. The OT was working on sensory modulation and fine motor skills. The kid could not connect because no one was coordinating the two plans. He was getting contradictory sensory strategies from each provider. The workaround was straightforward. I pulled both therapists into a single coordination call, aligned their goals around a shared activity schedule, and had them use the same sensory tools in the same way. Progress accelerated within three weeks. The therapies were not competing. They were just talking past each other.
Get the Full Details

Counter-intuitive things most people miss
First, developmental therapy is not a lesser or softer version of occupational therapy. It is a different discipline with its own certifications, frameworks, and evidence base. Calling it "just play therapy" is inaccurate and undermines the clinical reasoning behind the interventions. Second, occupational therapy does not only work with children. Adult OT is a massive field covering stroke rehabilitation, hand therapy, cognitive rehabilitation after brain injury, and workplace ergonomics. If you assume OT is only for kids, you are missing half the profession.
Limitations and when these therapies fall short
Developmental therapy requires significant parental involvement outside of sessions. The play-based strategies only generalize if caregivers apply similar techniques at home. Parents who cannot commit to that level of engagement often see slow or stalled progress, and the therapy alone will not compensate for that gap. Occupational therapy can become mechanically repetitive if the therapist is not careful. Some programs reduce OT to a series of fine motor worksheets and sensory tools without addressing the underlying functional goal. A child might have excellent pencil grip after six months of OT but still cannot write a coherent sentence because no one connected the fine motor work to the academic task. That is a failure of the program, not a failure of the discipline. Insurance coverage is another hard limitation. Many plans cover a limited number of occupational therapy sessions per year and often require extensive prior authorization for developmental therapy. Families frequently hit the session cap before meaningful progress is made. In those cases, home-based strategies and school-based accommodations become necessary supplements rather than optional additions.
How to decide which path to take
Start with a comprehensive evaluation from a developmental pediatrician or a pediatric neurologist. They can determine whether the primary deficits are developmental, functional, or both. If the child is struggling primarily with milestones like language, social interaction, and cognitive skills, developmental therapy should be the priority. If the child can meet most developmental expectations but cannot function independently in daily activities due to motor, sensory, or coordination challenges, occupational therapy is the clearer choice. When both are needed, which is common, insist on coordinated care. Separate providers working in isolation will waste time and money. Get written consent for communication between them. Share goals in writing. Check in monthly to adjust the plan. The difference between a coordinated approach and an uncoordinated one is usually the difference between meaningful progress and paying for two therapies that cancel each other out.