Why people stick with low carb when managing blood sugar
The most practical reason to try a low carb diet for diabetes isn't some dramatic transformation story. It's that carbohydrates directly raise blood glucose, and reducing them removes one of the biggest variables from the equation. When you eat less carbs, post-meal spikes drop, insulin requirements often fall, and the constant guessing game with medication dosing becomes slightly more predictable. That's the core mechanism. Everything else is detail. I've watched people nail down their numbers in two weeks simply by cutting out the obvious starches. But the real work starts after the easy wins run out. That's where most people hit a wall, not because the diet stops working, but because they haven't figured out what to eat instead of whatever they were used to eating before.
Understanding Diabetes And Low Carb Diet
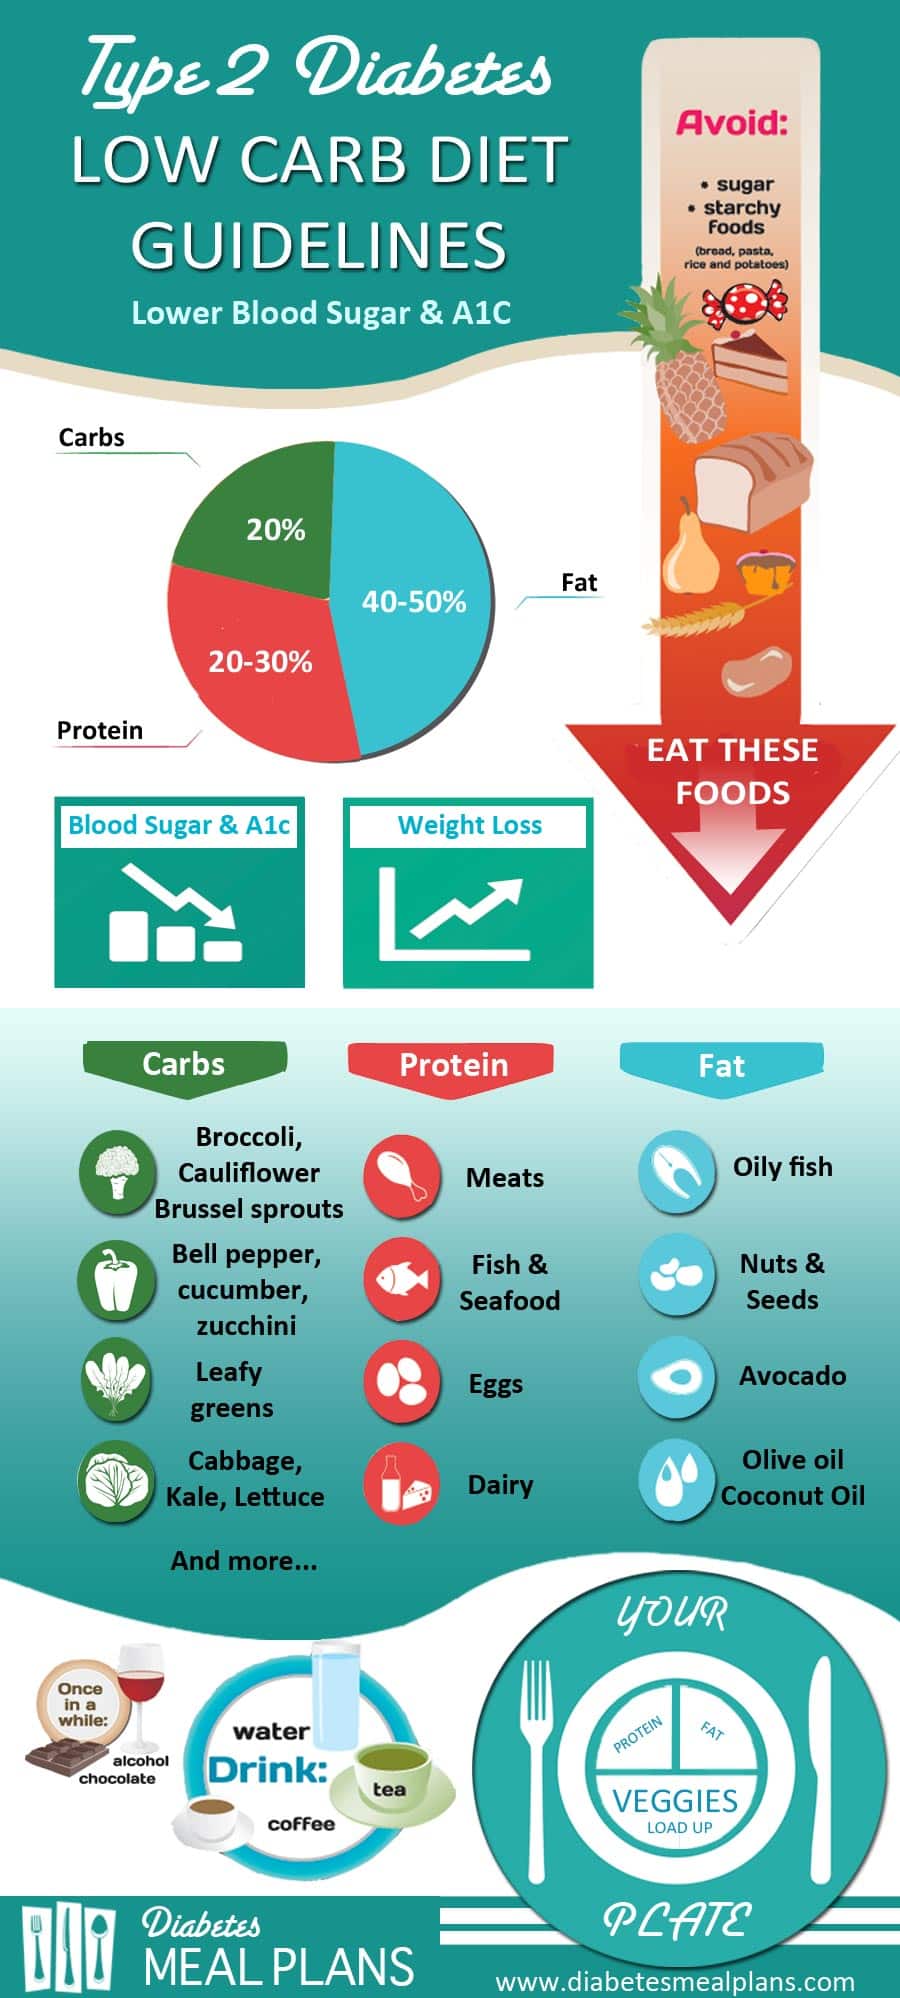
A low carb eating pattern for diabetes typically means keeping net carbohydrate intake somewhere between 50 and 130 grams per day, though some people go lower. Net carbs are total carbs minus fiber, since fiber doesn't significantly impact blood glucose. The exact number depends on your individual insulin resistance, activity level, and medication regimen. The key difference from a standard approach is that you're treating carbs as the primary lever to pull, not just one of many lifestyle factors. Protein and fat don't spike blood sugar nearly as aggressively. When you shift calories from carbs toward those macronutrients, your body has a much steadier glucose curve throughout the day. For someone on insulin or sulfonylureas, this shift is powerful and sometimes dangerous if you don't adjust medications accordingly. I can't stress that enough. Don't reduce your medication without talking to your doctor first. I once had a patient who dropped from 18 grams of carbs per day and then ignored her type 1 diabetes medication adjustments. She went into ketoacidosis at home because her basal insulin wasn't enough when she was running so low on glucose from food. Her ketones read 3.2 mmol/L and her blood sugar was 240 mg/dL. She spent two days in the ER. The workaround was straightforward in hindsight: anyone on insulin or secretagogues needs to check ketones regularly when going this low, and they need a clear sick-day plan that includes not skipping insulin even when eating almost nothing. I tell everyone now that carbohydrate restriction is a medication-modifier, not a replacement for medication management.
There are a few things beginners consistently get wrong. First, they count carbs but ignore the protein-to-carb ratio. Whey protein isolate and certain casein products can spike glucose in some people due to their insulinotropic effect, even though they have zero carbs. Second, they treat all non-starchy vegetables as interchangeable. Spinach has about 1 gram of net carb per cup raw. But peas, which people don't usually think of as starchy, have around 12 grams per cup cooked. Mistaking legumes for vegetables is one of the most common budget errors on this plan. A more advanced nuance that most guides skip is the dawn phenomenon and its interaction with low carb intake. Some people see their fasting glucose climb in the early morning despite eating very few carbs the previous day. This isn't the diet failing. It's hepatic glucose production driven by cortisol and growth hormone. The solution often isn't eating less at night but rather adjusting timing. For some people, a small protein snack before bed actually lowers morning fasting glucose by signaling the liver to reduce its glucose output. For others, it makes things worse. You have to test it and see what your own physiology does. The downsides are real and I'm not going to gloss over them. Low carb diets can cause temporary electrolyte imbalances in the first few weeks. Headaches, fatigue, and heart palpitations are common and usually resolve within 7 to 14 days if you're supplementing sodium, potassium, and magnesium adequately. The long-term risk profile for cardiovascular health on a very low carb diet depends heavily on what you fill your plate with. Saturated fat intake isn't inherently dangerous for everyone, but it raises LDL particle concentration in a significant subset of people with type 2 diabetes, and those people may benefit from emphasizing monounsaturated and omega-3 fats instead.
Get the Full Details

If you have advanced diabetic nephropathy, a higher protein intake could strain kidney function, so low carb may need to be modified or approached differently. In that case, a Mediterranean-style pattern with moderate carb reduction might be a safer intermediate step.
How to actually start without overcomplicating it
Pick a target range first. If you're new to this, 100 grams of net carbs per day is a reasonable starting point. It's low enough to see results but high enough that you won't feel deprived. After two weeks, reassess. If your average glucose has dropped and your cravings have decreased, you can try 70 grams. If you're struggling to stay on track at 100 grams, don't push lower yet. Consistency at 100 beats abandonment at 50. Map out three days of meals before you begin. Not a month. Three days. Write down every ingredient with its net carb count. Use a tracking app or a simple spreadsheet. The reason this matters is that most people severely underestimate carb content in sauces, dressings, and "healthy" foods like dried fruit, Greek yogurt, and whole grain breads. One serving of plain Greek yogurt can be 15 grams of carbs. One tablespoon of barbecue sauce is often 10 grams. These are not small numbers when you're operating at 70 grams per day. Stock your kitchen with replacements, not just restrictions. If you remove bread and rice but don't have anything satisfying in their place, you'll grab the old foods out of habit. Keep cauliflower rice, zucchini noodles, almond flour, and cloud bread ingredients on hand. Keep ready-to-eat proteins like hard-boiled eggs, deli turkey, and canned salmon available. The friction of deciding what to eat in the moment is what derails most attempts, not a lack of willpower.
Monitor your response data. Check fasting glucose daily and post-meal readings twice a week at different meal times. Record your numbers alongside what you ate. After 30 days, calculate your average glucose and look for patterns. Which meals cause the biggest spikes? Which ones barely move the needle? Let that data guide your next adjustments rather than following a rigid rule set. If you use a continuous glucose monitor, pay attention to the time-in-range metric rather than individual spike events. A diet that keeps you above 180 mg/dL for only 30 minutes after meals is performing better than one that occasionally spIKes to 200 but spends most of the day elevated. Context matters more than single data points. The transition period itself deserves attention. For the first 10 to 14 days, your body is adapting to using fewer immediate glucose sources. Energy levels may dip, focus might feel fuzzy, and exercise performance can temporarily decline. This is normal and usually passes. Hydration and electrolyte supplementation during this window make a noticeable difference. Aim for at least 2 to 3 liters of water daily and add a pinch of salt to your meals if you're not experiencing hypertension or fluid retention issues.

Practical meal structure that doesn't require counting everything
Once you understand carb content, you can simplify your approach. Build each meal around a protein source, a vegetable or two, and a fat source. Skip the carb counting for foods under 3 grams per serving since they won't meaningfully shift your daily total. Focus your counting effort on foods that actually move the needle: grains, legumes, starchy vegetables, fruits, dairy, and processed foods. A typical day at 70 grams might look like three eggs and spinach for breakfast with zero tracked carbs beyond the eggs. Lunch could be a large salad with chicken, olive oil, and cheese, adding roughly 5 grams from the vegetables. Dinner might be salmon with roasted Brussels sprouts and butter, around 8 grams. That leaves about 50 grams for snacks or flexibility items like berries or a small amount of nuts. This structure is flexible enough to adapt to different food preferences while keeping you in range without obsessive tracking. Restaurant eating is harder but manageable. Ask for substitutions: extra vegetables instead of fries, a side salad instead of bread, dressing on the side. Most protein-focused dishes at decent restaurants are naturally low carb. Avoid anything described as glazed, breaded, crispy, or glazed unless you specifically ask how it's prepared. Sugar is used in marinades and glazes more often than people realize.
Travel requires advance planning. Pack protein bars with low net carb counts, nuts, and single-serving cheese packets. Hotel minibars and airport food courts are hostile environments for this approach, and arriving hungry makes bad decisions almost inevitable. Eat a proper meal before you leave the house, even if it means taking longer to get to the airport. Alcohol complicates things. Dry wine has about 3 to 4 grams of carbs per glass. Hard liquor has negligible carbs but can delay hypoglycemia, especially if you're on insulin or sulfonylureas. Your liver prioritizes metabolizing alcohol over maintaining blood glucose, and that effect can last several hours. If you drink, do so with food present and monitor your glucose for at least six hours afterward.
When this approach stops working and what to do instead
Some people reach a plateau where further carb reduction doesn't produce additional improvements. Their numbers have stabilized and won't budge no matter how low they go. This is usually a signal to look at other factors: sleep quality, stress management, medication timing, or the possibility that protein intake is high enough to be driving gluconeogenesis. It's not uncommon for people who consume very high amounts of protein to see their fasting glucose rise slightly because excess amino acids can be converted to glucose by the liver. If you're at a plateau, adding resistance training or increasing daily step count often moves the needle more than further dietary restriction. Exercise improves insulin sensitivity through mechanisms that are independent of carbohydrate intake. For people who already eat very few carbs, the marginal benefit of cutting even further is small compared to the marginal benefit of adding movement. There's also a group of people for whom low carb isn't sustainable long-term, and that's fine. Adherence matters more than the perfect protocol. If you enjoy a moderate carb diet with whole grains, legumes, and fruits and your numbers are stable, there's no compelling reason to force yourself into a low carb pattern you dislike. The best diet is the one you can maintain consistently while keeping your glucose targets in range.

If you decide to proceed and want a resource to reference, the American Diabetes Association publishes position statements on carbohydrate management that cover this approach in detail. Their 2024 standards of care note that low carbohydrate eating patterns can be effective for short-term glycemic improvement, though they recommend individualized approaches and ongoing monitoring. Professional guidance remains important, especially if you're managing medication alongside dietary changes.