Getting Type 2 Diabetes Management Under Control
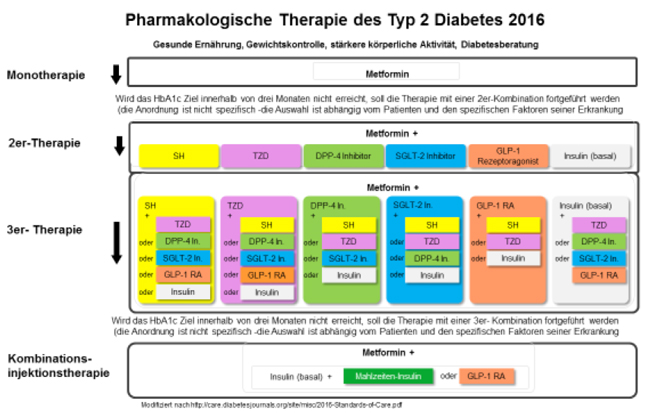
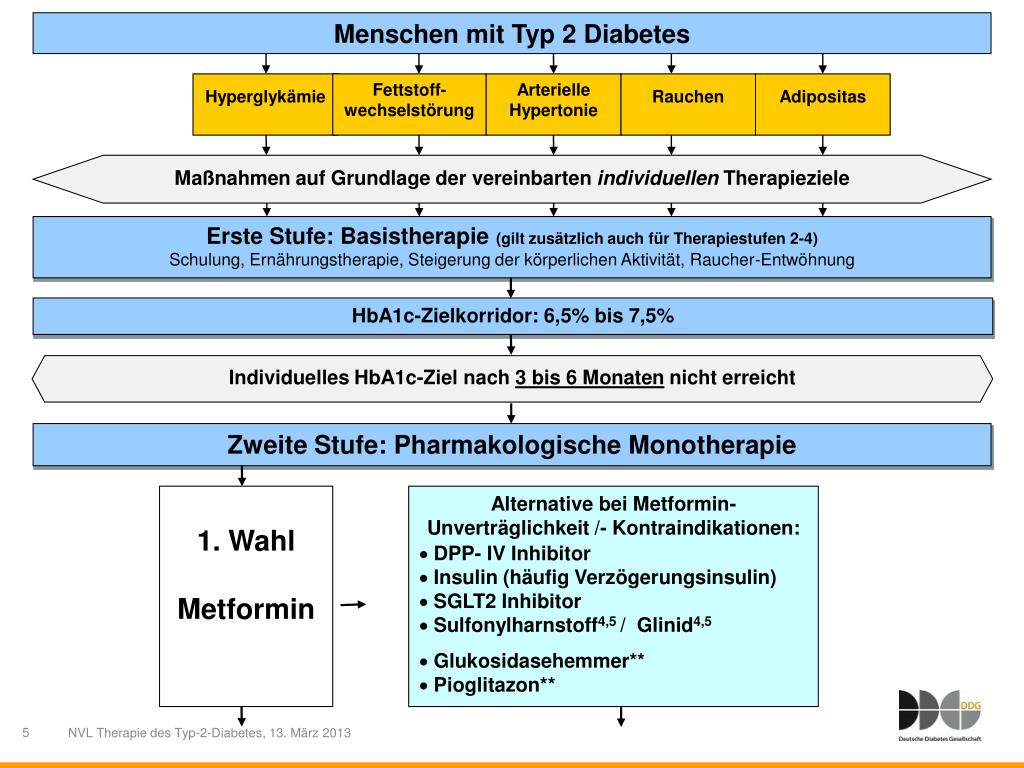
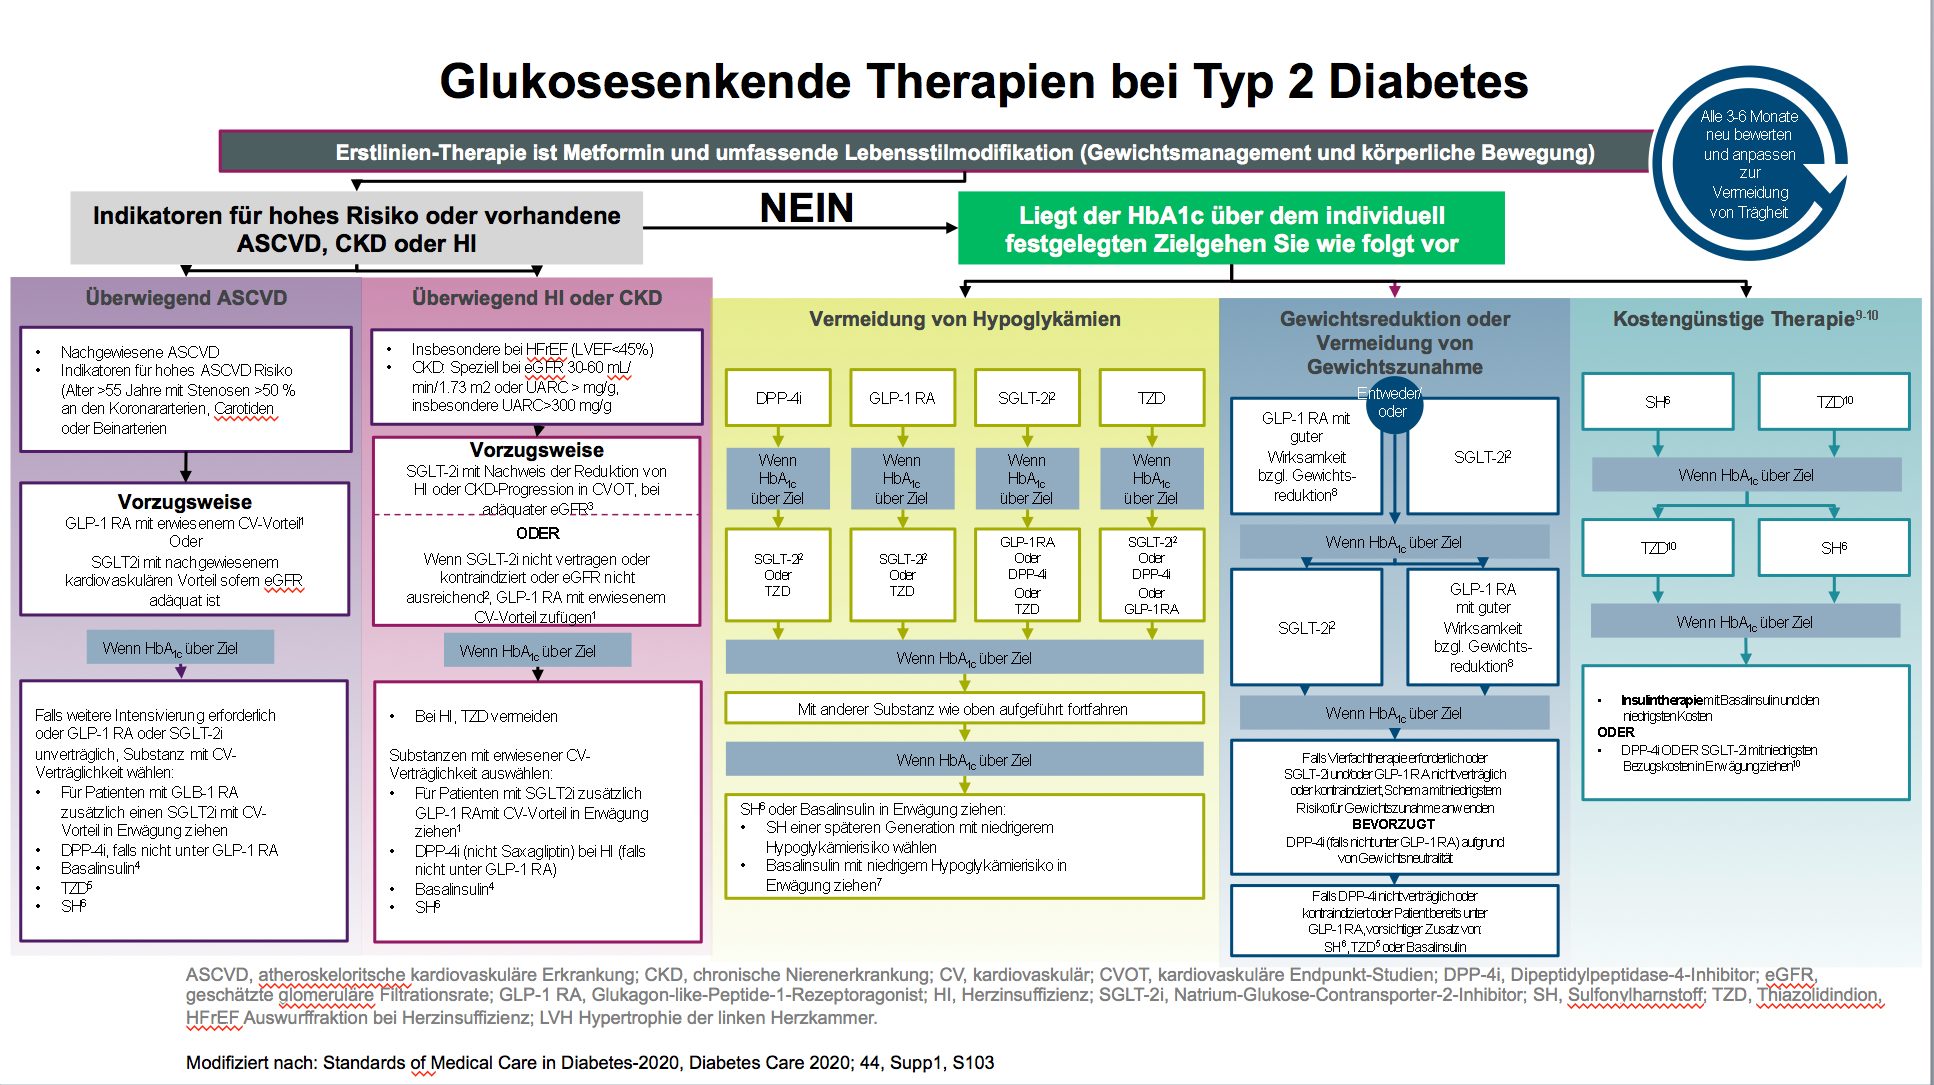
I used to work in a diabetes clinic for about eight years before moving into research. What I learned there is that most patients don't actually need their treatment changed very often. They need it explained to them properly, and then they need to stick with it. The problem is that sticking with it is harder than people think, especially when the medication does something that makes you feel worse before it makes you feel better. Metformin is still the first-line therapy, and for good reason. It lowers hepatic glucose production by inhibiting gluconeogenesis and improves insulin sensitivity in peripheral tissues. The typical starting dose is 500 mg once daily with the evening meal, then you titrate up by 500 mg per week until you reach 1500 to 2000 mg per day in divided doses. Extended-release formulations reduce gastrointestinal side effects significantly, which is the main reason people stop taking it in the first place. About 30 percent of patients on immediate-release metformin report diarrhea or nausea severe enough to discontinue. With XR versions, that drops to roughly 12 percent. It's not dramatic but it's enough to matter over the long term.
Diabetes Typ 2 Therapie: What Actually Changes Your Numbers
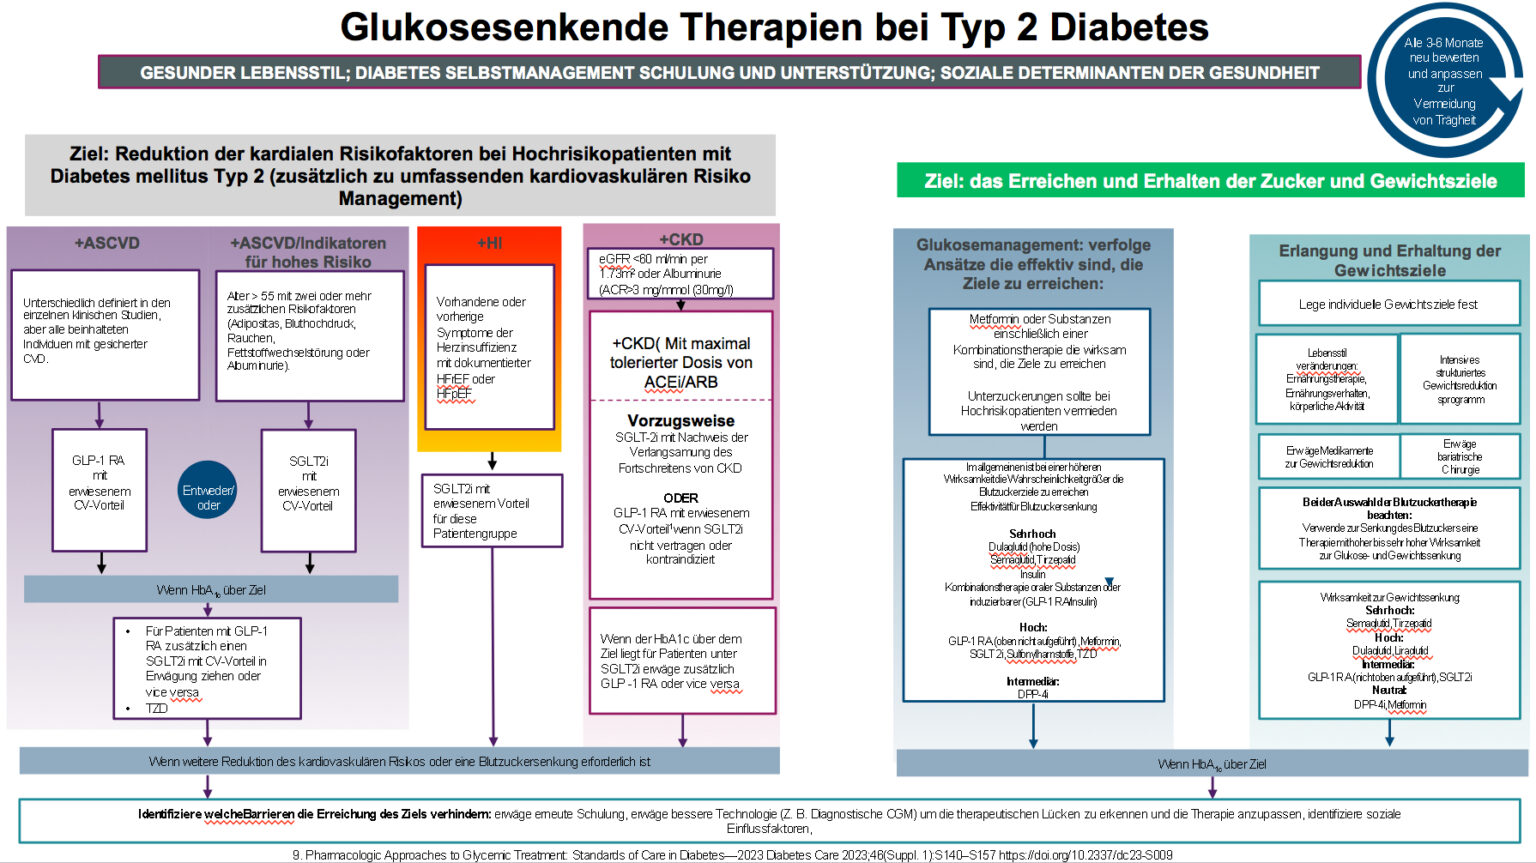
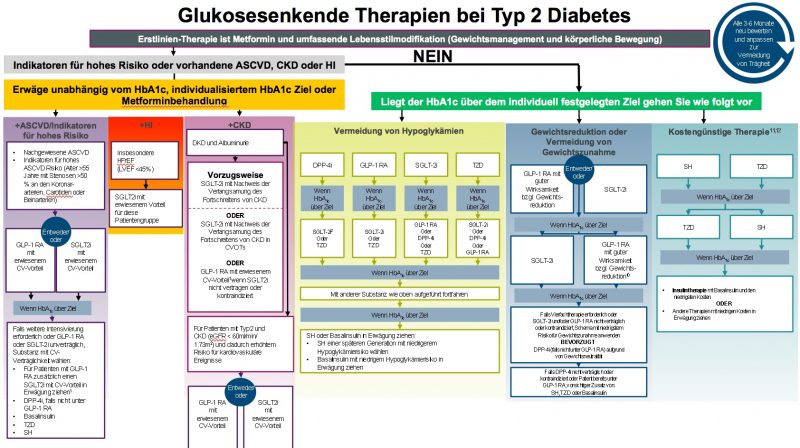
Sulfonylureas like glimepiride and glibenclamide are cheap and effective at lowering HbA1c, usually by another 0.8 to 1.2 percent on top of metformin. But they cause hypoglycemia in about 20 to 30 percent of patients over a year, and they promote weight gain averaging 2 to 4 kilograms. In practice, I saw patients who were perfectly stable on metformin alone and then got put on a sulfonylurea because their numbers hadn't dropped enough fast. They came back three months later with repeated lows and gained weight. We switched them to a DPP-4 inhibitor instead. The A1C benefit was smaller, maybe 0.5 to 0.8 percent, but they had no hypoglycemia risk and no weight gain. That trade-off is worth considering from the start, not after the patient has already had a bad experience. SGLT2 inhibitors are another class that gets overhyped in patient education materials. Empagliflozin and dapagliflozin lower A1C by roughly 0.5 to 1.0 percent and cause modest weight loss of 2 to 3 kilograms. Their real value isn't in glucose control. It's in cardiovascular and renal protection. The EMPA-REG OUTCOME trial showed a 38 percent reduction in cardiovascular death with empagliflozin in patients who already had established cardiovascular disease. Dapagliflozin showed similar benefits in the DELIVER trial for heart failure patients, including those without diabetes. If your patient has coexisting cardiovascular disease or chronic kidney disease with albuminuria, an SGLT2 inhibitor should be part of the treatment plan early regardless of A1C. That's not off-label use. That's guideline-recommended care. The downside is genital mycotic infections in about 5 to 10 percent of women and roughly 1 to 3 percent of men, plus a small increased risk of euglycemic diabetic ketoacidosis, particularly during acute illness or surgery. GLP-1 receptor agonists like semaglutide and liraglutide are currently the most effective single agents for lowering A1C, typically reducing it by 1.0 to 1.8 percent. They also produce meaningful weight loss, usually 4 to 8 kilograms depending on the agent and dose. Semaglutide at 2.4 mg weekly showed an average 15 percent body weight reduction in the STEP trials, though those patients didn't all have diabetes. At the lower doses approved for type 2 diabetes, the weight loss is more in the 5 to 8 percent range. The injection fatigue is real though. I had a patient who tolerated liraglutide fine for two years and then stopped because she was tired of injecting herself every day. She switched to oral semaglutide and was happier, but the GI side effects were worse on that one. Both require slow titration. Starting at the full dose guarantees nausea and vomiting in most people.
I ran into a specific edge case a few years back that I still think about. A patient on metformin, a sulfonylurea, and basal insulin had persistently elevated postprandial glucose spikes despite fasting numbers being acceptable. Her A1C was around 7.8 percent. We added a rapid-acting GLP-1 analog. Within two weeks her post-meal readings normalized and she actually lost three kilograms. But she developed gastroparesis-like symptoms, early satiety and nausea after even small meals. We cut the GLP-1 dose in half and split the timing of her meals, eating smaller amounts more frequently. It worked, but it took six weeks to dial in. The point is that adding agents sounds straightforward in the guidelines. In practice, the interactions between delayed gastric emptying, existing medication effects, and individual gut sensitivity create problems that aren't covered in any algorithm.
Get the Full Details

Monitoring and Adjusting Treatment
HbA1c testing every three to six months is standard. The target is generally below 7.0 percent for most non-pregnant adults, though some patients benefit from a tighter target below 6.5 percent if they can achieve it without hypoglycemia. Elderly patients or those with significant comorbidities should aim for something looser, maybe 7.5 to 8.0 percent. The evidence doesn't support aggressive control in those populations and the hypoglycemia risk outweighs any benefit. Fasting glucose targets usually sit between 80 and 130 mg/dL, and postprandial targets below 180 mg/dL at two hours after a meal. Continuous glucose monitoring is becoming more common even for type 2 patients on oral agents alone, though insurance coverage varies widely. Time in range, meaning the percentage of readings between 70 and 180 mg/dL, is a useful metric that many patients find more intuitive than A1C. A TIR above 70 percent correlates reasonably well with an A1C below 7 percent. Kidney function needs monitoring at least annually. Metformin should be withheld if eGFR falls below 30 mL/min per 1.73 m² and dose-reduced if it's between 30 and 45. SGLT2 inhibitors also need adjustment based on renal function, and their renal protective effects are most pronounced in patients with moderate chronic kidney disease. Liver enzymes should be checked at baseline and periodically, since nonalcoholic fatty liver disease is common in type 2 diabetes and can affect medication metabolism.
Baseline screening for complications should happen at diagnosis for type 2 diabetes since the disease is often present for years before detection. That means dilated eye exams, urine albumin-to-creatinine ratio, foot exams, and lipid panels. Blood pressure should be below 130 over 80 mmHg if it can be achieved safely. Statin therapy is recommended for almost all diabetic patients over 40 regardless of baseline LDL, unless contraindicated.
When Standard Therapy Fails
Not everyone responds to the usual stepwise approach. Some patients have significant beta-cell dysfunction at diagnosis and need insulin earlier than expected. Others develop secondary failure on oral agents within a few years. There's no shame in moving to injectable therapy or insulin. The data shows that delaying insulin in patients who clearly need it just increases the risk of complications from prolonged hyperglycemia. I've seen patients who refused insulin for two years because they thought it meant they had failed at managing their diabetes. Their A1C drifted to 9 or 10 percent and they developed peripheral neuropathy and retinopathy that was already advanced. Insulin isn't a last resort. It's a tool, and using it appropriately is better than letting glucose stay uncontrolled. Bariatric surgery deserves mention as an option for obese patients with type 2 diabetes. Remission rates after Roux-en-Y gastric bypass or sleeve gastrectomy are substantial, ranging from 40 to 80 percent depending on the study and how remission is defined. Even when remission doesn't occur, most patients see dramatic improvements in glucose control and can reduce or eliminate medications. The procedure carries its own risks, including nutritional deficiencies and surgical complications, so patient selection matters. But for the right candidate, it changes the disease trajectory in a way that no medication currently can. Lifestyle intervention remains foundational regardless of what medications are prescribed. Weight loss of just 5 to 7 percent of body weight improves insulin sensitivity measurably. Physical activity, especially resistance training combined with aerobic exercise, improves glucose uptake independent of weight loss. But expecting lifestyle changes alone to control type 2 diabetes in someone who already needs medication is unrealistic. Diet and exercise help, sometimes a lot, but they rarely replace the need for pharmacotherapy in established disease. Saying otherwise does patients a disservice because it sets them up to feel like failures when the lifestyle changes alone don't produce the results they were promised.