CT and MRI Protocols for Head and Neck Imaging: A Practical Guide
Most places handle head and neck imaging with two different modalities, and they don't always know which one they actually need. CT gets ordered when speed matters or when you're looking at bone. MRI is the right call for soft tissue detail, posterior fossa work, or when radiation exposure is a concern. The problem isn't picking between them—that part's straightforward. The problem is what happens after that decision, when you're actually building the protocol. I've spent years troubleshooting why studies come back nondiagnostic, and it's almost never a hardware issue. It's protocol misconfiguration. A CTA of the head can miss an aneurysm smaller than 3mm if the bolus timing is off by eight seconds. A neck MRI without proper fat suppression will make a schwannoma look like noise. These aren't edge cases. They happen every day.
When to Order Diagnostic Imaging Head And Neck Studies
The basic rule of thumb most residents learn: head trauma, stroke code, acute neurological deficit—start with non-contrast CT. It's fast, it's available at 2 AM, and it catches hemorrhage better than MRI in the hyperacute phase. If the CT is negative and suspicion for ischemic stroke remains, you go straight to MRI with DWI. Don't sit on it waiting for a second opinion. Time is brain tissue. For the neck, the calculus shifts. Chronic neck mass, dysphagia, laryngeal symptoms, suspected malignancy—MRI or contrast-enhanced CT depending on what you're chasing. If you're evaluating the thyroid, go MRI if the patient can cooperate for twenty minutes. If you're looking at bony erosion from a recurrent tumor, CT wins every time. The parotid gland, the submandibular space, the prevertebral chain—each of these has a preferred modality based on what you're actually trying to see. I once had a case where a radiologist ordered a standard neck CT with 5mm cuts for what turned out to be a paraganglioma. The lesion was there, visible on review, but it had been partially volume-averaged through the slice thickness. We re-scanned with 2mm cuts and the vascular supply became clear. The original read came back as "no definite mass." That's a common failure mode. When you're imaging the head and neck, 5mm is too thick for anything smaller than a lymph node in level II. Go 3mm or thinner if the scanner allows it.
CT Protocol Configuration
A standard non-contrast head CT uses a 0.625mm detector collimation, 120 kVp, and an automated exposure control that targets a CT dose index around 45 mGy for an average adult head. If you're working with a pediatric patient under ten years old, drop the kVp to 80 or use iterative reconstruction to keep the dose down without sacrificing the ability to detect acute blood. CTA head requires a contrast bolus tracking setup. Set your region of interest in the basilar artery or the mid-internal carotid. The trigger threshold should be 150 Hounsfield units. Without bolus tracking, you're guessing at injection timing, and the guess is usually wrong by enough to miss a vascular lesion. Use a power injector at 4-5 mL/s with a 50 mL saline chase. The chase matters—it clears the contrast out of the arm veins so you don't get streak artifact from venous contamination in the venous phase. For neck CTA, the same principles apply but the vascular territory is different. You need to cover from the aortic arch through the skull base, which means a longer scan range and a slower injection rate to ensure uniform opacification. I typically run 3.5 mL/s instead of 5 mL/s for the neck because the vessels are smaller and the flow dynamics are different. The contrast volume stays the same—80 to 100 mL—but the flow rate changes affect how sharply the bolus is defined across that longer field of view.
Get the Full Details
MRI Protocol Parameters
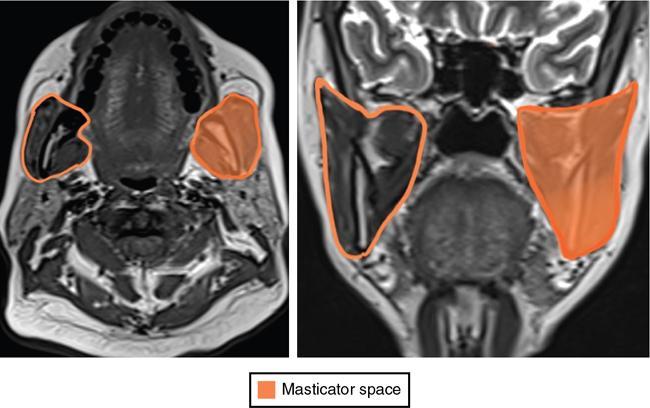
A brain MRI without a defined protocol is just a collection of pretty pictures with no diagnostic structure. Here's what a practical study looks like: axial T1, axial T2, FLAIR, DWI with ADC mapping, and then contrast-enhanced T1 with fat saturation if there's a reason to suspect pathology. That's the core. Everything else is conditional. FLAIR is non-negotiable for posterior fossa evaluation. The cerebellum and brainstem are difficult to image on T2 alone because CSF pulsation creates artifact. FLAIR suppresses the CSF signal and makes even small lesions in the brainstem stand out. I've lost count of the number of MS plaques I've seen missed on T2-only protocols because the technologist cut corners on the FLAIR sequence. For the neck, T2-weighted fat-saturated images in the axial and coronal planes are the workhorse. Fat saturation is critical here—the subcutaneous fat and marrow fat in the cervical spine will otherwise overwhelm the soft tissue detail you're trying to see. If your fat sat isn't working properly, check the shim. Most of the time the issue is magnetic field inhomogeneity, not a sequence problem. A good shim takes thirty seconds and it makes the difference between a diagnostic and non-diagnostic study.
Sagittal STIR or T2 fat-sat is essential for evaluating the cervical spine. I see too many studies where this sequence is omitted because the referring physician didn't specifically request it, but the pathology is right there in the cord if someone had taken the image. Advocate for the complete protocol. It takes four minutes and it catches things that would otherwise require a second study.
Common Pitfalls and How to Avoid Them
Motion artifact is the single biggest source of non-diagnostic studies in head and neck imaging. Dental hardware creates streak artifact on CT that can completely obscure the anterior cranial fossa. If the clinical question involves the frontal lobes or the paranasal sinuses, consider MRI instead. CT will show you the hardware; it won't show you what's behind it. On MRI, patient motion during DWI is catastrophic. A single bad b1000 image can make you miss an acute infarct. If the patient is unable to cooperate, reduce the echo train length and accept a slightly lower resolution rather than getting a motion-blurred study that requires repetition. Repeat DWI takes longer than you think and delays diagnosis. Contrast reactions are rare but they happen. The pre-medication protocols most places use—dexamethasone 20 mg at 13 hours and 7 hours before, plus diphenhydramine 50 mg one hour before—are adequate for patients with a known prior reaction. For patients with no history, standard monitoring is sufficient. The old practice of ordering the study on a Monday to avoid weekend staffing issues is outdated. The data doesn't support it, and it just delays diagnosis unnecessarily.

I had a patient last year with a cavernous sinus meningioma that was completely missed on three prior CT scans. The lesion was isodense to brain on non-contrast CT and barely perceptible on contrast-enhanced studies because the radiologists were reading through 5mm reformats instead of the thin-section original images. When we got the MRI with thin-section T1 fat-sat post-contrast, the tumor was obvious. It was there all along. This is why protocol matters more than equipment. A 1.5T scanner with a proper protocol will outperform a 3T scanner with a lazy one.
Post-Processing and Reconstruction
MIP reconstructions are standard for CTA and they should be generated with a slab thickness that matches your clinical question. For aneurysm detection, 3mm slabs work well. For mapping vascular stenosis in the carotid bifurcation, go thinner—2mm or even 1mm if your workstation supports it. The default MIP thickness on most scanners is too thick for detailed vascular assessment and it creates the illusion of patency where there is significant stenosis. Volumetric rendering for surgical planning is useful but overrated. It looks impressive in presentations and the referrals love it, but for actual surgical navigation, thin-slab MIPs in multiple planes give the surgeon more actionable information. The 3D model smooths over calcifications and narrow segments that matter for clip placement and stent sizing.
Contrast Considerations
Renal function matters more than people admit. eGFR below 30 is the cutoff where the risk of nephrogenic systemic fibrosis becomes clinically significant with gadolinium-based agents. If you're using a macrocyclic agent—which you should be, because they're far safer than the linear agents—the risk is much lower even at reduced eGFR, but you still need to document the value and weigh the benefit against the risk. For iodinated contrast in CT, the threshold is generally eGFR below 45 for routine studies. Hydration protocols are often ignored. A liter of IV normal saline before and after contrast administration in patients with borderline renal function reduces the incidence of contrast-induced nephropathy by roughly half. It's not glamorous and it adds fifteen minutes to the workflow, but it prevents complications that cost far more in downstream care. I push for this on any patient over sixty-five with a creatinine that's borderline high. It's a small step that makes a measurable difference.