How to Actually Draw Pulmonary and Systemic Circulation Diagrams That Don't Confuse Everyone
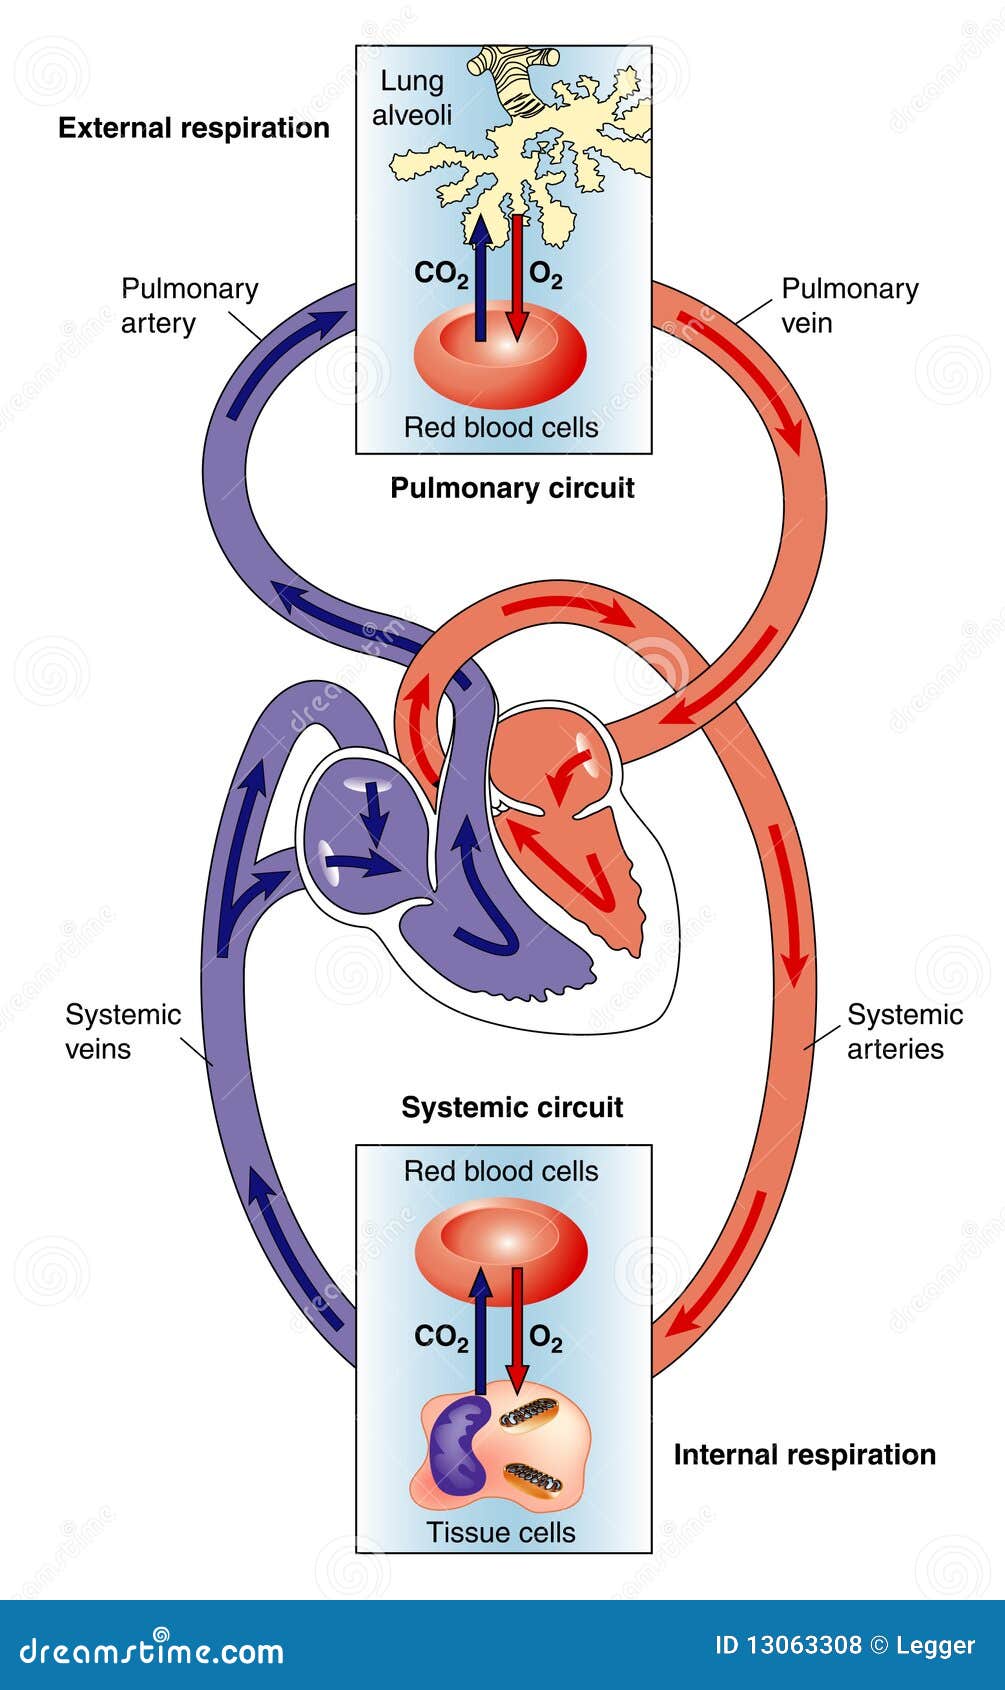
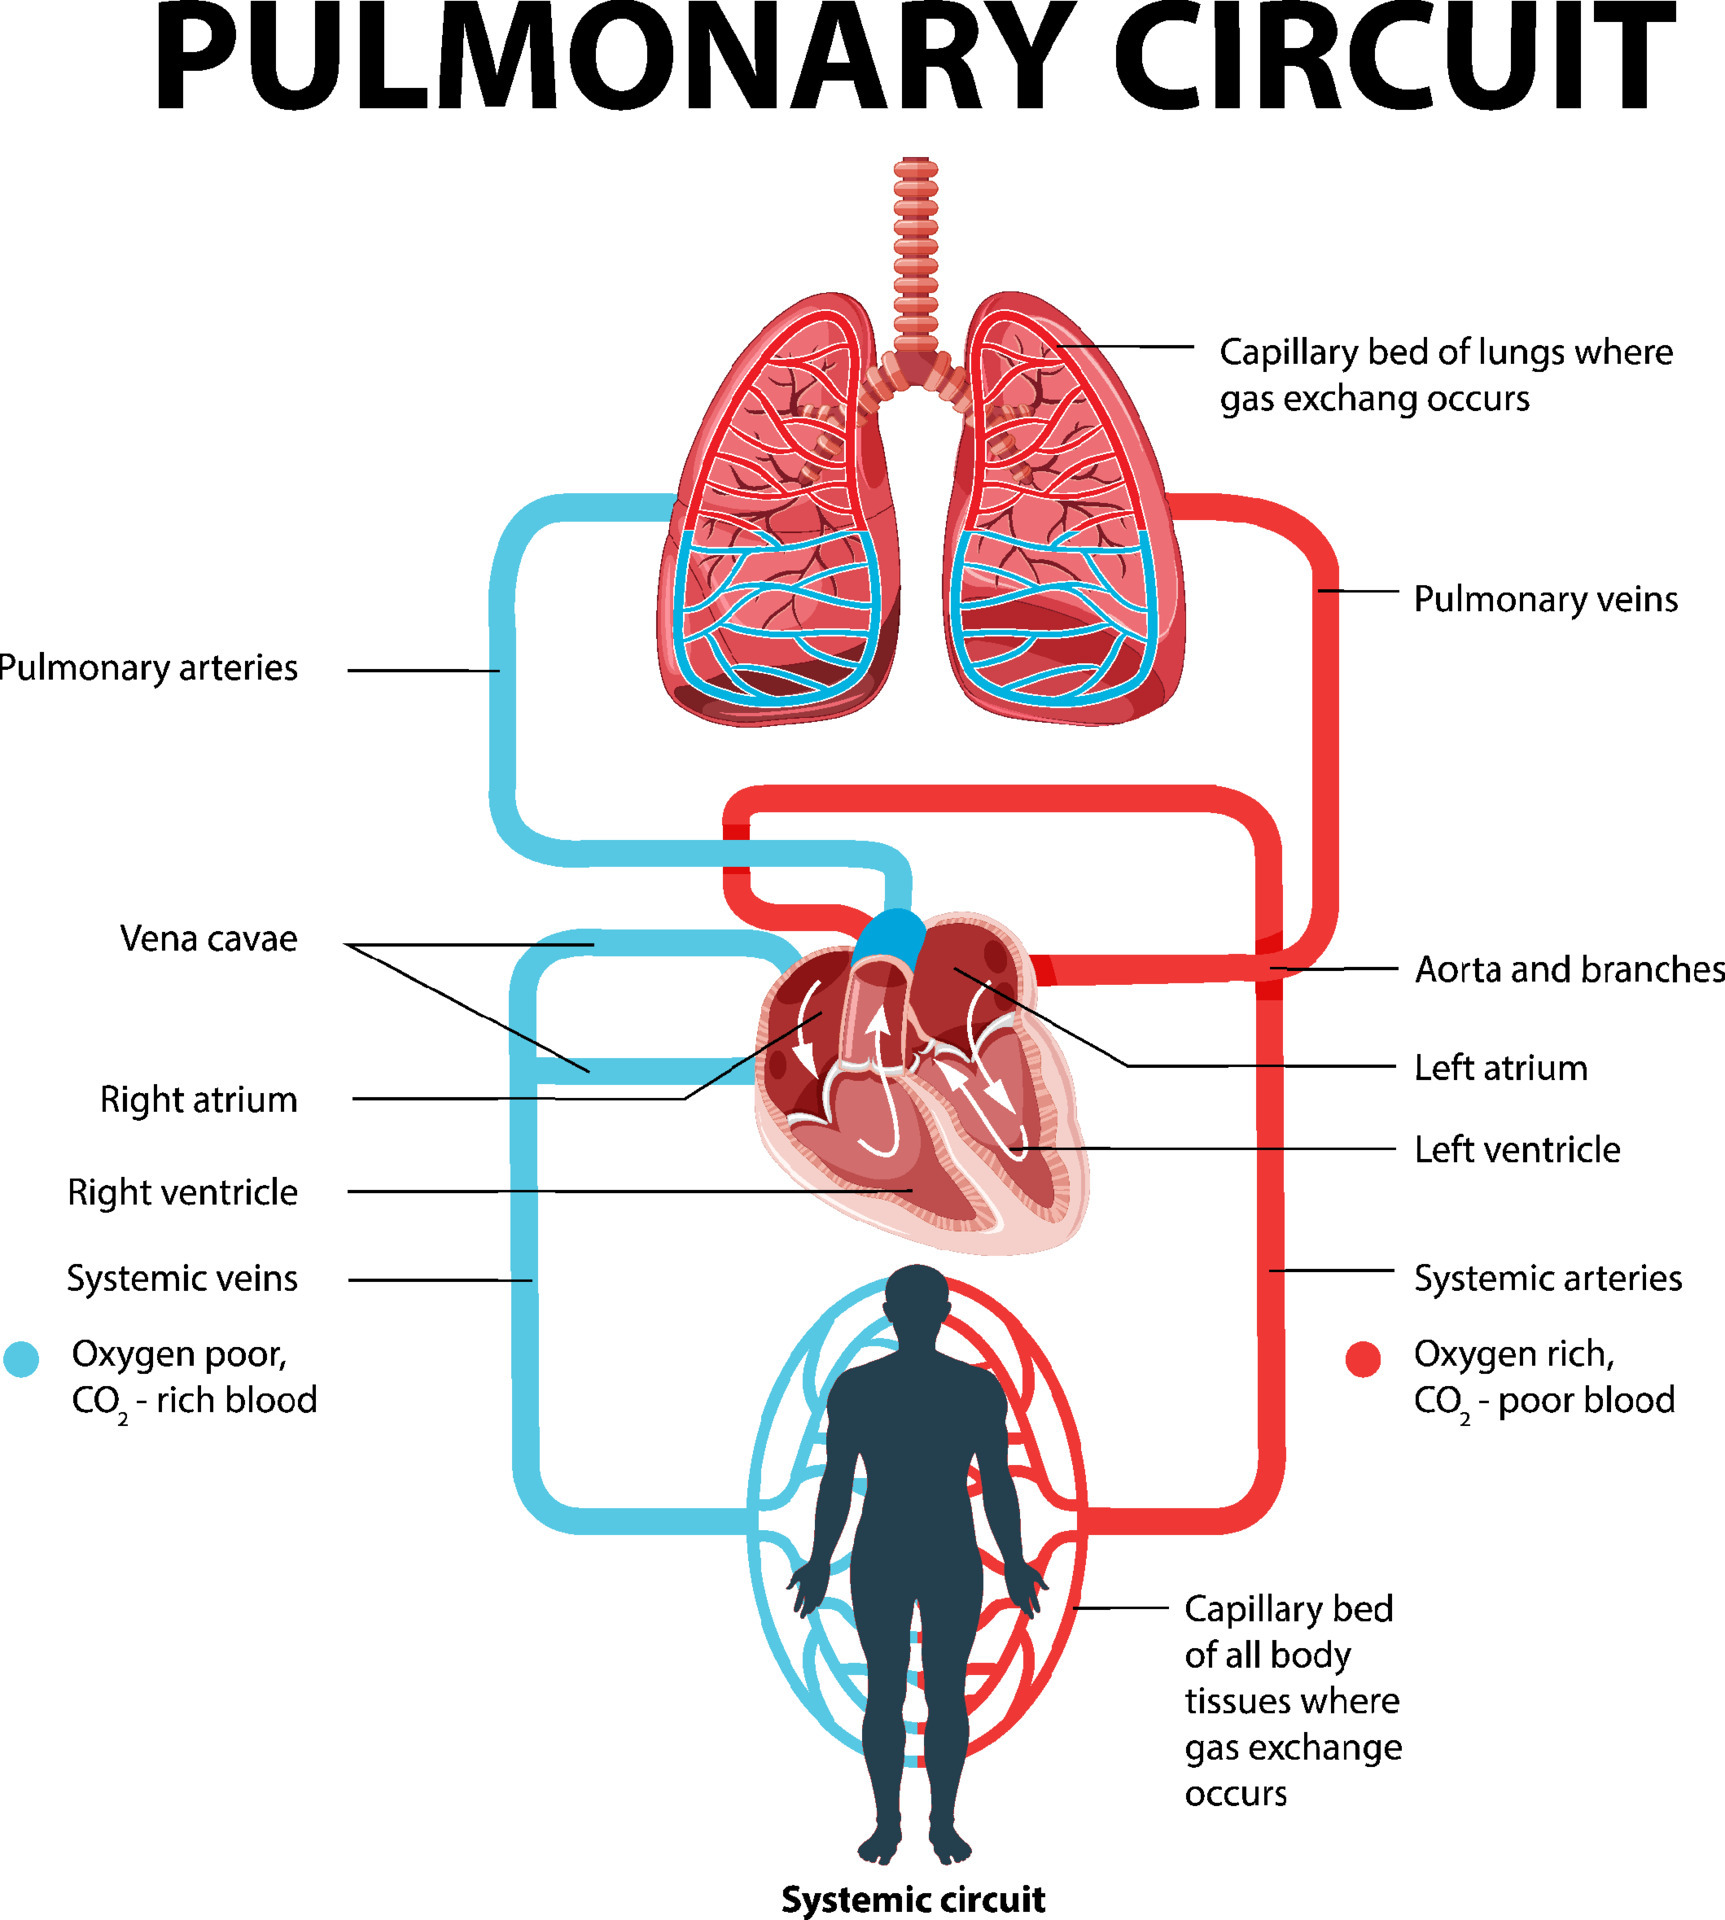
Most people get confused when trying to draw these because they treat the heart as two separate pumps instead of one connected organ. I spent three years in cardiothoracic surgery rotation before I stopped making the same mistakes my residents kept making on whiteboards. Start with a box for the heart. Divide it into four chambers using a vertical line for the septum and a horizontal line for the valves. Label them properly: right atrium, right ventricle, left atrium, left ventricle. The right side goes on the diagram's left because you're looking at the patient face-to-face. I know that feels backwards. It is backwards. Get used to it. Draw the lungs as two simple shapes on either side. Not detailed alveoli. Just lobes. The pulmonary circuit is short and low-pressure. The systemic circuit is long and high-pressure. Your lines should reflect this. Thick lines for systemic, thin lines for pulmonary. Color matters too. Blue for deoxygenated, red for oxygenated. Keep it consistent or nobody will follow your diagram.
The vena cavae enter the right atrium. The pulmonary veins enter the left atrium. Four veins, not two. Beginners always draw two big veins coming out of each lung. There are four. Superior and inferior vena cava on the right side. Pulmonary veins in pairs on the left. Get this right or your anatomy is wrong.
The valves and why they matter on paper
Tricuspid between right atrium and right ventricle. Mitral between left atrium and left ventricle. Pulmonary valve before the pulmonary artery. Aortic valve before the aorta. Draw them as simple arcs or flaps. Don't overcomplicate. The key point is direction. Blood flows one way. Arrows show this. No arrows means nobody knows which direction you're talking about. I had a med student once draw the entire diagram with the pulmonary artery coming out of the left ventricle. He confused transposition of the great arteries with normal anatomy. We spent twenty minutes going through it again. The fix was simple. Trace each vessel back to its chamber. If the vessel doesn't match the chamber name, redraw it.
Get the Full Details

Common mistakes that waste everyone's time
Drawing the aorta as a straight line coming out of the top. It arcs. It goes up, curves over, and comes down on the left side. The arch is important. It gives rise to the brachiocephalic, common carotid, and subclavian arteries. You don't need to draw all of those, but show the curve. A straight tube is wrong. Forgetting the coronary circulation. The right and left coronary arteries branch off the aorta right after it leaves the left ventricle. They supply the heart muscle itself. Most textbook diagrams skip this. I include a thin loop around the ventricles because people always ask where the heart gets its blood from. Mixing up pulmonary artery and pulmonary vein function. The pulmonary artery carries deoxygenated blood. It's the only artery that does this. The pulmonary veins carry oxygenated blood. They're the only veins that do this. Call them out explicitly in your legend. Nobody remembers this without being reminded.
Advanced nuance: The pressure gradient across the septum
Here's something most diagrams miss. The left ventricle works against much higher pressure than the right. Systemic vascular resistance is roughly ten times pulmonary vascular resistance. This means the left ventricular wall is about three times thicker. If you're drawing a cross-section, show this. A thick left ventricle and thin right ventricle tells the reader something important about function. I once worked with a professor who insisted on drawing both ventricles the same thickness. He said it was "cleaner." It was wrong. Patients with ventricular septal defects show this pressure difference clearly. The left side pushes harder. The diagram should reflect that reality.
Edge case: When the standard diagram fails you
Fetal circulation is different. The foramen ovale shunts blood from right atrium to left atrium. The ductus arteriosus connects pulmonary artery to aorta. If your audience needs to understand congenital heart defects, draw the fetal diagram too. Show the closures that happen after birth. The foramen ovale becomes the fossa ovalis. The ductus arteriosus becomes the ligamentum arteriosum. Without this, people think the adult heart is the only way it can be. I encountered a resident who couldn't understand Eisenmenger syndrome because he only knew the adult diagram. Once I showed him the fetal pattern and explained what happens when pulmonary hypertension reverses the shunt, everything clicked. He spent two days reviewing congenital defects after that.

Tools and materials that actually work
Paper and pen. Not fancy. A ruler helps with straight lines. Colored pencils or markers make the blue-red distinction clear. Digital tools work too if you're comfortable with them. I've used PowerPoint, draw.io, and even Microsoft Paint for quick diagrams. The medium doesn't matter. The accuracy does. Time estimate. A clean hand-drawn diagram takes about fifteen minutes if you know the anatomy. Twenty minutes if you're double-checking vessel connections. Thirty minutes if you're adding the coronary circulation and fetal variations. Don't rush it. A bad diagram causes more confusion than no diagram.
What to do when you're stuck
Look at a real echocardiogram. Not a cartoon. A real ultrasound image from a patient. The chambers look different than textbooks show. The valves move. The blood flow is dynamic. This helps you understand why the static diagram looks the way it does. I keep a reference chart from my residency. It's worn. The colors are faded. It's hanging above my desk because I consult it more often than I'd like to admit. Even experts need reminders about vessel origins and chamber relationships. The diagrams in books are simplified. Real anatomy has variations. Yours should acknowledge this. Draw the diagram from memory first. Then check it against a reference. Then draw it again from memory. This process takes longer upfront but saves time later because you actually remember it. I've watched people trace diagrams dozens of times and still get the pulmonary veins and arteries confused on exams. The tracing doesn't teach. The recall does.