Labeling the Tract: What You Actually Need to Draw
Most textbook diagrams start at the nose and work down, which is fine for students but a terrible way to actually use a diagram for clinical or teaching purposes. I learned that the hard way when a med student came to me once with a hand-drawn version she'd copied from a site and asked why her anatomy professor kept marking it wrong. The diagram was technically correct. It just wasn't organized the way clinicians read it.
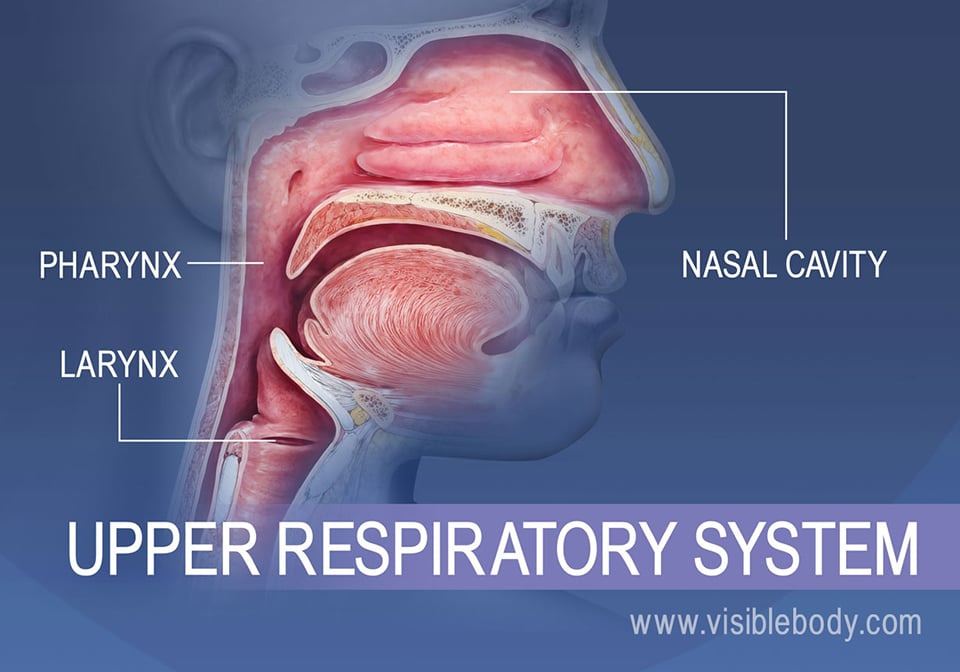
Here's what a useful Diagram Of Upper Respiratory System actually looks like when you're trying to use it rather than just memorize it.
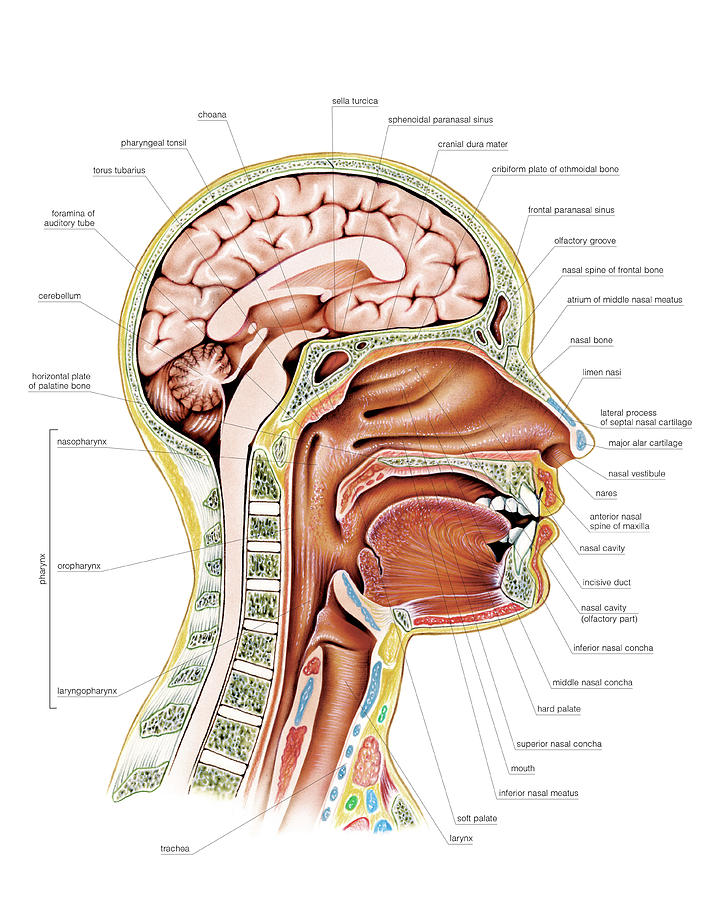
Start with the nasal cavity. That's where everything begins, but don't draw it as one empty space. Divide it with the nasal septum, label the superior, middle, and inferior nasal conchae separately. Those turbinates are where most people stop drawing, but they matter for airflow visualization. If you're shading the diagram to show air path, make the middle meatus the prominent channel. That's where the majority of inspired air actually travels in normal breathing. The inferior meatus gets labeled for the nasolacrimal duct. It's easy to skip that connection and then wonder why sinus drainage questions come up on exams.
Move to the paranasal sinuses. Frontal, maxillary, ethmoid, and sphenoid. Draw them as cavities adjacent to the nasal cavity, not floating above the head. I've seen too many diagrams place the frontal sinus like a bubble sitting on top of the skull with no anatomical relationship shown. That's misleading. The maxillary sinus should appear to open into the middle meatus. That ostium is tiny, about 2 to 3 millimeters, and it's the reason maxillary sinusitis is so common when that opening gets blocked.
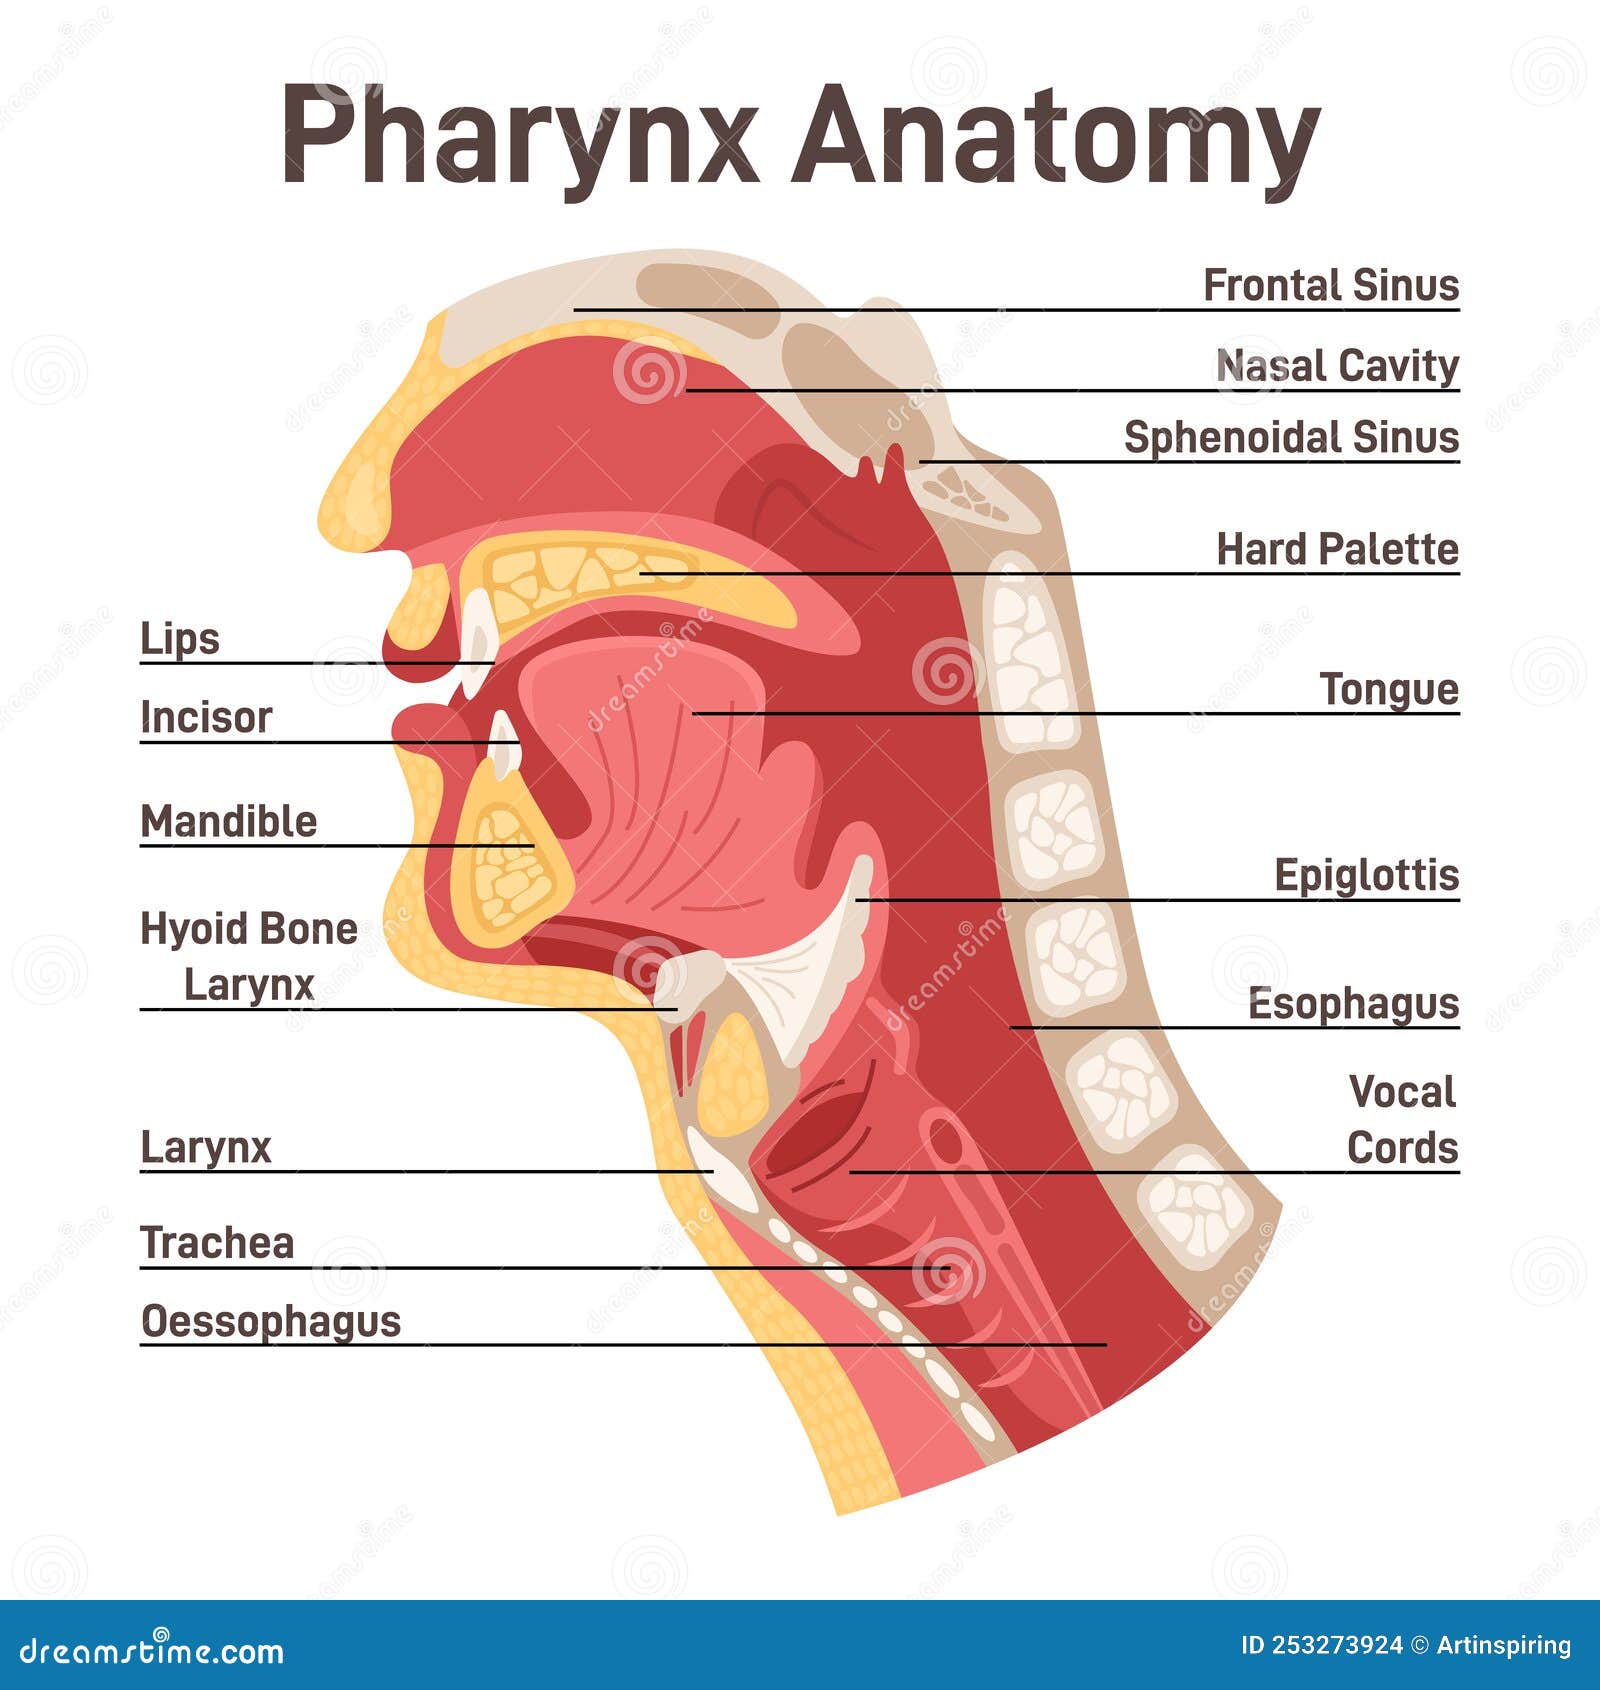
The pharynx comes next. Break it into three sections. Nasopharynx, oropharynx, and laryngopharynx. The nasopharynx sits behind the nasal cavity and contains the pharyngeal tonsil, also called the adenoid. The oropharynx is behind the oral cavity. The laryngopharynx connects down to the esophagus and larynx. Don't merge these. They have different clinical significance. The nasopharynx is where you'd look for an adenoid hypertrophy case. The oropharynx is where strep shows up. The laryngopharynx is where you worry about referral patterns from throat cancers.
Diagram Of Upper Respiratory System: Common Pitfalls and What to Fix
One specific problem I ran into repeatedly involves the larynx. People consistently draw the epiglottis as a wide flat flap that covers the entire laryngeal inlet. In reality, the epiglottis is more like a leaf-shaped cartilage that deflects air and food laterally toward the pyriform fossae. When you're drawing a diagram for teaching swallowing mechanics, this distinction matters because it explains why aspirated material tends to pool in the pyriform sinuses rather than going straight down the esophagus.
Another issue is the vocal folds. Label the true vocal cords and the ventricular folds separately. Most diagrams lump them together as "vocal cords." The true vocal folds are the lower pair and they produce sound. The false vocal folds sit above them and they're primarily protective. If you're diagramming this for a respiratory therapy class, make sure the glottis is identifiable as the space between the true vocal folds. That's the narrowest part of the adult upper airway and it's critical for understanding airway management.
For the laryngopharynx, show the esophageal opening posteriorly and the laryngeal inlet anteriorly. The relationship is often reversed in amateur drawings, which creates confusion about which structure leads where during deglutition.
The trachea marks the boundary between upper and lower respiratory. Some diagrams include the first few tracheal rings. Others stop at the cricoid cartilage. If you're drawing a complete upper respiratory diagram, include about three to four tracheal rings to show the C-shaped hyaline cartilage rings and the trachealis muscle posteriorly. Skip it if you want the diagram focused strictly on the upper tract. Either approach is valid. Pick one and stick with it.
If you need a reference file, searching "Diagram Of Upper Respiratory System PNG" or SVG on sites like OpenSnippets, BioRender, or even the Wikimedia Commons anatomy section will give you clean vector versions. BioRender has pre-made elements you can rearrange if you're building something custom. It takes about 10 minutes to assemble a decent labeled diagram there if you know which structures to pull.
I spent two weeks last year reworking a diagram for a local community college respiratory program because the existing one showed the right structures but had the left and right primary bronchi labeled identically, which confused first-year students into thinking both sides were symmetrical. They're not. The right main bronchus is wider, shorter, and more vertical. That asymmetry explains why aspirated foreign bodies lodge in the right lung far more often than the left. The diagram needed to show that angle difference explicitly. Once I corrected it, the incidence of that specific misconception in quiz results dropped noticeably over the next semester.
One thing diagrams never do well is show dynamic function. They show static anatomy. If you're using a diagram to teach about things like mucus transport, ciliary action, or the mucociliary escalator, you'll need supplementary visuals. The diagram is your anchor. It's not the whole lesson.
Gallery Diagram Of Upper Respiratory System
Upper Respiratory System Diagram
Upper Respiratory Tract Anatomy Of The Respiratory System Photographs
Upper Respiratory System with Diagram Diagram | Quizlet
What Is Upper Respiratory System
Upper Respiratory System | Respiratory Anatomy