What DBT Actually Looks Like in Practice
Most people encounter Dialectical Behavior Therapy Dbt For Borderline Personality Disorder after a crisis has already happened. They read about it in an article, hear a podcast recommendation, or get it suggested at a hospital discharge. The description on paper is clean. Interpersonal effectiveness, emotion regulation, distress tolerance, mindfulness. Four modules. Thirty weeks of group work. Individual therapy on top. It sounds manageable until you're actually sitting in that first session trying to understand why you're supposed to write down your emotions instead of just feeling them. The core problem DBT tries to solve is the gap between knowing what you should do in a moment of crisis and actually being able to do it. People with BPD often have detailed self-awareness. They can articulate exactly what triggers them, what makes things worse, and what would theoretically help. The disconnect is physiological. The nervous system gets hijacked before the prefrontal cortex has any chance to weigh in. DBT operates on that premise. It treats skills like a training program, not a conversation starter.
Learning Dialectical Behavior Therapy Dbt For Borderline Personality Disorder
I spent years running DBT groups and individual sessions, and the single most consistent failure point I saw was clients treating the diary card like a chore instead of a diagnostic tool. The diary card is supposed to track seven specific behaviors every day: suicidal ideation, self-harm, attempted suicide, acts directed at controlling anger, breaking treatment commitments, substance use, and impulsive behaviors across five categories like spending, sex, eating, drugs, and reckless driving. Most people fill it out once a week with vague entries. That defeats the entire purpose. You need daily granularity because emotions in BPD follow a trajectory. If you only capture the aftermath, you miss the ramp-up. The standard protocol assumes you have a certified DBT therapist. That's not always available. There are adaptations for group settings, for general mental health professionals who want to incorporate elements, and even for solo practitioners working with borderline patients. The key is fidelity to the model. DBT works because it's structured. When you start improvising based on what feels good in the session, you're doing emotion-focused therapy, not DBT. The distinction matters for outcomes. One thing people don't understand about the dialectical part is that it's not a debate technique. It's a philosophical stance. The therapist holds two truths at once: the client is doing the best they can, and they need to do better. The warmth without the pressure creates the conditions where behavior change actually sticks. I've seen therapists skip the validation because they thought the client needed a direct challenge. That backfires consistently. Validation isn't agreement. It's acknowledging the internal logic of someone's emotional response before asking them to reconsider their behavior.
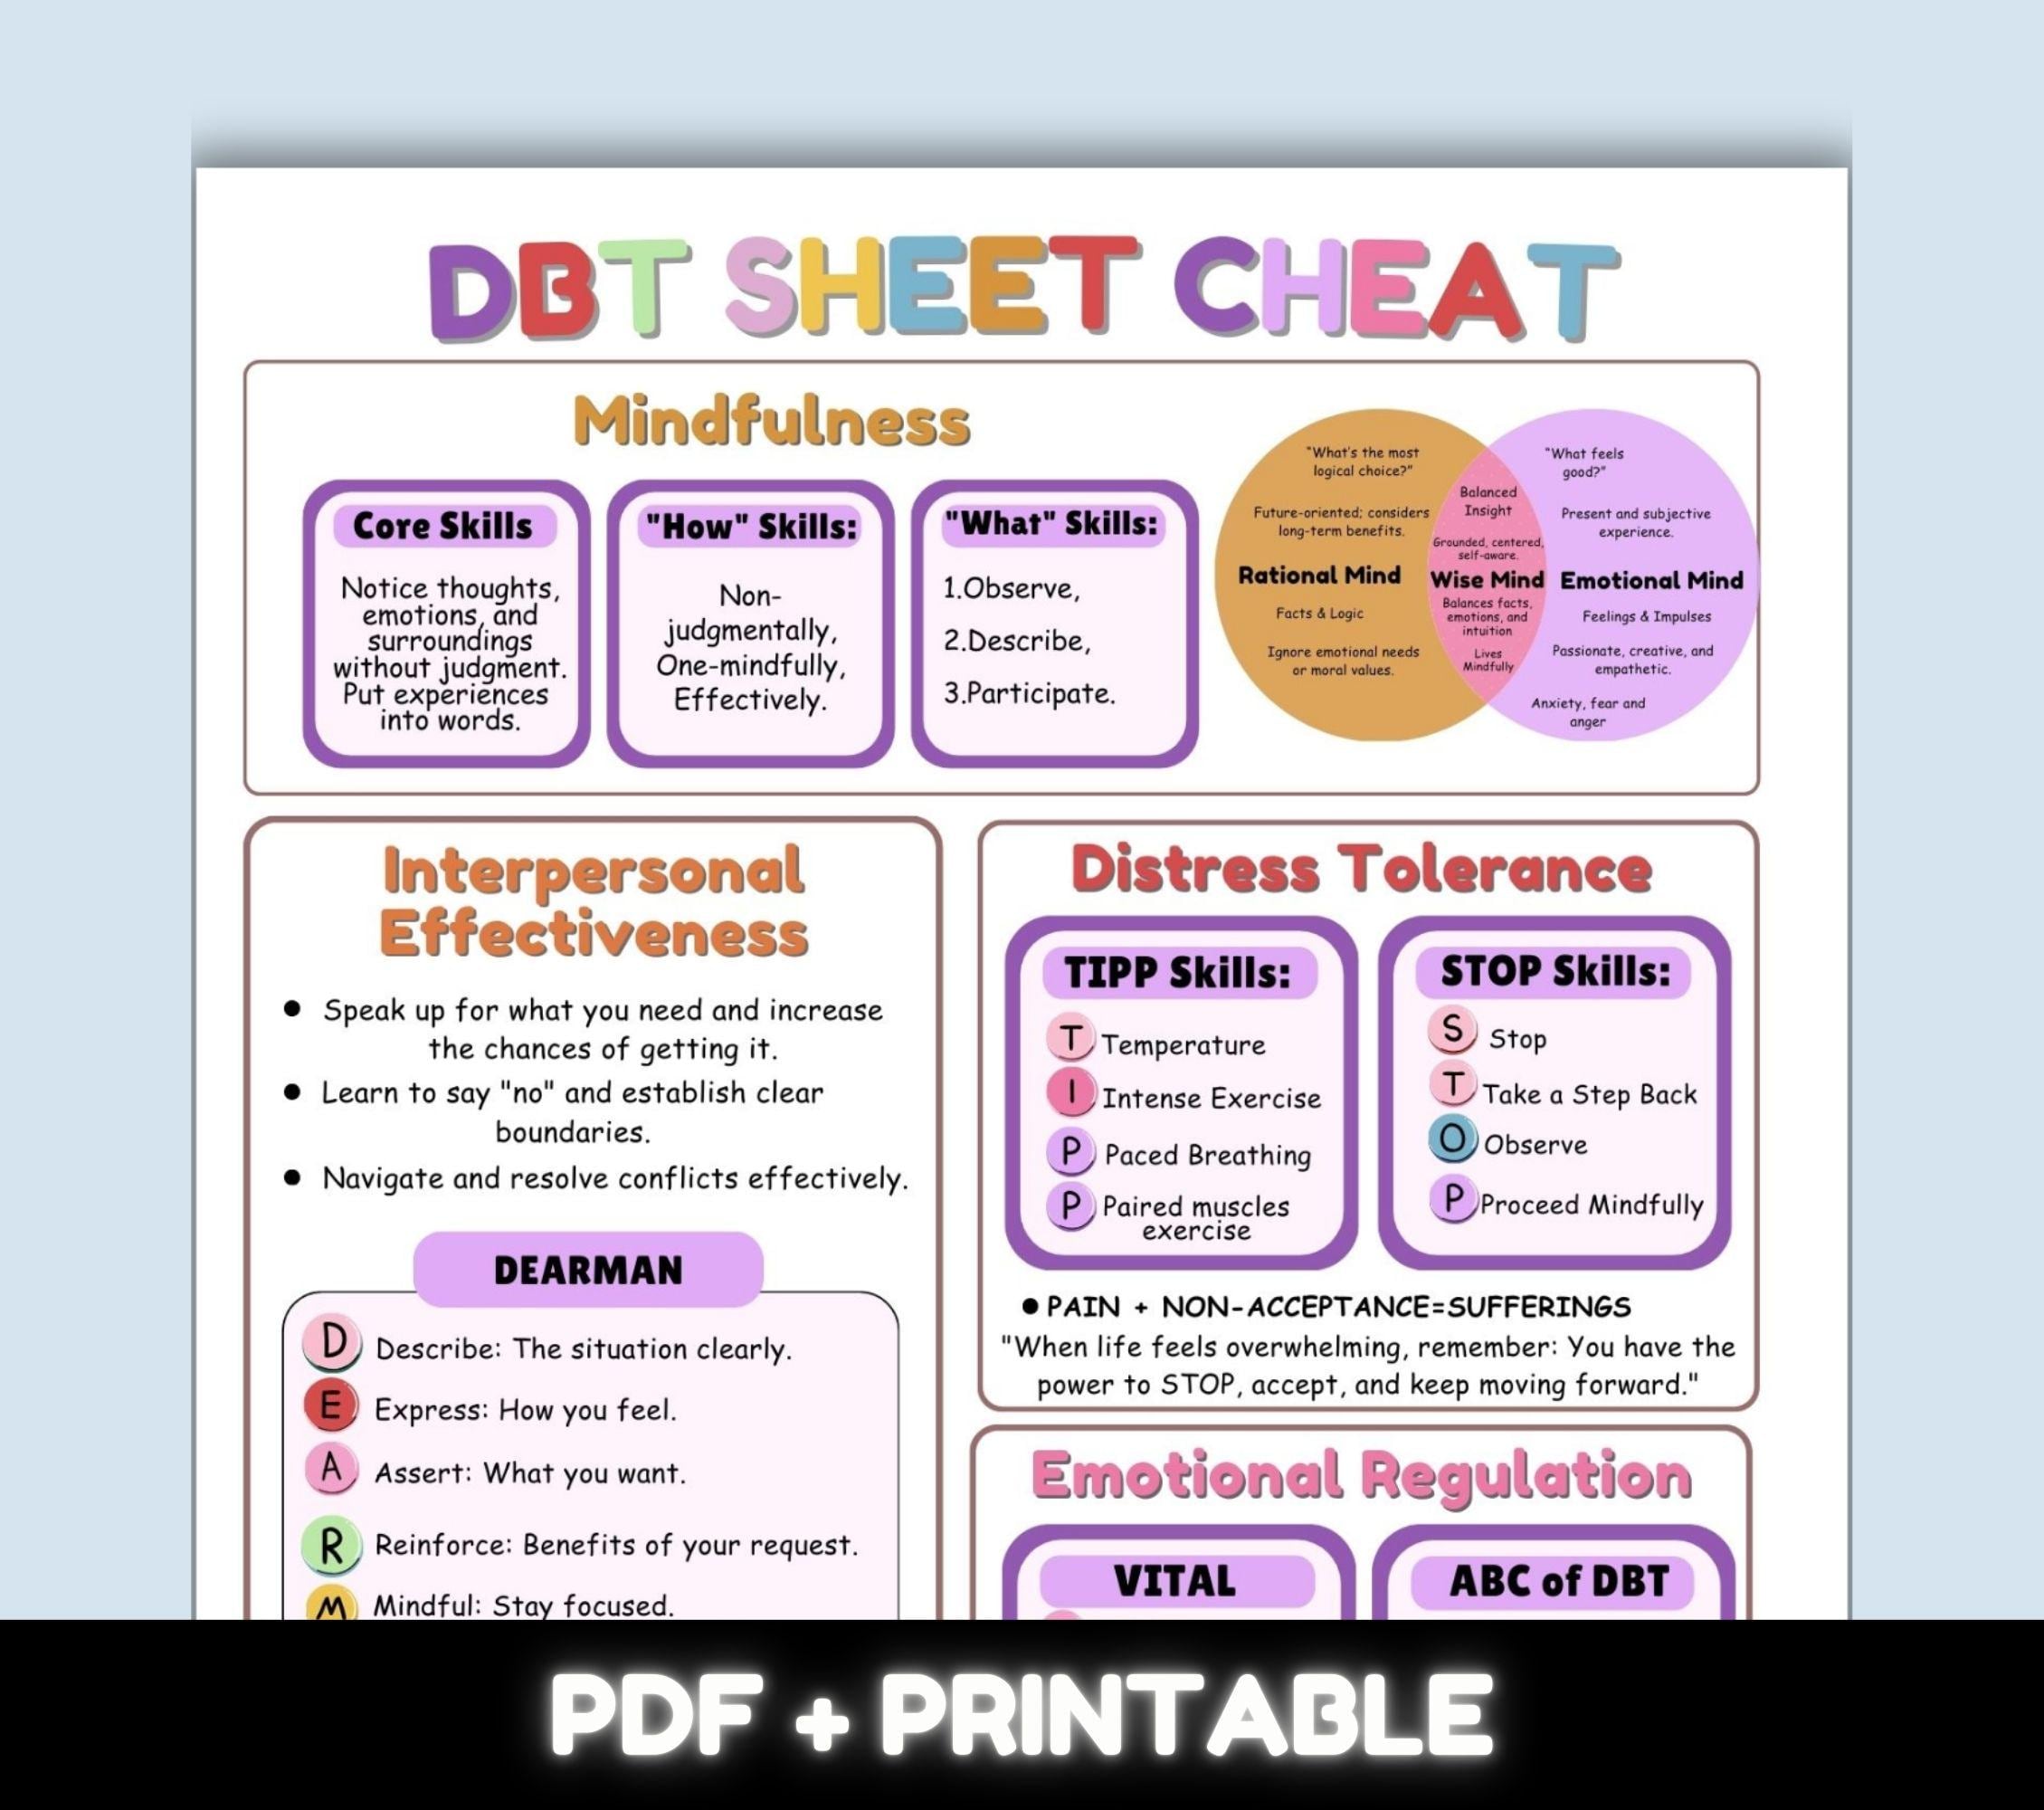
The skills training group runs for about twenty-four weeks and covers four modules. Mindfulness is first because everything else depends on it. If you can't observe your own state without immediately reacting to it, none of the other skills are accessible. Emotion Regulation teaches the opposite of what most people expect. You don't calm down by fighting the emotion. You calm down by understanding what function the emotion serves. The name it, picture it, challenge it, act it sequence seems obvious once someone explains it, but in a crisis, that sequence doesn't occur to you. That's why the skills are practiced repeatedly in session before they're expected in real life. Distress Tolerance is the module most people gravitate toward because it offers immediate tools. TIP skills, self-soothing with five senses, IMPROVE the moment, thought stopping, acceptance radicles. These are the skills that keep people from acting on urges. The problem is that distress tolerance alone is insufficient. You can tolerate distress perfectly well and still be stuck in the same dysfunctional relationship, the same job, the same patterns. Emotion Regulation addresses the upstream causes. Without both, you're managing symptoms, not building a life worth living. I ran into a case where a client was doing everything right in group but kept re-enacting the same interpersonal disaster every week. She had learned the DEAR MAN skill for asking for what she wanted. She used it verbatim in sessions. She got nowhere outside. The issue wasn't the skill. It was that she was using it at the wrong intensity level. DBT has a concept called WISE MAN, which modifies DEAR MAN with goals, mindfulness, assertiveness, and no shame. The client was applying DEAR MAN without the mindfulness component. She knew the words but hadn't checked whether her goal in that moment was connection or control. Once we slowed down and identified what she actually wanted versus what she thought she should want, the skill started producing different results. The script matters less than the intention behind it.
Get the Full Details

Where DBT Falls Short
DBT isn't appropriate for everyone. It requires the capacity to attend weekly group sessions and do daily diary cards and practice skills between sessions. Clients who are actively psychotic, acutely intoxicated, or experiencing severe homelessness often can't meet those demands. In those cases, treating the immediate crisis takes priority, and DBT becomes relevant later. There's also a question about whether DBT addresses trauma adequately. The original model was designed for chronically suicidal individuals, not necessarily for complex PTSD, though later adaptations like DBT-PTSD have been developed to close that gap. If trauma is driving the borderline symptoms, skipping trauma work while focusing exclusively on skills can leave people managing their symptoms without resolving the underlying cause. The research base is solid but not universal. Linehan's original trials showed significant reductions in suicide attempts and hospitalizations. Meta-analyses support modest to moderate effect sizes across studies. But the active ingredients aren't fully mapped. Is it the skills training? The individual therapy? The phone coaching? The therapist consultation team? We don't know for certain. The model works, but explaining why it works remains an open question in the field. If you're looking to learn DBT on your own because you can't access a program, there are workbooks and resources available. The original Skills Training Manual by Marsha Linehan is the primary text. There are adapted versions for adolescents and for specific populations. Apps exist but they're generally supplements rather than substitutes. The human interaction in DBT isn't incidental. The therapist's commitment to staying in the room with someone's worst moments is part of the mechanism. No app replicates that.
The most practical starting point if you're trying to help yourself or someone else is the mindfulness module. It's the foundation. The Observe and Describe exercises from the Gendreau adaptation or the original Linehan manual are accessible enough to begin independently. Start with five minutes a day. Notice the resistance. Sit with it. That's the practice. Everything else builds on that capacity to stay present when the urge to escape is strong.