What Actually Happens When You Use DBT With Addicted Clients
Most people think dialectical behavior therapy is just a fancy name for coping skills training. It's not. The model was originally built by Marsha Linehan for borderline personality disorder, and the reason it transfers to substance use is because both populations share the same core mechanism: emotional dysregulation driving impulsive action. That means you're not really treating the addiction first. You're treating the affective collapse that precedes every relapse. I've watched therapists spend months trying to get clients to stop using before they ever had the emotional regulation skills to sit with distress. It doesn't work. You can't expect someone in active withdrawal from their coping mechanisms to suddenly learn how to tolerate intense shame without acting on it. The sequence matters more than the content.
Dialectical Behavior Therapy For Substance Abusers
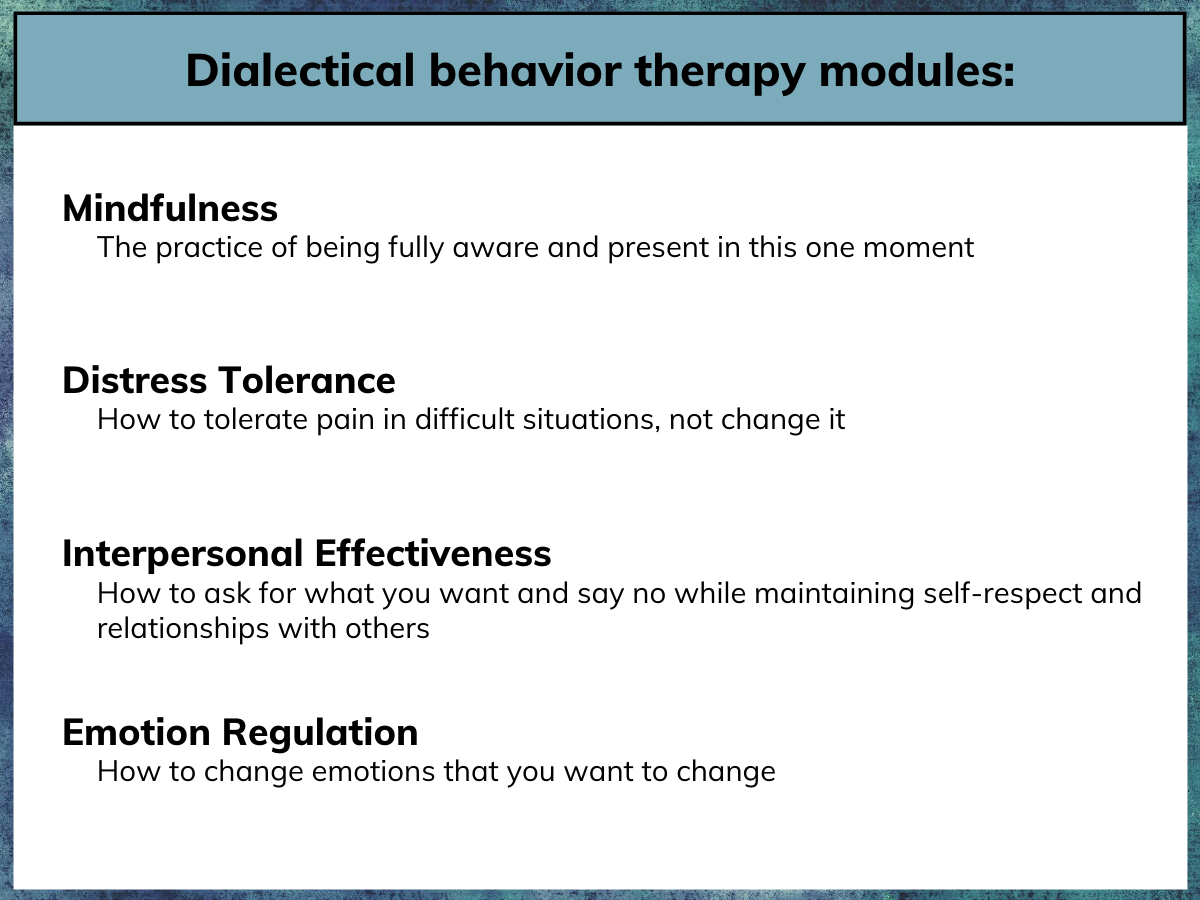
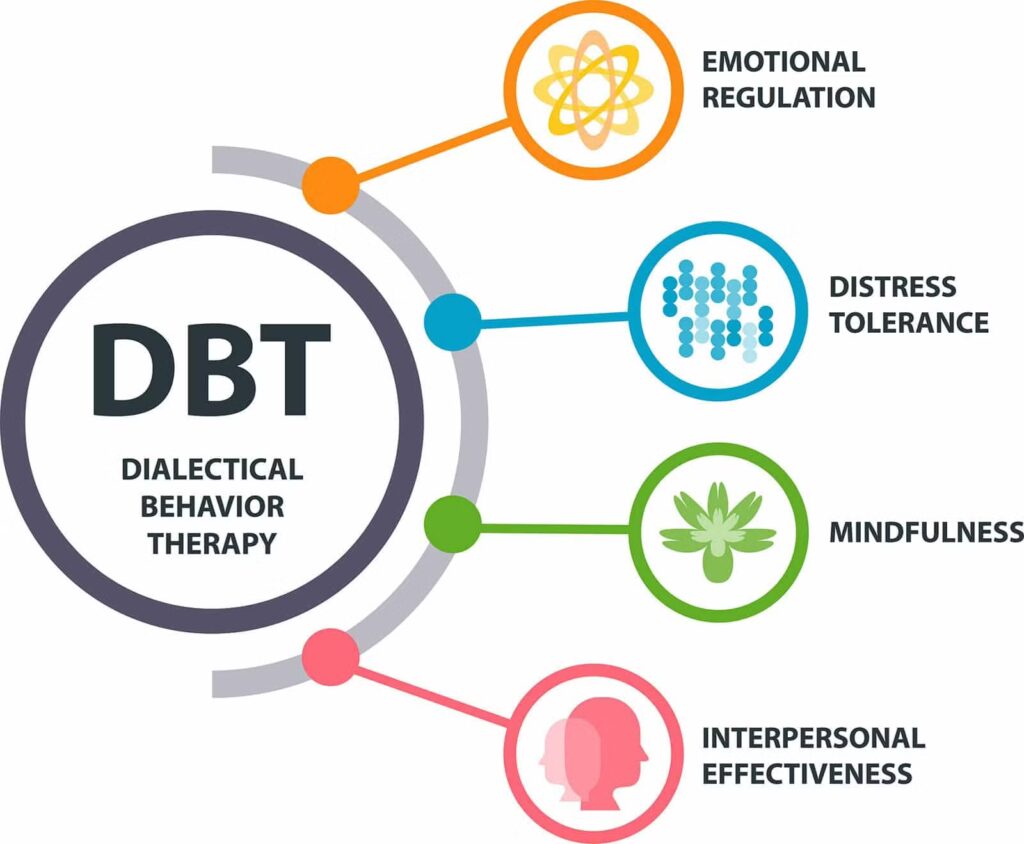
DBT for substance use disorders follows a modified protocol. Linehan herself adapted the original framework in her 2001 manual, and since then researchers like Brown, Chapman, and Gonzalez have refined it further. The core structure stays the same though. You still have individual therapy, skills training groups, phone coaching, and a consultation team for the therapists. What changes is the targeting. In standard DBT, the hierarchy of treatment targets goes like this: first life-threatening behaviors, then therapy-interfering behaviors, then quality-of-life-interfering behaviors, then skills deficits. For substance-abusing clients, the addiction-related behaviors slot into the first target category alongside suicidal and self-injurious acts. That priority placement is what makes the model effective here. You're not doing addiction counseling in a separate track. You're treating substance use as a behavioral emergency on the same level as suicide attempts. The four skills modules are where most people get confused. They think you just hand out worksheets on mindfulness and call it a day. Mindfulness in this context isn't relaxation. It's the foundational skill of observing your internal state without immediately reacting to it. For a client whose entire relationship with emotional experience has been avoidance through substance use, this is the hardest module and the most important one. You spend weeks on nothing else. I had a client who was a high-functioning executive with twenty-three years of sobriety who relapsed because he'd never actually learned to sit with discomfort. He'd spent two decades managing it with discipline and structure. The moment those structures failed, which they always do, he had no skill to fall back on. I kept him in the mindfulness module for eight weeks instead of the standard four. He learned to notice the urge to use without obeying it.
Distress tolerance is the second module and the one people think they understand but usually implement poorly. It's not about making crises better. It's about surviving them without making things worse. The TIPP skills — temperature, intense exercise, paced breathing, paced muscle relaxation — are physiological interventions that actually work because they target the autonomic nervous system directly. When a client's body is in fight-or-flight during a craving episode, talking them through cognitive restructuring is useless. Their prefrontal cortex is offline. You need to shift their physiology first. Cold water on the face triggers the mammalian dive reflex. That alone can break a craving cycle in under two minutes. Emotion regulation is where the real clinical work happens. Clients with substance use disorders typically have either chronically elevated negative affect or emotionally numb states that they find unbearable. The module teaches them to identify emotions, understand their function, and reduce vulnerability to emotionalmindset triggers. Sleep hygiene, nutrition, and medication adherence get discussed with the same seriousness as any other skill. These aren't side notes. They're treatment targets. A client who's sleeping three hours a night and eating irregularly is biologically primed for relapse regardless of how many coping skills they know. Interpersonal effectiveness is the fourth module and the one most therapists rush through. That's a mistake. Substance use is deeply social. Most people use in contexts that are socially reinforced. Recovery requires learning to say no, to ask for what you need, and to maintain relationships that don't involve substances. This isn't soft skills training. It's behavioral rehearsal for the environments where relapse actually happens.
Get the Full Details
Here's the part nobody talks about enough: DBT for addiction has a high dropout rate. Not because the model is bad, but because the early stages are brutal. You're asking people who've spent years numbing their emotions to feel everything intensely while also being asked to stop using the only thing that's ever worked. The first twelve weeks are where most people leave. I've seen it happen repeatedly. The workaround is to make the first session explicitly about validating how awful this process is. Linehan calls this the validation strategy, and it's not manipulative. It's clinically necessary. If the therapist comes in hot with "you need to learn these skills," the client hears "your current way of coping is inadequate." That triggers the same shame response that drives the craving in the first place. You validate the function of the behavior before you ask them to change it. Another counterintuitive point: chain analysis, which is a signature DBT technique, often fails when applied naively to addiction. The standard chain analysis traces back from a problem behavior to its triggers and links. But addicts are extremely skilled at chain analysis of their own patterns. They know exactly what happens before they use. What they don't know is what happens between the trigger and the behavior — the micro-moments of choice where a different skill could have interrupted the chain. I found that instead of doing a full backward chain analysis, it's more useful to do a forward analysis: given the trigger, what would the ideal response chain look like, and where exactly does the current chain break? That shift in direction catches the gap that backward analysis misses. The phone coaching component is equally misunderstood. It's not general support. It's specifically for in-vivo skill generalization. A client calls between sessions because they're at a party and having a craving. The therapist doesn't talk them through feelings. The therapist helps them apply a specific skill from the skills group to that exact moment. "What skill did we practice last Tuesday? Can you use it right now?" That's it. If the call becomes emotional processing, you've missed the point and you're reinforcing the behavior you're trying to shape. Calls should be brief, skill-focused, and ideally end with the client using the skill on the phone. I keep my coaching windows short and explicit. Forty-five minutes a day, two days a week. Longer than that and the boundaries dissolve and everyone gets exhausted.
The consultation team for therapists is non-negotiable. Treating addicted clients with DBT is emotionally demanding work. Therapists burn out fast if they don't have structured peer support. Linehan requires this component in her model and for good reason. I've worked with clinicians who skipped it and came back six months latercompassion fatigue and cynical attitudes toward their clients. That's when treatment fails. The client senses the detachment and drops out. There are legitimate limitations. DBT doesn't work well for people who are cognitively impaired or have significant untreated psychotic disorders. The skills training group assumes a minimum level of verbal abstract reasoning. I had to refer a client with chronic schizophrenia and co-occurring cocaine use to a simpler contingency management program. DBT wasn't appropriate. People who are in acute withdrawal also aren't ready for DBT. You stabilize medically first, then introduce the model. Jumping in too early just creates another failure experience that reinforces the belief that recovery is impossible. Another limitation is cultural fit. The direct, skills-based, highly structured approach doesn't resonate with everyone. Some clients need more relational grounding before they can engage with the model. I've seen successful adaptations that front-load the therapeutic relationship for another two to three sessions before introducing skills. That's not a deviation from the model. That's clinical judgment within the model.
Duration is typically twenty-four to thirty-six weeks for the full protocol. Some programs extend to eighteen months. The evidence base supports at least six months for meaningful outcomes. Shorter programs show initial gains that tend to fade. If you're running a ten-week workshop and calling it DBT for addiction, you're not doing DBT. You're doing a skills overview. The research is solid. A 2015 meta-analysis in Addiction found moderate effect sizes for DBT in reducing substance use compared to treatment-as-usual. The effects are stronger for stimulant use than for opioids, which makes sense given that opioid use involves more physiological dependence and less purely emotion-driven use. For alcohol and cannabis, the effects are comparable to CBT but with better retention rates. That retention difference matters. In addiction treatment, completion rate is one of the strongest predictors of outcome. If you're looking to implement this, the certified DBT training pathways go through the Behavioral Technology Associates network or the DBT-Linehan Board of Certification. Self-study isn't sufficient. The fidelity to the model matters, and untrained practitioners drift into a hybrid that loses the dialectical core. Without the dialectic — the balancing of acceptance and change — you're just doing CBT with a different label.
The skills training manual most people use is Linehan's DBT Skills Training Manual, second edition. It's dry. It's also the source. Everything else builds on it. The workbook DBT Skills Training from a Practical Guide by Ashurst and Turner is a decent supplementary resource for group leaders who want session-by-session structures. For the consultation team component, monthly meetings are the minimum. Biweekly is better. The content should cover treatment fidelity, therapist emotional responses to difficult clients, and problem-solving around implementation barriers. If your team meetings have become social hours, something is wrong. Insurance coverage for DBT varies widely. In the US, most major plans cover it if it's billed under CPT codes for individual psychotherapy and group therapy. The phone coaching component is harder to bill and some providers skip it entirely due to reimbursement complexity. That's a systemic problem, not a clinical one. Don't let billing constraints determine your treatment model. If you can't bill for coaching, build it into the individual session time or find a grant-funded program that covers it.
The bottom line is that DBT for substance use is not a quick intervention. It's not a workshop. It's a comprehensive treatment model that requires proper training, adequate time, and genuine commitment to the dialectical framework. When it's done correctly, it reduces relapse rates and improves quality of life in ways that standalone addiction counseling doesn't. When it's done poorly, it's just another program people drop out of. The difference is in the fidelity and the willingness to sit with the hard parts instead of rushing through them.