Why DBT Skills Training for Teens Is a Lot Harder Than the Manuals Make It Look
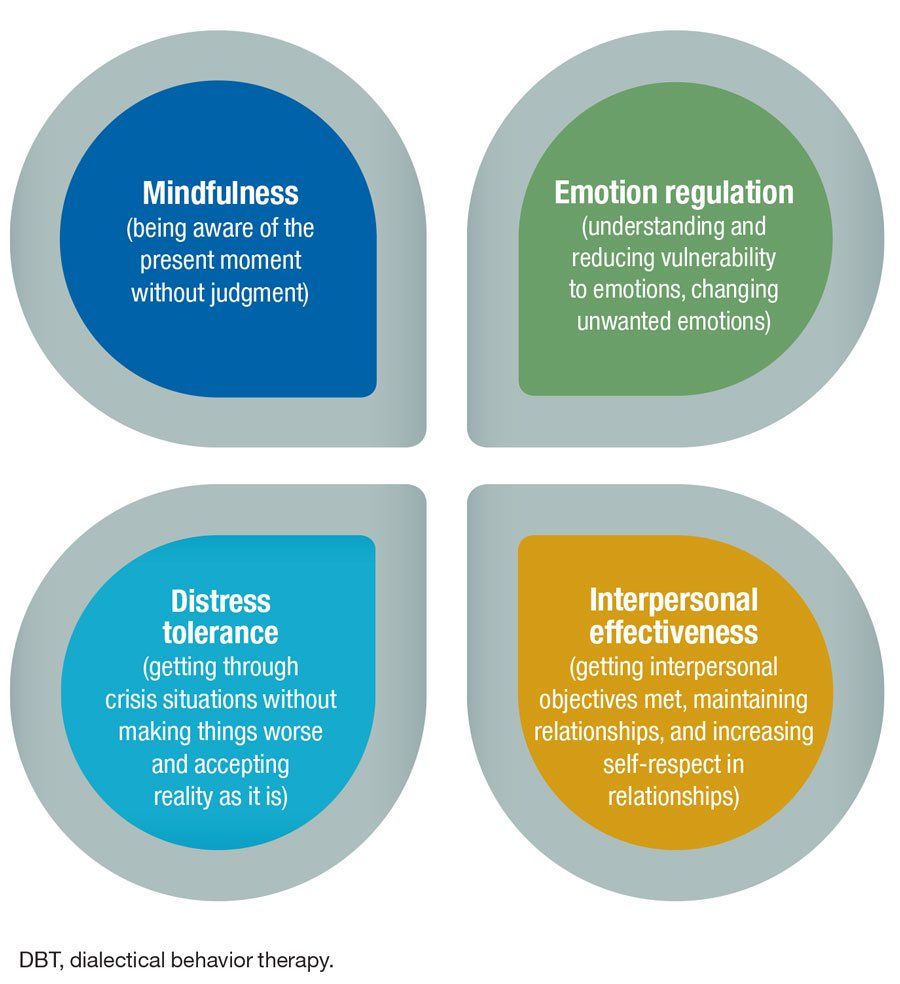
Dialectical Behavior Therapy Skills Training With Adolescents is basically the adult DBT program stripped of some of the heavier components and adapted for younger brains. The core modules stay the same—mindfulness, distress tolerance, emotion regulation, and interpersonal effectiveness—but everything else about delivery changes. You can't just read Marsha Linehan's workbook to a group of fifteen-year-olds and expect them to sit still through it. I spent about six years running adolescent DBT skills groups in a community mental health setting before moving mostly into individual work. What I learned is that the model itself is solid, but the implementation falls apart if you don't adjust for developmental reality. Let me walk through how it actually works in practice.
Dialectical Behavior Therapy Skills Training With Adolescents: What It Actually Looks Like
A standard group runs once a week for about twenty-four weeks. Each session follows a consistent structure: check-in, homework review, teaching a new skill, in-session practice, and assigning new homework. That sequence matters more than most people realize because teens with high emotional dysregulation need predictability to regulate around. The predictability itself becomes a containment tool. Check-ins are where things usually go sideways first. Adults can sit down and say how they're doing on a scale of one to ten. A fourteen-year-old in the middle of a panic spiral will stare at the floor and say nothing. I learned to start check-ins differently. Instead of asking for a numeric rating, I'd offer three options out loud and let them point. "Are you somewhere between okay and fine, somewhere between fine and not good, or somewhere between not good and completely falling apart?" It sounds simple but it cuts the time spent coaxing an answer out of a kid who's already overwhelmed by the abstract demand of self-assessment. Homework review is another place where groups routinely lose steam. The DBT model assumes people practice skills between sessions. Adolescents, particularly those with ADHD comorbidity, often don't. I used to let the group slide when kids didn't do the worksheet. That was a mistake. The skill doesn't stick unless you come back to it, even if they didn't do it. So I changed the homework review to be almost entirely focused on what got in the way. Not "did you do it," but "what made it impossible." That single reframing shifted the whole dynamic from shame-based avoidance to problem-solving.
Teaching the Modules Without Losing Them
The four modules get taught in order. Mindfulness comes first because you can't build distress tolerance on top of a foundation that isn't there. But here's the counter-intuitive part that nobody tells you in training: teaching mindfulness to an dysregulated teen in a group setting is almost never effective on the first pass. Their nervous systems are too activated. What works better is teaching a micro-version of it inside the distress tolerance module, then circling back to full mindfulness later. I've seen experienced clinicians try to run a full twelve-minute mindful breathing exercise with a group of adolescents who have been sitting for forty-five minutes already. Half of them are fidgeting, two are openly resisting, and the other half are dissociating. It looks like the kids can't do mindfulness. The actual problem is the format, the length, and the timing. Switching to sixty-second breathing stops with a sensory anchor—pressing your thumb and forefinger together and noticing the texture—changed the compliance rate dramatically. It felt too short at first. It wasn't. Distress tolerance is the module where most groups hit their hardest wall. TIPS, ACCEPTS, IMPROVE, self-soothing, radical acceptance. The skills are sound. The problem is that distressed teens often need these skills most precisely when they have the least capacity to learn them. That's the dialectic in dialectical behavior therapy, by the way. Acceptance and change happening at the same time. The therapist validates how impossible it feels to use a coping skill while your chest is caving in, and then you offer it anyway.
Get the Full Details

One specific edge case I ran into repeatedly involves high-functioning autistic teens in mixed groups. They can process the psychoeducation fine. They can recite the skill steps back to you. They just won't use the skill in crisis because the interoceptive awareness required to notice early emotional shifts is genuinely different for them. For one kid in particular, standard emotion labeling worksheets were useless. I ended up working with him to map physical sensations to emotions using a body outline drawing instead of words. He'd color in where he felt things. It took two sessions to set up and saved us probably eight weeks of frustration later. The skill was the same. The delivery just needed to match his processing style.
Emotion Regulation: Where Most Groups Actually Succeed
This is the module that tends to land best with adolescents. Check the facts. Name the emotion. Reduce vulnerability using ABC PLEASE. Opposite action. Urges toward dangerous behaviors are addressed directly with DEAR MAN and other interpersonal skills modules feeding into it. The concrete structure helps. Teens respond well to "here's a skill, here's when it applies, here's what it looks like." What's less discussed is how often parents need to be involved in emotion regulation work for this to transfer out of the group room. A teen learns to identify that a panic attack is building and should use deep breathing. Then they get home and their sibling starts screaming and the parent is yelling and the homework skill vanishes. I started sending home a parent handout that explained the emotion regulation chain and what to do when they noticed their kid using a skill versus ignoring one. It wasn't optional in my groups. Attendance at one parent skills session per month was required. The compliance went from roughly thirty percent to about seventy-five percent with a direct impact on outcomes.
Interpersonal Effectiveness: The Hardest Module for This Population
DEAR MAN, GIVE, FAST, SMART. The interpersonal effectiveness skills are designed to help people get what they want while keeping the relationship intact. For adolescents whose social world is the single most activating stressor in their lives, this module should logically be the most relevant. In practice it's often the most resisted. Twelve-year-olds don't trust that asking for what they need will work. Their lived experience says otherwise. They've seen friends get mocked for speaking up. They've seen siblings get shut down. The skills feel naive to them. I stopped trying to sell the long-term relational benefits and just framed it as "this is how you get the thing you want right now without making it worse." That reframing alone got participation up. Teenagers will engage with something they perceive as strategically useful. They won't engage with something they perceive as morally correct.

What This Approach Doesn't Fix
I need to be clear about the limitations because the literature sometimes makes it sound more effective than it actually is in real-world settings. DBT skills training for adolescents is not a standalone intervention for kids with active suicidality, severe eating disorders, or untreated substance use. It needs to be paired with individual therapy, family involvement, and sometimes medication management. The group teaches the skills. The individual therapist helps the kid actually use them when things fall apart. Skipping individual therapy and relying on the group alone is a common mistake I see when programs are short-staffed. Another limitation is duration. Twenty-four weeks is the standard, but many adolescents show diminishing returns after week sixteen if the skills haven't been integrated into daily life by then. I've adjusted my groups to focus more intensively on just two modules in the first twelve weeks rather than brushing through all four, then looping back. Retention and mastery matter more than coverage.
Practical Details for Running a Group
You'll need a structured curriculum. The linehan skills training manual for adolescents is the standard reference. Workbooks are available through multiple publishers. You don't have to use the official materials, but building your own from scratch without that foundation tends to produce gaps that show up later when you're trying to teach a skill that builds on something you never covered. Group size should be six to eight teens. Larger groups sound efficient but the homework review phase becomes unmanageable and the kids who need the most attention end up getting the least. Mixing diagnostic categories is fine and often helpful, but keep borderline personality disorder traits and conduct disorder issues from dominating the group dynamics without structure. Setting clear expectations in the first two sessions prevents that. Phone coaching is part of the adult DBT model and it's harder to implement with adolescents. Parents usually become the coaches, which means you need to train them separately. I found that thirty-minute parent training sessions every other week, taught as a parallel group, made a measurable difference in how often skills were reinforced between formal sessions.
Where People Go Wrong
The biggest mistake I see is treating the skills like information instead of behaviors. Explaining opposite action is not the same as practicing it. Teens need to role-play, they need to fail at role-plays in a safe environment, and they need to do it multiple times with different scenarios. If your group is mostly you talking and them listening, you're delivering psychoeducation, not skills training. The distinction matters for outcomes. Another common error is moving too fast through mindfulness. You can spend three weeks on this module and it's not excessive. The entire therapy rests on the ability to observe experiences without immediately reacting to them. That's a muscle that needs building, and for some teens it's genuinely the first time anyone has asked them to practice anything like that. Rushing it produces groups that look productive on the surface but fall apart the moment a real crisis hits. The model works. It's not magical. It requires consistency, developmental sensitivity, and an honest acknowledgment of what it can and can't do on its own. If you're willing to adapt the delivery to the population instead of forcing the population to adapt to the delivery, it tends to hold up.