
What You Actually Need to Know Before Starting
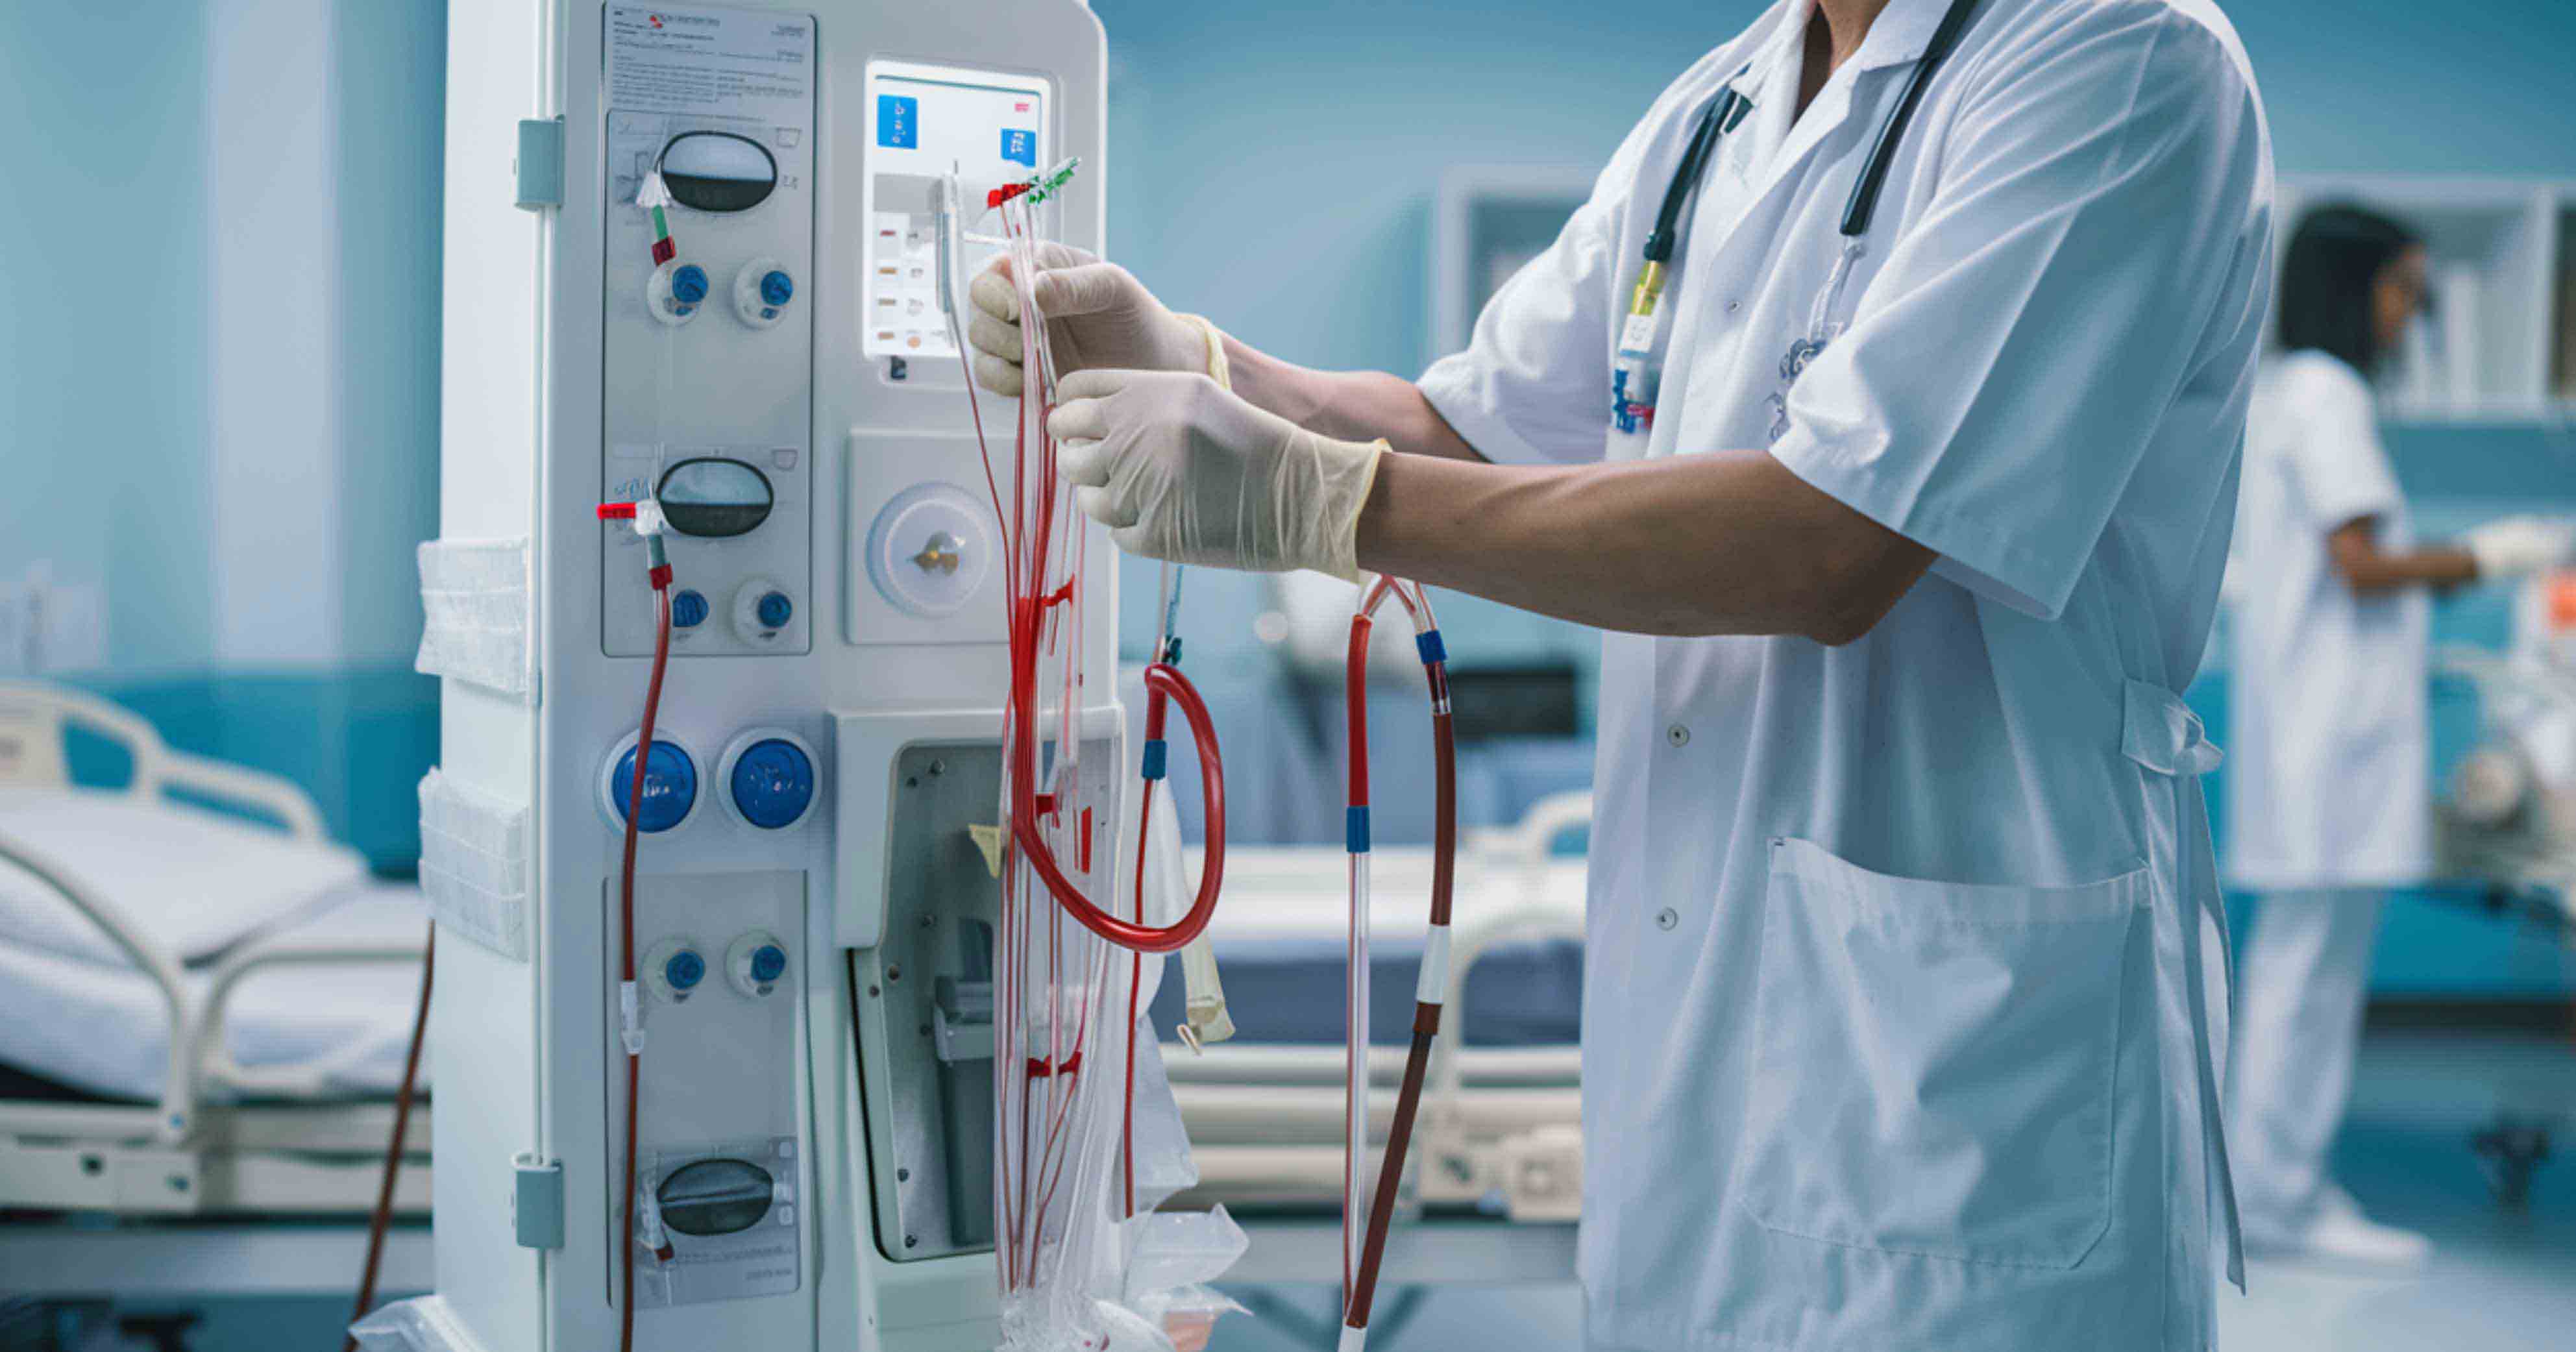
Dialysis biomedical technician training is nothing like the glossy brochure programs promise. It sits somewhere between clinical skills and electrical engineering, and most people who walk into it expect one or the other. The reality is you need both, and you need them at the same time because a dialysis machine failing during treatment is not a theoretical problem. I spent seven years in renal service departments before moving into consultant work. The people who survived that job usually had one trait in common: they understood that the manual is a reference document, not a playbook. The manufacturers assume you are reading their troubleshooting flowcharts in order from top to bottom. You will rarely do that in practice.
Dialysis Biomedical Technician Training
The core of this work revolves around four machine types: hemodialysis consoles, bicarbonate mixing systems, water treatment plants, and the dialysate delivery circuit. You will spend roughly sixty percent of your time on hemodialysis machines because those are the ones that break most often and the ones clinicians panic about first. The remaining forty percent splits between water treatment maintenance and quality testing. Blood glucose monitors and vascular access equipment get mentioned in training curricula but rarely require your attention unless the facility is very small. The biggest mistake trainees make is treating calibration as a ritual instead of a diagnostic tool. Every time you calibrate a pressure transducer or verify ultrafiltration accuracy, you are gathering data about machine health. Most people record the numbers, sign the form, and move on. That is how you miss a pump that has been drifting by two milliliters per hour for three weeks until a patient loses half a liter of fluid during a routine session. Another common trap is confusing electrical safety testing with functional testing. An ES checklist from a Fluke unit tells you the machine will not shock anyone. It does not tell you the conductivity sensor is reading high or the air detector is triggering late. You need both datasets. Relying on one set blinds you to half the failure modes that actually show up in the field.
The Water Treatment Section Most People Rush Through
Water purification is where dialysis machines actually fail, even though the failure mode never appears on the machine diagnostics. The resin in the water softener exhausts before the monitoring panel flags it. The carbon beds develop channeling. The reverse osmosis membranes develop microscopic tears that do not show up on a conductivity reading but will push endotoxin levels past the AAMI threshold over a four-hour treatment cycle. I learned this the hard way at a twenty-station outpatient clinic. We had a machine that kept throwing an unsalvageable dialysate conductivity alarm every afternoon between two and four o'clock. Three different service technicians replaced the conductivity cell, then the mainboard, then ran the full diagnostic sequence. Nothing held. The machine was fine. The RO membrane in the water plant was fouling on line two, and the conductivity spike only appeared when the plant cycled from standby to production mode during the afternoon treatment rush. We caught it by mapping conductivity readings against the plant cycle log, not by swapping parts on the dialysis console. That took approximately four days instead of the three weeks we burned before someone looked at the water plant.
Get the Full Details
Practical Workflow That Actually Works
When you get a call on a malfunctioning machine, do not pull it from the floor immediately. Document the alarm code, the treatment phase it occurred in, and any recent maintenance history. Then test the machine on the bench or in place with a resistive load before touching anything internal. The resistive load simulates blood flow without exposing anyone to biohazard risk, and it will tell you whether the issue is in the machine or in the external circuit. I typically run this sequence: visual inspection, power-on self-test, line-pressure verification, UF gravimetric check, air detector test, and conductivity accuracy verification. That takes about twenty minutes per machine if you know what you are doing and the machine is healthy. If you are new to the workflow, budget forty-five minutes. Factor in another fifteen minutes for documentation, which is not optional because the CMS surveyors will ask for it.
Calibration Intervals and What They Actually Mean
The standard calibration schedule calls for quarterly checks on hemodialysis machines and monthly checks on water treatment systems. Quarterly means every ninety days, not every calendar quarter, because the surveyors count days, not months. Monthly water testing should include conductivity, total organic carbon, and endotoxin sampling at each distribution point. The endotoxin tests require holding samples for fourteen hours before they are valid, so plan your sampling schedule accordingly or you will be collecting samples on Friday and realizing on Monday that they have expired. Bicarbonate concentrate verification is another area where shortcuts cause problems. You need to test the concentrate strength with a calibrated conductivity meter and compare it to the manufacturer specification. I use a handheld refractometer as a secondary check because the conductivity readings can drift if the probe is contaminated. Cleaning the probe between samples takes ten seconds and prevents a whole class of false readings.
Documentation Requirements That Will Actually Get You in Trouble
The electronic service log needs to capture the following for every service event: patient identifier redacted, machine serial number, date and time, alarm or fault description, actions taken, parts replaced, post-service test results, and your signature. If any of those fields is blank on a random audit, the surveyor will cite you under E-tag 542. The citation is not a warning. It carries a monetary penalty and a plan of correction deadline. Training programs emphasize documentation heavily because it is the part of the job that will keep you employed. The technical skills are important. The documentation is what determines whether you still have a job when the survey team arrives.

Advanced Diagnostic Techniques That Take Years to Learn
After you clear the basic certification requirements, the real learning begins. You will encounter intermittent faults that disappear when you hook up the bench tester. Those are the jobs that define a career. One technique that helped me significantly is thermal imaging during active treatment cycles. A heating element controller that is cycling incorrectly will show a thermal pattern long before it throws a fault code. A loose connection on the mainboard will appear as a hot spot on the power trace. I use a Forensic FLIR scope for this work, and it has caught issues that the manual diagnostics missed at least a dozen times. Another technique that is rarely taught in formal programs is signal tracing on the dialysate mixing manifold. The solenoid valves that control bicarbonate and acid concentrate are driven by low-voltage DC signals from the mainboard. When you trace those signals with a multimeter in DC voltage mode while the machine is in dialysate preparation mode, you can determine whether the valve is receiving the command to open or whether the fault is downstream in the valve coil itself. This distinction saves you from replacing mainboards that are perfectly functional.
What Formal Training Programs Actually Cover Versus What You Need
Most accredited Dialysis Biomedical Technician Training programs cover the basics: electrical safety, standard diagnostics, calibration procedures, and basic water treatment principles. They do not cover the failure modes that show up after three years on the job. You will learn about blown fuses and bad relays in the classroom. You will not learn about the firmware corruption that can occur on older Fresenius 4008S consoles when the battery on the real-time clock dies during a power fluctuation. That is a field problem that requires a specific workaround: disconnecting power for sixty seconds, reinstalling the CR2032, and running a full factory reset through the service menu. Similarly, training programs teach you to test the air detector with the calibration jig. They do not teach you that the air detector on a Gambro AK96 will give false positives if the tubing has any residual lubricant on the interior surface from manufacturing. Wiping the tubing with isopropyl alcohol before installation eliminates the issue entirely.
Tools You Should Own Beyond the Standard Kit
The standard biomedical toolkit includes multimeters, oscilloscopes, ES testers, and pressure calibration devices. Beyond that, you will find these items useful: a calibrated refractometer for concentrate verification, a handheld thermal imager, a tubing cutter rated for dialysis-grade tubing, a set of non-marring assembly tools, and a dedicated laptop with the manufacturer service software loaded. The service software licenses are expensive and usually tied to the facility, so having your own copy with the correct firmware files backed up will save you several hours the first time a machine bricks during a software update. A digital manometer with data logging capability is worth the investment. The analog gauges on most dialysis machines are prone to hysteresis, and the digital overlay readings can be misleading if the sensor is old. A datalogging manometer lets you capture the pressure curve across a full treatment cycle and compare it to the baseline from when the machine was new. Deviations in the curve shape are often more diagnostic than the absolute pressure values.

Certification Realities
The CBET exam from the AMSSA is the baseline credential. It covers general biomedical electronics, medical gas systems, and patient care technology. The dialysis-specific portion is minimal. You will need to supplement that exam preparation with manufacturer-specific training modules. Fresenius, B. Braun, and NxStage each have their own certification paths, and most facilities require you to be cross-certified on at least two platforms before you are allowed to work independently. Factor in eight to twelve hours of training per platform, plus the examination fees, which run approximately eight hundred dollars per vendor. One operational issue that severely impacts this work is parts availability. OEM parts for dialysis machines have lead times ranging from two weeks to six months depending on the component and the manufacturer. Generic replacements exist for some items like pressure transducers and solenoid valves, but using non-OEM parts on life-support equipment creates liability questions during surveys. The workable approach is to maintain a strategic spares inventory for the most common failures: UF cells, conductivity sensors, air detectors, and mains. Keep one spare of each on the shelf. That covers approximately seventy percent of fault conditions without waiting on a supply chain that will not move fast enough during a treatment outage. When you run out of spares, the alternative is cannibalizing a decommissioned machine. This is legal and common practice, but it requires careful documentation because the cannibalized machine must remain out of service permanently with its serial number recorded in the service log. The surveyors check this, and if you cannot account for a machine with a missing serial number, you get a deficiency.
Soft Skills That Matter More Than the Technical Training
You will spend more time explaining to a nurse why a machine is out of service than you will spend repairing it. The explanation needs to be accurate, concise, and framed in terms that help the clinical staff make scheduling decisions. Saying the mainboard needs replacement is technically correct. Telling them the machine will be back in service Thursday afternoon with the expected treatment capacity impact is actionable information. Both statements are true. Only one helps the facility operate. I learned this after a surveyor observed me giving a nurse a twenty-minute explanation of a pressure transducer failure mode. The nurse needed to know whether she could move her next patient to a different machine. She did not need to understand why the transducer was reading low. I shortened my explanations after that. The technical accuracy stayed the same. The delivery changed.
What This Job Does Not Offer
The work is repetitive in a way that most biomedical techs do not expect. You will test the same pressure ranges on the same machine models every week. The calibration routines become muscle memory. The satisfaction comes from catching problems before they reach the patient, which is not always visible to anyone outside the service department. If you need external recognition for your work, this is not the field to be in. The people who stay in dialysis biomedical service for a decade or more tend to be the ones who find the work self-validating. The machines work. The treatments run. The patients go home. That outcome is not guaranteed. It requires you to stay current on firmware updates, to read the bulletins that manufacturers send out quarterly, and to understand that a machine certified last year may have a known issue that was documented in a service advisory you missed. The bulletin volume is manageable if you check it weekly. It becomes a crisis if you check it monthly.


