What Dialysis Patient Care Technician Training Actually Covers
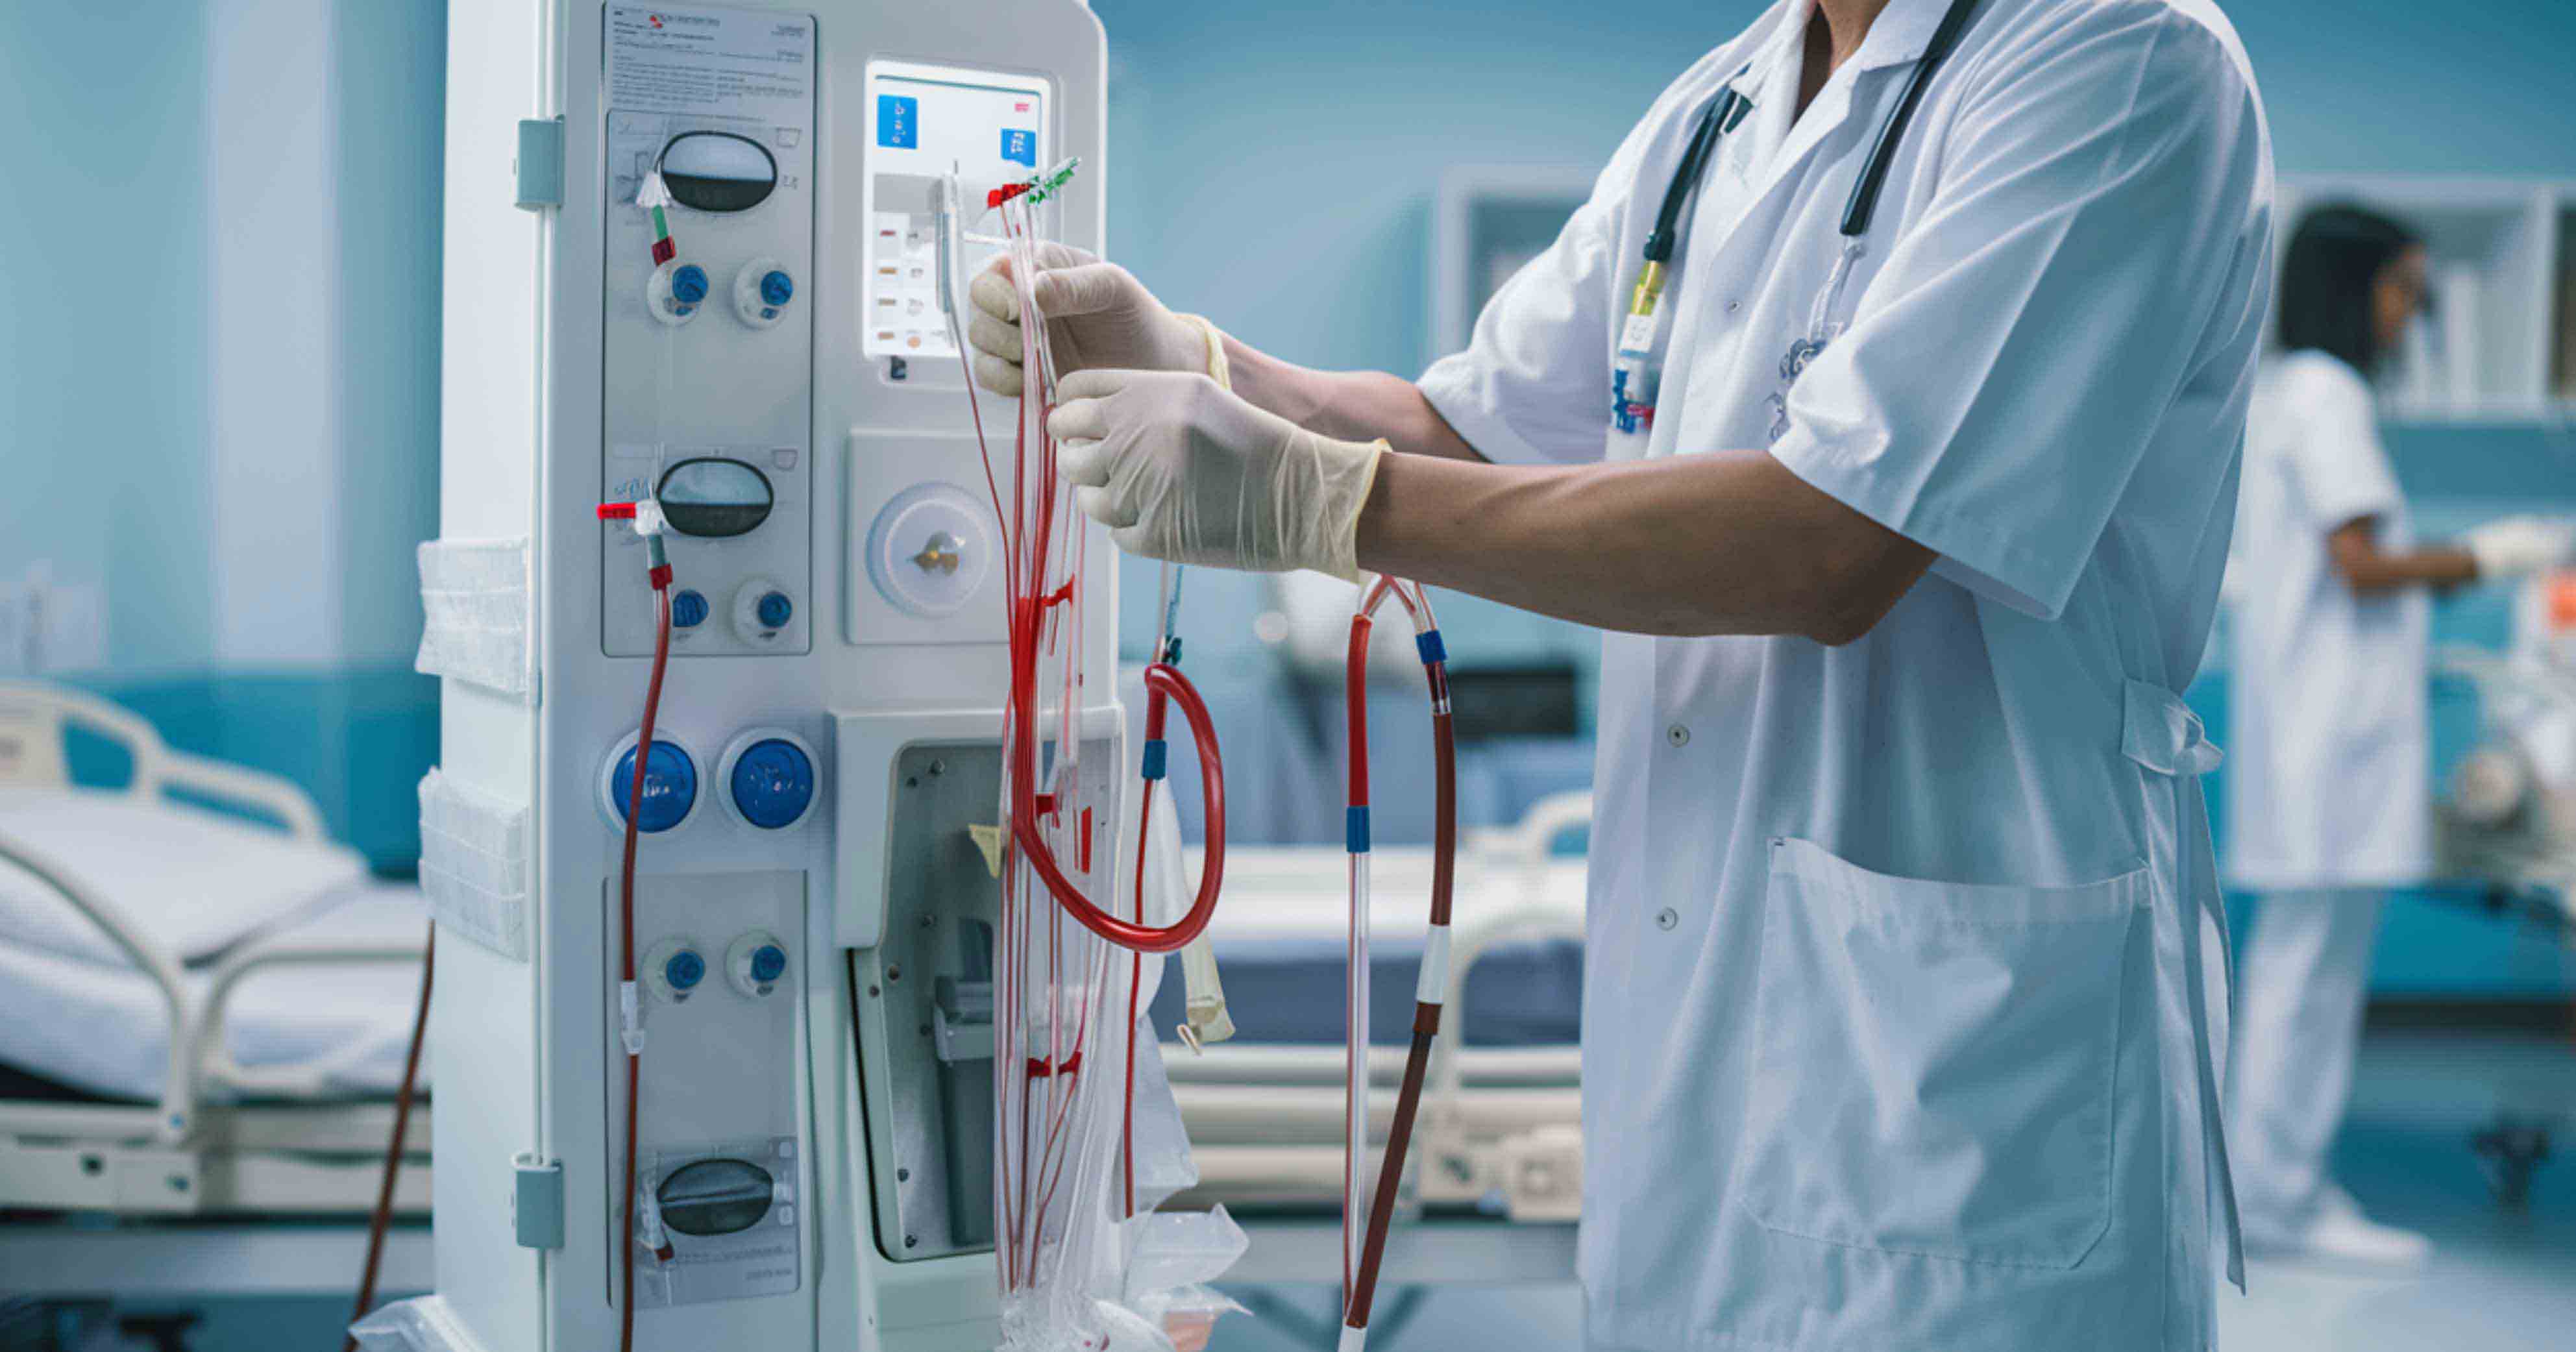
The bulk of dialysis patient care technician training falls into a handful of functional buckets. You learn vascular access assessment first because that is where patients suffer the most preventable damage. Then you move into machine setup and alarm response, vital sign tracking, emergency procedures, and documentation. The exact curriculum varies by state and by employer, but the core material is generally the same across CCI, NHA, and hospital-based programs. Most programs require around 120 hours of combined didactic and clinical time. Some employers hire first and train you, which is common in large dialysis chains. Others expect you to hold a certification before applying. Neither approach is clearly better. The employer-sponsored route saves you money upfront but leaves you waiting on scheduling. The self-funded route gets you certified faster but costs between $500 and $1,200 depending on the provider and whether clinical hours are bundled in. Vascular access assessment is the part of the training that matters most clinically and the part most people gloss over. You need to be able to palpate a fistula or graft thrill and distinguish normal from abnormal. Auscultation comes second. A bruit that changes from a continuous humming sound to a shorter systolic whoosh is a significant finding. The training will teach you the ABCs of access care and the warning signs of stenosis, but it will not make you fast at this. You build that speed through repetition on real patients.
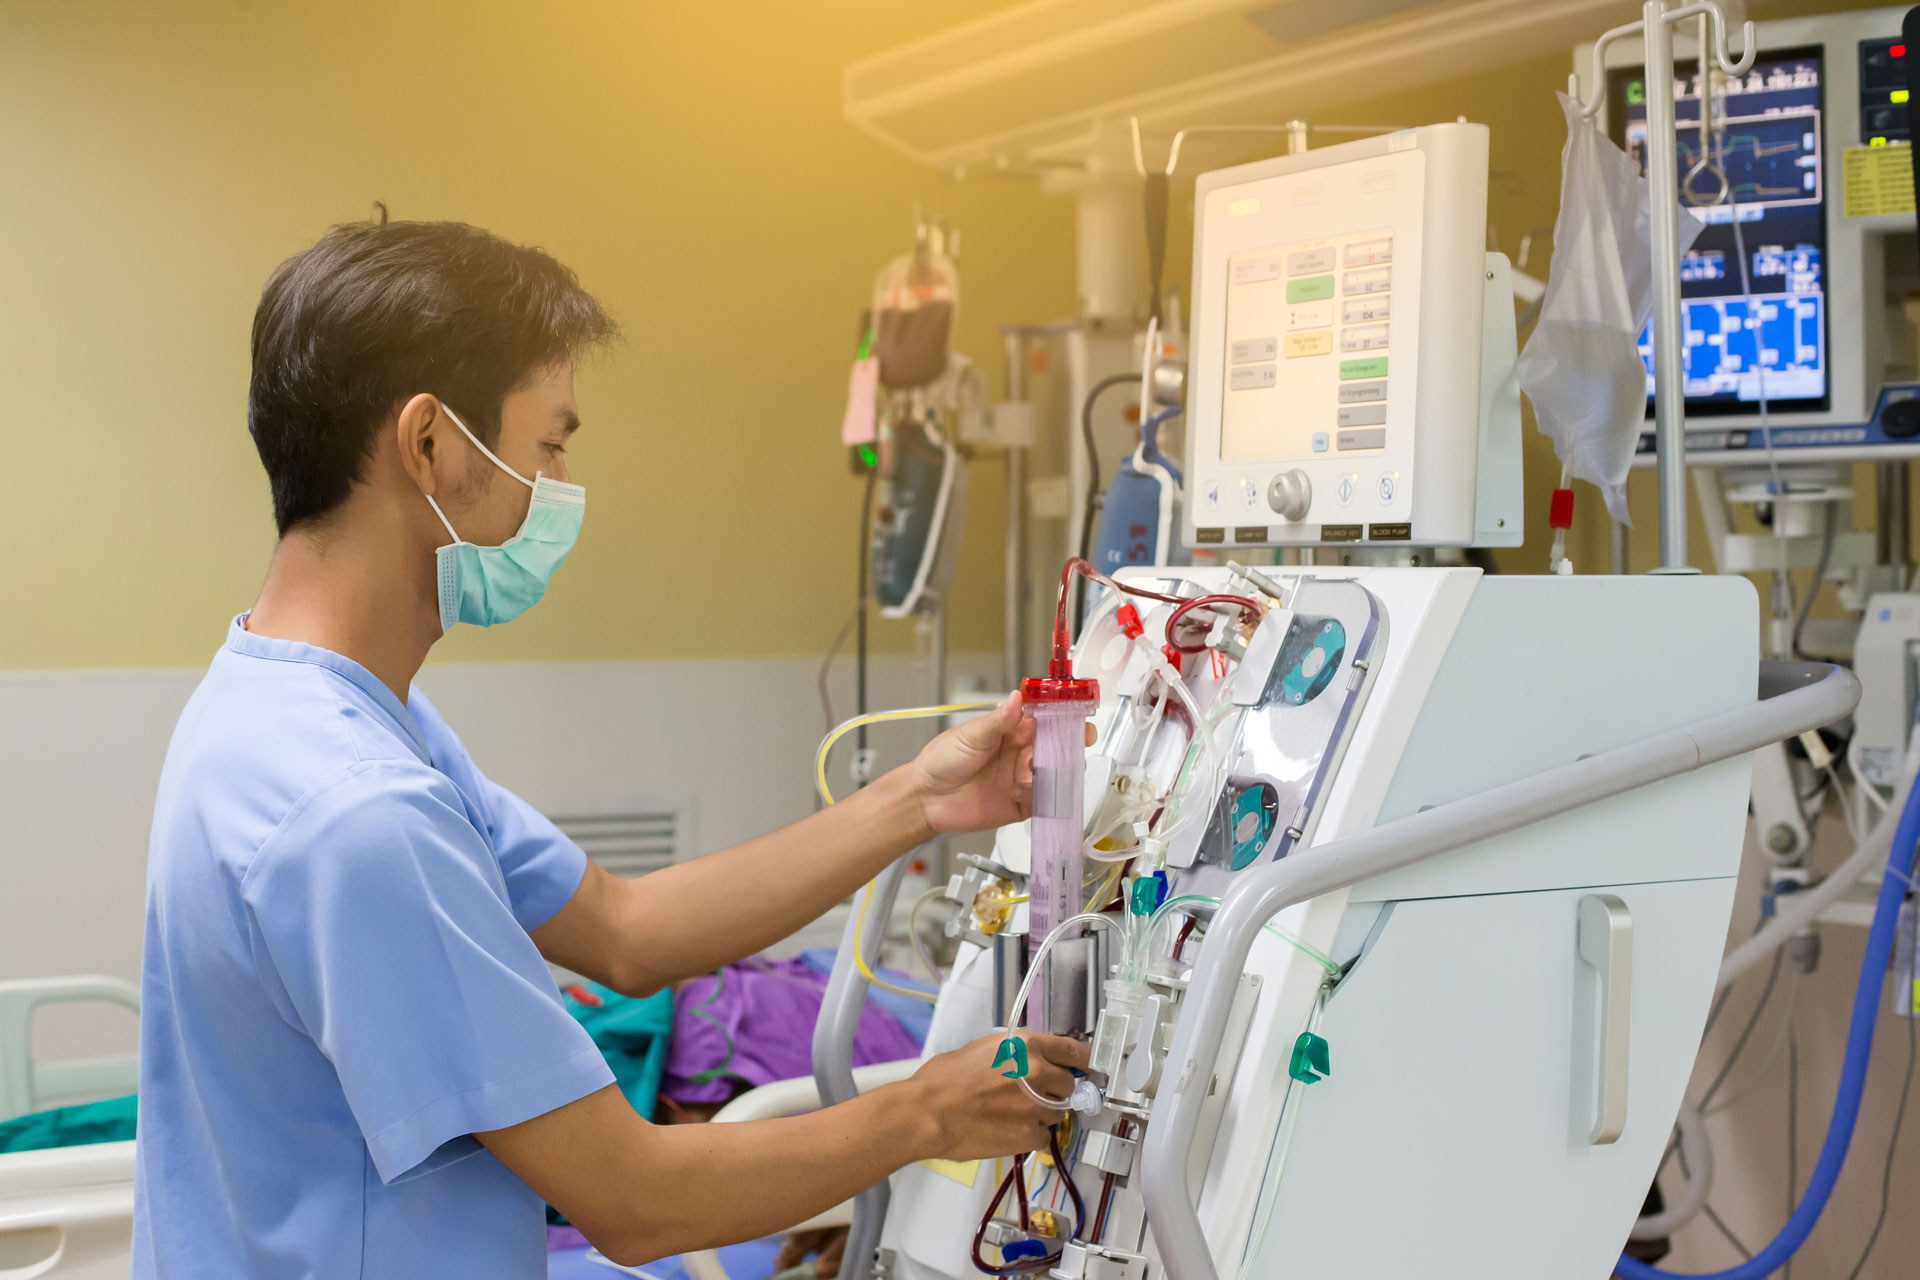
I dealt with a situation where a patient had a graft with a thrill that felt weaker than the previous week but still passed the standard checkpoint. The pre-treatment exam asked for a thrill presence checkmark, and the chart showed a documented thrill. On paper the patient was fine. The thrill was weaker and localized to the upper segment instead of diffuse along the entire access site. I flagged it before cannulation, the nurse ran a quick ultrasound, and they found a significant stenosis that could have caused a clot-down later that week if we had started the line without investigating. That kind of vigilance does not come from a textbook. It comes from the pattern recognition you develop after running assessments on the same patient multiple times over several weeks. Machine operation is straightforward once you have done it a few dozen times. The Fresenius 5008 and the Baxter Dialoge are the two systems you will encounter most often. Setup time drops from about twenty minutes to under eight once you stop second-guessing the circuit priming steps. The training covers the standard priming sequence, anticoagulation setup, blood line connection, and alarm response protocols. The part they do not always emphasize is how to triage alarms. A high venous pressure alarm and a monitor malfunction alarm look similar at first. One means there is a real blood flow problem. The other means a transducer is dirty or a tube is kinked. The difference matters when you are running three rooms. Patient monitoring and vital sign tracking are mostly procedural but technically demanding in practice. You take pre, intra, and post treatment vitals. You watch for intradialytic hypotension, cramping, and nausea. The training gives you target ranges and escalation thresholds. What it does not give you is a sense of how to spot a problem brewing before the numbers change. A patient who is pale, clutching their stomach, and quiet during treatment is often crashing before their blood pressure drops below the alarm threshold. That observation skill is something you pick up on the floor, not in a classroom.
The parts of training that are harder than they look
Needle insertion and dressing changes get the most attention in programs because they are hands-on skills. Cannulation technique, dressing application, and bleeding management are the mechanical tasks you practice on manikins first and real patients later. The needle gauge, angle, and recannulation rules matter. Most programs will have you practice using a silicone pad and then move to live patients under supervision. The learning curve is steep in the first two weeks and then levels out quickly. If you have prior phlebotomy experience, you will adapt faster. If you do not, budget extra time for the clinical portion. Infection control is another area where the gap between training and practice shows up. Hand hygiene, glove use, mask requirements, and machine disinfection protocols are all tested, but the actual discipline comes from watching someone competent model the behavior every shift. The CDC guidelines are clear, but the daily reality involves patients who forget their masks, spills that happen between scheduled cleanings, and the time pressure of running on a tight schedule. The training tells you what to do. The habits come from repetition and a unit culture that enforces the rules. Documentation is where a lot of new technicians struggle. The EHR systems used by most dialysis centers track weight changes, dialysis dose, blood pressure trends, medications given, and adverse events. You enter this data during and after each shift. The training will walk you through the interfaces, but the real issue is accuracy and timeliness. Skipping a field or entering an approximate weight can trigger compliance flags during audits. I have seen charts corrected days later because the original entry had a transcription error from a patient scale reading. Double-checking the decimal point on dry weight entries is not optional. It matters for ultrafiltration calculations and for the monthly QA review.
Get the Full Details

What the training will not prepare you for
Large hemodialysis units run at a pace that most classroom settings cannot replicate. A technician on a six-station float may be responsible for set-up, initiation, and ongoing monitoring across all rooms simultaneously. The training assumes a controlled environment with a preceptor nearby. The actual job rarely offers that level of oversight after your first month. You will be expected to handle routine situations independently and escalate correctly when something feels off. That transition is where some people stall out. The ones who adapt usually do so by leaning on the charge nurse and building a mental checklist for common scenarios. There is also the issue of scope of practice boundaries. A certified PCT can take vitals, insert needles, run machines, and respond to basic alarms. You cannot adjust anticoagulation orders, manage central line infections, or interpret lab trends beyond reporting them. Some employers will push you toward those gray areas, especially in smaller clinics with limited nursing coverage. The training itself does not always make these boundaries explicit enough. You need to know what falls outside your role and when to step back. Violating scope is a termination-level offense and a patient safety risk.
Choosing a program that will actually help you
Look for programs with substantial hands-on clinical hours, preferably in an active hemodialysis unit rather than an observation-only setting. CCI and NHA certifications are widely accepted. Some states require additional coursework or licensure, so check your local regulations before enrolling. Employer-sponsored programs can be a good deal, but verify the post-certification commitment requirements. Several chains ask for a one- to two-year retention period, and breaking that agreement usually means owing the training cost back. If you are starting from zero and need flexibility, an online didactic component paired with in-person clinical hours is the most common path. Programs like the NHA CHT preparation course and the CCI CET exam prep materials are widely used. You will still need a clinical site that accepts externs. If your current employer cannot provide that, community health centers and smaller dialysis providers sometimes partner with training programs to fill slots.
What you should do after certification
Certification gets you hired. Competence keeps you employed. The first ninety days matter more than anything you read in a manual. Focus on building speed and accuracy in your routine tasks before taking on extra responsibilities. Ask questions early. Most units have a preceptor or a lead tech who is willing to help if you show up willing to learn. Document everything carefully. Charts are audited regularly, and errors accumulate quickly if you do not catch them in real time. Track your own progress. Keep a simple notebook of difficult cases, alarm patterns you encountered, and access sites that required extra attention. This is not glamorous work, but it accelerates your learning curve faster than any refresher course. Three months in, you will start recognizing patterns that your training covered only in theory. That is when the job stops feeling like a series of tasks and starts feeling like a coherent workflow. The downside of this training pathway is that the ceiling is low unless you pursue further education. A PCT certification does not lead directly to nephrology nursing or advanced practice roles. If you plan to stay in dialysis long-term, consider pairing the PCT work with an LPN or RN program. The clinical experience you gather as a technician will make the nursing curriculum easier to absorb, and many employers offer tuition assistance for that path. If you intend to remain a PCT, you can still advance through senior technician roles, lead tech positions, and trainer assignments. The pay bump is modest but real.
The training itself is manageable. The work is not. You will deal with difficult veins, anxious patients, equipment failures, and understaffed shifts. The certification proves you can perform the core duties. Everything else depends on how you handle the daily reality of the unit.