How Diaphragmatic Breathing Actually Works in Speech Therapy
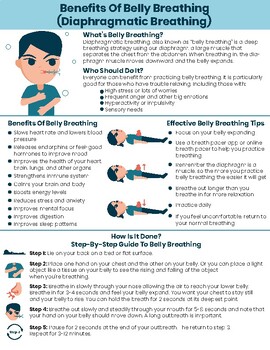
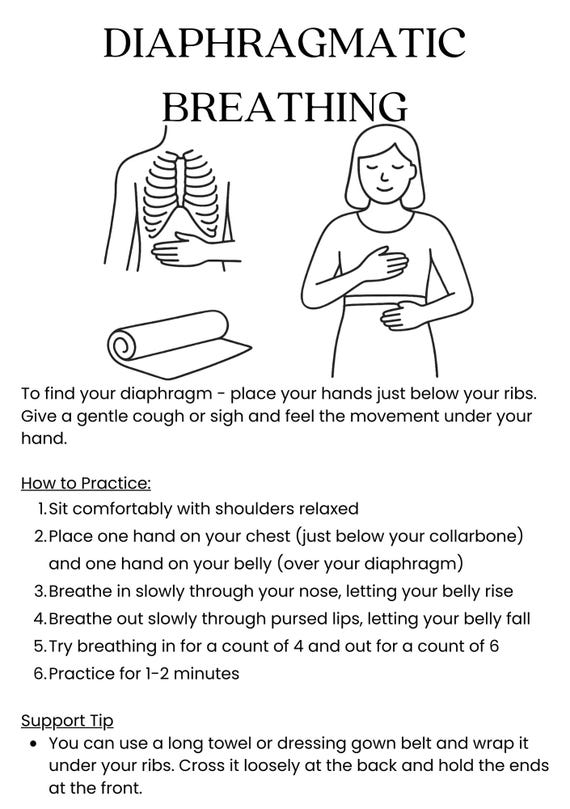
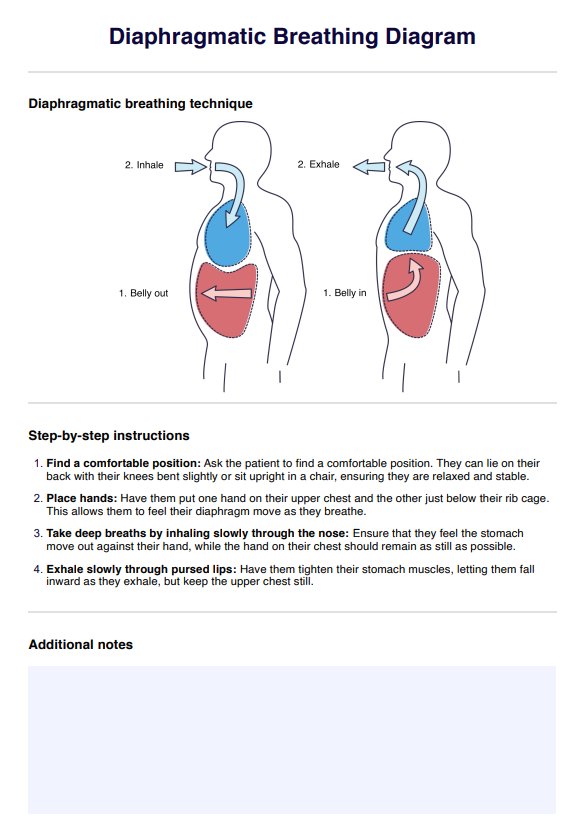
Most people breathe into their chest when they're nervous or talking for a while. That's the default pattern for a lot of clients I see. The diaphragm should be doing the work, but it rarely is without some retraining. Diaphragmatic Breathing Speech Therapy is basically teaching the body to reverse that habit so airflow supports vocal output instead of fighting against it. The mechanics are straightforward on paper. You inhale through the nose and your belly pushes out, not your shoulders. The diaphragm contracts downward, creating negative pressure that pulls air into the lungs. Then on the exhale, you control that release to drive speech. Simple concept. Getting a patient to actually do it without thinking about it is the part that takes time.
Starting with Diaphragmatic Breathing Speech Therapy in Practice
I usually begin by having the client lie flat on their back with a light book on their stomach. Not a heavy one. Just enough weight to give tactile feedback. They breathe in for four counts, watch the book rise, and breathe out for six counts while the book lowers. We do this for about five minutes before anything else. This alone tells me whether they have any capacity for diaphragmatic control or if we're dealing with a deeply entrenched thoracic pattern. Once they can do that lying down, we move to sitting, then standing, then actually speaking while maintaining the pattern. Each transition is where things tend to fall apart. I've had adults who could do it perfectly on their back but immediately jumped back to shoulder breathing the moment they stood up and tried to say anything. That's normal. It just means the new pattern hasn't been integrated into the motor system yet. The core exercise involves a sustained "sss" sound on exhalation. Start with ten seconds. Build to thirty over several sessions. I track progress by timing, not by how good it sounds. The breath support comes first, vocal quality follows later. If a client obsesses over tone early on, they tense up and everything slows down.
There's a variation I use that most therapists don't mention. It's called the strugghiuta technique, originally from Italian operatic tradition. It trains controlled exhalation under resistance and works well for clients who hyperventilate or speak in gasps. You'd be surprised how many people with stuttering or psychogenic voice disorders benefit from it.
Get the Full Details

What Actually Goes Wrong
Here's the thing nobody puts in a textbook. Some clients physically cannot access their diaphragm on command. I had a case last year with a 34-year-old woman who had complete vocal fold paralysis on one side and chronic anxiety. She'd been doing diaphragmatic breathing exercises for months through another therapist and made zero progress. She was forcing her abdomen out manually by contracting her rectus abdominis instead of letting the diaphragm descend. That created more tension, not less. The workaround was to stop all breathing exercises entirely for two weeks and focus on posture and rib cage mobility instead. We used myofascial release on her intercostals and scalenes, did gentle spinal decompression, and had her practice sighing naturally while seated in a supported chair. Once the mechanical restriction lifted, the diaphragm started responding on its own. She could do proper belly breathing within three sessions after that. Sometimes the problem isn't that they can't learn the technique. Sometimes the problem is that their body is too tight to execute it. Another common failure point is treating this as purely a breathing issue. It's not. It's a speech disorder intervention, which means coordination with phonation has to happen from the start. If a client learns diaphragmatic breathing in isolation and then tries to layer speech on top months later, they've basically built two separate motor programs that don't communicate. Stack them together earlier than you think you should.
Session Structure That Actually Moves People Forward
A typical session runs about 45 minutes. First ten minutes are breath awareness without speech. Then fifteen minutes of exercises combining breath and phonation. The last twenty minutes apply it to speech tasks that are relevant to the client's actual life. Reading aloud, phone calls, ordering coffee, whatever their trigger situations are. I skip the generic tongue twister stuff unless it's specifically helping with breath groups. I use a simple metronome app set to 60 beats per minute and have clients match their exhale to the tick. It sounds gimmicky but it gives the nervous system an external anchor. Without it, people either rush or drag inconsistently. With it, they start building predictability. After about six sessions most clients can maintain a steady 4-second exhale without the metronome. Progress notes should include breath duration in seconds, voice quality rating on a scale of 1 to 5, and which situations still cause regression. Numbers matter more than impressions here. "Getting better" means nothing on paper. "Increased from 8 seconds to 14 seconds over four sessions with mild stridor still present on high pitch" means something.
When Diaphragmatic Breathing Speech Therapy Won't Help
This approach doesn't fix structural issues. A shortened vocal fold, a neurological motor disorder like apraxia, or significant hearing loss won't respond to breath training alone. I've seen therapists waste three months on clients who needed a referral for laryngeal surgery or a neurological workup instead. If a client shows no improvement after four consistent sessions, reassess. Don't just keep repeating the same exercise hoping it'll click eventually. Anxiety-driven hyperventilation is another scenario where pure diaphragmatic training hits a wall. The breathing pattern is secondary to the panic response. In those cases, cognitive behavioral strategies or even a psychiatric referral should come first. Breath work becomes counterproductive if the client is still in fight-or-flight mode. Their body will reject the technique on principle. Cost and accessibility are real constraints too. A full course of speech therapy with a licensed provider runs between $100 and $250 per session depending on location and insurance. Most people need eight to twelve sessions to see meaningful change. That's $800 to $3,000 out of pocket for a lot of families. I've had clients supplement with recorded exercises at home, but only if they have basic self-awareness and discipline. For kids or clients with cognitive delays, home practice without professional supervision usually produces inconsistent results at best.
Tools and Resources
I don't endorse any specific app, but the ones worth looking into are the ones that give visual biofeedback. A phone camera facing upward while the client lies down works for free. You can watch the belly rise and fall in real time. Cheap respiratory trainers with a moving piston or ball are available online for around $20 to $40 and give a simple visual indicator of inhalation depth and exhalation speed. For clients who want structured practice between sessions, there are printable worksheets that break down the progression from supine breathing to sustained phonation to connected speech. I keep a stack in my office and hand them out at session two. The ones that include a daily log with checkboxes for breath duration and situation-specific practice tend to get used. The elaborate ones with graphics and QR codes sit untouched. Research references for anyone who wants to dig deeper include studies from the Journal of Speech Language Pathology and the American Journal of Speech-Language Pathology. The evidence base for diaphragmatic breathing in speech therapy is moderate at best. It works for some populations and certain conditions more than others. Don't treat it like a universal solution.
The technique itself isn't complicated. The application is. Pay attention to what the body is actually doing, not what you think it should be doing. Adjust when something isn't working. Move on to other approaches if this one stalls after a reasonable trial period.