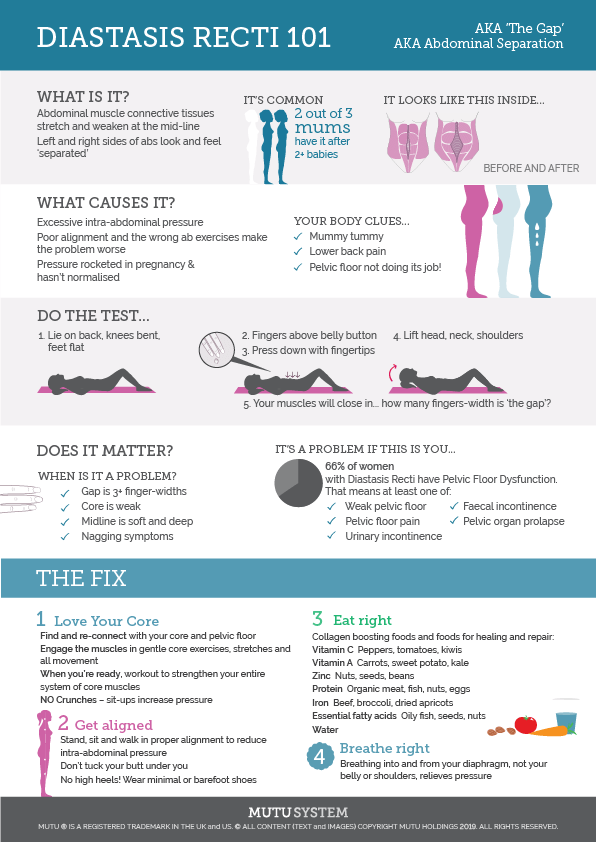
The Problem with Most Diastasis Recti Programs
Most people bounce into a postnatal phase after pregnancy and get handed a generic core workout they saw on social media. Crunches. Planks. Some random ab machine at the gym. They feel like they're doing something, but the gap between their abdominal muscles isn't closing. Sometimes it gets worse. The rectus sheath is a connective tissue structure, not a muscle, and it doesn't respond to the same stimulus as your biceps. It responds to intra-abdominal pressure management and targeted eccentric loading of the transverse abdominis. Everything else is noise. A proper Diastasis Recti Training Program needs to start with assessment, not exercise selection. You need to know the depth of the diastasis in finger-widths and centimeters, where the separation is worst (above, at, or below the umbilicus), and what your pelvic floor is doing when you bear down. I once had someone come to me with a 5cm gap at the epigastric region, and she was six weeks postpartum doing Russian twists with a medicine ball. The gap wasn't shrinking because every twist was pushing her abdominal contents forward through the weakened linea alba. She stopped the Russian twists, spent eight weeks on diaphragmatic breathing with gentle anterior pelvic tilt hold, and came back with a 3cm gap that finally started responding to load.
Building a Diastasis Recti Training Program From Scratch
Start with the breathing mechanics. This is non-negotiable and most programs skip it because it seems too simple. Lie on your back with knees bent. Place one hand on your sternum and the other on your lower ribs. Inhale through your nose and let the lower ribs expand laterally and posteriorly. You should feel your hands move outward, not up. Exhale fully through pursed lips, and on the last third of the exhale, draw your lower abdomen inward and upward toward your spine without pulling your ribs down. That is the activation of the transverse abdominis. Hold that engagement for five seconds, then release. Do ten reps. That is your Day 1 warmup. Once you can do that without compensating by hiking your glutes or flattening your low back into the floor, add the bridge. The dead bug is next, but only after bridges are solid. The key detail on bridges: don't lift through your low back. Initiate from the hamstrings and glutes, keeping a gentle tuck in the pelvis. If you feel it in your lumbar spine, you're doing it wrong. Hold the top for three breaths. Lower with control. Eight reps. From there you progress to modified planks on your knees, then bird dogs, then Pallof presses if you have a cable machine or resistance band. The Pallof press is important because it's a true anti-rotation exercise, and people with diastasis tend to rotate or shear through their midline under load because the transverse abdominis isn't bracing correctly. The Pallof forces that bracing pattern in a controlled way. Three sets of eight per side, holding each rep for two seconds at full extension.
Things to avoid. Sit-ups and any movement that involves spinal flexion under load. Full planks before you can maintain a neutral spine with the transverse abdominis engaged for sixty seconds. Heavy deadlifts and squats before you can manage your breath under compression. And if you notice coning or doming along your midline during any exercise, stop immediately. That dome is a sign that the intra-abdominal pressure is pushing against the linea alba rather than being managed by the deep core muscles. That's the exact opposite of what you want. Frequency matters more than intensity here. Three sessions per week, twenty minutes each, is better than one brutal ninety-minute session. The connective tissue needs recovery time. It remodels slowly. I've seen people try to do daily ab workouts and end up with a larger gap because the tissue never got a chance to adapt. Give it four days between sessions and track the measurements weekly at the same time of day with the same method. The truth no one wants to hear is that severe cases over 5cm with significant functional impairment often need more than a training program. If you have symptoms like urinary incontinence, pelvic organ prolapse, or chronic lower back pain alongside a wide gap, working through a physical therapist who specializes in pelvic floor rehabilitation is the route to take. Some cases require surgical intervention. A program alone won't fix everything, and pretending otherwise wastes months of your time.
Get the Full Details

Consistency is what actually moves the needle. Not the most advanced exercise in the program, not the heaviest weight, just showing up and doing the fundamentals correctly for twelve to sixteen weeks and watching the numbers change.




