Managing Flares Is Mostly About Timing, Not Perfection
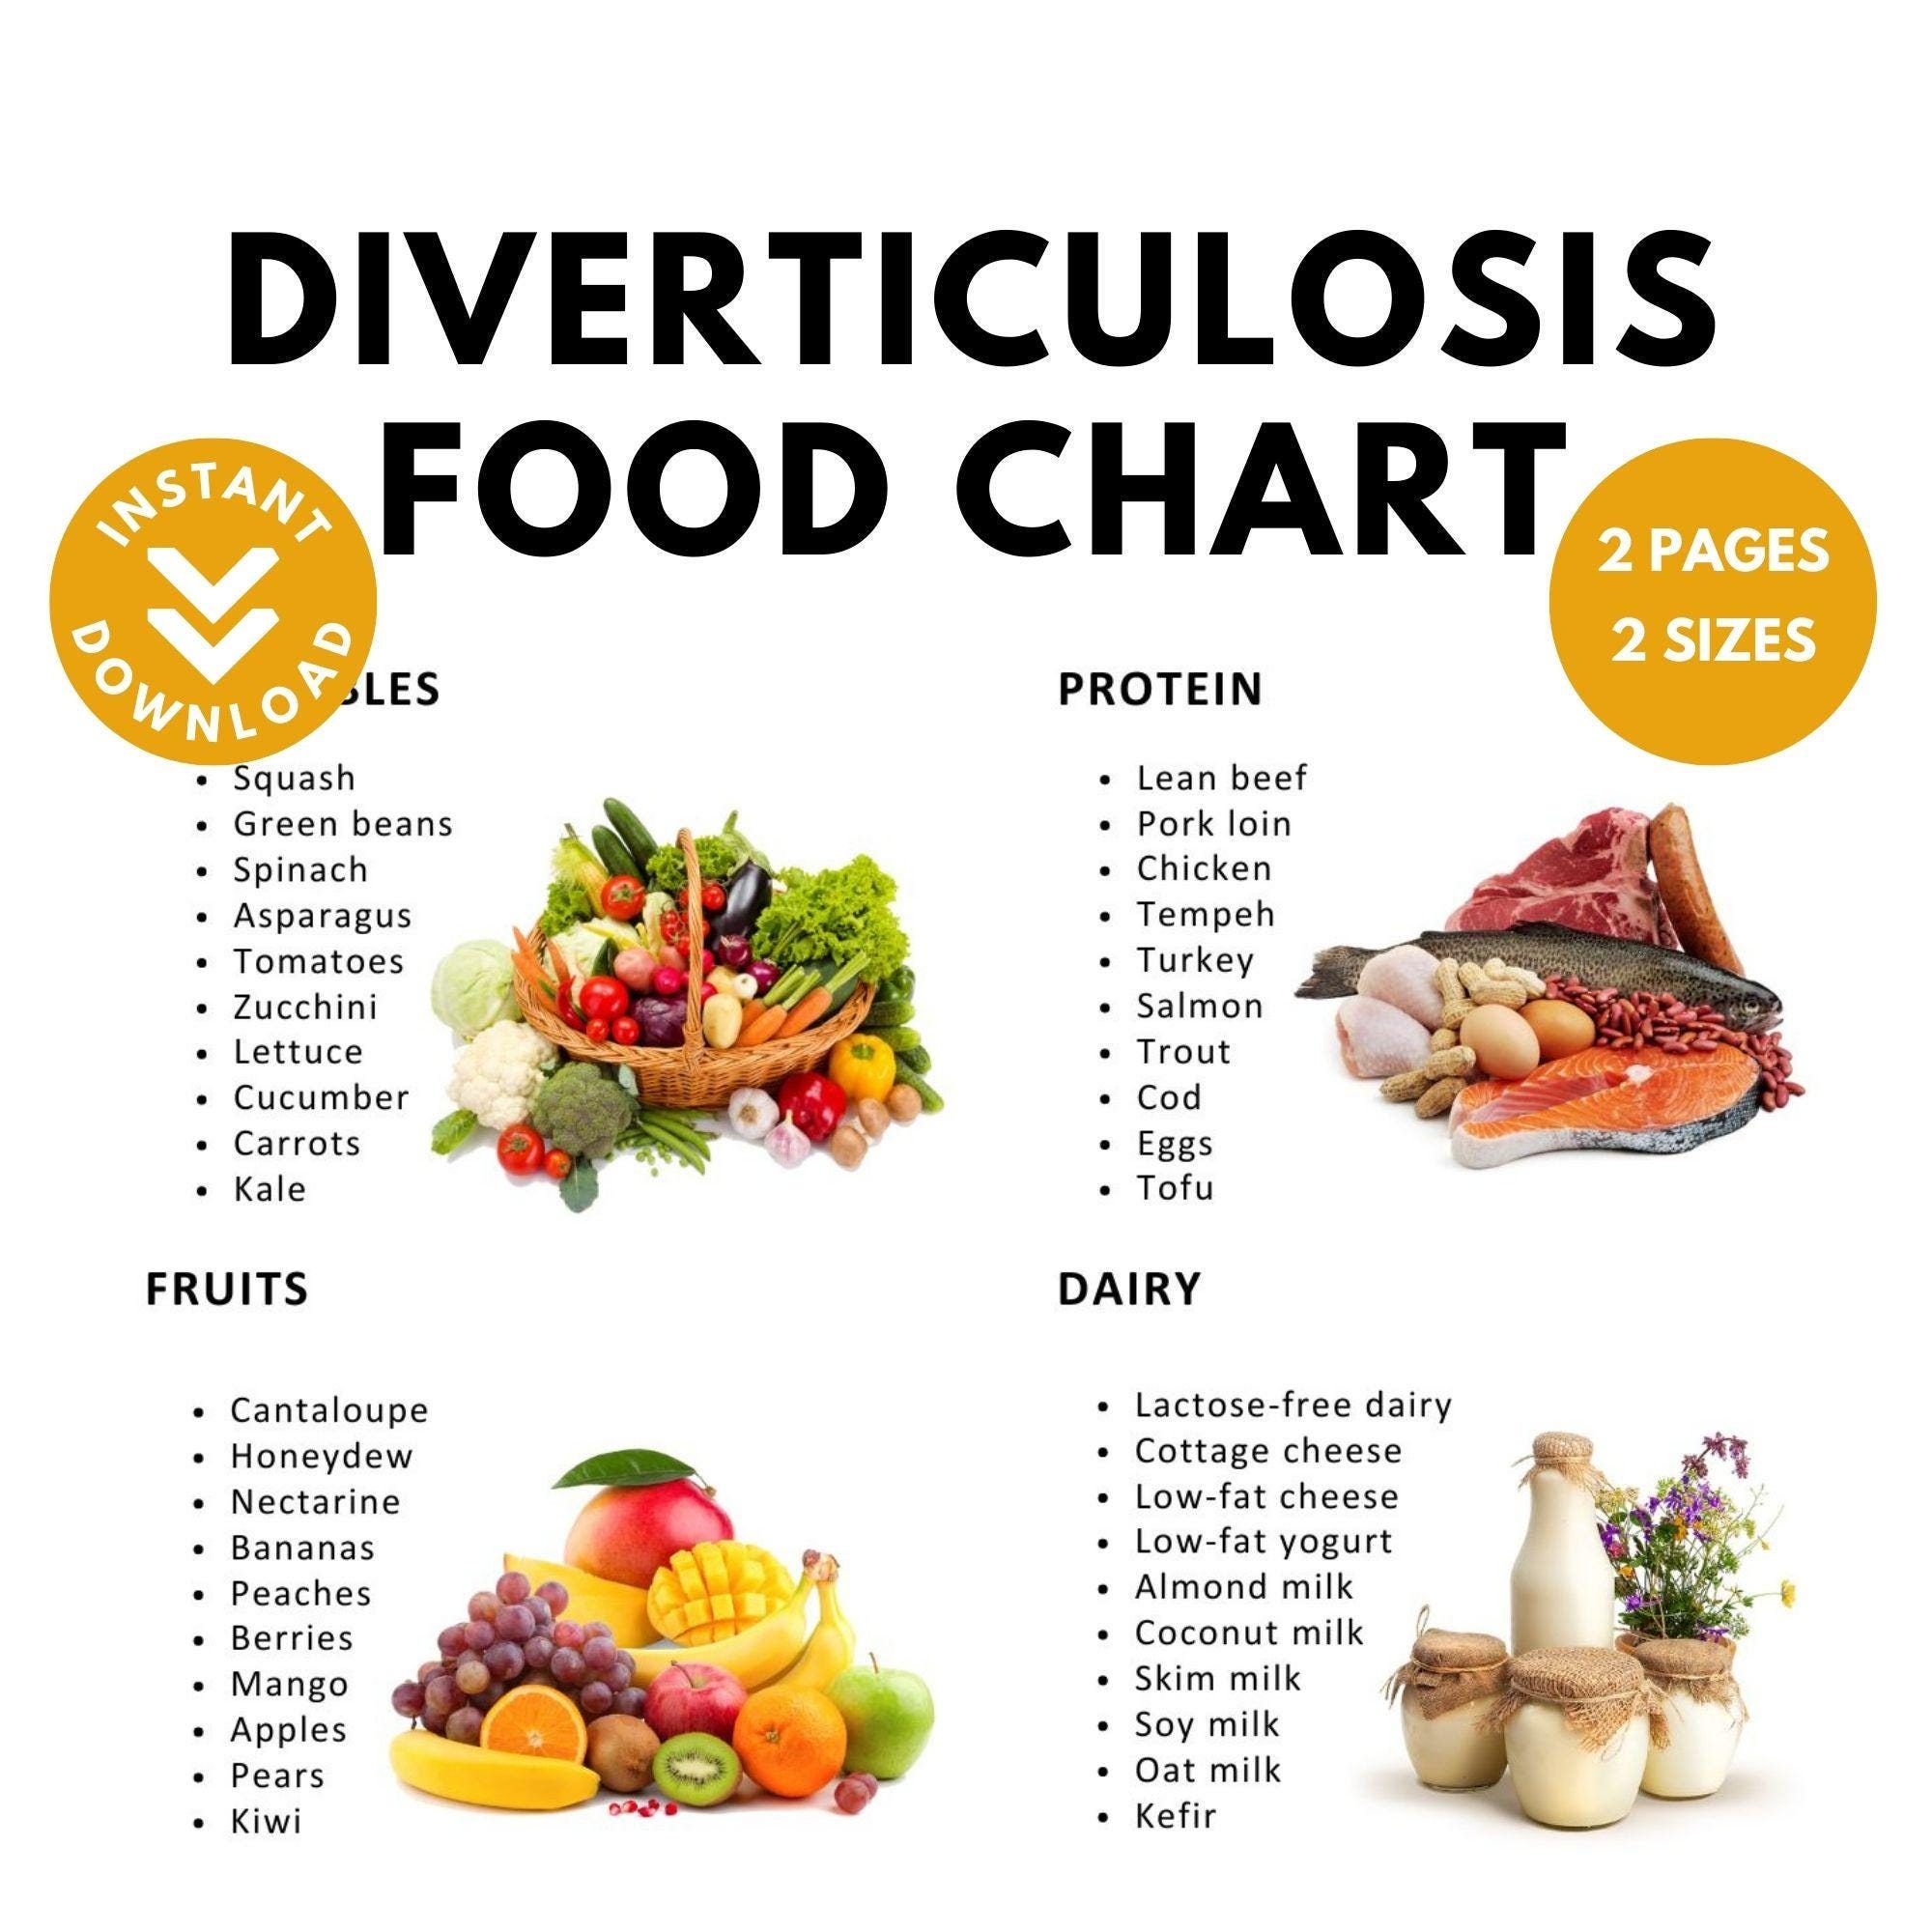
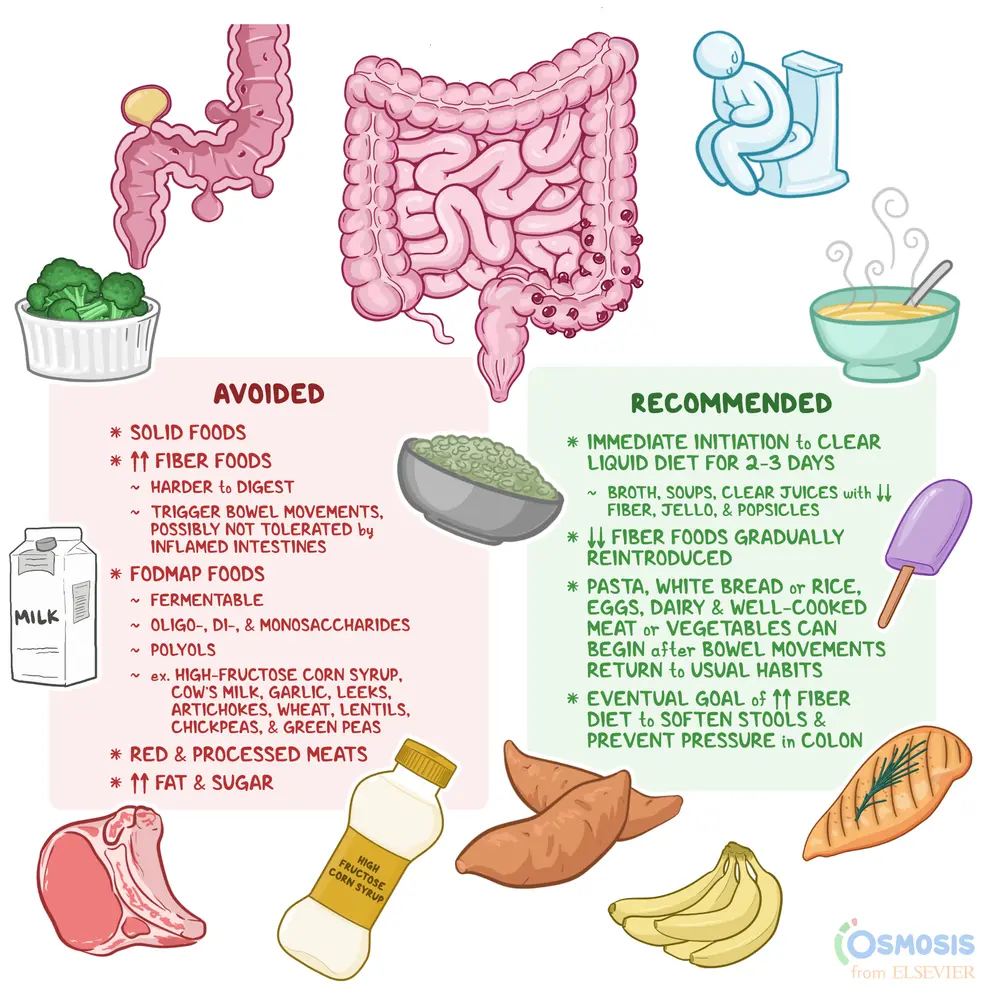
When you are dealing with both ulcerative colitis and diverticulitis, your nutrition strategy shifts depending on whether you are in active inflammation or maintaining remission. These are two different conditions affecting different parts of the colon, and they do not always respond to the same dietary approach at the same time. The Diet For Colitis And Diverticulitis is less about finding one perfect meal plan and more about learning how to read your own body during different disease phases. During a flare-up, the goal is reducing mechanical irritation to the colon lining. That means going low-residue. No raw vegetables, no whole grains, no nuts or seeds. I eat white rice, boiled potatoes, skinless chicken, and well-cooked carrots. Bananas and applesauce provide some soluble fiber without the roughage. I keep meals small and frequent instead of three large ones because a distended colon is an irritated colon. I spent about ten days on a liquid or near-liquid diet during a bad diverticulitis flare a few years back. Bone broth, strained vegetable soup, oral rehydration solutions. It was miserable but it shut the inflammation down faster than I expected. The key was not stretching out the strict phase. As soon as my white blood cell count dropped and the pain subsided, I began introducing soft solids within forty-eight hours. Waiting too long on a zero-residue diet actually delays recovery because your gut microbiome starves without any substrate.
One thing nobody warns you about: iron supplementation during flares. Most over-the-counter iron compounds irritate the GI tract. I switched to iron bisglycinate about a gram per day alongside food and it was far better tolerated. The cheaper ferrous sulfate variants are basically sandpaper on an already inflamed mucosa.
Transitioning Back to Remission Eating
Once symptoms stabilize for at least two weeks, you slowly reintroduce fiber. This is where most people mess up. They go from zero fiber to a salad bowl overnight because some health blog told them to "feed your microbiome." That is how you trigger another flare. Add one new fiber source per week. Start with soluble fiber sources like oats, psyllium husk, and peeled cooked squash. Insoluble fiber from raw greens and bran can come later if you tolerate it. For diverticular disease specifically, there is a persistent myth that you should avoid all nuts, seeds, and popcorn forever. Current gastroenterology guidelines from the American Gastroenterological Association no longer support that blanket restriction for people who are not in an acute diverticulitis phase. The evidence simply does not hold up. I started eating small amounts of popcorn during remission about four years ago with no issues. Everyone is different though, and if you notice a pattern with any food, remove it regardless of what any guideline says. Fish oil at two grams of combined EPA and DHA daily has helped me reduce the frequency of mild flares. It is not a treatment for an active episode, but as a maintenance supplement the anti-inflammatory effect is measurable in my experience. I track my hs-CRP levels alongside my symptom diary and the correlation is noticeable.
Get the Full Details

Practical Gaps in the Standard Advice
The standard low-residue diet leaves people deficient in magnesium and potassium within a few weeks. Both minerals support smooth muscle function in the colon, and depletion can actually worsen spasms. I add a magnesium glycinate supplement at night and eat mashed sweet potatoes for potassium. These are not glamorous solutions but they prevent the secondary problems that make flares worse. Another thing: probiotics are hit or miss. Some strains like Saccharomyces boulardii have decent evidence for reducing diarrhea frequency in IBD patients. Others, particularly those with high streptococcal content, have been linked to bacteremia in immunocompromised patients. If you try a probiotic, pick one with transparent strain labeling and start with half the recommended dose. Your gut is not going to thank you for a sudden microbial invasion.
What This Approach Cannot Do
No diet will stop a flare caused by an autoimmune cascade unrelated to food. I have had flares after stressful travel periods or infections where my diet was perfect and I still went symptomatic for weeks. Food manages symptoms and reduces triggers. It does not cure underlying immune dysregulation. If you are relying solely on diet to control moderate-to-severe ulcerative colitis, you are taking a risk. Dietary management works best alongside medical treatment, not as a replacement. Diverticulitis prevention through diet is also more variable than most sources admit. Fiber reduces intracolonic pressure, which theoretically helps, but individual anatomy and microbiome composition matter enormously. Some people tolerate high fiber brilliantly. Others develop significant bloating and gas that feels worse than the constipation fiber is meant to fix. Track your own response instead of following someone else's protocol blindly.
The Bottom Line on Long-Term Management
The Diet For Colitis And Diverticulitis is not a static thing. It changes based on your disease activity, your nutritional status, and your tolerance thresholds. Keep a symptom and food log. Not a vague one — actual entries with timestamps, portions, and symptom severity on a one to ten scale. After three months you will see patterns you would otherwise miss. The patterns are usually obvious in hindsight but invisible in real time. Working with a registered dietitian who actually understands inflammatory bowel disease makes a measurable difference. Most general nutritionists are not trained in the specifics of colitis and diverticular management. I found mine through a gastroenterologist referral and the adjustment to my supplementation alone prevented two potential flare-ups in six months. It is worth the copay.